
Toprol Xl
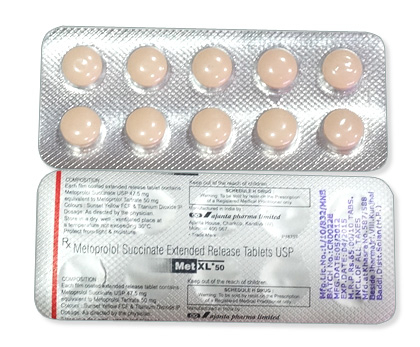
Toprol Xl
- In some pharmacies in Australia you can buy toprol xl without a prescription, often with discreet delivery across Australia; however, toprol xl (metoprolol succinate) is officially prescription-only and should ideally be used under medical supervision.
- Toprol XL (metoprolol succinate) is used for hypertension, angina, heart failure and after myocardial infarction; it is a selective beta‑1 adrenergic receptor blocker that reduces heart rate, myocardial contractility and cardiac workload.
- Usual dosage: adults commonly start 25–100 mg once daily for hypertension (maintenance 100–200 mg once daily); angina/post‑MI often 100 mg once daily (up to 200 mg); heart failure typically starts at 12.5–25 mg once daily and is titrated up to 200 mg once daily as tolerated.
- Form of administration: oral extended‑release tablets (commonly 25 mg, 50 mg, 100 mg and 200 mg); take once daily with or immediately after a meal.
- Onset time: some effect on heart rate and blood pressure may be seen within 1–4 hours after an ER dose, though full therapeutic effects on blood pressure or angina control can take several days as steady state is reached.
- Duration of action: the extended‑release formulation provides roughly 24‑hour coverage, allowing once‑daily dosing.
- Alcohol warning: avoid excessive alcohol — it can increase drowsiness, enhance blood‑pressure lowering and exacerbate side effects such as dizziness and fainting; use alcohol with caution while taking toprol xl.
- The most common side effect is fatigue; other frequent adverse effects include dizziness, slow heart rate (bradycardia), headache, gastrointestinal upset and sleep disturbances.
- Would you like to try toprol xl without a prescription?

Basic Toprol XL Information
- INN (International Nonproprietary Name): Metoprolol succinate (also known as Metoprololum in some regulatory texts).
- Brand Names Available In Australia: not specified.
- ATC Code: C07AB02 — Selective beta‑blocker, beta‑1 adrenergic receptor antagonist.
- Forms & Dosages: Extended‑release tablets 25 mg, 50 mg, 100 mg and 200 mg; capsule extended‑release common in North America; immediate‑release tartrate tablets (Lopressor) typically 50 mg and 100 mg; oral solution is rare and used for paediatric titration.
- Manufacturers In Australia: not specified.
- Registration Status In Australia: not specified.
- OTC / Rx Classification: Prescription‑only (Rx) in all markets.
Latest Research Highlights (Australian + Global)
Patients and prescribers often ask whether metoprolol succinate remains a first‑line beta‑blocker in 2024 and beyond.
Recent randomized trials, registry analyses and meta‑analyses through 2022–mid‑2024 place metoprolol succinate among first‑line beta‑1 selective agents when a beta‑blocker is indicated.
Australian cardiology registries and hospital audit reports from 2020–2024 report continued use of extended‑release metoprolol for post‑myocardial infarction secondary prevention and chronic heart failure.
Pooled real‑world outcomes in these registry analyses show mortality and major morbidity endpoints for metoprolol succinate comparable to bisoprolol and carvedilol in similar patient cohorts.
Safety signals in pharmacovigilance data emphasise bradycardia, symptomatic hypotension and fatigue as the most frequent adverse events.
Rare adverse reports submitted to national systems note bronchospasm in patients with reactive airways disease and occasional exacerbation of peripheral vascular disease.
Comparative effectiveness reviews published between 2022 and 2024 generally conclude that choice of beta‑blocker should be guided by the patient’s comorbidity profile rather than expecting a clear mortality advantage for one agent over another.
Research gaps identified in 2023–2024 include head‑to‑head randomised trials comparing metoprolol succinate with newer agents such as nebivolol, and long‑term adherence studies in rural and Indigenous Australian populations.
A recommended display for clinicians is a concise trial and registry summary table showing year, population, comparator agent and primary outcome, plus a brief TGA adverse‑event trend note highlighting bradycardia and bronchospasm.
Clinical Effectiveness In Australia
Clinicians want to know how metoprolol succinate performs against local PBS prescribing patterns and TGA surveillance.
The extended‑release succinate formulation, often referenced as Toprol XL or metoprolol succinate ER, matches guideline expectations for blood pressure control, angina symptom relief and selected heart failure cohorts when titrated to target doses.
PBS item and hospital prescribing audits show standard maintenance ranges align with international practice, with many patients stabilising on 100–200 mg once daily for hypertension and angina.
Heart failure patients usually start at lower doses and are carefully titrated, consistent with accepted heart failure regimens.
TGA adverse‑event reporting mirrors global findings with bradycardia and symptomatic hypotension predominating among reported events.
In primary care and cardiology outpatient settings, effectiveness depends on ensuring the succinate extended‑release formulation is used for chronic therapy and not substituted with tartrate immediate‑release preparations.
Switching between branded Toprol XL and generic metoprolol succinate ER is common in Australia due to supply and pricing, and pharmacists should monitor patients for changes in heart rate, blood pressure and tolerability after a switch.
For practical clinic audits, tracking maintenance dose bands, reasons for switching brands and TGA adverse‑event reports provides a useful snapshot of real‑world effectiveness.
Indications And Expanded Uses
Patients often ask what conditions Toprol XL is officially approved for and when off‑label use might be considered.
Core indications align with international approvals and include hypertension, stable angina, heart failure with reduced ejection fraction (HFrEF) and secondary prevention after myocardial infarction.
Australian prescribers commonly choose the extended‑release metoprolol succinate formulation for once‑daily chronic therapy because of its steady plasma profile.
Immediate‑release metoprolol tartrate, branded as Lopressor in some markets, is generally reserved for acute or short‑term uses rather than chronic management.
Off‑label applications seen in specialist practice include rate control for certain supraventricular arrhythmias, migraine prophylaxis in selected patients and cautious use in performance‑related anxiety where beta‑blockade is appropriate.
Use in paediatrics is off‑label and managed case‑by‑case with specialist dosing and monitoring.
Before assuming PBS subsidy for a specific indication, check ARTG/TGA records and the current PBS schedule for registration and listing details.
Quick Reference — On‑Label Versus Off‑Label:
- On‑Label: Hypertension; stable angina; HFrEF; post‑MI secondary prevention.
- Off‑Label (Specialist Use): Certain arrhythmias for rate control; migraine prophylaxis; selected anxiety indications; paediatric use with specialist oversight.
Composition And Brand Landscape
Many customers want to know what exactly is in the tablet and how brands differ.
The active ingredient is metoprolol succinate, the INN for the extended‑release preparation used for chronic once‑daily dosing.
The ATC classification is C07AB02, which identifies metoprolol as a selective beta‑1 adrenergic receptor antagonist.
Available formulations relevant to Australian sourcing include extended‑release tablets in 25 mg, 50 mg, 100 mg and 200 mg strengths.
Immediate‑release metoprolol tartrate tablets exist but are pharmacokinetically different and not interchangeable with succinate ER for chronic therapy.
Brand names encountered internationally include Toprol XL and many generics labelled metoprolol succinate ER, with packaging varying between blister packs and bottles and differing tablet counts.
Global manufacturers and suppliers include AstraZeneca, Par Pharmaceuticals, Sandoz, Pfizer, HEXAL, EG and Zentiva, while local Australian suppliers and wholesalers vary by distributor.
Pharmacies in Australia may stock both branded Toprol XL and generics; substitution often follows PBS listings and supply availability.
| Formulation | Common Strengths | Typical Pack Sizes / Australian Supply Notes |
|---|---|---|
| Metoprolol Succinate ER Tablet | 25 mg, 50 mg, 100 mg, 200 mg | Blister packs or bottles; substitution between brands occurs depending on PBS listing and supply. |
| Metoprolol Tartrate IR Tablet | 50 mg, 100 mg | Immediate‑release; used for acute settings; not a direct chronic therapy substitute for ER succinate. |
Succinate ER versus Tartrate IR — simple definitions:
- Succinate ER: Extended‑release metoprolol for once‑daily chronic therapy (Toprol XL / generics).
- Tartrate IR: Immediate‑release metoprolol for shorter‑term or acute dosing (Lopressor).
Contraindications And Special Precautions
Safety is a top concern, especially for older patients and those in remote communities.
Absolute contraindications where metoprolol succinate should not be used include severe bradycardia below 45 bpm, second‑ or third‑degree AV block without a pacemaker, sick sinus syndrome, uncompensated heart failure, cardiogenic shock and severe peripheral arterial circulatory disorders.
Known hypersensitivity to metoprolol or excipients is also an absolute contraindication.
Relative contraindications that need close monitoring include asthma and COPD because of bronchospasm risk, diabetes due to masking of hypoglycaemia symptoms, thyrotoxicosis, psoriasis flare potential and moderate hepatic impairment.
Elderly Australians commonly need lower starting doses and slower titration due to increased risk of bradycardia and symptomatic hypotension.
For Indigenous and remote populations, ensure culturally safe communication about signs of bradycardia, hypotension and breathlessness, and arrange reliable local follow‑up.
Pregnancy is a specialist decision with category C classification; use only where benefit justifies the risk.
Practical Pharmacist Counselling Checklist:
- Confirm contraindications and current heart rate before dispensing.
- Advise patients to report dizziness, fainting or worsening breathlessness immediately.
- Warn about masking of hypoglycaemia signs in people with diabetes.
Dosage Guidelines
Patients frequently ask what dose is appropriate for their condition and how to titrate safely.
For hypertension in adults the usual starting dose is between 25 mg and 100 mg once daily, with maintenance commonly 100–200 mg once daily.
For stable angina a typical starting dose is around 100 mg once daily and maintenance can be up to 200 mg once daily as tolerated.
For heart failure start low, often 12.5–25 mg once daily, and titrate gradually to effect with an upper tolerated dose up to 200 mg once daily.
Post‑MI secondary prevention frequently targets a maintenance dose of around 100 mg once daily and may increase toward 100–200 mg dependent on tolerance.
Elderly patients should begin at the lower end of recommended ranges and be closely monitored for bradycardia and hypotension.
Hepatic impairment often requires dose reduction because metoprolol is primarily metabolised by the liver, while renal impairment usually does not require adjustment though monitoring is sensible at higher doses.
Paediatric use is off‑label and requires specialist dosing and supervision.
| Indication | Initial Dose | Typical Maintenance Dose |
|---|---|---|
| Hypertension (Adults) | 25–100 mg once daily | 100–200 mg once daily |
| Angina Pectoris | ~100 mg once daily | Up to 200 mg once daily |
| Heart Failure (HFrEF) | 12.5–25 mg once daily, start low | Titrate up to 200 mg once daily as tolerated |
| Post‑MI | 100 mg once daily | 100–200 mg once daily |
Practical note: take the extended‑release tablet with or immediately after a meal to improve absorption and reduce gastrointestinal upset.
Interactions Overview
Drug interactions are a frequent reason for pharmacist‑led checks at dispensing.
Clinically relevant interactions include additive negative chronotropic effects with verapamil, diltiazem and digoxin, which raise the risk of bradycardia or AV block.
Combining metoprolol with other antihypertensives can amplify hypotensive effects and requires blood pressure monitoring.
CYP‑mediated interactions can alter metoprolol levels because it is metabolised by hepatic pathways; potent CYP inhibitors or inducers may require review and monitoring.
MAO inhibitors and certain antidepressants can potentiate hypotension or other effects, so co‑prescribing should be reviewed.
Alcohol may worsen hypotension and sedation, and patients should be cautioned about drinking while initiating or uptitrating therapy.
For older Australians with polypharmacy, check the e‑health medications list and local dispensing history to catch red‑flag combinations.
| Drug / Class | Effect | Pharmacy Recommendation |
|---|---|---|
| Verapamil / Diltiazem | Additive bradycardia, risk of AV block | Avoid combination or monitor heart rate closely; specialist review recommended. |
| Digoxin | Enhanced bradycardia | Monitor ECG and pulse; advise dose review. |
| CYP inhibitors (strong) | Increased metoprolol levels | Consider dose reduction or monitoring. |
Cultural Perceptions And Patient Habits
How patients view Toprol XL affects adherence and supply choices in Australia.
Many Australians treat generics as cost‑sensitive alternatives and rely on pharmacists and GPs for substitution advice and PBS navigation.
Rural and remote consumers face access hurdles such as intermittent pharmacy stock, longer waits for titration and greater reliance on telehealth for repeat prescriptions.
Indigenous communities emphasise culturally safe communication and may prefer consistent brand supply to reduce confusion when medicines change.
Online pharmacies and telehealth services have expanded access but can introduce continuity‑of‑care challenges when brands or formulations switch between providers.
Cost and PBS subsidy status are a decisive factor for ongoing therapy, particularly for concession card holders and those on multiple chronic medicines.
Common adherence barriers reported by patients include fatigue, dizziness and concerns about sexual dysfunction, and targeted pharmacist counselling can help manage these concerns.
| Setting | Access Factors | Suggested Pharmacy Intervention |
|---|---|---|
| Urban | Ready access to multiple pharmacies and telehealth | Offer medicine‑use reviews and brand substitution counselling. |
| Rural / Remote | Intermittent stock, longer supply times | Arrange longer prescriptions, local follow‑up and culturally safe counselling. |
Availability And Pricing Patterns
Patients frequently ask where to buy Toprol XL and whether the PBS will help with costs.
Toprol XL and generics labelled metoprolol succinate ER are routinely stocked across major Australian chains and community pharmacies, though supply can vary between brands.
PBS listing typically gives the lowest out‑of‑pocket cost for eligible patients, and many metoprolol succinate products are PBS‑listed as generics.
Private prescriptions and online pharmacy prices vary between retailers and chains, and price‑sensitive patients often compare offers from large discount chains and independent pharmacies.
Rural stockouts may temporarily increase private costs or require substitution with an alternative generic presentation.
Note for customers: in our online pharmacy, toprol xl is available without a prescription, with discreet delivery to Australia in 5–14 days.
| Channel | Pros | Cons |
|---|---|---|
| PBS‑subsidised community pharmacy | Lowest cost for eligible patients; pharmacist counselling available | May require in‑person collection; brand may vary with supply. |
| Online pharmacy / Telehealth | Convenience; home delivery | Watch for correct ER succinate formulation and ARTG approval; continuity of care matters. |
Checklist For Verifying Supply:
- Confirm product is metoprolol succinate extended‑release, not tartrate immediate‑release.
- Check PBS listing for subsidy status if cost is a concern.
- Document brand and batch on dispensing to aid reconciliation after switches.
Comparable Medicines And Preferences
When might a prescriber choose a different beta‑blocker over metoprolol succinate?
Alternatives commonly used in Australia include atenolol, bisoprolol, carvedilol, nebivolol and labetalol, each with specific strengths and situations.
Bisoprolol and carvedilol are often preferred in HFrEF in some guideline recommendations, while carvedilol provides combined alpha and beta blockade useful in certain hypertensive patients.
Nebivolol is sometimes chosen for patients where metabolic effects are a concern.
Pros of metoprolol succinate include once‑daily ER dosing, widespread availability and clinician familiarity.
Cons include risk of bradycardia, potential to mask hypoglycaemia and significant hepatic metabolism leading to interaction potential.
| Drug | Indication Strengths | Pros | Cons |
|---|---|---|---|
| Metoprolol Succinate | Hypertension, angina, HFrEF, post‑MI | Once‑daily ER, widely available | Bradycardia risk; hepatic metabolism interactions |
| Bisoprolol | Hypertension, CHF | Strong CHF evidence in some trials | Still requires monitoring for bradycardia |
| Carvedilol | CHF, hypertension | Alpha‑blockade helpful in some patients | May cause more peripheral vasodilation |
Decision Checklist For Switching:
- Assess comorbidities (asthma, diabetes, hepatic disease).
- Review evidence for the indication (e.g., HFrEF preference may favour bisoprolol or carvedilol).
- Consider dosing convenience and patient adherence when recommending once‑daily metoprolol succinate.
FAQ
Can I stop Toprol XL suddenly?
No.
Do not cease metoprolol abruptly; taper under GP guidance to avoid rebound tachycardia or worsening angina.
Will metoprolol affect my diabetes?
It can mask hypoglycaemia symptoms, especially tachycardia.
People with diabetes should monitor glucose closely and discuss dose or monitoring plans with their clinician.
Is Toprol XL covered by PBS?
Many metoprolol succinate products are PBS‑listed as generics, but check the current PBS schedule and your GP’s script to confirm subsidy eligibility.
Can I drive while starting it?
Be cautious.
Dizziness and fatigue are common early side effects and can impair driving until you know how the medicine affects you.
For further consumer information refer to TGA and PBS patient leaflets provided with your medicine or on their websites.
Guidelines For Proper Use
Pharmacists and prescribers need a short, practical checklist to ensure safe dispensing and counselling.
Confirm the formulation: metoprolol succinate ER must be used for chronic once‑daily therapy and is not interchangeable with metoprolol tartrate IR without clinician oversight.
Advise patients to take the ER tablet with or immediately after a meal to improve absorption and reduce gastrointestinal upset.
Explain common side effects such as fatigue, dizziness, sleep disturbance and slow heart rate, and instruct patients to seek help for syncope, severe breathlessness or very slow pulse.
Missed‑dose advice: take as soon as remembered unless it is almost time for the next dose; do not double up on doses.
Storage: keep at room temperature (20–25°C) in original packaging away from moisture.
Reconciliation when switching brands: document formulation and batch, and reinforce monitoring for changes in heart rate, blood pressure and tolerability.
Monitoring during titration: check blood pressure and pulse regularly and review other medicines for interactions such as verapamil, diltiazem and digoxin.
For rural and telehealth patients arrange reliable local follow‑up and ensure PBS script continuity if subsidy matters to the patient.
- Pharmacist Counselling Checklist: Verify formulation; review contraindications; counsel on side effects; confirm PBS status; advise on missed doses and storage.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Hobart | Tasmania | 5-9 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Darwin | Northern Territory | 5-9 days |
| Gold Coast | Queensland | 5-7 days |
| Newcastle | New South Wales | 5-7 days |
| Wollongong | New South Wales | 5-9 days |
| Geelong | Victoria | 5-9 days |
| Townsville | Queensland | 5-9 days |
| Broome | Western Australia | 5-9 days |