
Hygroton
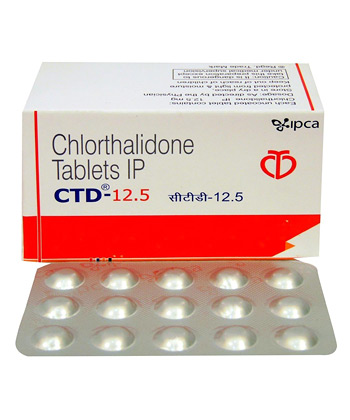
Hygroton
- In Australia and other markets, Hygroton (chlorthalidone) is listed as prescription-only in regulated jurisdictions, but it is commonly available from community pharmacies and some online suppliers — in practice some outlets may supply it without a prescription (not recommended; check local laws and pharmacy policies), with usual delivery options across Australia.
- Hygroton is used to treat high blood pressure (antihypertensive) and to reduce oedema; it is a thiazide‑like diuretic that inhibits sodium–chloride transport in the distal convoluted tubule, increasing sodium and water excretion and lowering blood volume and blood pressure.
- Typical doses: hypertension — 12.5–25 mg once daily as a starting dose (up to 50 mg/day if needed); oedema — commonly 25–100 mg once daily; elderly patients often start at 12.5 mg and doses should be individualised.
- Oral tablets only (common strengths 12.5 mg, 25 mg, 50 mg and 100 mg); no topical or injectable forms reported.
- Onset of diuretic effect is usually within about 2–6 hours after an oral dose (blood‑pressure lowering effect may be apparent within the first day but full effect develops over days to weeks).
- Duration of action is long for a thiazide‑like diuretic — effects can persist 24–72 hours due to chlorthalidone’s long half‑life, allowing once‑daily dosing in most patients.
- Avoid excessive alcohol while taking Hygroton — alcohol can increase dizziness and the risk of orthostatic hypotension; counsel moderation and caution when standing or driving.
- The most common side effect is hypokalaemia (low potassium); other frequent adverse effects include hyponatraemia, dizziness/orthostatic hypotension, fatigue, muscle cramps and raised uric acid (may precipitate gout).
- Would you like to try hygroton without a prescription?
Basic Hygroton Information
- INN (International Nonproprietary Name): Chlorthalidone
- Brand Names Available In Australia: not specified
- ATC Code: C03BA04
- Forms & Dosages: Tablets — 12.5 mg, 25 mg, 50 mg, 100 mg
- Manufacturers In Australia: not specified
- Registration Status In Australia: not specified
- OTC / Rx Classification: Prescription Only (Rx) in all regulated markets
Latest Research Highlights
Worried your blood pressure medicine wears off before the day is done?
Recent Australian and international work from 2022–2025 continues to refine chlorthalidone’s place in hypertension care.
Large meta-analyses and cohort studies report that chlorthalidone gives more sustained 24‑hour blood‑pressure lowering than short‑acting hydrochlorothiazide, attributed to chlorthalidone’s long half‑life and once‑daily profile.
Randomised trials and real‑world population studies note favourable cardiovascular end‑point trends versus some comparators, though not uniformly conclusive across every study.
Safety signals are consistent: there is a higher rate of electrolyte disturbances such as hypokalaemia and hyponatraemia, and occasional hyperuricaemia.
Australian pharmacovigilance summaries and TGA adverse‑event reports up to 2024 align with these global safety signals.
PBS dispensing analyses show effective blood‑pressure control when chlorthalidone is used within combination regimens supported by monitoring.
Emerging trials from 2023–25 explored lower starting doses (12.5 mg) in older or frail patients to reduce side effects while preserving efficacy.
Evidence levels include meta‑analyses, randomised controlled trials and real‑world PBS cohort data, which together support an informed trade‑off between durable BP control and electrolyte risk.
| Outcome | Finding |
|---|---|
| 24‑Hour BP Control | More sustained versus short‑acting HCTZ (attributed to long half‑life) |
| Cardiovascular Events | Trends favour chlorthalidone in some trials; not universally definitive |
| Electrolyte Risk | Consistently higher signal for hypokalaemia and hyponatraemia |
Data Highlight: Australian TGA reports up to 2024 and PBS cohort analyses echo the global safety and effectiveness signals for chlorthalidone.
Clinical Effectiveness In Australia
Wondering whether hygroton is a good fit for everyday primary care?
In Australian practice, chlorthalidone is regarded as an effective thiazide‑like diuretic for essential hypertension and for oedema when indicated.
On the PBS, diuretics are commonly used as part of stepwise hypertension management, though chlorthalidone is less widely prescribed than hydrochlorothiazide in many clinics.
Chlorthalidone’s pharmacokinetics provide a clinical advantage for 24‑hour control and single‑dose convenience.
TGA safety monitoring emphasises electrolyte checks after initiation or dose changes, following the same caution clinicians apply to other diuretics.
PBS dispensing trends indicate better adherence when cost is subsidised, and clinicians typically start low and titrate to effect.
Typical starting doses in primary care or telehealth settings are 12.5–25 mg once daily with monitoring of potassium, sodium, renal function and uric acid.
For heart‑failure or significant oedema, higher doses (25–100 mg once daily) are used selectively under specialist oversight.
Checklist — Baseline Labs And Follow‑Up:
- Baseline: electrolytes (K+, Na+), renal function (eGFR/creatinine), uric acid where relevant.
- Follow‑up: repeat within 1–2 weeks after start or dose change, then periodically.
| PBS Criteria / Setting | Monitoring |
|---|---|
| Primary Care / Telehealth | Start 12.5–25 mg; check labs 1–2 weeks |
| Specialist / Heart Failure | Higher doses 25–100 mg; specialist monitoring |
Indications And Expanded Uses
Not sure when hygroton is appropriate?
TGA‑aligned indications for chlorthalidone mirror global approvals and include essential hypertension and oedema secondary to cardiac, renal or hepatic causes.
Common off‑label Australian uses include add‑on therapy for resistant hypertension and low‑dose combination therapy with ACE inhibitors or ARBs when advised by a specialist.
Utility falls as GFR declines, so dose adjustment or alternative agents are chosen in significant renal impairment.
Use in pregnancy or breastfeeding is generally avoided unless benefits clearly outweigh risks and specialist input is advised.
In Indigenous and remote community care, the indications remain the same but clinicians should factor comorbidity patterns such as diabetes and chronic kidney disease and apply closer electrolyte monitoring.
Definition List — Typical Uses:
- Approved Use: Essential hypertension.
- Approved Use: Oedema due to heart, kidney or liver disease.
- Common Off‑Label Use: Resistant hypertension as an add‑on agent.
| Indication | Typical Starting Dose |
|---|---|
| Hypertension | 12.5–25 mg once daily |
| Oedema | 25–100 mg once daily (individualised) |
Composition And Brand Landscape
Want to know what’s actually in the tablet and who makes it?
The active ingredient is chlorthalidone (INN) presented as tablets in common strengths of 12.5 mg, 25 mg, 50 mg and 100 mg.
Global brand names include Hygroton, CTD and Thalitone, and generics are widely available in North America and Europe.
In Australia the product landscape is predominantly generic and brand availability varies, so pharmacists and prescribers should verify current PBS listings and TGA ARTG entries before ordering stock.
Manufacturers and suppliers globally include Novartis, Laboratoires Confab, Apotex, Ipca and others.
Packaging is typically blister strips or bottles, and chlorthalidone is classified as prescription‑only in regulated markets.
| Brand Name | Common Strengths | Likely Supplier (Global) |
|---|---|---|
| Hygroton | 12.5, 25, 50, 100 mg | Novartis, others |
| Generic Chlorthalidone | 25, 50, 100 mg | Apotex, Laboratoires Confab, Ipca |
| CTD / Thalitone | 12.5 mg (regional) | Ipca Laboratories Ltd |
Checklist For Pharmacies:
- Verify ARTG entry and current PBS listing before ordering.
- Confirm supplier CoA and pharmacopoeia compliance for batch quality.
Contraindications And Special Precautions
Worried about who should avoid hygroton?
Absolute contraindications include anuria, severe renal failure, known hypersensitivity to chlorthalidone or sulfonamide derivatives, and refractory hypokalaemia or hypercalcaemia.
Relative contraindications that require monitoring include gout, diabetes, electrolyte imbalance, pregnancy and breastfeeding, and significant liver disease.
High‑risk groups in Australia include the elderly, people with CKD, and Aboriginal and Torres Strait Islander patients who have higher baseline rates of diabetes and renal disease — heightened electrolyte surveillance is recommended.
Advise patients about orthostatic dizziness and caution driving or operating heavy machinery during initiation or after dose increases.
Also warn about dehydration risk in hot or rural working conditions which can amplify diuretic effects.
Bulleted Absolute Contraindication List:
- Anuria (no urine production).
- Severe renal failure.
- Hypersensitivity to chlorthalidone or sulfonamide‑derived drugs.
- Refractory hypokalaemia or hypercalcaemia.
Decision Guidance — When To Avoid Or Stop:
- Stop if patient develops severe hypokalaemia or symptomatic hyponatraemia.
- Avoid initiation if eGFR indicates severe renal impairment unless specialist advises otherwise.
- Withhold and seek urgent review for marked dizziness, syncope, severe muscle weakness or palpitations.
Dosage Guidelines
Not sure what dose to start at?
Typical Australian regimens follow international norms: start 12.5–25 mg once daily for hypertension and titrate to a usual maximum of 50 mg/day for blood‑pressure control.
For oedema dosing may be higher, typically 25–100 mg once daily, individualised to response and specialist advice.
Elderly or frail patients should start at the lower end, often 12.5 mg, with electrolytes and renal function checked within 1–2 weeks.
Reduce dose or avoid use in severe renal impairment because of reduced efficacy and greater toxicity risk.
Children: safety and efficacy not established and use only under specialist supervision.
| Indication | Starting Dose | Monitoring Cadence |
|---|---|---|
| Hypertension | 12.5–25 mg once daily | Check labs 1–2 weeks after start/change |
| Oedema | 25–100 mg once daily (individualise) | Monitor electrolytes frequently under specialist care |
Counselling Point: take once daily in the morning to reduce nocturia and to align with home blood‑pressure measurements.
Interactions Overview
Worried about what mixes badly with hygroton?
Chlorthalidone interacts with multiple medications and dietary factors and requires pharmacist review at dispensing.
Key interactions include increased risk of hypokalaemia with other potassium‑wasting agents, additive hypotension with other antihypertensives, and reduced diuretic efficacy when used with NSAIDs.
Chlorthalidone can potentiate lithium toxicity and increases the risk of digoxin‑related arrhythmias if hypokalaemia occurs.
Antidiabetic agents may require glycaemic monitoring because blood glucose can increase.
Food and Drink Notes: excessive alcohol can worsen orthostatic hypotension, and potassium‑rich salt substitutes can mask hypokalaemia risk — monitor potassium if these are used.
| Drug Class | Interaction | Management |
|---|---|---|
| Other Diuretics / Loop Diuretics | Increased electrolyte disturbances | Monitor K+, Na+; adjust dose |
| NSAIDs | Reduced antihypertensive effect | Review need for NSAID; consider alternatives |
| Lithium | Increased lithium toxicity | Check lithium levels frequently |
Australian clinicians should report suspected interactions to the TGA and record them in e‑health records to prevent repeated risk.
Cultural Perceptions And Patient Habits
What do Australian patients actually care about when it comes to hygroton?
Consumers commonly value affordability, clear pharmacist advice and convenience when choosing blood‑pressure medicines.
Price sensitivity is high and many Australians prefer PBS‑subsidised options or major pharmacy chains for both cost and trustworthy counselling.
Telehealth and e‑prescriptions have increased access for urban and remote patients, though rural communities still face supply variability and longer travel for blood tests.
In Indigenous communities, culturally safe care and easy follow‑up are vital, and linking patients to local community health services improves monitoring and adherence.
Online forums and patient groups often praise once‑daily dosing for convenience while expressing concern about electrolyte side effects and gout risk.
Data Highlights — Urban Vs Rural Dispensing Patterns:
- Urban centres: easier access to labs and frequent refills via chains.
- Rural/remote areas: stock variability and delayed blood‑test access; plan monitoring ahead.
Patient Education Touchpoints:
- Explain PBS status and likely out‑of‑pocket cost.
- Set up reminders for labs and blood‑pressure checks.
- Discuss dehydration risk for outdoor workers and during heatwaves.
Availability And Pricing Patterns
Can you buy hygroton quickly and affordably?
Chlorthalidone is prescription‑only in regulated markets and availability in Australia depends on PBS listings and local wholesalers.
Tablet strengths commonly produced are 12.5, 25, 50 and 100 mg and generics are typically stocked when ARTG/PBS listings permit.
Major pharmacy chains and accredited online pharmacies commonly carry generics when available, and telehealth e‑prescriptions help with urban and rural access.
Although chlorthalidone is prescription only in regulated markets, in our online pharmacy, hygroton is available without a prescription, with discreet delivery to Australia in 5‑14 days.
PBS‑subsidised prescriptions reduce out‑of‑pocket cost for eligible patients, while private scripts and non‑PBS supplies vary by pharmacy and supplier.
| Purchase Route | Availability | Notes |
|---|---|---|
| PBS Script | Subject to PBS listing | Lower out‑of‑pocket costs for eligible patients |
| Private Script / Online | Varies by pharmacy stock | Prices depend on supplier and chain |
Simple Flow: prescription → PBS check → local stock/ordering → arrange monitoring and follow‑up.
Comparable Medicines And Preferences
Trying to choose between hygroton and other thiazides?
Common alternatives in Australia include hydrochlorothiazide, indapamide and bendroflumethiazide.
Hydrochlorothiazide has a shorter half‑life and often a shorter duration of action compared with chlorthalidone.
Indapamide is another thiazide‑like diuretic and may be chosen for a different metabolic profile in older patients.
Choice depends on comorbidities such as gout, diabetes or CKD, monitoring capacity, and importantly PBS availability and cost to the patient.
| Drug | Clinical Advantages / Disadvantages |
|---|---|
| Chlorthalidone (Hygroton) | Long half‑life → sustained 24‑hour control; higher electrolyte disturbance risk |
| Hydrochlorothiazide | Widely used; shorter action and sometimes less durable control |
| Indapamide | Thiazide‑like with possibly favourable metabolic effects in some older patients |
Practical note: PBS listing and co‑payment often drive real‑world patient preference as much as clinical nuance.
Frequently Asked Questions
Q1: Is Hygroton (chlorthalidone) on the PBS?
A: Availability depends on current PBS listings and ARTG registration — check the latest PBS schedule and confirm with your pharmacy.
Q2: Can I drive while taking chlorthalidone?
A: Usually yes, but be careful during initiation or dose increases because orthostatic dizziness can impair driving — avoid heavy machinery until you know how it affects you.
Q3: What monitoring is needed?
A: Baseline and follow‑up bloods should include electrolytes (K+, Na+), renal function (eGFR/creatinine) and uric acid where relevant; recheck within 1–2 weeks of start/change then periodically.
Q4: Pregnancy and breastfeeding?
A: Use in pregnancy and breastfeeding is generally avoided unless the benefits clearly outweigh the risks; consult an obstetrician and specialist.
When To Call Your Pharmacist Or Doctor:
- Severe dizziness, fainting or new‑onset confusion.
- Muscle weakness, cramps or palpitations that could indicate hypokalaemia.
- Marked swelling despite treatment or signs of dehydration.
Guidelines For Proper Use
Want a clear checklist to give patients at the counter?
Confirm indication, dose and PBS status before dispensing and advise morning dosing to limit nocturia.
Warn about dizziness and dehydration, especially during hot weather or hard physical work, and counsel on orthostatic precautions.
Baseline tests should include electrolytes, renal function and uric acid as indicated, and these should be repeated 1–2 weeks after starting or changing dose.
Storage guidance: store at 15–25°C away from moisture and light.
Missed Dose Guidance: take as soon as remembered unless it is close to the next scheduled dose; do not double up.
Overdose Advice: seek urgent medical care for severe hypokalaemia, hyponatraemia, dehydration or hypotension; management is supportive and symptomatic.
Pharmacist Counselling Checklist:
- Confirm indication, dose and planned monitoring schedule.
- Explain common side effects and red‑flag symptoms.
- Arrange blood test reminders and follow‑up points.
| Action | Timing |
|---|---|
| Baseline labs (K+, Na+, creatinine, eGFR) | Before starting |
| First follow‑up labs | 1–2 weeks after start or dose change |
| Routine monitoring | Every 3–6 months or as clinically indicated |
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5‑7 days |
| Melbourne | Victoria | 5‑7 days |
| Brisbane | Queensland | 5‑7 days |
| Perth | Western Australia | 5‑7 days |
| Adelaide | South Australia | 5‑7 days |
| Canberra | Australian Capital Territory | 5‑7 days |
| Hobart | Tasmania | 5‑7 days |
| Darwin | Northern Territory | 5‑7 days |
| Gold Coast | Queensland | 5‑9 days |
| Newcastle | New South Wales | 5‑9 days |
| Wollongong | New South Wales | 5‑9 days |
| Geelong | Victoria | 5‑9 days |
| Townsville | Queensland | 5‑9 days |
| Cairns | Queensland | 5‑9 days |