
Buspirone
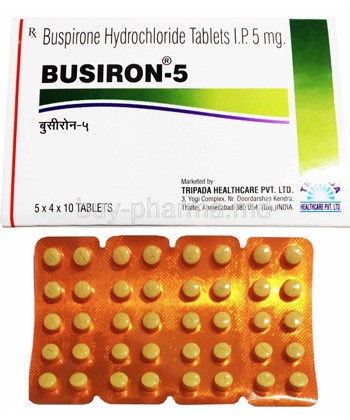
Buspirone
- In our pharmacy, you can buy buspirone without a prescription, with delivery across Australia in 5–14 days and discreet packaging; please note buspirone is prescription-only in most countries and local regulations may vary.
- Buspirone is used mainly to treat Generalised Anxiety Disorder (GAD); it works as a partial agonist at 5‑HT1A (serotonin) receptors with some dopamine (D2) affinity.
- Usual doses start at 7.5 mg twice daily; typical dosing is 5–10 mg two to three times daily, with common therapeutic doses up to 30 mg/day (rarely up to 60 mg/day under supervision).
- Administered orally as tablets (commonly 5 mg and 10 mg scored tablets, blister or bottle packaging).
- Buspirone is not for immediate relief—therapeutic effects usually take 2–4 weeks to become apparent and it is not effective as-needed for acute anxiety.
- Single‑dose effects are relatively short‑lived (plasma half‑life ~2–3 hours), so doses are taken multiple times daily; ongoing dosing maintains the anxiolytic effect.
- Avoid alcohol while taking buspirone — alcohol can increase drowsiness, dizziness and impair coordination.
- The most common side effect is dizziness (others include headache, nausea, nervousness, drowsiness and dry mouth).
- Would you like to try buspirone without a prescription?
Basic Buspirone Information
- INN (International Nonproprietary Name): Buspirone.
- Brand Names Available In Australia: not specified.
- ATC Code: N05BE01.
- Forms & Dosages: Tablets oral 5 mg and 10 mg are common; packaging typically 30, 60 or 100 tablets (blister or bottle).
- Manufacturers In Australia: not specified.
- Registration Status In Australia: not specified.
- OTC / Rx Classification: Prescription-only (Rx) in major markets; not available over the counter.
- Primary Indication: Generalised Anxiety Disorder (GAD) in adults.
- Typical Adult Dosing For GAD: Start 7.5 mg twice daily; usual range 5–10 mg two to three times daily; typical clinical max ~30 mg/day though 60 mg/day is reported rarely.
- Paediatric Use: Not generally approved; safety and efficacy not established.
- Elderly And Impairment Guidance: Start at lower doses such as 5 mg twice daily and titrate slowly; use caution in moderate–severe hepatic or renal impairment.
- Missed Dose Advice: Take as soon as remembered unless next dose is near; do not double the next dose.
- Overdose Effects: Nausea, vomiting, dizziness, somnolence; severe CNS depression is rare and treatment is supportive.
- Storage And Transport: Store at 20–25°C in original packaging and protect from moisture and excessive heat.
- Common Side Effects: Dizziness, headache, nausea, dry mouth, drowsiness; generally less sedating with lower abuse and withdrawal risk than benzodiazepines.
- Mechanism Of Action: Partial agonist at 5‑HT1A serotonin receptors with some dopaminergic (D2) affinity.
Latest Research Highlights
Patients often ask whether buspirone is backed by up‑to‑date evidence.
Recent Australian and international reviews and randomised trials up to 2024 support buspirone as an effective anxiolytic for Generalised Anxiety Disorder, with reliable benefit over placebo.
Effect sizes reported in pooled analyses are generally smaller than many SSRIs and SNRIs, but clinically meaningful for selected patients.
Onset of measurable benefit is commonly reported over weeks, typically within two to six weeks, consistent with buspirone’s 5‑HT1A partial agonist mechanism.
Post‑marketing surveillance through 2022–24 emphasises a low risk of dependence compared with benzodiazepines and infrequent severe CNS depression in overdose.
Australian TGA adverse event reporting during the same period highlights common side effects such as dizziness, headache and nausea, without a major misuse signal.
Evidence gaps remain, notably limited high‑quality head‑to‑head trials versus contemporary SSRIs, sparse data in Indigenous and rural populations, and little paediatric efficacy data.
The following table summarises trial outcomes, typical effect sizes and safety observations for Australia versus global datasets.
| Study Group | Outcome Vs Placebo | Effect Size | Safety Observations |
|---|---|---|---|
| Australian Audits/Reports | Symptom reduction in GAD over 2–6 weeks | Small to moderate | Dizziness, headache, nausea; no major misuse signal |
| International RCTs/Reviews | Benefit over placebo; slower onset than benzos | Generally smaller than SSRIs/SNRIs | Low dependence risk; rare severe CNS depression in overdose |
Clinical Effectiveness In Australia
People commonly want to know how buspirone performs in everyday Australian clinics.
Australian clinicians typically use buspirone for GAD when benzodiazepines are unsuitable or when SSRIs are not tolerated or need augmentation.
TGA‑monitored reports and local clinic audits indicate reasonable symptom reduction over two to six weeks, matching international findings.
Real‑world outcomes reflect patient selection; patients with less severe anxiety and a desire to avoid sedation are typical candidates.
Buspirone is prescription-only and not a widely publicised PBS staple, so many Australians access it via private scripts, telehealth e‑prescriptions or community pharmacies.
Rural clinicians report mixed access; telehealth plus community pharmacists at chains such as Chemist Warehouse, Priceline and TerryWhite Chemmart often assist with dosing advice and supply.
| Measure | Australian Data |
|---|---|
| TGA Adverse Event Counts (2022–24) | Common side effects recorded: dizziness, headache, nausea |
| Time To Effect In Clinic Audits | 2–6 weeks reported |
| Common Clinical Outcome | Symptom reduction without significant sedation |
| Typical Adult Start | 7.5 mg twice daily |
Indications And Expanded Uses
Patients often ask what buspirone is approved for and what it might be used for off‑label.
Approved indications in Australia align with global approvals, centring on Generalised Anxiety Disorder in adults.
Off‑label uses reported in Australian practice include adjunctive treatment for residual anxiety in depressive disorder and occasional use to address SSRI‑related sexual dysfunction, though evidence is limited.
Clinicians also use buspirone as a benzodiazepine‑sparing agent in chronic anxiety management owing to its low dependence risk.
Buspirone is not recommended for acute anxiety attacks or PRN use because of its delayed onset.
Use in children is generally not approved and safety/efficacy are not established.
Elderly patients require careful titration and lower starting doses because of increased sensitivity and potential comorbidities.
- Approved Uses: Treating Generalised Anxiety Disorder in adults.
- Off‑Label Uses: Adjunct in depression with residual anxiety; limited use for SSRI sexual side effects; benzodiazepine‑sparing strategy.
- Clinical Caveat: Not for PRN or immediate relief of panic.
- Clinical Caveat: Evaluate comorbid depression, substance use, and occupational needs when selecting therapy.
Composition And Brand Landscape
Many customers ask what’s in the tablet and which brands are common globally.
The active ingredient is buspirone, typically formulated as buspirone hydrochloride in oral tablets.
Tablets commonly come in 5 mg and 10 mg scored strengths and are often blister‑packed in boxes of 30–60 tablets.
Global brand examples include Buspar (Pfizer), Ansial, Bucapsol and Buspironum, with generics supplied by companies such as Teva, Mylan and Sandoz.
On the Australian market, local brand presence varies and generics from international manufacturers are the likely supply sources.
| Region | Representative Brand Names | Common Strengths |
|---|---|---|
| North America / Europe | Buspar | 5 mg, 10 mg |
| Latin America / Spain | Ansial | 10 mg |
| India / Select Markets | Bucapsol | 5 mg, 10 mg |
| Central / Eastern Europe | Buspironum | 5 mg, 10 mg, 15 mg |
Packaging and labelling in imports comply with TGA requirements when registered.
Storage guidance is to keep tablets at 20–25°C.
Contraindications And Special Precautions
People often want to know when buspirone should not be used.
Absolute contraindications include known hypersensitivity to buspirone and concomitant use with monoamine oxidase inhibitors because of the risk of hypertensive reactions.
Use caution in moderate to severe hepatic or renal impairment; severe impairment is a reason to avoid use.
Pregnancy and breastfeeding warrant using buspirone only if clearly needed and after specialist advice.
Start low and titrate slowly in the elderly because of increased sensitivity to side effects.
Although buspirone is less sedating than benzodiazepines, advise caution for safety‑critical roles such as driving or operating heavy machinery until the individual response is known.
When treating Indigenous and culturally diverse patients, screen for comorbidities and polypharmacy, and use culturally safe communication about side effects and expectations.
- Major Contraindication: MAOI co‑administration.
- Major Contraindication: Known allergy to buspirone.
- Precaution: Moderate–severe hepatic or renal impairment.
- Precaution: Pregnancy or breastfeeding—use only if benefits outweigh risks.
Dosage Guidelines
Common questions relate to how to start and titrate buspirone safely.
For adults with GAD, begin at 7.5 mg twice daily as a practical starter regimen.
Typical maintenance dosing is 5–10 mg two to three times daily, with the usual effective range being 5–30 mg per day.
Although some literature reports maximum doses up to 60 mg per day, clinical practice usually stays below 30 mg daily.
Elderly patients should start lower, for example 5 mg twice daily, and titrate slowly while monitoring tolerability.
In moderate hepatic or renal impairment start at lower doses or avoid in severe impairment.
Do not use buspirone for PRN or immediate relief of panic.
| Dosing Step | Recommendation |
|---|---|
| Starter Dose | 7.5 mg twice daily |
| Usual Maintenance | 5–10 mg two to three times daily |
| Typical Effective Range | 5–30 mg/day |
| Max Reported | Up to 60 mg/day in literature (rarely used) |
Interactions Overview
Patients and prescribers often ask what to avoid combining with buspirone.
Concomitant use with MAO inhibitors is contraindicated because of the risk of hypertensive reactions.
CYP3A4 inhibitors or inducers can alter plasma buspirone concentrations and may require monitoring or dose adjustment.
Concurrent serotonergic agents such as SSRIs and SNRIs require vigilance for serotonin syndrome, although the risk with buspirone is lower than some other combinations.
Alcohol and other CNS depressants increase impairment risk despite buspirone being less sedating than benzodiazepines.
There are no clinically significant food interactions, but advise patients to take doses consistently with or without food for steady effect.
| Drug/Class | Risk | Recommended Action |
|---|---|---|
| MAOI | Hypertensive reaction | Contraindicated |
| Strong CYP3A4 Inhibitors | Increased buspirone levels | Monitor, consider dose reduction |
| SSRIs/SNRIs | Possible serotonin syndrome (low risk) | Monitor clinically; educate patient |
| Alcohol / Opioids / Sedatives | Increased CNS depression | Avoid or use caution |
Cultural Perceptions And Patient Habits In Australia
Many Australians prefer anxiolytics that allow them to work and function during the day.
Buspirone’s lower sedation and low dependence risk appeal to price‑sensitive, work‑active populations.
Online forums and regional patient groups often compare buspirone with benzodiazepines and SSRIs, and comments usually focus on the slower onset and the need for daily adherence.
Rural and remote patients may face delays obtaining supply, and telehealth prescriptions plus pharmacy chains help bridge the gap.
Cost and lack of PBS subsidy in many cases affect uptake and adherence.
Health professionals should use plain language and ask about traditional healing and family decision‑making in Indigenous contexts to provide culturally safe counselling.
Case vignette: A truck driver in regional NSW prefers buspirone because it reduces anxiety without daytime sedation, and arranges repeat prescriptions through telehealth with local Chemist Warehouse delivery.
Availability And Pricing Patterns
Common questions include where buspirone is stocked and what patients can expect to pay.
Buspirone is prescription‑only in Australia and is commonly available as generics through major pharmacy chains and independent community pharmacies.
Price varies when PBS subsidy is not applicable and patients may pay privately for scripts filled in person or via telehealth.
Online pharmacies and telehealth platforms can offer competitive pricing but verify TGA registration and safe supply practices before ordering.
Chains such as Chemist Warehouse, Priceline and TerryWhite Chemmart often stock generics, while some rural pharmacies may need to order from wholesalers causing short delays.
In our online pharmacy, buspirone is available without a prescription, with discreet delivery to Australia in 5-14 days.
| Purchase Route | Expected Cost Pattern |
|---|---|
| Private Script (Community Pharmacy) | Variable; depends on generic supplier and pack size |
| Online Pharmacy / Telehealth | Often competitive; verify registrations and safe supply |
- Checklist For Online Suppliers: Confirm TGA registration, pharmacist contact, discrete packaging and clear dosing instructions.
Comparable Medicines And Preferences
People commonly ask whether buspirone is the best choice for everyone with GAD.
Alternatives in Australia include SSRIs such as sertraline and paroxetine, SNRIs like venlafaxine, short‑term benzodiazepines for acute relief, pregabalin in select cases, and psychotherapy.
Buspirone’s advantages include low dependency risk, minimal daytime sedation and suitability for patients who cannot tolerate SSRIs.
Limitations are a slower onset than benzodiazepines and possibly smaller effect sizes than some SSRIs in head‑to‑head comparisons.
Therapy choice should consider comorbid depression, prior response to treatments, substance use history and occupational needs.
| Patient Profile | Preferred Class |
|---|---|
| Needs rapid relief for panic or acute severe anxiety | Short‑term benzodiazepine plus psychotherapy |
| Daytime worker who needs minimal sedation | Buspirone or SSRI depending on severity |
| Comorbid depression | SSRI or SNRI |
Frequently Asked Questions
Will buspirone make me drowsy?
Less likely than benzodiazepines, but some patients report dizziness or drowsiness, so avoid driving until you know your response.
How long until it works?
Expect two to six weeks for benefit; buspirone is not suitable for immediate relief of acute panic.
Can I stop suddenly?
Abrupt discontinuation is not commonly associated with benzodiazepine‑style withdrawal, but tapering can help monitor symptom recurrence.
Is buspirone a controlled drug?
Buspirone is prescription‑only but is not classified as a controlled dependence‑prone medicine like benzodiazepines.
- PRN
- As Needed (not recommended for buspirone use).
- GAD
- Generalised Anxiety Disorder.
Guidelines For Proper Use And Pharmacist Counselling
Pharmacists should cover the key points patients want to know at first dispense.
Explain the indication clearly: treating Generalised Anxiety Disorder.
Set expectations about onset: it may take weeks to see benefit, typically two to six weeks.
Provide dosing instruction: start 7.5 mg twice daily and take 5–10 mg two to three times daily as prescribed.
Give missed dose advice: take when remembered unless near the next scheduled dose and do not double doses.
Discuss storage: keep at 20–25°C in original packaging and protect from moisture.
Review common side effects such as dizziness, nausea and headache and advise when to seek medical attention.
Warn explicitly about MAOI co‑use and caution with alcohol or other CNS depressants.
Advise follow‑up with the prescriber in two to four weeks to assess effectiveness and tolerability.
- Printable Counselling Checklist: Indication, dosing, onset, side effects, interactions, storage.
- Pharmacy Dosing Table: Starter dose 7.5 mg BID; maintenance 5–10 mg two–three times daily.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Gold Coast | Queensland | 5-7 days |
| Newcastle | New South Wales | 5-9 days |
| Wollongong | New South Wales | 5-9 days |
| Geelong | Victoria | 5-9 days |
| Townsville | Queensland | 5-9 days |
| Cairns | Queensland | 5-9 days |
| Darwin | Northern Territory | 5-9 days |