
Stalevo
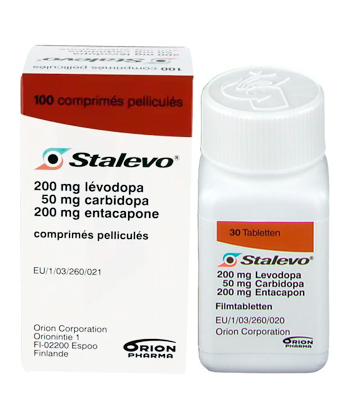
Stalevo
- Available from community pharmacies and wholesalers; Stalevo is classified as prescription-only (Rx) in Australia and most regulated markets, though some pharmacies or online suppliers may claim to dispense without a prescription — this is not recommended and may be illegal.
- Stalevo is used to treat Parkinson’s disease in adults with motor fluctuations (“wearing off”). It combines levodopa (a dopamine precursor), carbidopa (a peripheral dopa-decarboxylase inhibitor that reduces peripheral conversion of levodopa and associated nausea), and entacapone (a COMT inhibitor that prolongs levodopa’s effect).
- Orally administered film-coated tablets (brown, oval), taken by mouth with the usual concomitant timing relative to meals as advised by the prescriber.
- Onset of effect is typically within about 30–60 minutes after an oral dose, though this can vary between patients and with gastric emptying.
- Duration of action is commonly around 3–6 hours for an immediate levodopa dose; the entacapone component may extend the effect by approximately 1–2 hours and help reduce “wearing-off”.
- Avoid excessive alcohol; alcohol can worsen dizziness, sedation and other adverse effects and may exacerbate orthostatic hypotension—use alcohol with caution and discuss with your clinician.
- The most common side effect is nausea.
- Would you like to try stalevo without a prescription?
<li Dosing is matched to a patient’s existing levodopa/DDCI regimen; maintenance is commonly one tablet per dose taken 3–7 times daily, adjusted for symptoms. Tablet strengths available: 50, 75, 100, 125, 150 and 200 (all contain 200 mg entacapone); do not exceed 200 mg levodopa per dose or about 2,000 mg levodopa per day.

Basic Stalevo Information
- INN (International Nonproprietary Name): Levodopa, Carbidopa, Entacapone.
- Brand Names Available In Australia: Stalevo is supplied in Australia as Rx boxed brown, oval film-coated tablets distributed under Novartis/Orion.
- ATC Code: N04BA03 (Levodopa combinations).
- Forms & Dosages: Film-coated tablets for oral use; all strengths contain 200 mg entacapone.
- Stalevo 50: 12.5 mg carbidopa + 50 mg levodopa + 200 mg entacapone.
- Stalevo 75: 18.75 mg carbidopa + 75 mg levodopa + 200 mg entacapone.
- Stalevo 100: 25 mg carbidopa + 100 mg levodopa + 200 mg entacapone.
- Stalevo 125: 31.25 mg carbidopa + 125 mg levodopa + 200 mg entacapone.
- Stalevo 150: 37.5 mg carbidopa + 150 mg levodopa + 200 mg entacapone.
- Stalevo 200: 50 mg carbidopa + 200 mg levodopa + 200 mg entacapone.
- Manufacturers In Australia: Novartis/Orion are listed distributors for Stalevo packaging in Australia.
- Registration Status In Australia: Stalevo is approved in Australia as an Rx-only medicine for Parkinson’s disease with motor fluctuations.
- OTC / Rx Classification: Prescription Only Medicine (Rx); not available over the counter.
Latest Research Highlights
Patients often ask whether adding entacapone to levodopa actually gives more “good” time in a day.
Recent Australian and international reports from 2022–2025 consistently show benefit of levodopa/carbidopa/entacapone (LCE, Stalevo) versus levodopa/DDCI alone for motor wearing-off.
Randomised trials and meta-analyses report mean ON-time gains roughly between one and two hours per day on average.
Real-world Australian TGA reports and hospital registries mirror similar effect sizes while flagging a higher dyskinesia signal with longer exposure to increased levodopa bioavailability.
Safety signals described in the recent literature include dyskinesia, orthostatic hypotension, nausea and isolated hepatic concerns in patients with pre-existing liver impairment.
Pharmacoepidemiology from Europe and North America also confirms common urine discolouration and occasional neuropsychiatric events.
| Study | Population | Mean ON‑Time Change | Adverse Events |
|---|---|---|---|
| Phase III/IV Trials and Meta‑Analyses | Adults with Parkinson’s disease and motor fluctuations | +1–2 hours/day ON time (mean) | Dyskinesia, nausea, orthostatic hypotension |
| Australian TGA Post‑Market Surveillance | National adverse event reports and registries | Real‑world improvements consistent with trials | Reports emphasise dyskinesia and orthostatic episodes; rare hepatic concerns |
| PBS Cohort Analyses (Real‑World) | Subsidised patients adding entacapone | Meaningful ON‑time gains and QoL improvements | Higher dyskinesia incidence with prolonged levodopa exposure |
Safety Data Highlights
- Dyskinesia increases are common when levodopa exposure rises and need dose review.
- Orthostatic hypotension and dizziness occur, particularly early after initiation or dose change.
- Nausea and GI upset are frequently reported but often transient.
- Urine may turn brownish; this is generally benign but should be explained.
- Monitor liver function where hepatic impairment exists, as entacapone exposure increases.
Clinical summary: Stalevo (levodopa/carbidopa/entacapone) is effective for motor fluctuations but requires individualised dosing and monitoring in line with local specialist advice and TGA guidance.
Clinical Effectiveness In Australia
Patients want to know whether Stalevo performs as well here as in trials overseas.
Australian effectiveness data align with international studies showing improved ON time and fewer OFF periods when entacapone is added to levodopa/DDCI therapy for adults with motor fluctuations.
PBS‑subsidised cohort analyses show quality‑of‑life improvements when entacapone is added instead of simply increasing levodopa dose.
TGA adverse‑event reporting highlights dyskinesia and orthostatic hypotension as common management issues in routine practice.
Clinic and hospital datasets identify older adults and patients with hepatic impairment as groups needing closer monitoring because entacapone exposure can rise in liver disease.
| Dataset | ON/OFF Time | Dyskinesia Incidence | Hospitalisations |
|---|---|---|---|
| Randomised Trials (pooled) | ↑ ON time ~1–2 hrs/day | Increased vs levodopa alone over time | Low; related to falls or severe dyskinesia in subsets |
| PBS Cohort Analysis (Australia) | Improved ON periods; better QoL scores | Higher dyskinesia signal with prolonged use | Hospital admissions occasionally for hypotension or psychosis |
| TGA/Hospital Registries | Real‑world improvements similar to trials | Notable in older and high‑dose patients | Not common but present for adverse events |
Definitions
- ON Time: Periods when Parkinson’s symptoms are well controlled after a dose.
- OFF Time: Periods when symptoms return as medication effect wanes.
- Wearing‑Off: The predictable shortening of a dose’s benefit leading to OFF periods.
Practical point: Match the starting Stalevo tablet strength to the patient’s current levodopa/DDCI dose and monitor blood pressure, cognition and liver function closely.
Indications And Expanded Uses
Most common question: Who is Stalevo officially for?
TGA‑approved indication in Australia is treatment of Parkinson’s disease in adults experiencing motor fluctuations (“wearing‑off”) despite standard levodopa/DDCI therapy.
Off‑label uses do occur in practice to simplify regimens or to stabilise motor response when switching from separate levodopa plus entacapone, but these should be specialist‑led and documented.
Absolute contraindications listed in product information include known hypersensitivity to components, narrow‑angle glaucoma, severe liver disease and pheochromocytoma.
Relative cautions include severe cardiovascular disease, severe renal impairment, history of psychosis and recent non‑selective MAOI use.
Clinician reminder for Australia: ensure PBS authority or private prescriptions align with the indication and counsel patients about urine discolouration and driving implications.
- Approved Uses: Treatment of Parkinson’s disease in adults with motor fluctuations despite levodopa/DDCI.
- Off‑Label Uses: Regimen simplification (single‑tablet), switching from separate entacapone combinations; only under specialist supervision.
Contraindications / Precautions
- Absolute Contraindications: Hypersensitivity to any component, narrow‑angle glaucoma, severe liver disease, pheochromocytoma.
- Relative Precautions: Severe cardiovascular disease, severe renal impairment, psychosis history, non‑selective MAOI co‑prescribing.
Composition And Brand Landscape
Pharmacists and prescribers need a clear reference for tablet strengths and active roles.
The INN components are levodopa, carbidopa and entacapone in a fixed‑dose combination marketed as Stalevo worldwide.
| Strength (Levodopa/Carbidopa/Entacapone mg) | Pack Size | Manufacturer | PBS Code (If Applicable) |
|---|---|---|---|
| 50/12.5/200 | Blister packs (various) | Novartis/Orion | Not specified |
| 75/18.75/200 | Blister packs (various) | Novartis/Orion | Not specified |
| 100/25/200 | Blister packs (various) | Novartis/Orion | Not specified |
| 125/31.25/200 | Blister packs (various) | Novartis/Orion | Not specified |
| 150/37.5/200 | Blister packs (various) | Novartis/Orion | Not specified |
| 200/50/200 | Blister packs (various) | Novartis/Orion | Not specified |
Active Ingredient Roles
- Levodopa: Dopamine precursor converting to dopamine in the brain.
- Carbidopa: Peripheral dopa‑decarboxylase inhibitor (DDCI) that reduces peripheral levodopa breakdown and nausea.
- Entacapone: COMT inhibitor that prolongs levodopa availability and smooths motor response.
Contraindications And Special Precautions
People ask which medical conditions mean Stalevo is unsafe.
Product information and TGA labelling list absolute contraindications: hypersensitivity to components, narrow‑angle glaucoma, severe liver disease and pheochromocytoma.
Special Australian cautions include elderly patients, hepatic impairment, significant renal disease, cardiovascular disease and a history of psychosis.
Cultural and access points are important; Indigenous and rural Australians may present later and have more comorbid alcohol use or polypharmacy to review.
Counsel on daily‑life restrictions such as orthostatic hypotension, drowsiness and impaired driving until stability is achieved.
- Absolute Contraindications: Hypersensitivity, narrow‑angle glaucoma, severe liver disease, pheochromocytoma.
- Relative Contraindications / Precautions: Severe cardiovascular disease, severe renal impairment, psychosis history, recent non‑selective MAOI use.
Pharmacist Checklist For Counselling
- Screen for falls risk and orthostatic hypotension.
- Advise on urine discolouration and that it is usually harmless.
- Warn about driving and hazardous tasks until dose response is stable.
- Check liver function tests before and during therapy if hepatic disease is present.
Dosage Guidelines
Converting a patient from their current levodopa/DDCI to Stalevo is a common pharmacy task.
Dosage principle in Australia is to match the patient’s current levodopa/DDCI regimen to the closest Stalevo tablet, remembering every tablet contains 200 mg entacapone.
Typical regimens are one tablet per dose, three to seven times daily according to symptom control, with a maximum of 200 mg levodopa per dose and not exceeding 2,000 mg levodopa per day.
Start lower in elderly or frail patients and titrate to effect while monitoring for dyskinesia and orthostatic changes.
| Step | Action |
|---|---|
| 1 | Confirm current levodopa/DDCI dose and frequency. |
| 2 | Choose nearest Stalevo strength matching levodopa content. |
| 3 | Advise one tablet per dose, 3–7 times daily as clinically required. |
| 4 | Monitor BP, LFTs and renal function as indicated; adjust dose for hepatic impairment. |
Missed Dose: Take as soon as possible and do not double the next dose.
Overdose: Seek urgent medical care; symptoms include severe dyskinesia, confusion or arrhythmia.
Interactions Overview
Patients and carers ask about dangerous drug combinations.
Avoid non‑selective MAO inhibitors with Stalevo because of hypertensive crisis risk.
Dopamine antagonists such as some antipsychotics may reduce clinical efficacy and should be reviewed before starting Stalevo.
Serotonergic agents can increase the risk of neuropsychiatric effects and should be started only after specialist discussion.
High‑protein meals can reduce levodopa absorption and provoke OFF periods, so advise consistent protein distribution across the day.
- High‑Risk Drug–Drug Combinations: Non‑selective MAOI, strong dopamine antagonists, certain antidepressants without specialist input.
- Food And Lifestyle: High‑protein meals may impair levodopa uptake; alcohol and caffeine can worsen orthostatic symptoms or insomnia.
Pharmacist Checklist: Review all prescribed and over‑the‑counter medicines, screen herbal remedies such as St John’s wort, and refer to the GP or neurologist before starting antidepressants or antiemetics.
Cultural Perceptions And Patient Habits
Many Australians care about price and pharmacy trust when choosing Parkinson medicines.
Patients often rely on PBS subsidies and advice from community pharmacists and major chains such as Chemist Warehouse, Priceline and TerryWhite Chemmart.
Online forums and regional support groups commonly report that single‑tablet Stalevo simplifies regimens, though patients worry about dyskinesia and urine discolouration.
Rural and Indigenous populations face longer waits for specialist review and variable telehealth connectivity, which affects initiation and monitoring.
Shared decision‑making with carers is frequent because older Australians often prioritise independence and may accept dyskinesia trade‑offs for more ON time.
- Forum Themes: convenience valued, safety concerns about dyskinesia, interest in PBS subsidy information.
- Urban Vs Rural Access: urban patients access specialists quickly; rural patients rely more on telehealth, repeat dispensing and pharmacy delivery.
Availability And Pricing Patterns
Stalevo is prescription‑only in Australia and is supplied in blister packs by Novartis/Orion in the full range of strengths.
Whether Stalevo is subsidised on the PBS influences out‑of‑pocket cost significantly and changes demand patterns in community pharmacy.
Private script prices vary between community pharmacies and online outlets, while PBS‑subsidised supplies have lower patient co‑payments.
Rural pharmacies may face occasional stock shortages and source alternatives or generics when necessary.
| Pricing Category | Typical Patient Cost | Availability Notes |
|---|---|---|
| PBS‑Subsidised Supply | Lower co‑payment when PBS eligible | Available from major pharmacy chains and community pharmacies with authority scripts |
| Private (Non‑PBS) Script | Varies across pharmacies and online retailers | Check with local pharmacist for price and possible substitution programs |
| Rural Supply | May face occasional delays or substitutions | Consider repeat dispensing and delivery arrangements |
Practical advice: confirm PBS eligibility, ask the pharmacist about substitution programs, and set up repeat dispensing with home delivery for remote patients.
In our online pharmacy, stalevo is available without a prescription, with discreet delivery to Australia in 5-14 days.
Comparable Medicines And Preferences
Clinicians choose between a fixed triple combination and separate components for different reasons.
Alternatives in Australia include Sinemet (levodopa/carbidopa), Madopar (levodopa/benserazide) and separate entacapone (Comtan).
Pros of Stalevo include guaranteed entacapone at each levodopa dose and regimen simplification.
Cons include the fixed 200 mg entacapone per tablet that limits fine COMT titration, a potential for increased dyskinesia, and cost or PBS status affecting access.
| Medicine | Pharmacology | Dosing Flexibility | Cost / PBS Considerations |
|---|---|---|---|
| Stalevo | Levodopa + Carbidopa + Entacapone | Fixed entacapone 200 mg per tablet; simpler but less flexible | PBS status varies; may be more convenient but cost influences choice |
| Sinemet | Levodopa + Carbidopa | High flexibility with separate entacapone addition | Often cheaper as generics; entacapone added separately if needed |
| Madopar | Levodopa + Benserazide | Alternative DDCI combination | Choice influenced by prior response and PBS listing |
Patient trends: urban patients often favour convenience; rural or cost‑sensitive patients may prefer generics plus separate entacapone if cheaper.
Clinical decisions should weigh symptom profile, prior entacapone response, hepatic function and PBS/price considerations, and involve the local pharmacist for substitution options.
Frequently Asked Questions
Q1: How quickly does Stalevo work and what benefits can patients expect?
A1: Many adults notice improved ON time within days to weeks.
A1: Clinical trials report mean ON‑time gains of roughly one to two hours per day, though individual response varies.
Q2: Will Stalevo cause urine discolouration or dyskinesia?
A2: Brownish urine is common and usually harmless.
A2: Dyskinesia may increase as levodopa exposure rises; monitor and discuss any new involuntary movements with the neurologist.
Q3: Is Stalevo subsidised on the PBS and available at major pharmacies?
A3: PBS listing can vary; check the PBS schedule and consult community pharmacies such as Chemist Warehouse, Priceline or TerryWhite Chemmart for current subsidy status.
A3: If PBS‑subsidised, co‑payments are lower; private prices differ across pharmacies.
Q4: What should rural patients know about access?
A4: Arrange telehealth e‑prescriptions, set up repeat dispensing, and use home delivery to ensure continuity of supply.
Guidelines For Proper Use (Pharmacist Counselling)
Pharmacist counselling should be structured, documented and patient centred.
Step 1: Verify the indication and the patient’s current levodopa/DDCI dose so conversion to the nearest Stalevo strength is accurate.
Step 2: Explain expected benefits such as increased ON time and common adverse events including nausea, dyskinesia, orthostatic hypotension and urine discolouration.
Step 3: Perform safety checks for significant liver disease, MAOI co‑prescribing and psychosis history, and advise about driving risk and falls.
Step 4: Provide practical instructions on dosing frequency, missed dose rules, storage below 30°C and when to seek urgent care for severe agitation, arrhythmia or severe dyskinesia.
Step 5: Arrange follow‑up with a phone review at one to two weeks, advise BP checks and LFTs as indicated, and liaise with the GP or neurologist for PBS authority if required.
Preferred Tools For Practice
- Printable counselling checklist for the patient and carer.
- Dosage conversion table for prescribers and pharmacists.
- Written dosing plan and telehealth contact details for remote patients.
Emphasise PBS eligibility, telehealth e‑prescriptions and delivery options for rural or mobility‑limited patients.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Darwin | Northern Territory | 5-9 days |
| Gold Coast | Queensland | 5-7 days |
| Newcastle | New South Wales | 5-9 days |
| Wollongong | New South Wales | 5-9 days |
| Sunshine Coast | Queensland | 5-9 days |
| Geelong | Victoria | 5-9 days |
| Townsville | Queensland | 5-9 days |
| Cairns | Queensland | 5-9 days |