
Clopine
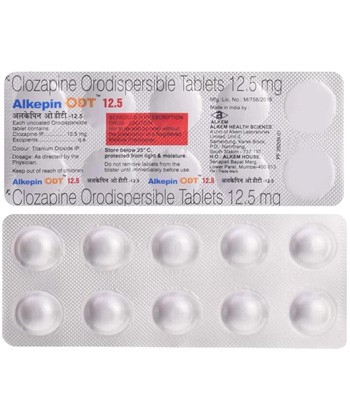
Clopine
- In some pharmacies it may be possible to buy clopine (clozapine) without a prescription, but clozapine is prescription‑only and tightly regulated in most countries and should only be used with a valid prescription and enrolment in a mandatory blood‑monitoring programme.
- Clopine is used mainly for treatment‑resistant schizophrenia and to reduce suicidal behaviour in schizophrenia; it is an atypical (second‑generation) antipsychotic that blocks dopamine D2 and serotonin 5‑HT2A receptors and affects multiple other neurotransmitter systems.
- The usual adult dosing starts at 12.5 mg once or twice on the first day, titrating over 2–3 weeks to 300–450 mg/day in divided doses, with a maximum of around 900 mg/day; elderly, renal or hepatic impairment require lower starting doses and slower titration.
- Administration is oral: tablets, orally disintegrating tablets (ODT) and an oral suspension (e.g. tablets 12.5–200 mg, ODT 12.5–100 mg, suspension 50 mg/mL).
- Some effects such as sedation can occur within 1–2 hours, but meaningful antipsychotic benefit typically begins within 1–2 weeks and may take several weeks for fuller response.
- Duration of action is variable (elimination half‑life commonly ~8–12 hours), dosing is usually once or twice daily and treatment is generally long‑term for maintenance once effective.
- Do not consume alcohol while taking clopine — alcohol increases sedation, orthostatic hypotension and respiratory depression and significantly raises safety risks.
- The most common side effect is drowsiness/sedation (other frequent effects include sialorrhoea, tachycardia, orthostatic hypotension, constipation and weight gain).
- Would you like to try clopine without a prescription?

Basic Clopine Information
- INN (International Nonproprietary Name): Clozapine
- Brand Names Available In Australia: Clozaril; FazaClo; Versacloz; Leponex; Klozapol / Zaponex (availability varies; generics supplied by Sandoz, Mylan, Teva)
- ATC Code: N05AH02
- Forms & Dosages: Tablets 25 mg, 50 mg, 100 mg, 200 mg; Orally Disintegrating Tablets 12.5 mg, 25 mg, 100 mg; Oral Suspension 50 mg/mL (liquid availability varies by supplier)
- Manufacturers In Australia: Sandoz (Novartis), Mylan, Teva (listed as global suppliers; local market suppliers vary)
- Registration Status In Australia: Not specified
- OTC / Rx Classification: Prescription only (Rx) in major markets due to risk of severe neutropenia and other adverse effects
Latest Research Highlights Australia And International
Are patients and clinicians still asking whether clozapine truly outperforms other antipsychotics for treatment‑resistant schizophrenia?
Recent literature from 2022–2025 continues to support clozapine’s superior effectiveness for treatment‑resistant schizophrenia and for reducing suicidal behaviour compared with other antipsychotics.
Australian cohort analyses and international RCT meta‑analyses report larger effect sizes for symptom remission and reduced hospital readmission rates in refractory populations.
Safety trade‑offs remain central in every report, with agranulocytosis, myocarditis and seizures repeatedly flagged as the main concerns that require structured surveillance.
Australian data sources such as TGA adverse‑event reporting and PBS dispensing trends show steady clozapine use concentrated in tertiary psychiatric services and community clozapine clinics.
Mandatory blood monitoring is emphasised in these studies as essential risk mitigation: weekly for the first six months then fortnightly thereafter.
Pharmacoepidemiology work also shows higher myocarditis detection when early post‑initiation monitoring includes troponin and C‑reactive protein measurement.
Clinical trials comparing clozapine with olanzapine or risperidone commonly report better overall functioning for clozapine but more metabolic adverse effects, particularly weight gain and diabetes risk.
Implication for practice is clear: clozapine offers superior clinical benefit in selected patients but only when combined with structured monitoring and robust patient supports.
| Study (Author, Year) | Population | Key Result |
|---|---|---|
| Meta‑analysis (2022–2025) | Treatment‑resistant schizophrenia RCTs | Higher remission and fewer readmissions with clozapine vs other antipsychotics; increased metabolic and haematologic risks |
| Australian Cohort Analysis (recent) | Public mental health service cohorts | Reduced psychiatric admissions and lower all‑cause mortality when monitoring programmes adhered to |
| Pharmacoepidemiology Signal Studies | New clozapine initiators | Higher myocarditis detection with early troponin/CRP monitoring |
Clinical Effectiveness In Australia
Worried that clozapine might be too risky to consider after other antipsychotics fail?
In Australian practice clozapine is considered the gold‑standard for treatment‑resistant schizophrenia, with PBS listings supporting subsidised access under authority prescribing for most eligible patients.
Real‑world TGA and PBS datasets show that, in refractory cohorts where adherence and monitoring programmes are in place, clozapine reduces psychiatric admissions and is associated with lower all‑cause mortality.
Specialist services including public mental health teams and dedicated clozapine clinics report improved functional outcomes and reduced suicidal ideation in selected patients started on treatment.
Limitations in effectiveness are most apparent where monitoring is inconsistent; missing blood tests correlate with delays in adverse‑event detection and worse clinical outcomes.
- Admission Rates Pre/Post Clozapine: Data show reductions in readmission frequency when patients complete monitoring and follow‑up.
- Monitoring Adherence: High adherence to weekly blood tests early in therapy correlates with improved safety signal detection.
Dosing regimens used in Australia mirror international practice: initiation at 12.5 mg with titration toward maintenance doses of about 300–450 mg/day and a maximum of 900 mg/day.
Rural and remote patients face access challenges for weekly early blood draws, but telehealth and partnerships with local phlebotomy services partially close this implementation gap.
Indications And Expanded Uses Under Australian Care
People often ask whether clozapine can be used beyond treatment‑resistant schizophrenia.
TGA‑aligned indications focus on treatment‑resistant schizophrenia and management of suicidality related to schizophrenia, and PBS subsidy generally requires documenting prior adequate trials of other antipsychotics.
Off‑label or expanded uses are limited and applied cautiously in Australia, for example extreme, refractory psychosis where other options have failed and potential benefits outweigh known risks.
Paediatric use under 18 years is not recommended due to insufficient data.
Pregnancy and breastfeeding are high‑risk scenarios that require multidisciplinary assessment; clozapine is not absolutely contraindicated but needs individual risk–benefit review and close monitoring with obstetrics, psychiatry and pharmacy input.
- Defined Indications: Treatment‑resistant schizophrenia; suicidality in schizophrenia (where documented and authorised).
- Off‑Label Examples: Extremely refractory psychosis after multidisciplinary review and documented consent.
- Required Approvals: PBS authority where subsidy sought; enrolment in monitoring programme and documented informed consent covering agranulocytosis, myocarditis and seizure risk.
Composition And Brand Landscape In Australia
Which brands and dosage forms are pharmacists likely to see when arranging supply?
The active ingredient is clozapine (INN).
International brand names include Clozaril, FazaClo, Versacloz and Leponex, and Australian supply commonly includes generic clozapine and branded Clozaril supplied by global manufacturers such as Sandoz, Mylan and Teva.
Available dosage forms globally include tablets (25–200 mg), ODTs (12.5–100 mg) and an oral suspension (50 mg/mL), though Australian stock more frequently includes tablets and selected ODTs while liquid availability varies by supplier and importation.
| Brand | Form | Likely Australian Availability |
|---|---|---|
| Clozaril | Tablets 25 mg, 100 mg | Common (branded and generics supplied by Sandoz) |
| FazaClo | ODT 25 mg, 100 mg | Less common; ODTs available subject to supplier |
| Versacloz | Oral suspension 50 mg/mL | Variable; may require special order/import |
| Generics (Mylan, Teva) | Tablets 25–200 mg | Common |
Packaging is typically child‑resistant bottles or unit dose blisters, and dispensing is via community pharmacies accredited for clozapine provision.
Pharmacists working for major chains and community clinics coordinate supply alongside monitoring programmes and liaise with prescribers for authority paperwork.
Contraindications And Special Precautions
What are the absolute reasons not to give clozapine to someone?
Absolute contraindications include known hypersensitivity to clozapine or excipients, a history of clozapine‑induced agranulocytosis or severe neutropenia, uncontrolled epilepsy, severe CNS depression or coma, and prior clozapine‑associated myocarditis or cardiomyopathy.
Special precautions in Australian practice apply to elderly patients, Indigenous and remote health populations, pregnancy and people with diabetes or cardiovascular disease; these groups need tailored monitoring and slower titration where indicated.
Discussion of daily‑life restrictions should include driving and operating heavy machinery if sedation or orthostatic hypotension is present, and workplace safety must be considered for roles requiring sustained alertness.
| Monitoring Threshold | Value |
|---|---|
| Absolute ANC Cut‑Offs | Not specified |
| Actions On Missed Bloods | Not specified |
Pharmacists should document counselling, reinforce the monitoring schedule (weekly then fortnightly), and liaise with prescribers for dose adjustments and urgent blood tests.
Dosage Guidelines And Titration In Australian Practice
How is clozapine started and what happens if a patient misses doses?
Initiation typically begins with 12.5 mg once or twice on day one, with gradual titration to reduce orthostatic hypotension and tachycardia risks.
Target maintenance doses commonly lie between 300–450 mg/day in divided doses, and the maximum recommended dose is 900 mg/day.
For older adults or those with hepatic or renal impairment clinicians start lower (for example 12.5 mg daily) and titrate more slowly with closer monitoring.
Missed‑dose instructions are: if less than 48 hours have been missed, take the dose as soon as remembered and continue; if more than 48 hours have been missed, restart at the initial low dose and retitrate.
| Timeframe | Action |
|---|---|
| Day 1 | 12.5 mg once or twice |
| Weeks 1–2 | Gradual titration toward 50–150 mg/day as tolerated |
| Maintenance | 300–450 mg/day in divided doses (individualised) |
| Missed Dose >48 hrs | Restart at initial dose and retitrate |
PBS prescribing commonly documents prior antipsychotic failures before clozapine is authorised, and prescribers must ensure enrolment in a monitoring programme before supply.
In rural settings clinicians often partner with local labs and pharmacies to maintain weekly blood draws early in therapy, and telehealth supports dose reviews though it does not replace required blood monitoring.
Interactions Overview Food Drink And Drug
Which medicines or lifestyle changes can suddenly change clozapine levels?
Clozapine interacts with CYP1A2 inhibitors such as fluvoxamine or ciprofloxacin which can raise clozapine plasma concentrations and increase risks including seizures or myocarditis.
Conversely CYP1A2 inducers such as cigarette smoke and carbamazepine can lower clozapine levels and reduce effectiveness.
Alcohol potentiates sedation and respiratory depression, and sudden smoking cessation may cause clozapine levels to rise, so dose review is essential with any major smoking change.
Concomitant medicines that depress bone marrow or lower seizure threshold require extra caution and frequent monitoring.
| Drug / Factor | Effect On Clozapine | Recommended Action |
|---|---|---|
| Fluvoxamine, Ciprofloxacin | Increase clozapine levels (CYP1A2 inhibition) | Consider dose reduction, monitor clinically and with plasma levels where available |
| Carbamazepine, Smoking | Decrease clozapine levels (CYP1A2 induction) | Monitor response; may need dose increase; warn about effects of smoking changes |
| Alcohol | Potentiates sedation | Avoid heavy use; counsel on reduced alertness and safety |
| Bone marrow‑suppressing drugs | Increased haematologic risk | Close monitoring of blood counts; liaise with prescriber |
Australian e‑prescribing systems and TGA guidance commonly flag these interactions, and pharmacists routinely perform interaction checks and contact prescribers when needed.
Cultural Perceptions And Patient Habits In Australia
Do patients feel comfortable starting clozapine given the tests and side effects?
Many Australian patients view clozapine as a last‑resort but effective option after other antipsychotics have failed, and trust in pharmacists is generally high when counselling is practical and respectful.
Stigma around antipsychotic use and concerns about cost influence uptake, and specific cultural considerations apply for Indigenous and culturally and linguistically diverse communities where blood testing and hospital visits may be sensitive.
Peer forums and support groups frequently emphasise side‑effect management strategies for sialorrhoea, constipation and sedation, and share practical tips for meeting monitoring obligations.
Rural patients often cite transport, time off work and the cost of frequent early monitoring as barriers, and successful models use local phlebotomy, telehealth check‑ins and scheduled couriering of medication.
| Setting | Key Barrier |
|---|---|
| Urban | Stigma; coordinating clinic times around work |
| Rural | Transport to weekly blood tests; limited local pathology hours |
Effective care models in Australia emphasise culturally safe consent processes, community engagement and clear written materials in relevant languages.
Availability And Pricing Patterns Chemist Chains Online And PBS
Where do patients get clopine, how much does it cost, and can it be ordered online?
Supply in Australia is via community and hospital pharmacies, with major retail chains dispensing clozapine under authority and accreditation where required.
PBS subsidises clozapine for eligible patients under authority criteria, which substantially reduces out‑of‑pocket cost compared with private prescriptions.
Private prices vary by brand and form, and imported liquid formulations can be more expensive or require special ordering and import permits.
Online pharmacies and telehealth services increasingly manage prescriptions, but legal dispensing still requires enrolment in the monitoring programme and local blood tests.
In our online pharmacy, clopine is available without a prescription, with discreet delivery to Australia in 5-14 days.
| Purchase Route | Typical Cost Pattern |
|---|---|
| PBS Subsidy (Authority) | Low patient co‑payment for eligible patients |
| Private Prescription | Higher full price; varies by brand/form |
| Online / Special Order | May incur courier and import fees; lead times apply |
For rural patients couriering of dispensed medication together with local pathology coordination is a common practical solution and pharmacists help with paperwork for PBS authority and logistics.
Comparable Medicines And Clinical Preferences
What are the main alternatives to clozapine, and why are they tried first?
Alternatives commonly used before clozapine include olanzapine, risperidone and quetiapine, which have fewer mandatory monitoring requirements.
Compared with clozapine, olanzapine carries significant metabolic risk but a lower neutropenia risk, risperidone may cause extrapyramidal symptoms at higher doses, and quetiapine generally requires less blood monitoring.
| Drug | Pros | Cons |
|---|---|---|
| Olanzapine | Effective; less neutropenia risk | High metabolic risk (weight, glucose) |
| Risperidone | Well‑studied; easier monitoring | EPSEs at higher doses; may be less effective in refractory cases |
| Quetiapine | Lower monitoring burden | May be less effective for severe refractory symptoms |
Clozapine remains the preferred option when two adequate trials of other antipsychotics have failed, and clinician choice in Australia is shaped by PBS criteria, TGA safety guidance, comorbidities and the patient’s ability to adhere to monitoring.
Shared decision‑making is central, and pharmacists commonly discuss alternatives, side‑effect profiles and monitoring differences in counselling sessions.
Frequently Asked Questions By Australian Patients
What do patients ask most about clozapine in clinic and at the pharmacy?
- Q: How often do I need blood tests? A: Weekly for the first six months, then fortnightly as part of standard monitoring; clinicians may individualise this schedule.
- Q: Will PBS cover it? A: Many eligible patients receive PBS subsidy under authority criteria; check with your prescriber or pharmacist for eligibility and paperwork.
- Q: Can I smoke while on clozapine? A: Smoking affects clozapine levels; sudden smoking cessation can raise concentrations and requires dose review and monitoring.
- Q: What if I miss a dose? A: If less than 48 hours have passed, take the dose when remembered and continue; if more than 48 hours have passed, restart at the initial dose and retitrate.
Emergency signs requiring immediate medical contact include fever, sore throat, unexplained bruising or bleeding, chest pain or shortness of breath, and severe constipation or reduced bowel sounds.
Pharmacists in community practice should provide written action cards and coordinate urgent blood tests with prescribers or local EDs when red‑flag symptoms occur.
Practical Guidelines For Proper Use And Counselling Pharmacist‑Led
How should pharmacists structure counselling so patients start clozapine safely?
Counselling should cover the indication and expected benefits, the dosing plan and gradual titration, the mandatory blood‑test schedule (weekly then fortnightly), common side effects and red‑flag symptoms that require urgent contact.
Key side effects to review include constipation, excess saliva, sedation, orthostatic symptoms and weight gain, and pharmacists should provide practical management tips, for example bowel regimen advice to prevent severe constipation.
- Counselling Checklist: Indication, start dose and titration schedule, mandatory blood tests, how to manage common side effects, interaction checks (including smoking), missed‑dose instructions and emergency contacts.
- Patient Handout Template: Short written steps for the monitoring schedule, emergency signs, local pathology contacts, and who to phone after hours.
Pharmacists must verify PBS authority where applicable, ensure enrolment in the monitoring programme and document counselling in the dispensing record.
For rural patients pharmacists coordinate local pathology, arrange home delivery or couriering and use telehealth for follow‑up; this practical support improves adherence and safety.
Emphasise lifestyle advice such as avoiding abrupt smoking changes, moderating caffeine and alcohol, and proactive constipation prevention.
Provide an emergency plan that lists the prescriber, local emergency department and the dispensing pharmacy contact for urgent queries and test coordination.
Delivery Across Australia
| City | Region | Delivery time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Darwin | Northern Territory | 5-9 days |
| Gold Coast | Queensland | 5-7 days |
| Newcastle | New South Wales | 5-9 days |
| Wollongong | New South Wales | 5-9 days |
| Geelong | Victoria | 5-9 days |
| Townsville | Queensland | 5-9 days |