
Largactil
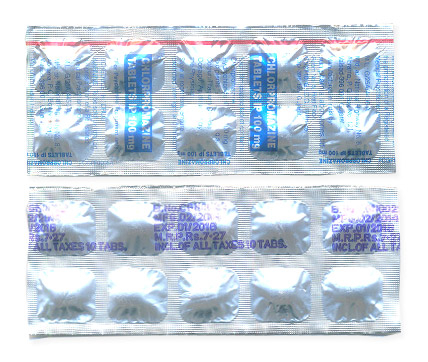
Largactil
- In our pharmacy, you can buy largactil without a prescription, with delivery in 5–14 days throughout Australia. Discreet and anonymous packaging.
- Largactil (chlorpromazine) is used for schizophrenia and other psychoses, mania, severe nausea/vomiting, pre‑operative anxiety and some cases of intractable hiccups; it is a first‑generation (phenothiazine) antipsychotic that primarily blocks dopamine D2 receptors and also antagonises serotonin, histamine and adrenergic receptors.
- The usual dose in adults for psychosis is to start 25–100 mg three times daily and adjust as needed with typical maintenance of 200–800 mg/day divided; for nausea 10–25 mg every 4–6 hours; paediatric dosing is weight‑based (around 0.5–0.55 mg/kg per dose) and elderly patients should start at lower doses.
- Administration forms include tablets (10 mg, 25 mg, 50 mg, 100 mg, 200 mg), oral solution (commonly 10 mg/mL) and injectable preparations for IM/IV use (commonly 25 mg/mL).
- Onset of effect: oral administration typically begins within about 30–60 minutes, IM within about 10–30 minutes and IV produces a more rapid onset.
- Duration of action: sedative effects commonly last 4–6 hours; single‑dose antipsychotic effects may persist 12–24 hours, while therapeutic antipsychotic benefits usually take days to weeks to become fully apparent.
- Alcohol warning: avoid alcohol while taking largactil — alcohol increases sedation, respiratory depression and risk of severe hypotension and should be avoided.
- The most common side effec is drowsiness (sedation); other frequent effects include dry mouth, blurred vision, constipation, orthostatic hypotension, weight gain and extrapyramidal symptoms; serious but less common risks include tardive dyskinesia, neuroleptic malignant syndrome and blood disorders.
- Would you like to try largactil without a prescription?

Basic Largactil Information
- INN (International Nonproprietary Name): Chlorpromazine
- Brand Names Available In Australia: not specified
- ATC Code: N05AA01
- Forms & Dosages: Tablets 10 mg, 25 mg, 50 mg, 100 mg, 200 mg; Oral solution commonly 10 mg/mL; Injection (IM/IV) 25 mg/mL
- Manufacturers In Australia: not specified
- Registration Status In Australia: not specified
- OTC / Rx Classification: Prescription-only (Rx) in all jurisdictions
Latest Research Highlights
Patients often ask whether older drugs like chlorpromazine still have a place in modern care.
Recent international meta-analyses (2022–mid-2024) reconfirm that first-generation antipsychotics, including chlorpromazine, remain effective for acute psychosis and rapid symptom control.
Those reviews also continue to show higher rates of extrapyramidal symptoms and metabolic concerns compared with many atypical agents.
Australian pharmacoepidemiology and TGA pharmacovigilance summaries since 2020 emphasise continued adverse-event reporting for tardive dyskinesia, orthostatic hypotension and QT prolongation, particularly among older people and in polypharmacy contexts.
Small Australian hospital audits note chlorpromazine’s value for acute agitation and for short courses treating refractory nausea in palliative settings.
The World Health Organization lists chlorpromazine on the Model List of Essential Medicines, underlining global importance where generics are needed.
Current evidence trends favour low-dose or short-course use for symptomatic control, with ECG and haematology monitoring when higher doses or maintenance therapy are considered.
Clinical gaps remain in Indigenous health settings and remote telehealth prescribing, where patient-centred research is limited.
| Outcome | Evidence Summary |
|---|---|
| Acute Psychosis | Effective for rapid symptom control; supported by older RCTs and recent meta-analyses. |
| Adverse Events | Higher extrapyramidal symptoms, orthostatic hypotension and QT risk versus many atypicals; vigilance required. |
| Short-Course Nausea/Hiccups | Useful in palliative and chemotherapy-related nausea as documented in small audits and clinical reports. |
Clinical Effectiveness In Australia
People want to know where chlorpromazine fits in Australian practice today.
Australian hospital formularies and TGA-aligned practice typically reserve chlorpromazine for acute psychosis, severe agitation and refractory nausea or preoperative anxiety where sedation or antiemetic action is required.
Outcomes from public hospital trusts show reliable short-term symptom reduction, with clinicians often switching to alternatives for maintenance because of side-effect burden and monitoring needs.
Emergency departments and palliative care teams commonly use chlorpromazine for rapid sedation and for refractory nausea or hiccups when other agents fail.
Pharmaco-supply factors, PBS listings and local hospital arrangements influence how often it is used in clinics and community settings.
In rural and remote Australia, telehealth-linked prescribing can improve access but increases the need for pharmacist collaboration for monitoring and supply.
| Use | Short-Term Efficacy | Adverse-Event Notes |
|---|---|---|
| Acute Psychosis/Agitation | Good—rapid calming effect documented in EDs | Risk of sedation, orthostatic hypotension, EPS |
| Refractory Nausea/Hiccups | Effective in short courses in palliative settings | Monitor sedation and anticholinergic effects |
Indications And Expanded Uses
Patients ask what chlorpromazine is approved for and when it is used off-label.
TGA-aligned indications reflect global practice: psychotic disorders, acute mania/agitation, severe nausea and preoperative anxiety are typical uses.
Standard adult dosing conventions include starting oral doses of 25–100 mg three times daily with maintenance often falling between 200–800 mg per day divided.
Short courses for intractable hiccups or chemotherapy-related nausea are common off-label uses supported by clinical reports and local audits.
Off-label prescribing can include management of severe agitation-related insomnia, but clinicians should document rationale and obtain informed consent.
Paediatric regimens are specialist-led and weight-based, typically around 0.5–0.55 mg/kg per dose, and require close supervision.
| Indication | Typical Australian Dose |
|---|---|
| Schizophrenia / Psychosis | Start 25–100 mg 3x daily; maintenance commonly 200–800 mg/day divided |
| Nausea / Vomiting | 10–25 mg every 4–6 hours orally for short courses |
| Preoperative Anxiety | 25–50 mg one hour before procedure |
- Absolute Contraindications: comatose states, severe bone-marrow depression, pheochromocytoma, known phenothiazine hypersensitivity, infants under six months.
- Prescribers should document off-label rationales and use PBS/hospital pathways where appropriate.
Composition And Brand Landscape
People often search for Largactil packaging or chlorpromazine formulations when arranging supplies.
The active ingredient is chlorpromazine hydrochloride, classed under ATC N05AA01 as a phenothiazine first-generation antipsychotic.
International brand names include Thorazine in the United States and Largactil in the United Kingdom and Europe, plus many generics sold under Chlorpromazine or local variants.
Common pharmaceutical forms are tablets (10–200 mg), an oral solution commonly 10 mg/mL, and injectable ampoules at 25 mg/mL for IM/IV use.
In Australia, chlorpromazine generally appears as generics; historical recognition for Largactil helps with search terms and patient literacy.
| Formulation | Typical Strengths / Packaging |
|---|---|
| Tablets | 10 mg, 25 mg, 50 mg, 100 mg, 200 mg |
| Oral Solution | Commonly 10 mg/mL |
| Injection | 25 mg/mL ampoules for IM/IV use |
Hospital supply typically prioritises ampoules for emergency and palliative use, while tablets and oral solution suit outpatient management and telehealth prescriptions.
Contraindications And Special Precautions
Patients and carers commonly worry about who should avoid Largactil entirely.
Absolute contraindications include comatose states, known phenothiazine hypersensitivity, severe bone-marrow depression, pheochromocytoma and infants under six months, per product data.
Relative contraindications requiring monitoring include significant cardiovascular disease, hepatic or renal impairment, seizure disorders, Parkinson’s disease and dementia, and frailty in older adults.
Older people with dementia have a notably higher mortality risk with antipsychotics and chlorpromazine should be avoided where possible.
Advise patients not to drive or operate heavy machinery until sedation and orthostatic effects are clear, and to avoid alcohol because of increased central nervous system depression.
- Monitoring Steps: baseline ECG for QT-risk or higher doses, blood pressure checks, full blood count and liver function tests for prolonged therapy.
- Prescribers should adjust dosing and ensure follow-up for Indigenous and remote-living patients with higher comorbidity burdens.
Dosage Guidelines
One of the most common questions is how much to take and how dosing differs by indication.
Typical adult initiation is 25–100 mg three times daily with titration to effect and maintenance usually between 200–800 mg/day divided into 2–4 doses.
For nausea, much lower doses such as 10–25 mg every 4–6 hours are often effective.
Paediatric dosing is specialist-led and generally weight-based at about 0.5–0.55 mg/kg per dose with careful titration.
Elderly patients usually start at roughly half the usual adult dose and titrate slowly while monitoring for sedation and hypotension.
| Indication | Starting Dose | Maintenance / Notes |
|---|---|---|
| Acute Psychosis | 25–100 mg 3x daily | 200–800 mg/day divided; monitor ECG and bloods at higher doses |
| Nausea | 10–25 mg every 4–6 hours | Short course; review regularly |
| IM/IV Use | 25 mg/mL ampoule as required | Monitor cardiovascular status during administration |
Counselling points include taking with food to reduce stomach upset and not stopping abruptly after long-term use to avoid withdrawal or symptom recurrence.
If a dose is missed, take it as soon as remembered unless it is near the next dose; do not double up.
Interactions Overview
Many callers ask which drugs are unsafe with chlorpromazine.
Chlorpromazine potentiates CNS depression with alcohol, benzodiazepines and opioids, increasing sedation and respiratory depression risk.
Concomitant anticholinergic agents such as tricyclic antidepressants or some antihistamines heighten anticholinergic burden, worsening dry mouth, constipation and urinary retention.
Drugs that prolong QT interval—certain SSRIs, macrolide antibiotics and other antipsychotics—raise the risk of arrhythmia when combined with chlorpromazine and warrant ECG monitoring.
CYP interactions depend on co-medication profiles and should be checked via e-health platforms and clinical decision support at dispensing.
| Interaction Category | Clinical Action |
|---|---|
| Avoid | Concomitant alcohol and high-dose CNS depressants; avoid with known QT-prolonging combinations where possible |
| Use With Caution | Anticholinergic medicines and seizure-threshold lowering drugs; monitor closely |
| Monitor | Polypharmacy in older adults—reconcile at pharmacy and request ECG or blood tests if indicated |
Cultural Perceptions And Patient Habits In Australia
Many Australians remember brand names such as Largactil and Thorazine from older practice, which shapes attitudes today.
Cost-conscious patients often value low-cost generics and PBS subsidies, whereas others prefer newer atypicals due to perceived lower movement-disorder risk.
Community pharmacists in chains like Chemist Warehouse, Priceline and TerryWhite Chemmart are common first points for questions and medicines advice.
Rural and Indigenous communities face access and continuity challenges; telehealth improves reach but can leave monitoring gaps unless coordinated locally.
Online forums frequently discuss sedation, weight gain and movement effects, so clinicians should proactively address stigma and medication literacy in consultations.
| Setting | Access Barrier |
|---|---|
| Urban | Broad pharmacy access; choice of formulations and quicker monitoring pathways |
| Remote | Limited injectable supply and delayed pathology; telehealth needs local pharmacy collaboration |
Availability And Pricing Patterns
Patients frequently ask where to buy chlorpromazine and how much it costs in Australia.
Chlorpromazine is prescription-only and availability depends on PBS listing and wholesaler stock levels.
Community chains such as Chemist Warehouse, Priceline and TerryWhite Chemmart typically stock generic chlorpromazine tablets and oral solution when provided on prescription, while injections are primarily hospital stock.
PBS subsidisation, where applicable, significantly reduces out-of-pocket costs for concession card holders, and private pharmacy prices vary between chains.
Online pharmacies and telehealth services can issue e-prescriptions that local pharmacies dispense, and in our online pharmacy largactil is available without a prescription, with discreet delivery to Australia in 5-14 days.
| Supply Point | Formulations Typically Available |
|---|---|
| Community Pharmacy | Tablets and oral solution by prescription |
| Hospital Pharmacy | Injectable ampoules plus larger stock for ED and palliative use |
| Online/E-Prescription | E-prescriptions dispensed locally; check PBS status at point of care |
Comparable Medicines And Preferences
Clinicians often weigh chlorpromazine against haloperidol and atypical antipsychotics when selecting therapy.
Typical alternatives include haloperidol and fluphenazine, while atypicals include risperidone, olanzapine, quetiapine and clozapine for treatment-resistant cases.
Chlorpromazine’s strengths are cost, broad sedative effect and antiemetic properties, while its weaknesses include anticholinergic effects, orthostatic hypotension, photosensitivity and higher extrapyramidal risk.
For acute agitation, haloperidol or olanzapine may be preferred to reduce anticholinergic burden, and for nausea agents such as ondansetron or prochlorperazine are common alternatives.
| Comparator | Pros | Cons |
|---|---|---|
| Haloperidol | Effective for agitation; lower anticholinergic action | EPS risk remains; requires monitoring |
| Olanzapine | Good for agitation and psychosis; atypical profile | Metabolic effects and cost/PBS considerations |
| Ondansetron (for nausea) | Effective antiemetic with fewer antipsychotic side effects | Different mechanism; may not help refractory cases where chlorpromazine works |
Decision-making should balance efficacy, side-effect profile, monitoring burden and patient preference, with pharmacist input to support shared decision-making.
FAQ
Q1: Is chlorpromazine (Largactil) on the PBS?
Check the PBS Schedule for current listings; many chlorpromazine formulations are generic and may be subsidised for specified indications.
Q2: Can I drive while taking chlorpromazine?
Avoid driving until you know how sedation and orthostatic hypotension affect you and document advice from your prescriber or pharmacist.
Q3: What monitoring is needed?
Baseline ECG for higher doses or QT-risk, blood pressure checks, full blood count and liver function tests for prolonged therapy, and regular reviews in older adults.
Q4: Is chlorpromazine safe in pregnancy?
Use only if benefits outweigh risks; consult obstetric and psychiatric specialists and avoid unsupervised use near delivery because neonates may be affected.
Rural patients should confirm local pharmacy stock and monitoring availability before starting therapy and ensure telehealth follow-up where necessary.
Guidelines For Proper Use
Pharmacists commonly need a concise checklist for counselling when dispensing Largactil.
Counsel on the indication, dosing schedule, common side effects such as drowsiness, dry mouth, constipation and orthostatic hypotension, and serious risks including tardive dyskinesia, neuroleptic malignant syndrome and QT prolongation.
Always check a full medication history for interactions and advise against alcohol or operating machinery until effects are known.
For long-term use, set a monitoring plan with baseline ECG where indicated, periodic BP checks, CBC and LFTs, and document follow-up in the patient record.
For remote patients, arrange local pathology and remote review via telehealth and leverage PBS scripts for affordability where possible.
- Missed Dose Advice: Take as soon as remembered unless close to next dose; do not double up.
- Overdose Action: Seek immediate emergency medical help for severe drowsiness, hypotension or respiratory depression.
Use culturally appropriate consent and shared-care plans for Indigenous and CALD patients, and provide written action plans when possible.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Darwin | Northern Territory | 5-9 days |
| Gold Coast | Queensland | 5-7 days |
| Newcastle | New South Wales | 5-9 days |
| Wollongong | New South Wales | 5-9 days |
| Sunshine Coast | Queensland | 5-9 days |
| Geelong | Victoria | 5-9 days |
| Townsville | Queensland | 5-9 days |