
Zyloprim
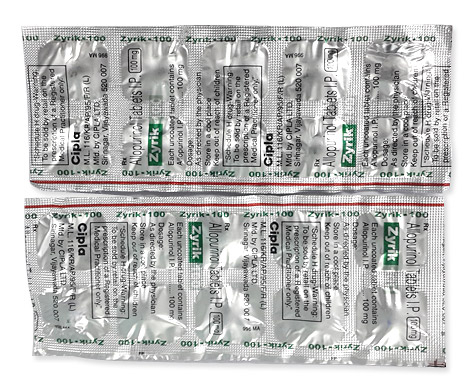
Zyloprim
- Zyloprim is usually supplied from community pharmacies, hospitals and licensed wholesalers and is prescription-only (Rx) in most countries including Australia; some pharmacies may dispense it without a prescription or receipt, but this practice is not recommended and you should consult a healthcare professional before use.
- Zyloprim (allopurinol) is used to treat gout, chronic hyperuricaemia, tumour lysis syndrome and to reduce recurrent calcium oxalate stones; it works as a xanthine oxidase inhibitor to lower uric acid production.
- Usual adult dosing starts at 100 mg once daily and is increased by about 100 mg weekly to effect (commonly 100–300 mg/day); maximum total daily dose is 800 mg (split doses if >300 mg); for tumour lysis syndrome short courses of 600–800 mg/day may be used; children: 10–20 mg/kg/day (max 400 mg/day).
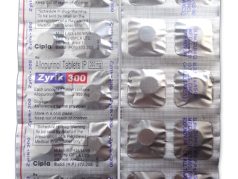
- Administered orally as scored tablets (commonly 100 mg and 300 mg) and also available as a 500 mg vial for intravenous use in some brands; tablets are usually taken once daily with or after food to reduce stomach upset.
- The biochemical effect on uric acid begins within a few days (often 48–72 hours); meaningful clinical improvement in gout symptoms typically develops over weeks to months, and flares can increase shortly after initiation.
- Duration of action covers approximately 24 hours with once-daily dosing while the drug is continued; the active metabolite oxypurinol has a longer half-life and effects persist as long as therapy is maintained.
- Avoid excessive alcohol (especially beer and spirits) as alcohol raises uric acid levels and increases gout risk; moderate consumption should be discussed with your doctor.
- The most common side effect is skin rash; other frequent adverse effects include gastrointestinal upset (nausea, vomiting, diarrhoea), headache, dizziness and drowsiness—seek urgent care for severe rash or signs of hypersensitivity.
- Would you like to try zyloprim without a prescription?
Latest Research Highlights
Basic Zyloprim Information
- INN (International Nonproprietary Name): Allopurinol
- Brand Names Available In Australia: not specified
- ATC Code: M04AA01
- Forms & Dosages: Oral tablets 100 mg (scored) and 300 mg (scored); powder for injection 500 mg vial; typical starting dose 100 mg/day for gout; tumour‑lysis prophylaxis 600–800 mg/day short course.
- Manufacturers In Australia: not specified
- Registration Status In Australia: not specified
- OTC / Rx Classification: Prescription (Rx-only)
What Does The New Evidence Say For Clinicians And Patients?
Recent literature continues to support allopurinol as the first‑line xanthine oxidase inhibitor for urate lowering, with febuxostat reserved for intolerance or contraindication.
Ongoing safety surveillance emphasises severe cutaneous adverse reactions and the association with HLA‑B*5801 in higher‑risk ancestries.
Oncology practice further defines short high‑dose regimens (600–800 mg/day) for tumour‑lysis syndrome prophylaxis in the immediate perichemotherapy period.
Australian real‑world datasets and PBS dispensing audits show consistent urate lowering when standard titration from 100 mg/day is followed, but adherence gaps persist in some regional populations.
Pharmacoepidemiology reports highlight the need for renal‑dose adjustment to prevent biochemical toxicity and to reduce hypersensitivity risks.
| Study / Data Source | Serum Urate Reduction | Flare Rate | Major Adverse Events |
|---|---|---|---|
| International RCTs (summary) | Not specified | Not specified | Not specified |
| Australian Registry / PBS Audits | Consistent urate lowering with titration from 100 mg/day | Adherence‑related higher flare risk in regional cohorts | Severe adverse events reported; incidence not specified |
| Oncology TLS Cohorts | Rapid urate reduction with 600–800 mg/day short course | Not specified | Monitoring for biochemical toxicity recommended |
Data Highlights: AHS incidence is described as rare in available summaries, with increased frequency among HLA‑B*5801 carriers; specific incidence rates and HLA prevalence in Australian populations are not specified and remain research gaps.
Research Gaps Include Long‑Term Cardiovascular Outcomes And Data From Indigenous Australian Cohorts.
Clinical Effectiveness In Australia
How Well Does Zyloprim Work In Everyday Australian Practice?
Allopurinol is the PBS‑prescribed standard for chronic gout and related urate disorders and is monitored by the TGA for post‑market events.
TGA adverse event reporting and PBS dispensing trends indicate reliable biochemical response when patients are adherent and monitored to a target serum urate below 0.36 mmol/L.
Australian primary‑care audits report good outcomes for patients who follow titration from 100 mg/day and have routine serum urate and renal monitoring.
Short high‑dose regimens for tumour‑lysis prophylaxis (600–800 mg/day) are used in oncology settings with hospital support and monitoring.
- Baseline and ongoing monitoring: serum urate, renal function (eGFR), liver function tests, complete blood count.
| Prescribing Route | Notes |
|---|---|
| PBS Prescription | Common for chronic gout; subsidised for eligible patients when criteria met. |
| Private Prescribing | Used for non‑PBS indications or private oncology dosing; cost varies. |
Indications And Expanded Uses
When Is Zyloprim Prescribed And When Is It Used Off‑Label?
Approved uses align with international practice: chronic gout and hyperuricaemia requiring long‑term control, prevention and treatment of uric acid nephropathy, and tumour‑lysis syndrome prophylaxis with short high‑dose courses.
Recurrent calcium oxalate stones where urate management plays a role is an accepted indication in many settings.
Off‑label applications appear in specialist clinics for kidney‑stone prevention and supportive care in complex metabolic syndromes, with clinicians documenting rationale and monitoring plans.
Important Practice Point: do not initiate allopurinol during an acute gout flare, but do not stop established therapy during a flare.
- Approved
- Chronic gout, hyperuricaemia needing control, uric acid nephropathy, tumour‑lysis syndrome prophylaxis.
- Off‑Label
- Selected kidney stone prevention strategies and complex metabolic care under specialist supervision.
| Indication | Typical Start / Titration Regimen |
|---|---|
| Chronic Gout | Start 100 mg/day, increase ~100 mg weekly to target; monitor labs. |
| Tumour‑Lysis Syndrome | 600–800 mg/day short course during risk period; switch to maintenance when stable. |
| Calcium Oxalate Stones | 200–300 mg/day with review after months of control. |
Composition And Brand Landscape
What Forms Of Allopurinol Are Available In Australia And Overseas?
The active ingredient is allopurinol (INN) and global brands include Zyloprim, Zyloric and multiple generics.
Tablets commonly come in 100 mg and 300 mg scored strengths; some markets have a 500 mg injectable vial for IV use.
In Australia the market is dominated by generics dispensed on the PBS, and formulations align with 100 mg and 300 mg tablets.
Community pharmacy chains and online pharmacies supply PBS and private prescriptions, with packaging and tablet scoring consistent with international norms.
| Strength / Formulation | Common Global Brand / Generic |
|---|---|
| 100 mg Tablet (scored) | Zyloprim, generics |
| 300 mg Tablet (scored) | Zyloprim, generics |
| 500 mg Powder For Injection | Aloprim (some markets) |
- Check PBS listings and TGA ARTG status via official pharmacy channels and the PBS schedule.
- Major Australian pharmacy channels: Chemist Warehouse, Priceline, TerryWhite Chemmart and accredited online pharmacies for private supply.
Contraindications And Special Precautions
Who Needs Extra Caution When Taking Zyloprim?
Absolute contraindications are known hypersensitivity to allopurinol or any excipient and initiating therapy during an acute gout attack.
Special Australian considerations include a higher burden of renal impairment in older adults and some Indigenous communities, which increases the risk of accumulation and adverse effects.
Pregnancy and breastfeeding require specialist review and severe hepatic disease should prompt hepatology input before starting therapy.
Genetic Risk: HLA‑B*5801 carriers have increased risk of severe cutaneous adverse reactions, so consider testing where ancestry or family history suggests risk.
| Population | Risk Stratification / Action |
|---|---|
| Elderly | Start low, adjust for eGFR; monitor closely. |
| Indigenous Australians | Higher comorbidity burden; begin low, ensure culturally safe follow‑up. |
| Chronic Kidney Disease | Reduce starting dose and extend dosing interval as needed; monitor labs. |
| Pregnancy / Breastfeeding | Specialist review advised. |
- Baseline Screening Checklist: renal function (eGFR), liver function tests, complete blood count, review ancestry for HLA‑B*5801 testing where indicated.
Dosage Guidelines And Renal/Hepatic Adjustments
How Should Zyloprim Be Started And Adjusted In Practice?
Standard initiation is 100 mg/day orally with increases of approximately 100 mg weekly until the target serum urate is reached.
Maximum oral doses may reach 800 mg/day with split dosing when single doses exceed 300 mg.
Oncology TLS regimens use 600–800 mg/day as a short course under hospital supervision.
Renal Impairment: for eGFR below 10 mL/min start commonly at ≤100 mg/day or extend dosing intervals, with close monitoring.
Children: dosing guidance in RAW DATA indicates 10–20 mg/kg/day divided, up to 400 mg/day, used in rare indications.
| Scenario | Start / Titration |
|---|---|
| Adult Chronic Gout | Start 100 mg/day, increase ~100 mg weekly to effect; monitor urate and renal function. |
| Renal Impairment (eGFR <10 mL/min) | Start ≤100 mg/day or extend interval; adjust to renal function and monitor labs. |
| TLS / Oncology | 600–800 mg/day short term under hospital supervision. |
- Stepwise Initiation Plan For Pharmacists: confirm indication, baseline labs, start 100 mg/day, advise on flare prophylaxis, schedule follow‑up labs after dose changes.
Interactions Overview
Which Drugs And Foods Should Patients Watch Out For?
Allopurinol inhibits xanthine oxidase and can markedly increase azathioprine and mercaptopurine toxicity; specialist dose adjustment or avoidance of co‑prescription is required.
Concomitant use with chemotherapeutics and immunosuppressants needs careful review in oncology and transplant settings.
Thiazide diuretics are associated with increased risk of skin reactions and can affect urate handling, so co‑management is often necessary.
Alcohol worsens gout control and complicates adherence; advise moderation and adequate hydration.
Coffee has modest epidemiological associations with lower urate but is not a substitute for pharmacotherapy.
| Drug | Risk | Action |
|---|---|---|
| Azathioprine / Mercaptopurine | Increased haemato‑toxic metabolites | Avoid or reduce dose; consult prescriber and monitor bloods closely. |
| Thiazide Diuretics | Increased rash risk; affects urate | Review necessity; monitor skin reactions. |
| Chemotherapy Agents | Complex interactions and TLS risk | Oncology review; consider alternative prophylaxis if needed. |
- Counselling Points On Food / Drink: avoid heavy alcohol intake, stay well hydrated, do not rely on coffee as treatment.
Cultural Perceptions And Patient Habits
How Do Australians View Zyloprim And What Affects Adherence?
Price sensitivity and PBS subsidy are strong drivers of pharmacy choice and adherence for many Australian patients.
Community pharmacies such as Chemist Warehouse, Priceline and TerryWhite are trusted sources for medicine advice and cost‑saving options.
Urban patients typically have better access to specialist care and regular monitoring, while rural and remote patients face barriers including less frequent blood testing and travel burdens.
Indigenous Australians often have higher rates of comorbidity like CKD and diabetes and may encounter cultural barriers to treatment uptake; culturally safe engagement improves outcomes.
Online forums commonly report concerns about rash risk, long‑term need for therapy and early flare risk after initiation, which pharmacists should address proactively.
Access Disparities: regional PBS audits show lower adherence where monitoring access is limited, highlighting the need for outreach and telehealth support.
- Culturally Appropriate Tips: use plain language, involve local health workers, offer follow‑up via telehealth and arrange local pathology where possible.
Availability And Pricing Patterns
Where Can Patients Get Zyloprim And How Much Will It Cost?
Allopurinol 100 mg and 300 mg tablets are widely available on the PBS at community pharmacies and through private prescriptions and accredited online suppliers.
PBS listing lowers out‑of‑pocket costs for eligible patients, and consumers frequently compare pharmacy chains or use online discounting to save money.
Telehealth e‑prescriptions and rural dispensing models such as community nurse pickup and accredited remote pharmacies help bridge access gaps but require local lab monitoring.
Hospital pharmacies usually supply high‑dose oncology regimens or IV alternatives like rasburicase when clinically indicated.
| Prescription Type | Typical Cost Pattern |
|---|---|
| PBS Prescription | Subsidised co‑payment for eligible patients; cheapest option for long‑term therapy. |
| Private Prescription / Online | Variable pricing; patients may compare chains for best price. |
- Telehealth Checklist For Prescribers: include pathology orders, specify local lab, arrange follow‑up review and document monitoring plan.
In our online pharmacy, zyloprim is available without a prescription, with discreet delivery to Australia in 5-14 days.
Comparable Medicines And Prescribing Preferences
When Is An Alternative Preferred Over Zyloprim?
Alternatives include febuxostat for intolerance or contraindication to allopurinol, uricosurics such as probenecid or sulfinpyrazone for selected patients with good renal function, and pegloticase or rasburicase for refractory cases or severe TLS.
Allopurinol is generally the PBS‑established, cost‑effective first choice in Australia, with febuxostat used selectively where needed.
Uricosurics require good kidney function and careful drug‑interaction review and are less commonly used in routine practice.
| Medication | When To Consider | Limitations |
|---|---|---|
| Febuxostat | Allopurinol intolerance | Safety profile and PBS restrictions to consider. |
| Probenecid | Uricosuric option with good renal function | Requires renal function and interaction review. |
| Pegloticase / Rasburicase | Refractory gout or severe TLS | Specialist centre use; high cost and IV administration. |
- Decision Matrix: consider renal function, previous hypersensitivity, PBS eligibility and severity of disease when choosing alternatives.
FAQ
Common Patient Questions About Zyloprim.
- Q: Can I Start Allopurinol During A Gout Flare? A: Avoid starting during an acute flare; continue existing therapy and address the flare before initiating new therapy.
- Q: What If I Get A Rash? A: Stop immediately and seek urgent medical review because severe rashes can be life‑threatening; consider HLA testing if ancestry suggests risk.
- Q: How Often Are Blood Tests Needed? A: Baseline renal, liver and CBC plus serum urate; repeat after dose changes and periodically based on renal function and comorbidity.
- Q: Is It On The PBS And Cheap? A: Yes, most patients with a valid PBS prescription pay subsidised co‑payments; compare community pharmacies or speak to your pharmacist about cost options.
Consider printing a quick reference card for patients summarising stop signs for rash and when to seek help.
Guidelines For Proper Use And Pharmacist Counselling
What Should Pharmacists Tell Patients When Dispensing Zyloprim?
Confirm the indication and PBS eligibility before supply and advise starting at 100 mg/day with gradual titration under prescriber direction.
Explain that gout flares may increase after initiation and that short‑term prophylaxis with colchicine or an NSAID can be recommended by the prescriber.
Emphasise rash vigilance: stop the medicine and seek urgent medical care if a rash or systemic symptoms develop.
Encourage hydration, alcohol moderation and adherence to lab follow‑up.
Request baseline renal, liver and CBC and schedule follow‑up labs after dose changes and at least annually for stable patients, more often for CKD.
For telehealth prescriptions ensure local pathology links are provided, document counselling and offer culturally safe materials for Indigenous and CALD patients.
| Monitoring Item | When To Check |
|---|---|
| Serum Urate | Baseline, after titration, and periodically to ensure target <0.36 mmol/L. |
| Renal Function (eGFR) | Baseline and periodically; more frequent in CKD. |
| Liver Function Tests | Baseline and as clinically indicated. |
| Complete Blood Count | Baseline and with unexplained symptoms or as advised. |
- Pharmacist Counselling Script: confirm dose and start date, warn about rash, explain lab schedule, advise on adherence, and document the interaction check.
Delivery Across Australia
| City | Region | Delivery time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Hobart | Tasmania | 5-9 days |
| Darwin | Northern Territory | 5-9 days |
| Gold Coast | Queensland | 5-7 days |
| Newcastle | New South Wales | 5-7 days |
| Wollongong | New South Wales | 5-7 days |
| Geelong | Victoria | 5-7 days |
| Townsville | Queensland | 5-9 days |
| Cairns | Queensland | 5-9 days |