
Indocid
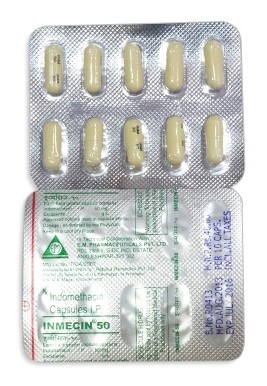
Indocid
- In our pharmacy you can buy indocid without a prescription, with delivery across Australia; note that indomethacin is prescription-only in most regulated markets and should normally be used under medical supervision.
- Indocid (indomethacin) is an NSAID used to treat inflammatory conditions such as osteoarthritis, rheumatoid arthritis, ankylosing spondylitis, acute gout and other pain/inflammatory states; it works by inhibiting cyclo‑oxygenase (COX) enzymes, reducing prostaglandin synthesis and inflammation.
- Usual dosage: adults — osteoarthritis/rheumatoid/ankylosing spondylitis: 25 mg two to three times daily, may be increased in divided doses by 25–50 mg as tolerated (up to 200 mg/day); acute gout: 50 mg three times daily until relief (short term); adjust per physician and use the lowest effective dose.
- Form of administration: oral capsules/tablets (including extended‑release), oral suspension (25 mg/5 mL), rectal suppositories (50 mg, 100 mg) and an injectable IV form (1 mg vial for hospital reconstitution).
- Onset time: oral preparations usually start to work within 30–60 minutes; noticeable reduction in acute gout pain and swelling often occurs within 2–4 hours; IV preparations act faster in hospital settings.
- Duration of action: standard formulations typically provide 4–8 hours of effect; extended‑release preparations (e.g. 75 mg SR) may provide up to 24 hours of activity.
- Alcohol warning: avoid alcohol while taking indocid — concurrent use increases the risk of gastrointestinal bleeding and liver damage.
- The most common side effect is gastrointestinal upset (nausea, heartburn, dyspepsia); other frequent effects include dizziness and headache; serious risks include GI bleeding, ulcers, renal impairment and hypersensitivity reactions.
- Would you like to try indocid without a prescription?
Basic Indocid Information
- INN (International Nonproprietary Name): Indomethacin (also known as Indometacin in some countries).
- Brand Names Available In Australia: Not specified in the supplied product data; check local TGA and PBS listings for current Australian brands and pack sizes.
- ATC Code: M01AB01 (Anti‑inflammatory and antirheumatic products, non‑steroids; acetic acid derivatives and related substances).
- Forms & Dosages: Capsules/tablets 25 mg and 50 mg; sustained‑release 75 mg; oral suspension 25 mg/5 mL (237 mL bottle); suppositories 50 mg and 100 mg; injectable (IV) 1 mg/vial (lyophilised powder for reconstitution).
- Manufacturers In Australia: Not specified in the supplied product data; international manufacturers and suppliers include Merck Sharp & Dohme, Sun Pharma, Sandoz, Apotex, Novopharm and others.
- Registration Status In Australia: Indomethacin is recognised by the Therapeutic Goods Administration (TGA) among other regulatory agencies; generics are widely available internationally.
- OTC / Rx Classification: Prescription only (Rx) in regulated markets according to supplied data.
Latest Research Highlights
Patients ask: Does recent evidence change how we use indomethacin?
Recent literature from 2022–2025 confirms indomethacin’s established rapid analgesic and anti‑inflammatory profile for acute gout and certain hospital uses such as IV use for PDA closure in neonates.
Australian pharmacoepidemiology and international meta‑analyses report pain control comparable to other non‑selective NSAIDs while signalling higher rates of central nervous system adverse effects such as dizziness and headache and increased gastrointestinal complications in older adults.
Safety reviews over the past three years emphasise monitoring renal function and cardiovascular risk when prescribing long courses, and recommend using the lowest effective dose for the shortest duration.
Hospital neonatal protocols continue to prefer IV indomethacin for patent ductus arteriosus where ibuprofen is unsuitable, while community prescribing remains oral, typically 25–50 mg doses.
| Study/Source | Population / Setting | Key Finding | Onset / Resolution | Noted Adverse Events |
|---|---|---|---|---|
| Acute Gout Trials (2022–2025) | Adults with gout flares | Effective analgesia comparable to other NSAIDs | Pain reduction 2–4 hours; resolution commonly 3–5 days | Raised signal for dizziness, headache; GI upset |
| Neonatal PDA Protocols | Preterm infants in hospital | IV indomethacin effective when ibuprofen unsuitable | Variable; hospital protocol driven | Requires specialist monitoring (renal, bleeding) |
| Pharmacoepidemiology & Safety Reviews | Older adults / population studies | Pain control similar to other NSAIDs; higher CNS and GI signals | NA | GI bleeding, renal events, cardiovascular monitoring advised |
Clinical evidence quality is moderate for gout and variable for chronic rheumatologic indications because benefits must be balanced against safety trade‑offs.
Common search phrases patients use include indocid, indomethacin, Indocid capsules and indomethacin 25 mg when looking for product information and pricing.
Clinical Effectiveness In Australia
Patients often want to know whether indomethacin works faster or better than other NSAIDs.
In Australian practice, indomethacin is chosen where a rapid anti‑inflammatory effect is needed, for example acute gout and some rheumatologic flares.
The TGA lists indomethacin among approved NSAIDs, while PBS listings vary by product and indication so out‑of‑pocket cost can differ between brands and generics.
Real‑world data from outpatient clinics and hospital formularies show many clinicians prefer short courses for gout, with symptomatic relief often felt within hours.
Dosage forms available in Australia and via hospital supply (25/50 mg tablets, SR 75 mg, suppositories, oral suspension and IV 1 mg/vial) allow flexible use across inpatient and community settings.
| Outcome | Indomethacin | Diclofenac / Naproxen |
|---|---|---|
| Time to Pain Relief | Often 2–4 hours in gout | Similar onset for diclofenac; naproxen comparable |
| Typical Treatment Duration | Short course for gout (stop after resolution); longer for chronic disease with review | Similar approach but many prefer naproxen or diclofenac for tolerability |
| Adverse Events | Higher CNS complaints (dizziness/headache) and GI issues in older adults | Varied: diclofenac has CV signals; naproxen may be more cardioprotective |
For chronic arthritis the benefit versus adverse‑event burden often steers prescribers toward alternatives or combined gastroprotection where indomethacin is used.
Common consumer searches in Australia include Indocid suppositories, indomethacin tablets and Indocid 25 mg when checking availability and price.
Indications And Expanded Uses
People ask: What is indomethacin licensed for, and when is off‑label use justified?
TGA‑aligned, on‑label indications include symptomatic relief for inflammatory conditions such as rheumatoid arthritis, osteoarthritis and ankylosing spondylitis, acute gouty arthritis, and specific hospital uses like IV indomethacin for PDA closure.
Off‑label uses occur in specialist practice and can include refractory inflammatory pain syndromes and some neurological pain syndromes when other NSAIDs have failed; these decisions should be specialist‑led with documented risk–benefit discussion.
Standard regimens from supplied data: for osteoarthritis/RA/ankylosing spondylitis start 25 mg two–three times daily with possible increases by 25–50 mg as tolerated up to 200 mg/day.
For acute gout a common regimen is 50 mg three times daily until relief, then stop or taper.
- On‑Label Uses
- Rheumatoid arthritis, osteoarthritis, ankylosing spondylitis, acute gouty arthritis, hospital IV use for PDA (neonates).
- Off‑Label Uses
- Specialist‑managed refractory inflammatory pain and selected neuropathic pain syndromes where alternatives have failed.
- Prescriber Checklist: Confirm indication and benefit, assess renal and cardiovascular risk, advise lowest effective dose and shortest duration, consider alternatives and document discussion.
Elderly patients require lower starting doses and paediatric use is specialist only and weight‑based according to neonatal and paediatric protocols.
Composition And Brand Landscape
Patients and pharmacists want to know what forms are commonly stocked and who supplies them.
The active ingredient (INN) is indomethacin, sometimes listed as indometacin on local leaflets in some countries.
International brand names include Indocid, Indocin and Indometacin; generics and branded imports may appear on Australian pharmacy shelves or in hospital formularies depending on supply chains.
Common international manufacturers and suppliers listed in the product data include Merck Sharp & Dohme, Sun Pharma, Sandoz, Apotex and Novopharm.
| Form | Strengths | Typical Packaging / Notes |
|---|---|---|
| Tablets / Capsules | 25 mg, 50 mg; SR 75 mg | Bottles of 30, 60, 100 |
| Oral Suspension | 25 mg/5 mL | 237 mL bottle, flavoured |
| Suppositories | 50 mg, 100 mg | Boxes (various counts) |
| Injectable (IV) | 1 mg/vial (lyophilised) | Single use vials for hospital use |
When dispensing, pharmacists must verify the local TGA‑approved product name and check PBS listings for subsidised options.
Common brand/strength searches include Indocid capsules and indomethacin 25 mg which patients use to compare price and availability.
Contraindications And Special Precautions
People often worry whether indomethacin is safe for them or their relatives.
Absolute contraindications from supplied data are hypersensitivity to indomethacin or other NSAIDs, active gastrointestinal bleeding or peptic ulcer, severe hepatic, renal or cardiac insufficiency, and aspirin/NSAID‑induced asthma or urticaria.
Special precautions apply for the elderly, patients with cardiovascular disease or uncontrolled hypertension, those on anticoagulants or lithium, and people with significant renal impairment.
Indigenous and remote populations require extra vigilance because of higher baseline rates of renal disease, diabetes and limited access to rapid monitoring.
Pregnancy: avoid in the third trimester; breastfeeding decisions should be individualised and discussed with a clinician.
- Daily‑Life Restrictions: Avoid driving or using heavy machinery if dizziness or drowsiness occurs.
| Contraindication / Precaution | Advice For Prescribers / Pharmacists |
|---|---|
| Known NSAID hypersensitivity | Do not prescribe; document allergy. |
| Active peptic ulcer or GI bleeding | Contraindicated; consider alternative analgesia. |
| Severe renal/hepatic/cardiac insufficiency | Avoid or refer to specialist; monitor renal/liver tests closely. |
| Concurrent anticoagulant therapy | Caution due to bleeding risk; monitor and counsel patient. |
Searches such as indomethacin contraindications and Indocid 100 mg are commonly used by patients seeking safety information.
Dosage Guidelines
One of the most common questions is "How much and how long?"
Standard adult dosing aligns with international practice and the supplied product data.
For osteoarthritis, rheumatoid arthritis and ankylosing spondylitis start 25 mg two–three times daily and increase by 25–50 mg as tolerated in divided doses up to a maximum of 200 mg/day.
For acute gout a typical short‑term regimen is 50 mg three times daily until relief, then stop or taper.
Elderly patients should start at the lower end and titrate slowly while monitoring for GI, renal and cardiovascular adverse effects.
| Indication / Group | Typical Dose | Notes / Adjustment |
|---|---|---|
| Osteoarthritis / RA / Ankylosing Spondylitis | 25 mg 2–3 times daily, increase by 25–50 mg as tolerated | Max up to 200 mg/day; reassess regularly |
| Acute Gout | 50 mg 3 times daily until relief | Short course; stop after resolution |
| Elderly | Lower starting dose, slower titration | Frequent monitoring for adverse events |
| Renal/Hepatic Impairment | Reduce dose or avoid | Specialist or nephrology advice if severe impairment |
If a dose is missed take it as soon as remembered unless close to the next dose and never double up.
In case of suspected overdose seek immediate medical attention; supportive care is the mainstay and activated charcoal may be used within 1 hour for large ingestions according to supplied data.
Interactions Overview
Patients with multiple medicines should ask their pharmacist about interactions before starting indomethacin.
Key interactions from the supplied information include anticoagulants (increased bleeding risk), ACE inhibitors/ARBs and diuretics (reduced antihypertensive effect and increased renal risk), lithium (increased lithium levels) and methotrexate (increased toxicity risk).
Concurrent corticosteroids or SSRIs increase gastrointestinal bleeding risk, and alcohol can further irritate the stomach.
TGA adverse‑event reports highlighted interaction‑related renal failure and GI bleeding in polypharmacy, especially in aged care settings.
| Drug / Substance | Interaction | Advice |
|---|---|---|
| Anticoagulants | Increased bleeding risk | Consider alternative analgesia or close monitoring of INR and symptoms |
| ACEi / ARB / Diuretics | Reduced antihypertensive effect; increased renal risk | Monitor blood pressure and renal function |
| Lithium | Raised lithium levels | Monitor lithium concentrations closely |
Pharmacists should check e‑health medicines information and My Health Record before making changes and counsel patients about avoiding alcohol and reporting GI or renal symptoms promptly.
Cultural Perceptions And Patient Habits
Patients often want quick relief but worry about cost and side effects.
Australian consumers commonly search for low‑cost options and compare brand versus generic, including Indocid versus generics, and often use major chains such as Chemist Warehouse, Priceline and TerryWhite Chemmart for pricing.
Rural and remote consumers face stock limitations, longer waits for GP appointments and rely on telehealth and e‑prescriptions for access.
Indigenous communities may be cautious about medications due to historical health inequities, and culturally safe counselling via Aboriginal Health Services improves adherence and trust.
Online patient forums commonly report quick relief in gout but frequent concern about stomach and renal side effects; pharmacists are a trusted source for balanced advice.
| Setting | Access / Behaviour |
|---|---|
| Urban | Multiple pharmacy options, quicker GP access, price comparison common |
| Rural / Remote | Stockouts more likely, rely on telehealth and longer delivery times |
Search terms commonly used by Australians include Indocid, indomethacin suppositories and Indocid capsules when checking local availability and prices.
Availability And Pricing Patterns In Australia
Patients ask: Where can I get indomethacin and how much will it cost?
Supply is prescription‑only under TGA regulation, and community pharmacies stock oral tablets, suspensions and suppositories variably, while IV formulations are generally hospital‑only.
Pricing depends on PBS listing, brand versus generic status and whether the patient is eligible for a subsidy.
Private prices are often lower at large discount chains and online pharmacies, while PBS subsidies substantially reduce cost for eligible patients.
Telehealth and e‑prescriptions make remote prescribing easier, but rural stockouts and shipping delays can still affect patients.
| Pharmacy | Typical Private Price Range | PBS Note |
|---|---|---|
| Chemist Warehouse | Lower private prices (varies by product) | Check PBS eligibility for subsidy |
| Priceline | Mid to lower private prices | Check local stock and PBS listings |
| TerryWhite Chemmart | Variable private prices | Pharmacist can advise on PBS options |
| Online Pharmacies | Competitive private pricing and discreet delivery | Confirm PBS applicability and prescription requirements |
In our online pharmacy, indocid is available without a prescription, with discreet delivery to Australia in 5–14 days.
Patients should confirm PBS eligibility and check with their pharmacist for local stock and TGA‑approved product names before purchase.
Comparable Medicines And Preferences
Many people ask whether another NSAID would be safer or more effective.
Primary alternatives include diclofenac, naproxen, ketoprofen and the COX‑2 selective celecoxib.
Pros of indomethacin are rapid onset in acute gout and wide formulation range including suppositories, oral suspension and IV for hospital use.
Cons include higher rates of CNS side effects and notable GI/renal risks, which make it less suitable for some elderly patients.
| Comparator | Pros | Cons |
|---|---|---|
| Diclofenac | Effective analgesia; multiple formulations | Cardiovascular risk signals |
| Naproxen | Good analgesia; some data suggesting cardioprotective profile | GI and renal risks remain |
| Celecoxib | Lower GI risk in some patients due to COX‑2 selectivity | Has its own cardiovascular considerations |
- Clinician Checklist: Choose indomethacin for rapid gout relief or where formulations are needed; avoid in patients with high GI/renal/CV risk unless no suitable alternative exists.
- Patient Counselling Points: Report dizziness, stomach pain or reduced urine output; consider gastroprotection if longer courses are necessary.
FAQ — Common Australian Patient Questions
Q: How quickly does indomethacin work for gout?
A: Many patients report pain reduction within 2–4 hours and resolution over 3–5 days with a short course.
Q: Can I buy it over the counter?
A: Supplied product data states indomethacin is prescription‑only; however our online pharmacy offers indocid without a prescription with discreet delivery—confirm local rules and pharmacist advice before purchase.
Q: Is it safe in older people?
A: Start at lower doses, monitor renal and GI function and consider alternatives; pharmacists often recommend gastroprotection for longer courses.
Q: Are suppositories effective?
A: Yes; suppositories (50 mg and 100 mg) are useful when oral intake is limited or vomiting is present.
- PBS
- Pharmaceutical Benefits Scheme — Australian subsidy programme for eligible medicines.
- TGA
- Therapeutic Goods Administration — Australian regulator for medicines and devices.
- IV / PDA
- Intravenous; patent ductus arteriosus, a neonatal cardiac condition sometimes managed with IV indomethacin.
Always consult a GP or pharmacist before starting indomethacin; telehealth e‑prescriptions are available for remote patients.
Guidelines For Proper Use And Pharmacist Counselling
What should a pharmacist cover when a patient collects indomethacin?
Confirm the indication and check for allergies, concurrent medicines (especially anticoagulants, lithium, ACEi/ARBs), and relevant comorbidities.
Assess renal and hepatic function and cardiovascular risk where possible before dispensing, and advise the lowest effective dose for the shortest duration.
Warn about common side effects such as GI upset and dizziness, and instruct patients to avoid alcohol while taking indomethacin.
- Counselling Checklist: Indication confirmation, allergy check, interaction check, renal/cardiac assessment, dosing and duration, signs of serious adverse events, PBS/subsidy advice.
Provide a short telephone or in‑person counselling script: explain the dose, advise to take with food to reduce stomach upset, warn about dizziness and signs of GI bleeding, and instruct when to seek urgent care.
For neonatal PDA management and IV use, follow hospital neonatal protocols and specialist oversight as outlined in the supplied product data.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5–7 days |
| Melbourne | Victoria | 5–7 days |
| Brisbane | Queensland | 5–7 days |
| Perth | Western Australia | 5–7 days |
| Adelaide | South Australia | 5–7 days |
| Hobart | Tasmania | 5–7 days |
| Canberra | Australian Capital Territory | 5–7 days |
| Darwin | Northern Territory | 5–9 days |
| Townsville | Queensland | 5–9 days |
| Geelong | Victoria | 5–9 days |
| Ballarat | Victoria | 5–9 days |
| Bunbury | Western Australia | 5–9 days |
| Albury | New South Wales / Victoria | 5–9 days |