
Allopurinol
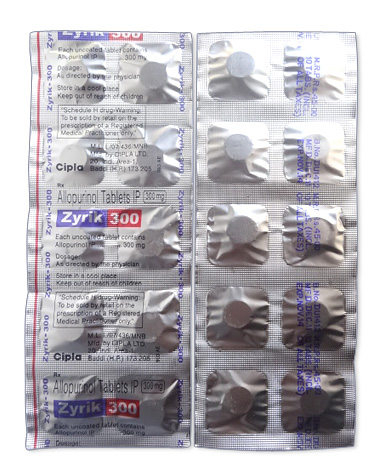
Allopurinol
- In Australia (and most countries) allopurinol is classified as prescription-only (Rx) and is supplied via community and hospital pharmacies with a valid prescription; it is not recommended to obtain or use prescription medicines without medical supervision.
- Allopurinol is used to treat gout and chronic hyperuricaemia, to prevent uric acid kidney stones and tumour lysis syndrome; it is a xanthine oxidase inhibitor that reduces uric acid production (converted in the body to active oxypurinol).
- Usual adult dosing: start low (commonly 100 mg/day) and titrate according to serum uric acid — typical maintenance 200–300 mg/day (mild) and 400–600 mg/day (severe); maximum doses up to 800 mg/day in specialist settings; tumour lysis prophylaxis often uses 600–800 mg/day (divided). Dose reductions required in renal impairment (e.g. if CrCl <20 mL/min often max ~100 mg/day). Children: ~10–20 mg/kg/day (max ~400 mg/day).
- Administered orally — tablets are the standard form (commonly 100 mg and 300 mg); some regions have 200 mg/400 mg or compounded suspensions, but there are no common injectable forms.
- Allopurinol begins to lower serum uric acid within about 24–48 hours, though clinical benefits (fewer attacks, reduction in tophi) usually take several weeks to months as levels are titrated.
- The effect is maintained with once-daily dosing (oxypurinol has a long half-life); clinically the urate-lowering effect persists over 24 hours with regular dosing and steady state is reached over days to weeks.
- Avoid excessive alcohol while on allopurinol — alcohol increases uric acid and the risk of gout flares and may worsen liver function; moderate intake and good hydration are advised.
- The most common side effects include skin rash (stop and seek urgent review if any rash appears), gastrointestinal upset (nausea, diarrhoea), and elevated liver enzymes; rare but serious adverse reactions include severe cutaneous adverse reactions such as Stevens–Johnson syndrome or toxic epidermal necrolysis.
- Would you like to try allopurinol without a prescription?
Basic Allopurinol Information
- INN (International Nonproprietary Name): Allopurinol (also referenced as Allopurinolum or Allopurinolum Ph. Eur.).
- Brand Names Available In Australia: Teva, Sandoz, Mylan/Mayne, Apotex/Arrotex, Sanofi (Zyloric) and other generic brands are represented in global supplier lists; specific local stocking varies by supplier and pharmacy.
- ATC Code: M04AA01.
- Forms & Dosages: Oral tablets are standard, most commonly 100 mg and 300 mg; some regions may offer 200 mg or 400 mg or compounded forms, but oral tablets are the norm.
- Manufacturers In Australia: Not specified in the provided data; major global suppliers include Teva, Sandoz, Mylan, Accord, Zentiva, Aspen and Sanofi (Zyloric).
- Registration Status In Australia: Widely registered internationally and noted as registered with the Australian Therapeutic Goods Administration (TGA).
- OTC / Rx Classification: Prescription-only (Rx) in Australia and other territories due to risk of serious side effects.
Latest Research Highlights
Clinicians ask whether allopurinol still holds up against newer options and what safety signals to watch.
Recent systematic reviews from 2020–2024 continue to support allopurinol’s long‑term effectiveness at lowering serum urate and reducing gout flares and tophi formation.
Head‑to‑head trials comparing febuxostat with allopurinol show febuxostat is typically non‑inferior for urate lowering, but some higher‑risk cardiovascular cohorts had mixed safety signals.
Australian cohort analyses and registry data reinforce efficacy findings while emphasising ongoing vigilance for severe cutaneous adverse reactions (SCARs), including Stevens‑Johnson Syndrome and Toxic Epidermal Necrolysis.
Regulatory summaries from the TGA continue to highlight SCAR risk and recommend targeted HLA‑B*5801 screening for at‑risk ethnic groups.
Nephrology research, including cohort and mechanistic studies, suggests possible stabilisation of renal function with urate‑lowering therapy for selected patients, although large randomised controlled trials are still limited.
Oncology guidance maintains rasburicase as first choice for high‑risk tumour‑lysis syndrome, with allopurinol favoured for lower‑risk prophylaxis or short‑term use.
Practical takeaway: efficacy is well established, cardiovascular safety needs individual assessment, and SCAR screening is a priority for certain ancestries.
Clinical Effectiveness In Australia
Patients often want to know whether allopurinol will stop their flares and dissolve tophi over time.
Allopurinol (INN: Allopurinol; ATC: M04AA01) is a cornerstone urate‑lowering therapy used across Australian primary care and specialist practice for chronic gout and uric acid nephrolithiasis.
Routine PBS prescribing data and primary‑care audits show broad utilisation with the usual serum urate target below 0.36 mmol/L (6 mg/dL).
Titration to achieve and maintain that target is standard practice and determines long‑term success in flare reduction.
TGA pharmacovigilance stresses early rash surveillance and renal and liver monitoring when initiating or escalating dose.
Clinical benefits such as fewer gout flares, gradual tophi dissolution over months to years, and reduced recurrence of uric acid stones are dose‑dependent and require adherence.
In everyday Australian practice GPs commonly start at 100 mg daily and check serum urate every 2–4 months while titrating upward until the target is reached.
Co‑prescribing prophylactic colchicine or an NSAID during initiation is common to reduce paradoxical flares that can follow urate lowering.
Indications And Expanded Uses
People ask whether allopurinol is only for gout or useful in other situations.
TGA‑approved indications include chronic gout and hyperuricaemia requiring long‑term urate lowering, prevention of uric‑acid nephrolithiasis and prophylaxis for tumour‑lysis syndrome in lower‑risk oncology patients.
Off‑label Australian practice sometimes uses allopurinol for hyperuricaemia associated with chronic kidney disease, genetic hyperuricaemia syndromes and in metabolic‑syndrome research settings, typically with specialist oversight and informed consent.
Allopurinol must not be started during an acute gout attack, although patients already established on therapy should generally continue through an acute episode.
Typical tablet strengths available are 100 mg and 300 mg and dosing should be titrated to serum urate; higher short‑term doses such as 600–800 mg/day may be used under oncology guidance for tumour‑lysis prophylaxis.
Regulatory and PBS eligibility varies by indication, so prescribers confirm TGA and PBS criteria when seeking subsidy for long‑term treatment.
Composition And Brand Landscape
People often compare brand names, generics and prices when collecting medicines from a pharmacy.
The active ingredient is allopurinol (INN), a xanthine oxidase inhibitor that blocks uric acid synthesis.
Most Australian supply chains rely on multiple generic manufacturers and established suppliers such as Teva, Sandoz, Mylan, Accord and Sanofi (historically Zyloric).
Standard oral tablet strengths are 100 mg and 300 mg; some suppliers produce 200 mg or 400 mg or provide compounding options, but tablets are the standard presentation.
On the PBS many listed presentations are generics or brand‑neutral, and retail chains commonly stock multiple generics at competitive private prices.
For consumers: a brand is the marketed name while a generic lists the active ingredient and is chemically equivalent once registered.
Pharmacists should check excipients when counselling patients with known allergies to non‑active ingredients.
Contraindications And Special Precautions
Patients frequently ask which groups must avoid allopurinol or need special care.
Absolute contraindications include known hypersensitivity to allopurinol or any excipients and any history of severe cutaneous reactions such as Stevens‑Johnson Syndrome or Toxic Epidermal Necrolysis.
High‑risk groups include people with certain ancestries where HLA‑B*5801 carriage is more common; screening is recommended for at‑risk ethnic groups and specialist input is advised for Indigenous population considerations.
Renal impairment requires dose reduction and careful monitoring; for example, if creatinine clearance (CrCl) is less than 20 mL/min a conservative maximal dose such as 100 mg/day may be considered and individualised.
Allopurinol should not be initiated in pregnancy or breastfeeding unless essential, and elderly patients usually start at lower doses.
Day‑to‑day advice includes stopping immediately and seeking urgent care for any rash, avoiding initiation during an acute gout attack, and not self‑escalating doses without monitoring.
When a rash develops the recommended action is immediate cessation and urgent clinical assessment because a rash can herald SCARs.
Dosage Guidelines
Many patients want clear starting doses and what monitoring they will need.
A common Australian starting dose is 100 mg once daily with stepwise titration guided by serum urate measurements.
Maintenance doses for mild disease are commonly 200–300 mg/day and 400–600 mg/day for more severe disease, with specialist use reaching up to 800 mg/day when required and carefully monitored.
Renal impairment requires dose adjustment and cautious titration; where CrCl is very low clinicians often limit doses to around 100 mg/day and individualise based on response and tolerance.
Children receive allopurinol primarily for chemotherapy‑associated hyperuricaemia or inherited disorders, typically 10–20 mg/kg/day in divided doses up to 400 mg/day.
For tumour‑lysis prophylaxis oncology regimens may use short‑term allopurinol 600–800 mg/day divided with specialist supervision.
Monitoring should include serum urate every 2–4 months during titration and periodic liver and renal function tests thereafter.
Interactions Overview
Patients often ask whether common medicines will clash with allopurinol.
Clinically significant drug interactions include potentiation of azathioprine and mercaptopurine toxicity, so dose reduction or avoidance is required when used together.
Co‑administration with certain cytotoxic agents and didanosine needs specialist oversight and review of current oncology protocols.
Thiazide diuretics have been associated with a higher risk of severe cutaneous reactions when combined with allopurinol and merit careful assessment.
Ciclosporin and other immunosuppressants require close monitoring for interactions and adverse effects.
Alcohol does not directly change allopurinol pharmacokinetics but increases gout risk and undermines urate control; counsel patients on hydration and moderation.
Coffee has epidemiological associations with lower gout risk but is not a substitute for prescription therapy.
Cultural Perceptions And Patient Habits In Australia
Patients ask whether cultural beliefs or cost will affect their treatment choices.
Australian patients are often price‑sensitive and look for PBS‑subsidised generics or competitive private prices at retail chains and online pharmacies.
Trust in pharmacists for counselling is high, particularly in regional and rural communities where GP access can be limited.
Telehealth e‑prescriptions have increased access but can complicate baseline pathology if local testing is delayed.
Common patient concerns seen in forums and community conversations include confusion about starting during a flare, fear of rash, stopping medication when asymptomatic and reliance on natural remedies.
Indigenous and multicultural communities may have different health beliefs and it is important to provide culturally safe communication and to check ancestry for HLA‑B*5801 risk when relevant.
Adherence barriers include initial paradoxical flares and medication cost when PBS criteria are not met, while adherence facilitators include reminder apps, pharmacist follow‑ups and clear written leaflets.
Availability And Pricing Patterns
Customers want to know where to buy allopurinol and how much it will cost out of pocket.
Allopurinol is prescription‑only in Australia and widely available through PBS‑subsidised listings for eligible patients.
Private prices vary across retailers such as Chemist Warehouse, Priceline and TerryWhite Chemmart, and online pharmacies often advertise lower retail rates for generic 100 mg and 300 mg tablets.
PBS coverage reduces out‑of‑pocket cost for concession and general patients who meet subsidy criteria, while some generics may be cheaper off‑PBS but require a private script.
Rural centres can face occasional supply delays, but many pharmacies offer home delivery or click‑and‑collect services and telehealth scripts can be dispensed locally.
In our online pharmacy, allopurinol is available without a prescription, with discreet delivery to Australia in 5‑14 days.
When advising patients, pharmacists should check pack sizes (commonly 30, 60 or 90 tablets) and confirm PBS entitlement to reduce cost barriers.
Comparable Medicines And Preferences
People often ask whether febuxostat or other drugs are better than allopurinol.
Febuxostat is an alternative xanthine oxidase inhibitor and is useful for patients intolerant of allopurinol, but it carries cardiovascular safety caveats in some populations and requires assessment of cardiovascular risk before use.
Uricosuric agents such as probenecid and sulfinpyrazone increase renal uric acid excretion and suit under‑excretors with adequate renal function, but are less used where CKD is present.
Rasburicase is reserved for rapid urate breakdown in high‑risk tumour‑lysis syndrome and is not a chronic‐use option.
Choice considerations in Australia favour allopurinol as first‑line due to cost, PBS access, clinician familiarity and a long safety record, with alternatives for intolerance or contraindication.
Frequently Asked Questions
- Can I Start Allopurinol During A Gout Flare?
No — initiation during an acute attack can worsen flares; continue if already established but start only after the flare has settled and consider prophylaxis.
- Do I Need Tests Before Starting?
Yes — baseline renal function, liver function tests, full blood count and serum urate are recommended, and consider HLA‑B*5801 testing for at‑risk ancestries.
- What If I Get A Rash?
Stop immediately and seek urgent assessment because a rash can herald life‑threatening SCARs such as SJS/TEN.
- How Long Until It Works?
Serum urate usually falls within weeks, but tophi and reduced flare frequency can take months to years and depend on adherence and dose titration.
Contact your clinician urgently for rash, fever, mucosal lesions or widespread skin changes.
Guidelines For Proper Use And Pharmacist Counselling
Pharmacists need a clear checklist to counsel patients safely and effectively.
Confirm the indication and PBS eligibility before dispensing and review concomitant medications such as azathioprine, mercaptopurine and thiazides for interaction risk.
Check baseline renal and hepatic results and advise a typical starting dose of 100 mg/day with gradual titration to serum urate targets.
Explain the need for blood tests every 2–4 months during titration and periodic monitoring thereafter.
Recommend co‑prescription prophylaxis during initiation, for example colchicine 0.5 mg once daily or an appropriate NSAID where not contraindicated, to reduce paradoxical flares.
Advise on hydration, moderation of alcohol and the importance of stopping and seeking urgent care for any rash or mucosal symptoms.
Provide a simple patient leaflet covering purpose, expected timeline, side‑effect red flags, missed‑dose instructions (take when remembered, do not double) and storage below 25°C.
Where telehealth or rural dispensing is in use, arrange local pathology access and pharmacy‑led follow‑up by phone or text to check progress and adherence.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Hobart | Tasmania | 5-9 days |
| Darwin | Northern Territory | 5-9 days |
| Newcastle | New South Wales | 5-9 days |
| Wollongong | New South Wales | 5-9 days |
| Gold Coast | Queensland | 5-9 days |
| Sunshine Coast | Queensland | 5-9 days |
| Geelong | Victoria | 5-9 days |
| Ballarat | Victoria | 5-9 days |