
Zoloft
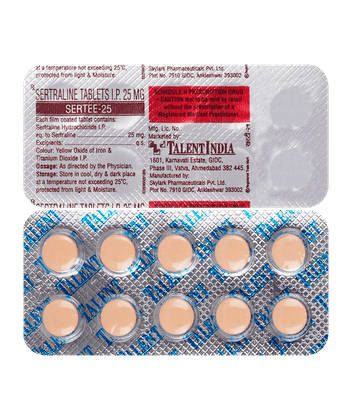
Zoloft
- In pharmacies, Zoloft (sertraline) is a prescription-only medicine in Australia and many other countries, but availability and supply rules can vary by location and pharmacy.
- Zoloft is used to treat depression, obsessive compulsive disorder, panic disorder, post-traumatic stress disorder, social anxiety disorder, and premenstrual dysphoric disorder. It is a selective serotonin reuptake inhibitor (SSRI), which works by increasing serotonin levels in the brain.
- The usual dose of Zoloft is 50 mg once daily for most adults, with a typical range of 50–200 mg daily depending on the condition and response. Some conditions may start at 25 mg daily, and the maximum daily dose is usually 200 mg.
- The form of administration is an oral tablet or oral concentrate/solution. Tablets are available in 25 mg, 50 mg, and 100 mg strengths, and the oral concentrate is 20 mg/mL and must be diluted before use.
- Zoloft usually starts to work within 1–4 weeks, although some people may notice early improvements sooner.
- The duration of action is about 24 hours, so it is generally taken once daily. Full treatment courses may continue for weeks to months or longer, depending on the condition.
- Do not drink alcohol while taking Zoloft, as alcohol may increase side effects such as drowsiness, dizziness, and impaired concentration.
- The most common side effects are nausea, diarrhoea, dry mouth, insomnia, drowsiness, headache, dizziness, sweating, fatigue, and sexual dysfunction.
- Would you like to try Zoloft without a prescription?

Basic Zoloft Information
- INN (International Nonproprietary Name): Sertraline
- Brand names available in Australia: Zoloft and generic sertraline, depending on PBS listing and pharmacy stock
- ATC Code: N06AB06
- Forms & dosages: Tablets 25 mg, 50 mg, 100 mg; oral concentrate 20 mg/mL, 60 mL multidose bottle
- Manufacturers in Australia: Pfizer originator brand, with generic suppliers varying by PBS and wholesaler availability
- Registration status in Australia: Prescription only (Rx); no OTC version
- OTC / Rx classification: Prescription only (Rx)
Latest Research Highlights In Australia And Globally
Thinking about whether Zoloft is actually worth the hassle of starting an antidepressant?
That is a fair question, especially when the first few weeks can feel awkward before things improve.
Sertraline is the INN for Zoloft and sits in the SSRI class, with the ATC code N06AB06.
Recent evidence from 2022 to 2025 continues to support sertraline hydrochloride as a solid option for depression, anxiety disorders, OCD and PMDD, with benefits often starting in 1 to 4 weeks.
For most people, acute treatment usually needs at least 6 to 12 weeks before the full picture is clear.
Australian practice mirrors global evidence, but access and continuity matter more here because PBS subsidies, GP review cycles and repeat scripts shape whether people stay on treatment long enough to benefit.
In plain terms, the medicine works best when it is taken consistently and given enough time.
| Condition | What Recent Evidence Suggests | Common Safety Issues | Australian Takeaway |
|---|---|---|---|
| Depression | Symptom reduction is generally seen over weeks, not days. | Nausea, insomnia, sexual dysfunction | Often chosen when a PBS-covered SSRI is needed for ongoing use. |
| Anxiety disorders | Useful for panic, social anxiety and PTSD symptoms. | Early jitteriness, sleep change, nausea | Starting low helps some people tolerate the first fortnight better. |
| OCD | Response may take longer and dose optimisation matters. | GI upset and discontinuation symptoms if stopped abruptly | Staying the course is often more important than rushing to judge it. |
| PMDD | Can help cyclic symptoms with continuous or luteal-phase dosing. | Sexual side effects and headache | Useful when symptoms are strongly tied to the menstrual cycle. |
Global sertraline evidence remains consistent with older SSRI research, but newer studies keep showing the same practical message: symptom relief is gradual and side effects are usually front-loaded.
Nausea tends to be one of the most common early complaints, while insomnia or drowsiness can go either way depending on the person.
Sexual dysfunction is still a real issue for some patients, and discontinuation symptoms can happen if the medicine is stopped suddenly after regular use.
That is why many Australian GPs aim to review early tolerability before deciding whether to raise the dose.
For patients comparing PBS-covered sertraline with other SSRIs, the real question is often not “which one is strongest?” but “which one can I keep taking safely and consistently?”.
Clinical Effectiveness In Australia
Does sertraline actually hold up in everyday Australian care, not just in study papers?
In GP and psychiatry settings, the answer is usually yes, provided the dose is sensible and follow-up happens on time.
PBS subsidisation can make a big difference here because continuity is easier when cost is predictable.
Many Australians start with a telehealth appointment, receive an e-prescription, and then collect the medicine from a local or online pharmacy.
That workflow is now common, especially for people balancing work, childcare or regional access barriers.
| Condition | Starting Dose | Typical Range | Expected Response Window |
|---|---|---|---|
| Major depressive disorder | 50 mg once daily | 50 to 200 mg/day | 1 to 4 weeks for early change, longer for full effect |
| OCD | 50 mg once daily | 50 to 200 mg/day | Often slower, with review over several weeks |
| Panic disorder | 25 mg start | 50 to 200 mg/day | Early benefit may be followed by gradual dose changes |
| PTSD | 25 mg start | 50 to 200 mg/day | Usually assessed after a sustained trial |
| Social anxiety disorder | 25 mg start | 50 to 200 mg/day | Improvement is often seen in day-to-day confidence and avoidance |
| PMDD | 50 mg daily | 50 to 150 mg/day | Can work within a cycle when used consistently |
What “working” looks like in real life is usually subtle at first.
A person may sleep a bit better, stop dread spirals sooner, or find themselves getting through a workday without as much physical tension.
For OCD, it may mean fewer intrusive thoughts or less time spent on checking behaviours.
For panic, it may mean fewer attacks and less fear of the next one.
Follow-up timing matters.
Many Australian clinicians check in after the first couple of weeks to look for side effects, then again after dose changes.
If the medicine is helping but not enough, the dose may be stepped up carefully, up to a maximum of 200 mg/day for most indications.
That stepwise approach is a big part of antidepressants sertraline being so widely used in Australian primary care.
Indications And Expanded Uses
People often search for sertraline because they have heard it is “an antidepressant”, but that is only part of the story.
In Australian practice, it is commonly used for depression and several anxiety-related conditions as well.
It is prescription only, and there is no OTC version.
- Major depressive disorder: Used when low mood, loss of interest and functional decline persist.
- OCD: Used to reduce obsessive thoughts and compulsive rituals.
- Panic disorder: Often chosen when panic attacks and anticipatory fear dominate.
- PTSD: Used for trauma-related anxiety, hyperarousal and related symptoms.
- Social anxiety disorder: Helps with fear of scrutiny and social avoidance.
- PMDD: Used for cyclical mood and physical symptoms linked to the menstrual cycle.
Those are the standard, TGA-aligned uses that most Australian patients will hear about from a GP or psychiatrist.
Off-label prescribing can happen too, usually when a clinician judges that the expected benefit outweighs the risk.
That may include comorbid anxiety symptoms, or mental health management where symptoms overlap and a single SSRI may simplify treatment.
In perinatal mental health, the decision is more individual and careful, because pregnancy and breastfeeding need risk-benefit review rather than a one-size-fits-all approach.
Patients in clinic often ask about Zoloft indications because the label “antidepressant” sounds narrower than the actual use pattern.
The practical reality is that sertraline uses extend beyond low mood, especially when anxiety is part of the picture.
Composition And Brand Landscape
Wondering whether Zoloft and generic sertraline are the same thing?
The active ingredient is sertraline, and brand, packaging and excipients can vary between manufacturers.
That matters to some patients because a tablet change can look dramatic even when the medicine is clinically equivalent.
| Market | Brand / Generic | Forms | Notes |
|---|---|---|---|
| Australia | Zoloft and generic sertraline | Tablets, oral concentrate | PBS listing and stock levels can influence what is dispensed. |
| United States | Zoloft | 25 mg, 50 mg, 100 mg tablets; oral concentrate | Colour and tablet appearance differ by strength. |
| Canada | Zoloft | Tablets and oral concentrate | Similar dose forms to other markets. |
| Europe | Zoloft and multiple generics | Tablets in country-specific blister packs | Label and excipient differences are common. |
Australian pharmacies often carry brand and generic sertraline options, including major chains such as Chemist Warehouse, Priceline and TerryWhite Chemmart, alongside independent stores and online pharmacies with e-script fulfilment.
Packaging colour, tablet markings and inactive ingredients can vary between manufacturers, so a patient who notices a “different-looking” tablet is usually seeing a supply change, not a different drug class.
That is where PBS generic medicines can help lower cost without changing the active ingredient.
For many people, the choice comes down to price, supply continuity and personal comfort with a known brand.
Contraindications And Special Precautions
Before starting sertraline, a good safety screen matters.
That is especially true if the person is taking other antidepressants, has a history of bipolar disorder, or has liver disease.
| Risk Group Or Situation | Why It Matters | Practical Action |
|---|---|---|
| MAOIs | Serious interaction risk | Do not use together. |
| Pimozide | Contraindicated combination | Avoid co-administration. |
| Disulfiram with oral concentrate | Specific contraindication | Do not combine if using concentrate. |
| Known hypersensitivity | Allergic reaction risk | Do not use. |
| Children under 6 years | Lack of safety data | Do not use. |
| Bipolar disorder | Risk of mania | Needs careful review before prescribing. |
| Bleeding disorders | SSRIs can increase bleeding tendency | Review all medicines and symptoms. |
| Severe hepatic impairment | Reduced clearance and accumulation | Lower dose or longer interval may be needed. |
| Pregnancy and breastfeeding | Risk-benefit balance is individual | Discuss with a clinician before starting or continuing. |
Older adults are often more sensitive to adverse effects, so they usually need a slower titration.
People with seizure disorders also need more caution.
For rural and remote patients, especially in Indigenous health settings, continuity of care can be the bigger safety issue because gaps in reviews, transport barriers and script interruptions can lead to poor adherence or unsafe stopping and starting.
Driving and workplace safety should also be considered early on.
If drowsiness, dizziness or slowed reaction time happens, it is sensible to avoid driving or operating machinery until the person knows how the medicine affects them.
That advice is particularly important in jobs involving vehicles, tools or heavy equipment.
Dosage Guidelines
What dose is right depends on the condition, age and how the person tolerates the medicine.
The usual Australian-style approach is to start simply, then adjust with follow-up rather than making big jumps.
| Condition | Starting Dose | Usual Range | Maximum Dose |
|---|---|---|---|
| MDD | 50 mg once daily | 50 to 200 mg/day | 200 mg/day |
| OCD | 50 mg once daily | 50 to 200 mg/day | 200 mg/day |
| Panic disorder | 25 mg start | 50 to 200 mg/day | 200 mg/day |
| PTSD | 25 mg start | 50 to 200 mg/day | 200 mg/day |
| Social anxiety disorder | 25 mg start | 50 to 200 mg/day | 200 mg/day |
| PMDD | 50 mg daily | 50 to 150 mg/day | 150 mg/day |
For panic disorder, PTSD and social anxiety, a 25 mg start can make the first week easier to tolerate.
For MDD and OCD, 50 mg once daily is the standard starting point.
In older adults, the safest path is usually the lowest effective dose with careful titration.
If liver function is reduced, the dose may need to be lowered or the dosing interval extended.
Renal adjustment is not usually specific, but severe impairment still deserves caution.
PBS and GP review cycles can influence when the next step happens, because dose increases are often aligned with a follow-up appointment and repeat script planning.
That is a practical reason many patients stay in touch with their pharmacist as well as their doctor.
Interaction Overview
Sertraline has a fairly familiar SSRI interaction profile, but the important ones are worth checking every time a new medicine is added.
| Interaction Type | Risk | Action |
|---|---|---|
| MAOIs | Serotonin syndrome risk | Do not combine. |
| Pimozide | Contraindicated | Avoid combination. |
| Other serotonergic drugs | Serotonin excess | Review for overlap and symptoms. |
| Some migraine medicines | Added serotonergic burden | Ask a pharmacist or doctor before using. |
| Linezolid | Potential serious interaction | Needs medical review before use. |
| St John’s wort | Can increase side effects and serotonin risk | Avoid unless specifically advised. |
| Medicines that raise bleeding risk | Bleeding tendency may increase | Check all blood thinners and NSAIDs. |
| Oral concentrate with disulfiram | Contraindicated | Do not use together. |
The oral concentrate must be diluted before use, so it is not a “drink straight from the bottle” medicine.
Alcohol is not always an absolute no, but it can worsen sleep, dizziness or low mood for some people, so it is best kept modest or avoided early in treatment.
Caffeine and coffee are similar: not banned, but they may add to jitteriness or insomnia in sensitive people.
Australian pharmacist medication reviews and e-health checks are useful here because they can catch combinations that a busy patient may not realise are important.
Cultural Perceptions And Patient Habits
Australians often talk about Zoloft in very practical terms.
Will it change my personality?
How long until it works?
Why do the first two weeks feel worse?
Those are the kinds of questions pharmacy staff hear every day.
There is also a strong price sensitivity around PBS subsidy, especially for repeat medicines taken for months rather than days.
Some patients want the same brand every time because it feels familiar.
Others will ask for the cheapest PBS-covered generic and are happy as long as the dose stays the same.
That preference is normal and often comes down to trust, budget and prior experience.
Rural access is another big factor.
Telehealth and e-prescriptions have made it easier for people outside major cities to keep treatment going without long trips to a clinic.
For many households, that convenience is the difference between starting treatment and postponing it again.
In an online pharmacy setting, zoloft is available without a prescription, with discreet delivery to Australia in 5-14 days.
Questions about adherence usually improve when a pharmacist normalises the first few side effects and explains that not every rough patch means the medicine is wrong.
That kind of reassurance can keep people on treatment long enough to see if sertraline is the right fit.
Availability And Pricing Patterns
Where do Australians usually get sertraline, and why do prices seem to change between pharmacies?
Most commonly, people fill it through a community pharmacy, an online pharmacy or a chain store with e-script support.
Major names such as Chemist Warehouse, Priceline and TerryWhite Chemmart are often compared against independents because repeat pricing matters over time.
| Channel | Typical Access | Price Pattern | Notes |
|---|---|---|---|
| Community pharmacy | In-store scripts and repeats | PBS or private pricing | Good for pharmacist counselling. |
| Chain pharmacy | In-store and online | Often competitive | Brand switching may happen with stock changes. |
| Online pharmacy | E-script fulfilment | Comparison shopping is common | Useful for repeats and discreet delivery. |
| PBS vs private | Depends on eligibility and listing | PBS usually lowers out-of-pocket cost | Patients often check both before ordering. |
Supply can vary by strength and manufacturer, especially during disruptions or when a pharmacy is moving between generic suppliers.
That can affect whether a patient receives Zoloft 50 mg, Zoloft 100 mg or a generic sertraline equivalent.
The available forms sold are tablets 25 mg, 50 mg and 100 mg, plus the 20 mg/mL oral concentrate.
There are no injectable, topical or rectal versions.
For people who need regular repeats, stock consistency often matters as much as price because missed doses can interrupt progress.
Comparable Medicines And Preferences
Sertraline is part of the SSRI group, so it is often compared with fluoxetine, paroxetine, citalopram and escitalopram.
They work in a broadly similar way, but the side-effect profile and practical fit can differ.
| Medicine | Typical Strengths / Use Pattern | Common Preference Point | Possible Downside |
|---|---|---|---|
| Sertraline | Often chosen for depression and anxiety disorders | Flexible, widely used, familiar to Australian GPs | Nausea, insomnia, sexual side effects |
| Fluoxetine | Another common SSRI | May suit people who want a different activation profile | Can feel more activating for some |
| Paroxetine | SSRI option for some patients | May suit selected cases | Can be harder to stop for some people |
| Citalopram | Common SSRI in Australia | Often considered simple and familiar | Tolerability varies by person |
| Escitalopram | Closely related SSRI | Often selected for tolerability | Still shares SSRI class effects |
A quick pros and cons check can help.
Why sertraline may be preferred: broad use across depression, anxiety and OCD, familiar dosing, and practical PBS availability.
Why another SSRI may be preferred: a different sleep effect, different sexual side-effect burden, or previous good response to a specific medicine.
That choice should not be made on brand name alone, because similar-class medicines can still feel quite different from one patient to the next.
Frequently Asked Questions
How long does Zoloft take to work?
Most people notice some change in 1 to 4 weeks, but acute treatment usually needs at least 6 to 12 weeks before the effect is properly judged.
Can I drink alcohol on sertraline?
Alcohol is not always an absolute contraindication, but it can make drowsiness, sleep problems or mood symptoms worse, so moderation is sensible and some people are better off avoiding it early on.
What if I miss a dose?
Take it as soon as you remember unless it is close to the next dose.
Do not double up.
If too much is taken, urgent medical help is needed because overdose can cause somnolence, vomiting, tachycardia, agitation and nausea.
Is sertraline subsidised by PBS?
PBS subsidy may apply depending on the script and current listing, which is why many Australians compare options before they fill a repeat.
Guidelines For Proper Use
Good sertraline counselling is mostly about consistency, patience and follow-up.
Store tablets at 20 to 25°C and keep them away from moisture and excess heat.
Protect the oral concentrate from light and always dilute it before use.
Take the medicine as directed each day, because irregular use makes it harder to know whether it is helping or causing side effects.
- Do keep your follow-up appointments so benefit, side effects and dose changes can be reviewed.
- Do let a pharmacist know about every other medicine, including migraine products, St John’s wort and blood thinners.
- Do expect the first weeks to be a settling-in period rather than an instant fix.
- Do not stop suddenly without advice if you have been taking it regularly.
- Do not double a missed dose.
Pharmacist medicine checks, telehealth follow-up and PBS repeat planning can make treatment easier to maintain, especially when work, travel or family life gets busy.
If the medicine is not helping enough after an adequate trial, or if side effects are getting in the way, that is a reason to review the plan rather than abandon it silently.
Shared decision-making matters here, because the best antidepressant is the one the patient can take safely, affordably and long enough to benefit from.
Delivery Across Australia
| City | Region | Delivery time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Darwin | Northern Territory | 5-7 days |
| Gold Coast | Queensland | 5-7 days |
| Newcastle | New South Wales | 5-7 days |
| Wollongong | New South Wales | 5-9 days |
| Geelong | Victoria | 5-9 days |
| Townsville | Queensland | 5-9 days |
| Ballarat | Victoria | 5-9 days |