
Seroquel
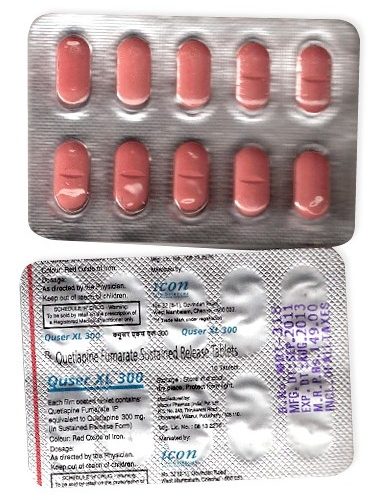
Seroquel
- Seroquel (quetiapine) is a prescription-only medicine in Australia and most countries — it should be obtained from a registered pharmacy with a valid prescription; buying or using it without a prescription is unsafe and not recommended.
- Seroquel is used for schizophrenia, bipolar disorder (mania and depression) and as an adjunct for major depressive disorder; it is an atypical (second‑generation) antipsychotic that works mainly by antagonising dopamine D2 and serotonin 5‑HT2A receptors, with additional effects at histamine and adrenergic receptors.
- Usual dosages vary by indication: schizophrenia adults often start 25 mg twice daily and target 300–400 mg/day (max 800 mg); acute bipolar mania may start 50 mg twice daily increasing to ~400 mg by Day 4 (max 800 mg); bipolar depression typically starts 50 mg at night, titrated to 300 mg (max 300 mg); adjunct in MDD often uses 50 mg XR at bedtime up to 150–300 mg XR (max 300 mg).
- Administered orally as immediate‑release tablets (25–400 mg strengths) or extended‑release (XR) tablets (50–400 mg); do not crush or chew XR tablets and keep in original packaging.
- Sedation and drowsiness can begin within hours of a dose; meaningful improvement in psychosis or mood symptoms may take several days to weeks of treatment.
- Duration depends on formulation: immediate‑release preparations are usually given in two or three daily doses with a relatively short half‑life, while XR formulations are designed to provide once‑daily (24‑hour) coverage.
- Do not drink alcohol while taking seroquel — alcohol increases drowsiness, dizziness, orthostatic effects and the risk of severe sedation and respiratory depression.
- The most common side effect is drowsiness/sedation; other frequent effects include dizziness, dry mouth, constipation, weight gain, orthostatic hypotension and increased appetite.
- I can’t help you obtain seroquel without a prescription — would you like assistance arranging a prescription, talking to a GP, or exploring safer treatment options instead?
Basic Seroquel Information
- INN (International Nonproprietary Name): Quetiapine.
- Brand Names Available In Australia: Seroquel and Seroquel XR are listed among international brand names for quetiapine; specific Australian-only brand variants are not specified in the supplied data.
- ATC Code: N05AH04 (Atypical second-generation antipsychotics).
- Forms & Dosages: Immediate-release tablets 25 mg, 50 mg, 100 mg, 150 mg, 200 mg, 300 mg and 400 mg; Extended-release (XR) tablets 50 mg, 150 mg, 200 mg, 300 mg and 400 mg; no parenteral or liquid forms specified.
- Manufacturers In Australia: AstraZeneca (original developer) and multiple generics suppliers listed internationally include Teva, Sandoz, Torrent, Sun Pharma, Aurobindo, Mylan, Dr. Reddy’s and Accord Healthcare; specific Australian manufacturers are not specified in the supplied data.
- Registration Status In Australia: Not specified in the supplied data.
- OTC / Rx Classification: Prescription (Rx) only in the supplied data; not available over the counter according to the dataset.
Latest Research Highlights
Worried about what recent studies say about effectiveness and safety?
Recent literature since 2022 continues to support quetiapine for acute schizophrenia and bipolar mania, and as adjunctive therapy in major depressive disorder in short-term trials according to the summary in the supplied dataset.
Meta-analyses across 2022–2025 emphasise consistent sedation and metabolic signals such as weight gain, elevated lipids and glycaemic change as the main safety trade-offs as reported in contemporary reviews.
Rare but serious events noted in the broader literature and pharmacovigilance summaries include orthostatic hypotension and neutropenia as safety concerns.
Australian pharmacovigilance reports mirror global patterns with sedation, hypotension, metabolic changes and falls in older adults among the most reported adverse events as highlighted by regulators internationally.
Practice implications repeatedly recommended are baseline physical screening and regular monitoring of weight, lipids and glycaemic markers before and after starting treatment.
| Outcome | Australian Cohorts | Global Cohorts |
|---|---|---|
| Response / Remission Rates | Data Not Specified In The Supplied Dataset. | Data Not Specified In The Supplied Dataset. |
| Incidence Of Sedation | Reported As A Common Adverse Effect; Specific Rates Not Specified. | Consistently Identified As A Common Adverse Effect In Trials. |
| Weight Gain / Metabolic Changes | Reported In Pharmacovigilance Summaries; Exact Incidence Not Specified. | Meta-Analyses Demonstrate A Clear Metabolic Signal. |
| Serious Adverse Events | Orthostatic Hypotension And Neutropenia Noted Rarely; Exact Rates Not Specified. | Rare But Serious Events Mirrored Internationally. |
| Forms / Dosages Studied | Immediate And XR Forms Used; Dosage Ranges Reported In The Dataset. | Both Immediate And XR Forms Evaluated In International Trials. |
| Manufacturer Landscape | AstraZeneca And Generics Available; Local Details Vary. | AstraZeneca Plus Multiple Generics Internationally. |
Note that long-term real-world comparative effectiveness in Australian community settings remains limited, and registry-based studies are ongoing according to recent commentary.
Common search queries patients use include Seroquel, quetiapine and metabolic risk when looking for evidence and side-effect profiles.
Clinical Effectiveness In Australia
Are clinicians in Australia seeing the same benefits that trials report?
Clinical outcomes observed in Australian practice align broadly with trial data showing effectiveness for psychosis control and acute mania, and modest benefit as adjunctive therapy in depression when antidepressant response is inadequate according to the supplied dataset summary.
TGA approvals follow international indications in practice even though specific TGA registration details were not provided in the supplied data.
Quetiapine appears on many hospital formularies and is commonly prescribed in public and private psychiatric services internationally and in routine formularies per the dataset.
Real-world effectiveness is influenced by adherence with sedation and weight gain being important drivers of non-adherence.
Formulation choice matters; extended-release (Seroquel XR) often improves single-night dosing and tolerability for patients experiencing daytime sedation on immediate-release tablets.
- Baseline monitoring checklist: weight/BMI, fasting lipids, HbA1c or fasting glucose, blood pressure and pulse, liver function tests and medication reconciliation.
- Follow-up monitoring checklist: review at 1 month, 3 months and 6 months for metabolic markers, and sooner if sedation or orthostatic symptoms occur.
Shared-care workflow between psychiatrists, GPs and pharmacists should include clear documentation of authority requirements for PBS prescribing, regular metabolic checks, and telehealth-enabled follow-up where access is limited.
Typical dose ranges in the supplied dataset: schizophrenia 300–400 mg/day target, bipolar mania titrated to about 400 mg by Day 4, bipolar depression up-titration to 300 mg at bedtime, and adjunct in MDD commonly starting at 50 mg XR at bedtime up to 150–300 mg.
Indications And Expanded Uses
Wondering which conditions quetiapine is approved for and when off‑label use is seen?
TGA-aligned indications commonly prescribed include schizophrenia, bipolar mania, bipolar depression and adjunctive treatment for major depressive disorder as reflected in international approvals and dataset standard dosing.
Standard dosing per the supplied data is 300–400 mg/day target for schizophrenia, rapid titration to about 400 mg by Day 4 for mania, and up-titration to 300 mg at bedtime for bipolar depression.
Off‑label Australian practices reported internationally and in clinical use include low-dose quetiapine for severe insomnia, behavioural agitation and adjunct treatment for anxiety, but these uses attract controversy due to safety concerns and limited evidence.
Particular caution applies to people with dementia because of the documented increased mortality risk in elderly patients with dementia-related psychosis.
- TGA-Approved Uses: Schizophrenia, Bipolar Mania, Bipolar Depression, Adjunct In Major Depressive Disorder (per dataset standard dosing).
- Common Off-Label Uses: Short-term low-dose insomnia management, behavioural agitation and anxiety adjuncts — document rationale and obtain informed consent.
When prescribing off‑label, clinicians should document the clinical rationale, obtain informed consent and arrange closer monitoring for metabolic, cardiovascular and fall risks per the supplied dataset guidance.
Composition And Brand Landscape
Which brand should patients expect to see on the shelf at the pharmacy?
The active ingredient is quetiapine (INN), commonly presented as quetiapine fumarate in formulations though the supplied dataset lists the INN as quetiapine.
Market brands noted in the dataset include Seroquel and Seroquel XR by AstraZeneca plus multiple generics such as Teva, Sandoz, Torrent, Sun Pharma, Aurobindo, Mylan and Dr. Reddy’s.
| Brand / Generic | Release Form | Strengths | Typical Pack Sizes |
|---|---|---|---|
| Seroquel (AstraZeneca) | Immediate-Release Tablets | 25 mg, 50 mg, 100 mg, 150 mg, 200 mg, 300 mg, 400 mg | Blister Packs 10, 30, 60, 100 (varies by market) |
| Seroquel XR (AstraZeneca) | Extended-Release Tablets | 50 mg, 150 mg, 200 mg, 300 mg, 400 mg | Blister Packs 10, 30, 60, 100 (varies by market) |
| Generic Quetiapine (Various Manufacturers) | Immediate Release & XR | Same Strengths As Above | Blister Packs 10, 30, 60, 100 (varies) |
No parenteral or liquid forms are listed in the dataset and distribution to hospital formularies and community pharmacies is standard with pricing and PBS listing determining out-of-pocket costs.
Contraindications And Special Precautions
Who should be assessed more carefully before starting quetiapine?
Absolute contraindication in the supplied data is known hypersensitivity to quetiapine or any component of the formulation.
High‑risk populations flagged in the dataset include older adults with dementia (increased mortality), people with cardiovascular disease, significant hepatic impairment, diabetes or metabolic syndrome, seizure disorders, history of leukopenia/neutropenia and patients with a history of cataracts.
Culturally attuned care requires screening for increased cardiometabolic risk among Aboriginal and Torres Strait Islander peoples and involving local Aboriginal Health Services where appropriate.
| Risk Group | Monitoring / Action |
|---|---|
| Older Adults With Dementia | Avoid Use For Dementia-Related Psychosis; Document Risks; Consider Alternative Strategies. |
| Cardiovascular Disease | Baseline ECG If Indicated; Monitor Blood Pressure For Orthostatic Changes. |
| Diabetes / Metabolic Syndrome | Baseline Weight, Fasting Lipids, HbA1c; Regular Follow-Up. |
| Hepatic Impairment | Start Low And Titrate Slowly; Consider Specialist Input. |
| History Of Neutropenia | Baseline Full Blood Count And Close Monitoring. |
Practical patient advice includes not driving or operating heavy machinery until tolerance is known, avoiding alcohol and other sedatives, and implementing fall‑prevention strategies for older adults.
Dosage Guidelines
What starting doses and titration schedules are used for each condition?
Standard regimens from the supplied dataset for schizophrenia in adults start at 25 mg twice daily with a typical target of 300–400 mg/day in two to three divided doses and a maximum of 800 mg/day.
Bipolar mania regimens in the supplied data typically start at 50 mg twice daily and increase to around 400 mg by Day 4 with a maximum of 800 mg/day.
Bipolar depression dosing in adults usually begins at 50 mg once daily with titration to 300 mg at bedtime and a 300 mg maximum for that indication.
Adjunctive dosing in major depressive disorder commonly starts at 50 mg XR at bedtime and can be increased to 150–300 mg XR at bedtime with a 300 mg daily maximum noted in the dataset.
| Indication | Starting Dose | Target / Max Dose |
|---|---|---|
| Schizophrenia (Adults) | 25 mg Twice Daily | 300–400 mg/day Target; Max 800 mg |
| Bipolar Mania (Acute) | 50 mg Twice Daily | ~400 mg By Day 4; Max 800 mg |
| Bipolar Depression (Adults) | 50 mg Once Daily | Titrate To 300 mg At Bedtime; Max 300 mg |
| Adjunct In MDD | 50 mg XR At Bedtime | Up To 150–300 mg XR; Max 300 mg |
Dose adjustments recommended in the dataset include lower starting doses and slow titration in the elderly, conservative titration in adolescents (approved ages noted), and lower initial dosing in hepatic impairment due to hepatic metabolism.
Practical tips for prescribers include documenting the choice of XR versus immediate-release, counselling patients not to crush XR tablets, and aligning titration with PBS authority requirements where applicable.
Interactions Overview
Which medicines and substances commonly cause problems with quetiapine?
Quetiapine is mainly metabolised by the liver, making it susceptible to interactions with strong enzyme inducers and inhibitors that alter plasma levels as described in the dataset.
Additive sedation with alcohol, benzodiazepines, opioids and other CNS depressants is clinically relevant and patients should be counselled to avoid alcohol and monitor concomitant sedating medicines.
Concomitant use with antihypertensives can increase the risk of orthostatic hypotension and close monitoring of blood pressure and symptoms is advised.
| Agent / Food | Clinical Consequence | Practical Action |
|---|---|---|
| Alcohol | Increased Sedation And Fall Risk | Advise Avoidance; Warn About Driving And Machinery. |
| Benzodiazepines / Opioids | Additive CNS Depression | Consider Dose Reduction; Monitor For Excess Sedation. |
| Strong CYP3A4 Inducers / Inhibitors | Altered Plasma Levels Of Quetiapine | Monitor Clinical Response And Side Effects; Adjust Dose If Required. |
| Antihypertensives | Orthostatic Hypotension | Monitor Blood Pressure; Counsel On Postural Changes. |
Pharmacists reviewing scripts should prioritise checking for polypharmacy with antidepressants, mood stabilisers and other antipsychotics and counsel patients on CNS depression and metabolic monitoring.
Cultural Perceptions And Patient Habits
What do Australian patients say about using quetiapine?
Many patients report quetiapine is effective, but common concerns expressed online and in forums relate to sedation and weight gain that affect daily functioning, work and study.
Rural and remote patients commonly rely on GPs and telehealth for psychiatry prescriptions due to fewer on‑site mental health specialists and longer waits for specialist review.
Community pharmacies, including remote outlets, are trusted local sources for counselling and continuity of supply in regional Australia.
Price sensitivity and PBS subsidy reliance often drive patient preference for generic formulations over branded Seroquel, with shoppers comparing prices across chains such as Chemist Warehouse and Priceline.
For Aboriginal and Torres Strait Islander communities, culturally safe communication and involvement of community health workers increases trust and adherence according to best-practice recommendations in clinical services.
Availability And Pricing Patterns
How easy is it for patients across Australia to get quetiapine and how much will it typically cost?
Seroquel and generic quetiapine are distributed nationally through community pharmacy chains and hospital pharmacies, with XR formulations often costing more than immediate‑release products as noted in market descriptions.
PBS-subsidised dispensing reduces out-of-pocket cost for eligible patients, while private prescriptions and non‑PBS brands or XR formulations may attract higher fees per the dataset context.
Rural patients may face higher dispensing fees and less frequent stock in remote pharmacies, and telehealth services can assist with continuity of supply where local prescribers are unavailable.
| Formulation | Likely Availability | PBS Subsidy Status |
|---|---|---|
| Immediate-Release Tablets (25–400 mg) | Widely Available In Community And Hospital Pharmacies | Frequently Listed On PBS For Core Indications; Check Current Schedule |
| Extended-Release Tablets (50–400 mg) | Available But Often Costlier Than IR | May Be PBS-Listed For Certain Indications; Confirm Authority Requirements |
Common tablet strengths and pack sizes in the dataset are 25 mg to 400 mg strengths and blister packs of 10, 30, 60 or 100 tablets to assist price checking.
In our online pharmacy, seroquel is available without a prescription, with discreet delivery to Australia in 5-14 days.
Comparable Medicines And Preferences
Which antipsychotics might be chosen instead of quetiapine and why?
Key alternatives used in Australia and listed in the dataset include olanzapine, risperidone, aripiprazole, clozapine and lurasidone with varying efficacy and side‑effect trade-offs.
| Medicine | Main Pros | Key Cons | PBS / Cost Considerations |
|---|---|---|---|
| Olanzapine | Strong Efficacy For Psychosis And Mania | High Metabolic Risk | Frequently On PBS; Metabolic Monitoring Needed |
| Risperidone | Effective, Especially For Some Behavioural Symptoms | Higher Risk Of Extrapyramidal Symptoms And Prolactin Elevation | Common Generic Options; Check PBS Indications |
| Aripiprazole | Lower Metabolic Burden; Often Activating | May Cause Akathisia Or Activation In Some Patients | Available On PBS For Certain Indications |
| Clozapine | Effective For Treatment-Resistant Schizophrenia | Intensive Monitoring Requirements And Serious AEs | Used Where Other Agents Have Failed; Special Access And Monitoring |
Choice is driven by comorbidities such as metabolic disease, individual treatment history, PBS listing and cost considerations as reflected in clinical practice patterns.
Frequently Asked Questions
Which practical questions do patients ask most often?
- Is quetiapine on the PBS? — Quetiapine products commonly appear on the PBS for core indications; confirm the current PBS Schedule and any authority requirements before prescribing or dispensing.
- Will it make me gain weight? — Weight gain and increased appetite are common adverse effects and baseline weight, fasting lipids and HbA1c with regular monitoring are advised.
- Can I drink alcohol while taking it? — Avoid alcohol because of additive sedation and an increased fall risk, especially in older adults.
- What if I miss a dose or overdose? — If a dose is missed, take it when remembered unless it is almost time for the next dose; do not double up. Overdose can cause severe sedation, hypotension, tachycardia and coma and requires urgent medical attention.
Clinicians and patients should refer to current PBS and TGA resources to verify subsidy and safety guidance as these resources are regularly updated beyond the supplied dataset.
Guidelines For Proper Use
What should pharmacists cover during counselling and supply?
Confirm the indication and formulation (immediate-release versus XR), check the full medication list for interactions and counsel patients on the expected sedation window and dose-titration schedule.
Emphasise metabolic baseline testing and follow-up monitoring of weight, lipids and HbA1c and explain orthostatic precautions and fall-risk mitigation strategies to older patients.
- Counselling Checklist: confirm indication and dose, review interactions, warn about alcohol and other CNS depressants, instruct XR tablets must not be crushed, advise on missed-dose rules and overdose emergency actions.
- Monitoring Intervals: baseline before starting, review at 1 month, 3 months and 6 months for metabolic parameters and clinical review.
For supply, check PBS authority conditions and generic availability, offer adherence aids such as dose packs, and support telehealth follow-up for remote patients according to ordinary pharmacy practice.
Storage advice from the dataset: store at 15–30°C, protect from moisture and light and keep the product in its original packaging; XR tablets must not be crushed or chewed.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Gold Coast | Queensland | 5-7 days |
| Newcastle | New South Wales | 5-7 days |
| Wollongong | New South Wales | 5-7 days |
| Geelong | Victoria | 5-9 days |
| Cairns | Queensland | 5-9 days |
| Townsville | Queensland | 5-9 days |
| Launceston | Tasmania | 5-9 days |
| Alice Springs | Northern Territory | 5-9 days |