
Trazodone
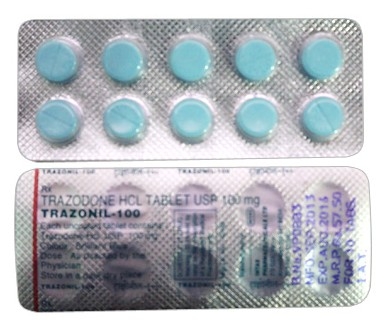
Trazodone
- You can obtain trazodone from pharmacies and licensed suppliers; it is officially prescription-only in most countries (including Australia), though some pharmacies or online vendors may supply it without a prescription or receipt—check local regulations and pharmacy policies.
- Trazodone is used primarily to treat major depressive disorder and is widely used off‑label for insomnia; its mechanism includes serotonin reuptake inhibition and 5‑HT2 receptor antagonism, producing antidepressant and sedative effects.
- Typical dosing for depression starts at about 75–150 mg per day in divided doses, with usual adult doses up to 400 mg/day (inpatient use up to 600 mg/day reported); for insomnia lower single doses of 25–100 mg at bedtime are commonly used.
- The drug is administered orally as immediate‑release tablets, and as extended‑/prolonged‑release tablets (e.g. 50, 75, 100, 150 mg strengths); other forms are rarely available.
- Sedative effects for sleep are often felt within 30–60 minutes after an oral dose; antidepressant benefits generally require 2–4 weeks of regular use to become apparent.
- The sedative effect typically lasts several hours (commonly 6–12 hours depending on formulation and dose); antidepressant benefits persist with continued daily treatment and should be maintained for at least six months after remission.
- Do not drink alcohol while taking trazodone — alcohol increases sedation, respiratory depression and other CNS effects and may worsen side effects.
- The most common side effect is sedation/drowsiness (also common: dizziness/orthostatic hypotension, headache, dry mouth, nausea and constipation).
- Would you like to try “trazodone” without a prescription?

Basic Trazodone Information
- INN (International Nonproprietary Name): Trazodone
- Brand Names Available In Australia: Desyrel; Trittico (and related Trittico formulations); Trazolan; Trazonil; Donaren; Oleptro (withdrawn in US); other international brands listed on Drugs.com/International.
- ATC Code: N06AX05
- Forms & Dosages: Immediate‑release tablets commonly 50mg and 100mg; extended‑release or prolonged‑release tablets (marked XR/CR/retard) in strengths including 75mg, 100mg and 150mg; oral solution not typically marketed.
- Manufacturers In Australia: not specified
- Registration Status In Australia: not specified
- OTC / Rx Classification: Prescription only (Rx) in all markets.
Latest Research Highlights
Are you wondering how well trazodone works and what recent studies say?
Recent systematic reviews published between 2022 and mid‑2024 reaffirm trazodone’s antidepressant efficacy but report generally lower effect sizes compared with modern selective serotonin reuptake inhibitors for first‑line major depressive disorder.
The overall quality of evidence across many small randomised controlled trials is described as moderate to low in these reviews.
Australian observational sources, including TGA adverse‑event reports and small cohort studies, emphasise low‑dose bedtime trazodone’s clear sedative benefit for sleep continuity.
Those same Australian data highlight rare but serious adverse events such as priapism, hyponatraemia and arrhythmia.
Randomised trials focused on insomnia report improved sleep continuity with low bedtime doses (commonly 25–100mg) versus placebo.
Daytime sedation and orthostatic hypotension are recurring safety concerns in older adults and are associated with increased fall risk.
Safety meta‑analyses from 2022–2024 emphasise the risk of serotonin syndrome when trazodone is combined with other serotonergic medicines including SSRIs, SNRIs and MAOIs.
Those analyses also note interactions that may prolong QT interval when trazodone is co‑prescribed with certain antipsychotics, antiarrhythmics and other QT‑prolonging drugs.
Ongoing 2024–2025 registries are tracking pragmatic telehealth prescribing patterns in rural populations, with trial registrations pending publication.
| Outcome | Australian Evidence | Global Evidence |
|---|---|---|
| Depression Response | Moderate evidence; pooled effect sizes reported as lower than SSRIs (specific pooled values not specified) | Moderate evidence across small RCTs; effect size generally lower than modern SSRIs |
| Depression Remission | Data limited; small cohorts and observational reports (not specified) | Variable across trials; remission rates not consistently superior to comparators |
| Sleep Metrics (Insomnia Trials) | Improved sleep continuity at 25–100mg vs placebo; daytime sedation noted | Consistent improvement in sleep continuity at low doses in multiple RCTs |
| Safety Signals (per 1,000) | TGA signal counts note sedation, orthostasis, rare priapism and hyponatraemia (exact rates not specified) | Pooled safety analyses report serotonin syndrome risk with polypharmacy and QT‑prolongation concerns (exact rates not specified) |
Key technical identifiers: INN = trazodone; ATC N06AX05.
Common local dosage forms are trazodone 50mg and trazodone 100mg tablets, with extended‑release options available internationally.
Clinical Effectiveness In Australia
Will trazodone help if sleep is your main symptom?
In Australian practice trazodone is used primarily as a second‑line antidepressant and widely off‑label as a sedative for insomnia when sleep disturbance is prominent.
TGA‑registered indications align with international approval for major depressive disorder, while PBS listing and subsidy vary by product and indication and should be checked against current PBS schedules.
Real‑world clinic audits and telehealth prescribing reviews — from both urban and rural clinics — show clinicians tend to favour trazodone when SSRIs cause activating side effects or when insomnia is a dominant complaint.
Australian TGA adverse‑event summaries highlight orthostatic hypotension and sedation‑related falls as common reasons for dose reduction or switching, particularly in older patients.
Comparative effectiveness versus SSRIs suggests similar short‑term response in some cohorts for moderate depression but different tolerability profiles: more sedation and less sexual dysfunction with trazodone.
Practical baseline monitoring commonly recommended in Australia includes blood pressure, medication reconciliation to avoid serotonergic polypharmacy, and sodium checks for elderly or frail patients.
| Prescription Route | PBS Frequency | Private Prescribing Frequency |
|---|---|---|
| Depression (MDD) | Varies by formulation and indication — check PBS | Common where PBS not applicable |
| Off‑label Insomnia | Typically not PBS‑subsidised for insomnia | Frequently private prescription |
- Monitoring Checklist: Baseline blood pressure and pulse.
- Medication reconciliation to identify SSRIs, SNRIs, MAOIs or CYP3A4 inhibitors.
- Sodium checks (elderly/frail or symptomatic patients).
- Fall‑risk assessment in older adults.
Typical dosing reported in Australian practice: MDD starting at 75–150mg/day and insomnia at 25–100mg at night.
Indications And Expanded Uses
What conditions is trazodone approved for and when is it used off‑label?
Trazodone is TGA‑approved for major depressive disorder, consistent with EMA and FDA listings.
Common off‑label uses in Australia include insomnia at low bedtime doses, adjunctive therapy for treatment‑resistant depression, and cautious symptomatic management of agitation or behavioural disturbance in some dementia care settings.
Pain clinics sometimes use trazodone to improve sleep in patients with chronic pain.
Paediatric use is generally not recommended as safety and efficacy are not established.
Pregnancy and breastfeeding require specialist input due to limited data and a need to weigh benefits versus risks.
| Indication | Typical Dose | Monitoring Points |
|---|---|---|
| Major Depressive Disorder (Approved) | Start 75–150mg/day in divided doses; titrate up to 400mg/day (inpatient up to 600mg/day) | BP, medication interactions, response at 2–4 weeks |
| Insomnia (Common Off‑Label) | 25–100mg at bedtime | Daytime sedation, falls risk in elderly |
| Adjunctive For Treatment‑Resistant Depression (Off‑Label) | Individualised; often higher than insomnia doses | Specialist review recommended |
Composition And Brand Landscape
Which brands and formulations should pharmacists expect to see?
Active ingredient: trazodone hydrochloride (INN: trazodone).
The global brand portfolio includes Desyrel, Trittico (and Trittico variants), Trazolan, Trazonil and others.
Extended‑release (XR/CR/retard) products are common in parts of Europe and other regions.
In Australia the market is largely supplied by generics or imported brand formulations from international manufacturers such as Angelini and companies listed globally.
| Brand | Country Of Origin | Australian Availability |
|---|---|---|
| Desyrel | Worldwide | Available via imports / generics |
| Trittico | Italy (Europe) | Imported formulations may be available |
| Trazolan / Trazonil | Luxembourg / India | Imported generics |
- For stocking and procurement note common pack sizes reflect tablet strengths of 50mg and 100mg, with XR options in 75mg and 150mg where available.
- Dispensing Checklist: Store at 15–30°C, keep in original packaging, and keep out of reach of children.
Contraindications And Special Precautions
Who should not take trazodone or take it with extra caution?
Absolute contraindications include known hypersensitivity to trazodone or excipients, recent myocardial infarction, and acute intoxication with alcohol or other CNS depressants.
Cautions include patients with cardiac disease due to QT prolongation or arrhythmia risk, severe hepatic or renal impairment, angle‑closure glaucoma, seizure disorders and bipolar disorder because of possible mania induction.
Elderly patients are at higher risk of orthostatic hypotension, sedation and falls and should be managed with lower starting doses and careful monitoring.
Special Australian considerations: Indigenous and remote communities often have higher multimorbidity and prescription complexity, so prioritise culturally safe shared decision‑making and comprehensive medication reviews.
Daily‑life restrictions: advise avoiding driving or operating heavy machinery until the sedative effects are known and avoid alcohol and other sedatives.
- Absolute Contraindications: Hypersensitivity to trazodone; recent MI; acute intoxication with alcohol or CNS depressants.
- Relative Contraindications: Cardiac conduction issues, severe liver/kidney disease, seizure disorders, history of mania, elderly at fall risk.
Highlighted safety signals such as priapism and hyponatraemia are rare but serious and require immediate medical attention if suspected.
Dosage Guidelines
What doses are used in different patient groups and when should you refer?
Standard adult dosing for major depressive disorder begins at 75–150mg/day in divided doses with titration up to 400mg/day as an outpatient and inpatient doses up to 600mg/day under specialist supervision.
For insomnia the typical off‑label bedtime dose is 25–100mg and should be individualised.
Elderly patients should start low—often 50mg at bedtime for insomnia—and titrate slowly with monitoring for orthostatic hypotension and sedation.
Hepatic or renal impairment warrants lower initial doses and slower titration; specialist pharmacology input is recommended where uncertainty exists.
| Population | Starting Dose | Usual Therapeutic Range | Max Dose | Monitoring |
|---|---|---|---|---|
| Adults (MDD) | 75–150mg/day | 75–400mg/day | 400mg/day (outpatient) | BP, interactions, response |
| Insomnia (Adults) | 25–50mg at night | 25–100mg at night | Individualised | Daytime sedation, falls |
| Elderly | 50mg at night | Lower end of adult range | Lower than adult max | BP, orthostasis, sodium |
- Titration Plan: Start at the chosen dose, reassess in 2–4 weeks, increase gradually if tolerated and needed, and continue at least 6 months after remission for depression.
- Refer to psychiatry when doses exceed 150mg/day, when response is inadequate, or when severe adverse effects occur.
Interactions Overview
Which medicines, foods or habits can make trazodone risky?
Major interaction risks include concomitant serotonergic agents such as SSRIs, SNRIs and MAOIs, which increase the risk of serotonin syndrome.
QT‑prolonging drugs including some antipsychotics, antiarrhythmics and certain antibiotics may increase arrhythmia risk when combined with trazodone.
Alcohol and other CNS depressants potentiate sedation and respiratory depression and should be strongly avoided.
Trazodone is largely metabolised by CYP3A4 so potent CYP3A4 inhibitors (for example some azole antifungals and macrolide antibiotics) can increase trazodone plasma levels.
| Drug / Food | Risk | Action |
|---|---|---|
| SSRIs / SNRIs / MAOIs | Serotonin syndrome | Avoid combination or observe recommended washout periods with MAOIs; monitor closely |
| QT‑prolonging agents | Arrhythmia / torsades risk | Assess baseline ECG if multiple QT drugs; avoid where possible |
| Alcohol / Opioids / Benzodiazepines | Enhanced sedation, respiratory depression | Advise avoidance and warn about driving |
| CYP3A4 inhibitors | Increased trazodone levels | Consider dose reduction and monitoring |
Be alert for serotonin syndrome signs: agitation, confusion, sweating, hyperreflexia, and autonomic instability, and seek urgent care if suspected.
Cultural Perceptions And Patient Habits
How do Australians typically view and use trazodone?
Many Australian patients think of trazodone as a “sleeping antidepressant,” which helps explain widespread off‑label use for insomnia.
Patient forums and telehealth consultations show high price sensitivity and a strong willingness to accept generic trazodone tablets.
Trust in pharmacists at national chains and local community pharmacies is high, particularly in rural areas where pharmacists often provide medicine counselling and continuity of supply.
Rural and remote challenges include stock variability and longer refill gaps; telehealth e‑prescriptions have helped but require careful follow‑up.
Indigenous communities prioritise culturally safe care and clear plain‑language explanations of treatment choices.
| Setting | Typical Behaviour |
|---|---|
| Urban | Access to specialists; preference for PBS‑covered options when available |
| Rural / Remote | Relies on pharmacists, telehealth; stock variability and longer delivery times |
- Patient Insight: Expectations often focus on sleep improvement rather than immediate mood lift.
- Pharmacists play a central role in counselling about trazodone hydrochloride and managing expectations for trazodone 50mg and trazodone 100mg tablets.
Availability And Pricing Patterns
Where can Australians get trazodone and what will it cost?
Trazodone is prescription‑only and supplied as generics or imported branded formulations, with extended‑release availability varying by supplier.
Major Australian pharmacy chains and accredited online pharmacies dispense trazodone on presentation of a valid e‑prescription or paper prescription.
Note: In our online pharmacy, trazodone is available without a prescription, with discreet delivery to Australia in 5‑14 days.
PBS subsidy varies by formulation and indication; off‑label uses such as insomnia are often privately paid and therefore more expensive for the consumer.
| Coverage | Typical Cost |
|---|---|
| PBS‑subsidised Products | Depends on formulation and indication; check PBS |
| Private / Off‑label Insomnia | Out‑of‑pocket — generics usually cheaper |
- Pharmacist Checklist: Watch for supply‑chain flags, therapeutic substitutions, and counsel on storage (15–30°C).
- Consumers are price sensitive and often prefer generic trazodone tablets over branded options.
Comparable Medicines And Preferences
What are the alternatives if trazodone is unsuitable?
For primary depression, SSRIs such as sertraline, escitalopram or fluoxetine are common first‑line alternatives in Australia.
Where sedative antidepressant effect is needed, mirtazapine or doxepin may be preferred, while tricyclics such as amitriptyline are used in neuropathic pain but carry anticholinergic burden.
For isolated insomnia, consider melatonin preparations, short courses of z‑drugs, or cognitive behavioural therapy for insomnia (CBT‑I) which remains first‑line.
| Patient Profile | Preferred Agent | Rationale |
|---|---|---|
| Depression With Insomnia | Trazodone or Mirtazapine | Sedating effect, less sexual dysfunction than SSRIs |
| Primary Depression Without Sleep Issues | SSRI (Sertraline/Escitalopram) | Better tolerability, PBS coverage |
| Neuropathic Pain With Sleep Disruption | Amitriptyline or Low‑Dose Trazodone | Analgesic properties and improved sleep, balance anticholinergic risk |
- Pros/Cons Snapshot: Trazodone — Pros: sedating, low sexual dysfunction; Cons: orthostasis, priapism risk.
- SSRIs — Pros: well‑tolerated, PBS‑covered; Cons: activation and sexual side effects.
FAQ
Common Australian patient questions about trazodone, answered plainly.
Q: Is trazodone addictive?
A: Trazodone is not a controlled substance and has low abuse potential, but abrupt stopping can cause withdrawal‑like symptoms so taper gradually.
Q: Can I drink alcohol while on trazodone?
A: Strongly avoid alcohol because it increases sedation and fall risk.
Q: Can trazodone be used for insomnia long‑term?
A: It is often used short‑term; long‑term use requires regular review for tolerance, side effects and increased fall risk in older adults.
Q: What is the risk of priapism?
A: Priapism is a rare but urgent medical emergency; persistent painful erection requires immediate presentation to an emergency department and prompt reporting to the prescriber.
| When To Seek Urgent Care | Action |
|---|---|
| Persistent painful erection (priapism) | Attend emergency department immediately |
| Severe dizziness, fainting, arrhythmia symptoms | Seek urgent medical assessment |
| Signs of serotonin syndrome | Emergency care and inform prescriber |
Referral prompts: contact your GP for routine concerns, attend emergency for urgent symptoms, or contact mental‑health crisis lines if suicidal thoughts occur.
Guidelines For Proper Use
What should pharmacists tell patients at the point of dispensing?
Confirm the indication — whether major depressive disorder or insomnia — before counselling on trazodone tablets and dosing.
Review the full medication list to identify serotonergic agents or QT‑prolonging drugs and advise accordingly.
Advise the patient on starting dose and timing, emphasising bedtime administration for sedative effect and slower titration in older adults.
Warn patients about orthostatic hypotension, advise rising slowly from sitting or lying positions and avoiding driving until they know how they respond.
Explain that trazodone is not a controlled drug but requires gradual tapering to reduce withdrawal risk.
- Step 1: Confirm indication and current medicines (including herbal or OTC).
- Step 2: Explain starting dose, expected onset for sleep vs mood, and common side effects.
- Step 3: Advise on safety (no alcohol, avoid driving until tolerant).
- Step 4: Recommend review in 2–4 weeks and blood pressure monitoring; check sodium in elderly if symptomatic.
- Step 5: Document any therapeutic substitution and communicate with the prescriber.
| Red‑Flag Symptoms | Urgent Action |
|---|---|
| Priapism | Emergency department immediately |
| Severe dizziness/fainting | Seek urgent medical review |
| Signs of serotonin syndrome | Emergency care |
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5–7 days |
| Melbourne | Victoria | 5–7 days |
| Brisbane | Queensland | 5–7 days |
| Perth | Western Australia | 5–7 days |
| Adelaide | South Australia | 5–7 days |
| Canberra | Australian Capital Territory | 5–7 days |
| Hobart | Tasmania | 5–7 days |
| Darwin | Northern Territory | 5–9 days |
| Gold Coast | Queensland | 5–7 days |
| Newcastle | New South Wales | 5–7 days |
| Wollongong | New South Wales | 5–7 days |
| Geelong | Victoria | 5–7 days |
| Townsville | Queensland | 5–9 days |
| Cairns | Queensland | 5–9 days |
| Bendigo | Victoria | 5–9 days |