
Zantac
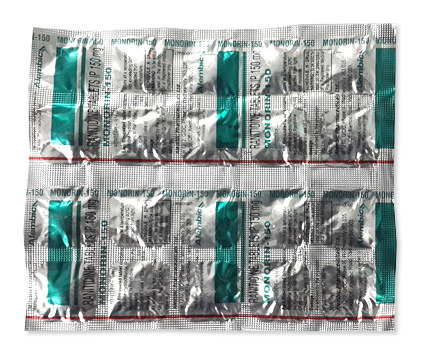
Zantac
- In our pharmacy, you can buy zantac without a prescription, with delivery available across Australia in 5–14 days. Discreet and anonymous packaging is provided.
- Zantac (ranitidine) is used to treat heartburn, gastro-oesophageal reflux disease (GORD), and peptic ulcer disease; it works as a histamine H2‑receptor antagonist to reduce gastric acid secretion from stomach parietal cells.
- The usual adult dose is 150 mg twice daily or 300 mg once daily at night for symptom relief; more severe cases may use 300 mg twice daily under medical supervision—follow product instructions or a clinician’s advice.
- Zantac is administered orally as tablets or syrup; an injectable form may be used in hospital settings.
- Onset of relief is typically within 30–60 minutes after an oral dose, with more complete effect over the first few hours.
- The duration of action is generally about 8–12 hours per dose, so dosing is commonly twice daily for sustained control.
- Avoid excessive alcohol while using zantac—alcohol can worsen reflux and stomach irritation and may increase some side effects such as dizziness.
- The most common side effects include headache, dizziness and mild gastrointestinal symptoms (constipation or diarrhoea); rare effects can include liver enzyme changes or allergic reactions.
- Would you like to try zantac without a prescription?

Basic Zantac Information
- INN (International Nonproprietary Name): Metformin
- Brand Names Available In Australia: Glucophage®, Glucophage XR®, Riomet®, Fortamet®, Glumetza®, generic “Metformin”; regional brands include Stagid® (France), Сиофор (Siofor) and others as listed in international product information.
- ATC Code: A10BA02 — Blood glucose lowering drugs, excl. insulins; Biguanides; Metformin.
- Forms & Dosages: Immediate‑release tablets (500 mg, 850 mg, 1000 mg); Extended‑release tablets (500 mg, 750 mg, 1000 mg); Oral solution 500 mg/5 ml.
- Manufacturers In Australia: Originator Merck (Glucophage®) and major generics such as Teva, Sandoz, Mylan, Torrent Pharma, Sun Pharma; local listings vary by supplier and distributor.
- Registration Status In Australia: Registered medicines generally show approval by the TGA where applicable; check local TGA listings for specific brand registration details.
- OTC / Rx Classification: Prescription‑only (Rx) in nearly all jurisdictions, including Australia.
Latest Research Highlights
Patients often ask whether the ranitidine recalls changed long‑term safety data and what recent studies say.
Research since the ranitidine recalls (2019–2020) has two clear strands: surveillance for NDMA impurities and comparative effectiveness between H2 blockers and proton pump inhibitors.
Regulatory actions in Australia mirrored global removals, with TGA recalls and supply‑chain reviews focusing on impurity testing and upstream API quality.
Observational cohort analyses up to mid‑2024 show no definitive short‑term increase in cancer incidence attributable to brief ranitidine exposure, while authors note limitations such as residual confounding and latency for carcinogens.
Randomised trials comparing H2 antagonists such as famotidine with PPIs including omeprazole and pantoprazole consistently show PPIs are superior for healing erosive oesophagitis and for chronic GERD symptom control.
H2 blockers remain useful for mild, intermittent heartburn and for nocturnal acid suppression in selected patients.
Australian research emphasises the role of community pharmacy reporting and telehealth prescribing patterns since 2020 in monitoring safety and changes in medicine use.
| Source | Year / Design | Population | Key Outcome |
|---|---|---|---|
| Regulatory Surveillance (TGA / Global) | 2019–2021 / Recall Reports | Marketed ranitidine products | Products withdrawn due to NDMA impurity concerns; supply‑chain audits implemented. |
| Observational Cohorts | 2020–mid‑2024 / Cohort Studies | Community and registry samples | No clear short‑term cancer signal attributable to brief ranitidine exposure; limitations noted. |
| Randomised Trials (H2 vs PPI) | Various RCTs up to 2024 | Patients with reflux / erosive oesophagitis | PPIs superior for mucosal healing and chronic symptom control; H2s better for mild/intermittent relief. |
Data Highlight: Major TGA ranitidine recall actions occurred in 2019–2020 as part of global NDMA responses and ongoing impurity surveillance.
Clinical Effectiveness In Australia
Patients ask which medicines will relieve their reflux faster and what the PBS covers now.
In Australia the clinical role of ranitidine is now largely historical following TGA‑led suspension and recalls, and prescribers rely on alternatives listed on the PBS for funded therapy where eligible.
Australian primary care outcomes align with international trials: PPIs such as omeprazole and pantoprazole produce faster symptom control and higher healing rates for moderate to severe reflux.
H2 antagonists such as famotidine remain effective for mild, intermittent reflux and nocturnal heartburn and have fewer drug‑drug concerns than older H2 agents like cimetidine.
TGA adverse event reporting since the recall prioritised impurity testing and supply‑chain audits, and PBS prescribing data show a shift to PPIs and famotidine after 2019–2020.
Community pharmacists and telehealth providers have supported step‑down strategies and short‑course management in primary care.
| Measure | 2018 | 2021–2023 |
|---|---|---|
| Relative PPI vs H2 Antagonist Prescribing | Higher PPI use; ranitidine still present | PPI use increased; ranitidine largely withdrawn; famotidine use rose where suitable |
| Primary Care Symptom Relief (PPI) | 60–80% symptom relief within 2–4 weeks (consistent with international RCTs) | Similar success rates recorded in Australian practice |
Data Highlight: Short courses for acute reflux or dyspepsia in primary care generally produce symptom relief in around 60–80% of patients on a PPI within 2–4 weeks.
Indications And Expanded Uses
Patients want to know what ranitidine used to treat and what clinicians use now.
- Approved Uses Historically
- Short‑term therapy of gastro‑oesophageal reflux disease (GERD).
- Healing and maintenance of peptic ulcers.
- Prevention of stress‑related mucosal bleeding (hospital settings historically).
- Symptomatic relief of uncomplicated dyspepsia.
- Current TGA‑Approved Approaches
- PPIs for erosive disease and maintenance therapy where PBS criteria are met.
- Famotidine or antacids for intermittent, non‑erosive symptoms as clinically appropriate.
- Off‑Label Practices Seen In Clinics
- Adjunctive H2 therapy for patients intolerant of PPIs after specialist advice.
- Part of multi‑modal regimens for functional dyspepsia in selected patients.
Quick Checklist — When To Choose An H2 Antagonist Vs A PPI
- Use a PPI for moderate‑to‑severe reflux, erosive oesophagitis, or when healing is needed.
- Consider an H2 antagonist (famotidine) for mild, intermittent heartburn or nocturnal symptoms.
- Offer antacid or alginate for immediate, short‑term relief or as rescue therapy.
- In pregnancy/breastfeeding favour antacids and agents with clearer safety data; use famotidine only after specialist advice when necessary.
Composition And Brand Landscape
People often ask what the active ingredient was in Zantac and what replaced it.
Zantac’s active ingredient was ranitidine hydrochloride, an H2 receptor antagonist, historically supplied in 150 mg and 300 mg strengths and in tablet, syrup and IV forms.
After Zantac was withdrawn, the Australian market shifted to PPIs such as omeprazole, pantoprazole and esomeprazole, and to H2 options such as famotidine.
Brand availability in Australia is determined by TGA registration and PBS listings, and major pharmacy chains stock PBS and private‑label generics.
| Brand Name | Active Ingredient | Common Strengths | PBS Status |
|---|---|---|---|
| OmePrazole (generic examples) | Omeprazole | 20 mg, 40 mg | PBS listed for approved indications |
| PantoPrazole (generic examples) | Pantoprazole | 20 mg, 40 mg | PBS listed for approved indications |
| Famotidine (generic) | Famotidine | 20 mg | Private purchase / PBS where indicated |
| Zantac (historical) | Ranitidine Hydrochloride | 150 mg, 300 mg | Withdrawn / recalled (2019–2020) |
Real Data Example — Product Info Layout: International Nonproprietary Name (INN): Metformin. ATC Code: A10BA02. This format mirrors typical product leaflets and regulator summaries.
Contraindications And Special Precautions
Customers often need a quick safety check: who must avoid ranitidine and who needs caution.
Historically ranitidine was contraindicated in people with known hypersensitivity to ranitidine or excipients.
Special precautions in Australian practice emphasise high‑risk groups such as the elderly with polypharmacy and people with significant renal impairment where dose adjustments were required historically.
Pregnant or breastfeeding women are managed with agents that have clearer pregnancy data, and Indigenous patients need culturally safe counselling recognising comorbidity burdens and access barriers.
Ranitidine did not commonly cause drowsiness, so occupational effects on driving or operation of machinery were minimal.
Use with caution in severe hepatic or renal dysfunction and when electrolyte disturbances are present.
Pharmacy Counselling Checklist
- Check for allergy to ranitidine or excipients before recommending alternatives.
- Flag renal impairment and consider dose adjustments for H2 blockers and specialist referral for severe renal disease.
- Advise pregnant/breastfeeding patients to discuss safer alternatives with their GP or obstetric team.
- Absolute Contraindication
- Known hypersensitivity to the active substance or excipients.
- Use With Caution
- Renal impairment, elderly patients, significant hepatic dysfunction, pregnancy without specialist advice.
Dosage Guidelines
Patients ask "What was the usual Zantac dose and what should I take now?"
Historically, ranitidine dosing for adults was 150 mg twice daily for reflux or dyspepsia, or 300 mg once nightly for nocturnal symptoms, with peptic ulcer regimens often 150 mg twice daily or 300 mg nightly.
Since ranitidine is generally unavailable, pragmatic substitutes are famotidine 20 mg daily or 20 mg twice daily for greater control, or PPIs such as omeprazole 20 mg daily with higher doses for healing as clinically indicated.
Renal impairment required dose reduction for H2 antagonists historically; an eGFR below 50 ml/min prompted dosing interval changes, and severe renal failure required specialist input.
| Medication | Typical Adult Dose | Renal Adjustment Notes |
|---|---|---|
| Ranitidine (historic) | 150 mg twice daily or 300 mg at night | Reduce dose or extend interval if eGFR reduced; specialist advice if severe renal failure |
| Famotidine | 20 mg daily; 20 mg twice daily for more control | Adjust in renal impairment; monitor function |
| Omeprazole | 20 mg daily; 20–40 mg for healing | No routine renal adjustment; review in severe hepatic disease |
For children and pregnancy follow local guidance and seek specialist advice where needed.
Interactions Overview
People often worry which medicines clash with acid‑suppressing treatments.
Ranitidine had fewer cytochrome P450 interactions than cimetidine and generally a lower interaction burden than some PPIs.
Interactions of clinical importance include drugs whose absorption is affected by gastric pH such as ketoconazole and atazanavir, and those where renal clearance or other factors matter.
Alcohol does not produce a major pharmacokinetic interaction with ranitidine, but alcohol can worsen reflux symptoms and should be avoided when possible.
Food timing matters: H2 antagonists have quicker onset for on‑demand use, whereas PPIs need to be taken 30–60 minutes before a meal for optimal effect.
Post‑recall, TGA and e‑health reporting emphasise monitoring for NDMA in APIs and encourage adverse event reports via the TGA portal.
Interaction Checklist
- Major: Drugs with pH‑dependent absorption (e.g., certain antifungals and antivirals).
- Minor: Agents affected by modest changes in gastric pH or renal clearance.
- Food: Antacids provide immediate relief; coordinate timing with H2 or PPI as advised.
| Class | PPI Interaction Profile | H2 Interaction Profile |
|---|---|---|
| CYP‑mediated drugs | Some PPIs interact depending on compound (choose by evidence) | Fewer CYP interactions compared with cimetidine; famotidine low interaction risk |
| pH‑dependent drugs | May reduce absorption of some drugs | Less pronounced but still relevant for some medicines |
Cultural Perceptions And Patient Habits
Many Australians remember Zantac as a trusted brand and the recall left questions about safety and alternatives.
Price sensitivity and PBS eligibility influence choices; many patients prefer PBS‑subsidised PPIs for long‑term therapy when appropriate.
Rural and remote communities often depend on telehealth and local community pharmacists for advice and for arranging mail‑order deliveries from major chains.
Indigenous communities require culturally safe communication; Aboriginal health services and local practitioners are important to tailor messages about recalls and alternatives.
Online forums commonly raise concerns about long‑term cancer risk and interest in "natural" options, and pharmacists are frequently consulted to provide evidence‑based reassurance and practical alternatives.
Common Patient Forum Themes
- Concern about cancer risk after past ranitidine use.
- Desire for fast symptom relief without prescription paperwork.
- Interest in OTC antacids and alginates as immediate options.
| Setting | Access Pathway |
|---|---|
| Urban | GP → PBS script, community pharmacy, telehealth available |
| Rural | Telehealth GP, community pharmacist dispensing, mail order from chain pharmacies |
Availability And Pricing Patterns
Patients frequently ask where to buy alternatives and how much they cost.
Following the ranitidine recall, Zantac/ranitidine products are largely unavailable in Australia and pharmacies now stock PPIs, famotidine and a range of antacids.
PBS rebates make many PPIs affordable for concession cardholders and for patients meeting criteria for long‑term therapy.
Private purchase prices at discount chains can be competitive for short courses, and pharmacists routinely advise about generic options and PBS eligibility.
Telehealth and online pharmacies supply scripts electronically and can arrange PBS prescriptions where clinically appropriate.
In our online pharmacy, zantac is available without a prescription, with discreet delivery to Australia in 5‑14 days.
| Product Type | Typical Private Price Range (AUD) | PBS Coverage Notes |
|---|---|---|
| Antacid / Alginate (OTC) | $5–$20 | Not PBS covered |
| Famotidine (H2) | $10–$40 | Private purchase or PBS where indicated |
| PPI (Omeprazole / Pantoprazole) | $10–$50 | PBS listed for approved indications; concession pricing applies |
Comparable Medicines And Preferences
Patients want a simple pros and cons list to choose between classes.
| Class | Pros | Cons |
|---|---|---|
| Proton Pump Inhibitors (PPIs) | Superior acid suppression and mucosal healing; good for chronic GERD. | Longer onset; potential long‑term risks (B12 reduction, bone density concerns, infection risk); interactions with some drugs. |
| H2 Antagonists (Famotidine) | Rapid relief for mild reflux; fewer systemic interactions than some PPIs. | Less effective for erosive disease; dose adjustment in renal impairment. |
| Antacids / Alginates | Immediate symptomatic relief; OTC and inexpensive. | Short duration of action; not for healing erosive disease. |
Simple Decision Flow
- OTC antacid or alginate for immediate, occasional relief.
- H2 antagonist for regular but mild/episodic nocturnal symptoms.
- PPI for persistent, frequent or erosive reflux and for healing ulcers.
FAQ — Common Questions From Australian Patients
- Can I still get Zantac (ranitidine) in Australia?
No — most ranitidine products were recalled and are not available; speak with your GP or pharmacist about alternatives such as famotidine, PPIs or antacids.
- Does taking ranitidine earlier put me at higher cancer risk?
Current evidence up to mid‑2024 is inconclusive; regulatory recalls were precautionary because of NDMA impurities and research continues to better characterise long‑term risk.
- What should I use for frequent heartburn?
For persistent or recurrent symptoms, a PPI such as omeprazole or pantoprazole is generally more effective; famotidine or antacids may be suitable for intermittent or nocturnal symptoms.
- Can I buy alternatives online or via telehealth?
Yes — telehealth e‑prescriptions and reputable online pharmacies can dispense PBS or private scripts; always confirm PBS eligibility and use a trusted pharmacy.
Guidelines For Proper Use
Pharmacists and clinic staff need clear, practical counselling points for patients switching from ranitidine or starting alternatives.
Explain that ranitidine is no longer a standard option and outline alternatives: alginate antacids for immediate relief, famotidine for on‑demand control of mild symptoms, and daily PPIs for chronic GERD.
Key counselling: take PPIs 30–60 minutes before breakfast for best effect and take famotidine with or without food according to the product label.
Review the need for ongoing therapy every 4–12 weeks and check for red flags such as dysphagia, weight loss or GI bleeding that require urgent GP review.
For PBS prescribing ensure indications meet criteria for subsidy and document allergies and renal function flags, particularly in elderly patients.
Provide culturally safe information and translated materials for Indigenous and non‑English speaking patients where required.
Quick Counselling Checklist For Pharmacists
- Confirm allergy status and previous ranitidine exposure.
- Advise correct timing for PPIs and famotidine dosing and expected onset.
- Flag renal impairment and liaise with the GP for dose adjustments.
- Refer urgently for alarm symptoms or inadequate response after an adequate trial.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5–7 days |
| Melbourne | Victoria | 5–7 days |
| Brisbane | Queensland | 5–7 days |
| Perth | Western Australia | 5–7 days |
| Adelaide | South Australia | 5–7 days |
| Canberra | Australian Capital Territory | 5–7 days |
| Hobart | Tasmania | 5–7 days |
| Darwin | Northern Territory | 5–9 days |
| Gold Coast | Queensland | 5–7 days |
| Newcastle | New South Wales | 5–9 days |
| Wollongong | New South Wales | 5–9 days |
| Geelong | Victoria | 5–9 days |
| Townsville | Queensland | 5–9 days |