
Reglan
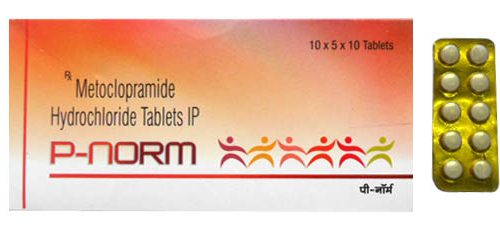
Reglan
- In our pharmacy, you can buy reglan without a prescription, with delivery in 5–14 days throughout Australia. Discreet and anonymous packaging.
- Reglan (metoclopramide) is used for nausea and vomiting, diabetic gastroparesis and as a prokinetic for reflux/GERD; it acts as a dopamine (D2) receptor antagonist with central antiemetic action in the chemoreceptor trigger zone and peripheral prokinetic effects on gastrointestinal motility.
- Usual dosage: adults commonly 10 mg orally up to 4 times daily (for gastroparesis typical total ≤40 mg/day; for short-term GERD 10–15 mg up to 4× daily with a possible maximum of 60 mg/day in some regimens); IV/IM dosing is individualised for acute nausea; children are weight‑based and elderly or those with renal/hepatic impairment require dose reduction and short durations.
- Forms of administration: tablets (5 mg, 10 mg), orally disintegrating tablets, oral solution (5 mg/5 mL), injectable solution (5 mg/mL ampoules/vials) and a nasal spray formulation (Gimoti in some markets).
- Onset time: orally usually within about 15–60 minutes; IV acts within minutes and IM within around 10–30 minutes.
- Duration of action: effects commonly last about 4–6 hours (plasma half‑life ≈5–6 hours), so repeat dosing is often required for ongoing symptoms.
- Alcohol warning: avoid alcohol — it can increase drowsiness and other central nervous system side effects and may worsen extrapyramidal reactions.
- The most common side effect is drowsiness (other frequent effects include fatigue, restlessness/akathisia, headache, nausea and diarrhoea; prolonged use risks tardive dyskinesia).
- Would you like to try reglan without a prescription?
Basic Reglan Information
- INN (International Nonproprietary Name): Metoclopramide.
- Brand Names Available In Australia: not specified.
- ATC Code: A03FA01.
- Forms & Dosages: Tablets 5 mg and 10 mg; Orally disintegrating tablets 5 mg and 10 mg; Oral solution 5 mg/5 mL; Injectable solution 5 mg/mL (ampoules/vials); nasal spray available in some other markets.
- Manufacturers In Australia: not specified.
- Registration Status In Australia: not specified.
- OTC / Rx Classification: Prescription-only (Rx) in nearly all jurisdictions due to neurological risk.
Latest Research Highlights
Patients and prescribers often ask whether metoclopramide still has a place in practice given recent safety reviews.
Large international and Australian analyses from 2022–2025 support metoclopramide’s short-term benefit for nausea control, diabetic gastroparesis symptom relief and adjunctive use in some reflux cases.
Regulatory agencies including the FDA, EMA and TGA have issued safety communications that emphasise limiting duration and cumulative dose because of extrapyramidal symptoms and tardive dyskinesia risk.
Systematic reviews show symptomatic improvement compared with placebo in diabetic gastroparesis, but effect size varies and adverse events rise with prolonged exposure.
Australian pharmacovigilance summaries in the TGA Database of Adverse Event Notifications report cases consistent with global signals, notably acute dystonia in younger adults and tardive dyskinesia in older patients with longer exposure.
Head-to-head trials versus domperidone or erythromycin are limited and mixed, with comparative cardiac and antibiotic stewardship considerations affecting choice.
Trial Outcomes Summary
| Outcome | Effect Versus Placebo | NNT (Where Available) | EPS Incidence |
|---|---|---|---|
| Diabetic Gastroparesis Symptoms | Modest improvement in symptom scores reported | not specified | Increased with longer use; acute EPS reported |
| Acute Nausea/Vomiting | Short-term benefit for chemotherapy and post-op nausea | not specified | Lower with short courses; risk rises with cumulative dose |
| Reflux Adjunctive Use | Symptomatic relief in select refractory cases | not specified | Variable; caution in elderly |
Data Highlight
The TGA adverse-event reports align with international findings showing acute dystonia in younger adults and tardive dyskinesia in older patients with prolonged exposure.
Specific TGA counts are not specified in the product information provided, but reporting emphasises vigilance and limiting duration.
Clinical Effectiveness In Australia
Which patients benefit most from metoclopramide in everyday Australian practice?
Short courses are effective for acute nausea such as chemotherapy-related nausea and post-operative vomiting, according to hospital audit series and specialist clinic reports.
In tertiary gastroenterology clinics, metoclopramide speeds gastric emptying on studies and lowers symptom scores over weeks for diabetic gastroparesis, but benefits often wane if treatment is prolonged.
TGA registrations allow prescription use, and most real-world effectiveness data in Australia are from audits and specialist case series rather than large PBS-funded randomised trials.
Measured Outcomes
- Symptom scales (gastroparesis cardinal symptom index and similar tools) show modest short-term improvements.
- Gastric emptying studies demonstrate accelerated transit with metoclopramide in responsive patients.
- Patient-reported nausea frequency and need for rescue antiemetic are commonly used measures.
| Benefit Timing | Short-Term (Days–Weeks) | Long-Term (Months) |
|---|---|---|
| Effect | Noticeable symptomatic relief and improved gastric emptying | Benefits often decrease; tachyphylaxis or relapse reported |
| Risk | Lower risk of EPS when limited to short courses | Increased risk of tardive dyskinesia with prolonged use |
Most Australian prescriptions for metoclopramide are private scripts, and telehealth e-prescriptions have increased access in rural areas while making careful follow-up essential.
Indications And Expanded Uses
People often want to know when metoclopramide is appropriate and how long it can be used.
TGA-aligned indications match international practice and include acute nausea and vomiting, facilitation of gastric emptying in diabetic gastroparesis, and adjunctive treatment in some refractory reflux cases.
Off-label uses seen in Australian practice include radiology preparation antiemesis, procedural prophylaxis and short-term treatment for migraine-associated vomiting.
Approved Versus Off-Label Uses
- Approved: Acute nausea/vomiting, diabetic gastroparesis facilitation, adjunct in certain reflux cases.
- Off-Label: Radiology preparation, procedural antiemesis, short-term migraine vomiting control.
| Indication | Typical Australian Regimen | Recommended Maximum Duration |
|---|---|---|
| GERD / Reflux Adjunct | 10–15 mg up to four times daily (max 60 mg/day) | 4–12 weeks |
| Diabetic Gastroparesis | 10 mg up to four times daily (max 40 mg/day) | 2–8 weeks |
| Procedure/Chemotherapy Nausea | Individualised dosing; IV/IM options available | Single dose or short-term |
Contraindications include GI obstruction, perforation or haemorrhage and pheochromocytoma, which make metoclopramide unsuitable.
Composition And Brand Landscape
What exactly is in each tablet or ampoule, and where does it come from?
The active ingredient is metoclopramide, commonly provided as metoclopramide hydrochloride in many formulations.
The ATC classification is A03FA01, the propulsive/metoclopramide group for gastrointestinal motility agents.
| Brand | Region | Forms & Strengths |
|---|---|---|
| Reglan | USA, Romania, France | Tablets 5 mg / 10 mg; Oral solution 5 mg/5 mL; Injectable 5 mg/mL |
| Metozolv ODT | USA | Orally disintegrating tablets 5 mg / 10 mg |
| Primperan | France and EU | Tablets, solution, ampoules |
| Perinorm | India, Southeast Asia | Tablets, solution, ampoules |
| Gimoti | USA | Nasal spray (gastroparesis) |
In Australia, most metoclopramide products are supplied as generics from international manufacturers, with packaging and strengths matching the global forms of tablets, oral solution and injectables.
Common retail supply points include major community pharmacy chains and online pharmacies.
Contraindications And Special Precautions
Who should avoid metoclopramide, and which patients need extra care?
Absolute contraindications include pheochromocytoma, gastrointestinal obstruction, perforation or haemorrhage, a previous history of tardive dyskinesia from metoclopramide, uncontrolled epilepsy and known hypersensitivity.
Relative cautions apply to patients with Parkinson’s disease, depression or other psychiatric histories, renal or hepatic impairment, the elderly and breastfeeding mothers because the drug passes into milk.
Prescriber Checklist
- Confirm no history of tardive dyskinesia or hypersensitivity.
- Check for GI obstruction, perforation or active GI bleeding before prescribing.
- Review current antipsychotic or dopamine antagonist therapy that increases EPS risk.
- Assess renal and hepatic function and consider dose reduction for impairment.
- Document intention to limit duration and schedule follow-up review.
Advise patients to avoid driving or operating machinery if they feel drowsy or experience movement side-effects, and counsel on alcohol as it can increase sedation.
Extra vigilance is recommended for Indigenous and remote community patients with multimorbidity and limited follow-up access.
Dosage Guidelines
How should metoclopramide be dosed for common conditions in Australian practice?
Standard adult regimens include GERD management at 10–15 mg up to four times daily with a maximum of 60 mg/day for 4–12 weeks.
Diabetic gastroparesis is commonly treated with 10 mg up to four times daily with a typical maximum daily dose of 40 mg for 2–8 weeks.
Injectable metoclopramide for acute settings is commonly available as 5 mg/mL and dosing is individualised for chemotherapy-related nausea or procedural use.
| Indication | Typical Dose | Maximum | Duration |
|---|---|---|---|
| GERD / Reflux Adjunct | 10–15 mg up to four times daily | 60 mg/day | 4–12 weeks |
| Diabetic Gastroparesis | 10 mg up to four times daily | 40 mg/day | 2–8 weeks |
| Procedure/Chemotherapy | Individualised IV/IM dosing | not specified | Single dose or short-term |
For elderly patients and those with renal or hepatic impairment, start at the lower end of the dose range and reduce frequency or dose as clinically indicated.
For children use weight-based dosing and avoid neonates where possible.
Interactions Overview
Which medicines or substances commonly interact with metoclopramide?
Metoclopramide has additive central nervous system depression with alcohol and sedatives, so counsel patients accordingly.
Co-prescribing with antipsychotics or other dopamine antagonists increases the risk of extrapyramidal symptoms and requires careful review.
Because metoclopramide accelerates gastric emptying it can alter the absorption of orally administered medicines, potentially changing their onset and effect.
| High-Risk Combination | Interaction Mechanism | Management Tip |
|---|---|---|
| Antipsychotics / Neuroleptics | Increased EPS and tardive dyskinesia risk | Avoid co-prescribing or monitor closely; consult psychiatry if needed |
| Alcohol / Sedatives | Enhanced CNS depression | Advise patients to avoid alcohol and caution with driving |
| Oral Medicines Sensitive To Gastric Emptying | Altered absorption and onset | Monitor therapeutic effect; consider dose timing adjustments |
In Australian e-health records and TGA reports, antipsychotic co-prescribing is a commonly flagged risk scenario, so pharmacists should screen for interacting neuroleptics when dispensing metoclopramide.
Cultural Perceptions And Patient Habits
How do Australians view metoclopramide, and how do pharmacists tailor advice?
Many patients want rapid symptom relief and are price-aware, which influences choice between branded and generic metoclopramide tablets or oral solution.
There is high public trust in pharmacists for medicine advice, and telehealth plus online pharmacies have widened access in rural areas.
Patient forums and clinic feedback often express concern about neurological side effects and a preference for short courses where possible.
Culturally Tailored Counselling Tips
- Use plain language leaflets and, where relevant, translated materials for non-English speakers.
- Offer follow-up calls for remote and Indigenous patients to check for movement side-effects and adherence.
- Respect patient concern about visible movement disorders and explain the rationale for short durations.
For example, an urban patient may choose a single short course for post-op nausea, while a rural patient may prefer scheduled pharmacist follow-up because access to specialists is limited.
Availability And Pricing Patterns
Where can Australians obtain metoclopramide and what does it cost?
Metoclopramide is prescription-only in Australia, typically available from community pharmacies such as Chemist Warehouse, Priceline and independent pharmacies.
Generic metoclopramide products for tablets, oral solution and injectables are commonly stocked, and prices vary by pharmacy and pack size.
| Pharmacy Channel | Likely Price | Turnaround For E-Script | Rural Availability |
|---|---|---|---|
| Major Chain (e.g., Chemist Warehouse) | Lower cost for generics | Same day to 2 days | Depends on stock; often available |
| Independent Pharmacy | Variable; competitive | Same day to 3 days | Often used for local supply and advice |
| Online Pharmacy / Telehealth | Competitive; compare chains | 2–7 days depending on delivery | Useful for remote patients; may require hospital order for injectables |
Clinicians should check current PBS listings for subsidised access as coverage can vary by indication and change over time.
In our online pharmacy, reglan is available without a prescription, with discreet delivery to Australia in 5-14 days.
Comparable Medicines And Preferences
What are practical alternatives to metoclopramide and how do they compare?
Alternatives used in Australia include domperidone, erythromycin, ondansetron and prochlorperazine, each carrying different benefits and risks.
- Domperidone avoids central dopamine blockade and has less EPS risk, but carries cardiac QT and proarrhythmia concerns requiring ECG consideration.
- Erythromycin can act as a prokinetic but is an antibiotic with stewardship concerns and tachyphylaxis over time.
- Ondansetron and prochlorperazine are effective antiemetics for many causes of nausea but work by different mechanisms and have their own adverse-event profiles.
Choice depends on age, cardiac risk, psychiatric history, pregnancy and PBS cost considerations, with metoclopramide favoured for short-term central antiemetic and prokinetic effects.
Prescribing Algorithm Prompts
- Assess urgency of nausea control and cause (chemotherapy, post-op, gastroparesis, reflux).
- Screen for QT risk if considering domperidone or drugs that prolong QT.
- Avoid prolonged metoclopramide use in elderly; prefer alternatives or specialist review for long-term management.
FAQ
-
Is metoclopramide available on the PBS?
Coverage varies by indication and can change; check current PBS listings before prescribing.
-
How long is it safe to take metoclopramide?
Guidance recommends short courses — typically days to weeks depending on indication, with common ranges of 2–12 weeks; prolonged use increases the risk of tardive dyskinesia.
-
Can I drive while taking metoclopramide?
Avoid driving or operating machinery if you feel drowsy, dizzy or experience movement side-effects.
-
What should pregnant or breastfeeding patients do?
Use with caution and discuss risks and benefits with the prescriber because metoclopramide passes into breastmilk.
| When To Call Your GP Or Emergency Department | Examples |
|---|---|
| Acute Dystonia | Sudden neck spasm, tongue protrusion or severe muscle contractions |
| Severe Sedation Or Confusion | Unable to stay awake or marked disorientation |
| New Involuntary Movements | Persistent or worsening abnormal facial or limb movements |
Guidelines For Proper Use
How should pharmacists and prescribers counsel patients and monitor therapy?
Confirm indication and intended maximum duration on the prescription, and document baseline neurological history and current neuroleptic use.
Dispense the lowest effective dose and avoid large repeat supplies without clinical review.
Recommend follow-up within 1–2 weeks for acute prescriptions and more frequent review for elderly patients or those with renal impairment.
Pharmacist Checklist
- Verify indication, dose and intended duration before supply.
- Screen the medication list for antipsychotics, strong sedatives or other dopamine antagonists.
- Provide a patient leaflet that lists expected benefits, common side-effects and emergency signs.
Storage advice: store at room temperature (20–25°C), keep liquids from freezing and protect injectables from light if required.
For telehealth prescriptions arrange a scheduled review and confirm local pharmacy stock for rural patients.
Delivery Across Australia
| City | Region | Delivery time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Darwin | Northern Territory | 5-7 days |
| Gold Coast | Queensland | 5-9 days |
| Newcastle | New South Wales | 5-9 days |
| Wollongong | New South Wales | 5-9 days |
| Sunshine Coast | Queensland | 5-9 days |
| Geelong | Victoria | 5-9 days |
| Townsville | Queensland | 5-9 days |
| Cairns | Queensland | 5-9 days |