
Omnicef
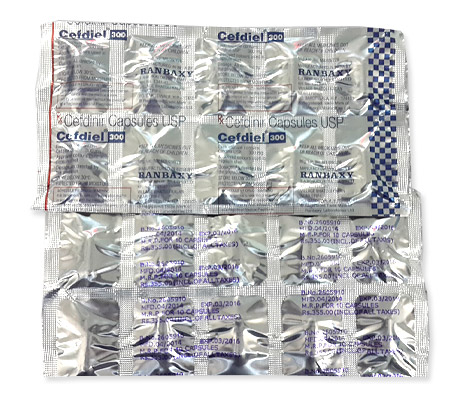
Omnicef
- In our pharmacy, you can buy omnicef without a prescription, with delivery in 5–14 days throughout Australia and discreet packaging (note: cefdinir/Omnicef is officially prescription‑only in most jurisdictions).
- Omnicef (cefdinir) is a third‑generation oral cephalosporin antibiotic used to treat bacterial infections such as community‑acquired pneumonia, acute maxillary sinusitis, pharyngitis/tonsillitis, acute exacerbations of chronic bronchitis and uncomplicated skin/skin‑structure infections; it works by inhibiting bacterial cell‑wall synthesis via binding to penicillin‑binding proteins, causing cell lysis of susceptible organisms.
- Usual dosage: Adults and adolescents (≥13 years) — typically 300 mg every 12 hours (or 600 mg once daily for some indications) for 5–10 days (pneumonia often 10 days); children (6 months–12 years) — weight‑based dosing commonly 14 mg/kg/day divided q12–24h for pneumonia/sinusitis, pharyngitis 7 mg/kg q12h or 14 mg/kg once daily; maximum paediatric dose 600 mg/day; reduce dosing frequency for creatinine clearance <30 mL/min.
- Form of administration: Oral only — 300 mg capsules and reconstitutable oral suspension (125 mg/5 mL and 250 mg/5 mL) for paediatric use.
- Onset time (how fast it starts working): Bactericidal activity begins shortly after absorption; many patients notice symptomatic improvement within 24–72 hours, though full clinical response may take several days.
- Duration of action: Plasma half‑life is approximately 1.7–2 hours in adults (longer with renal impairment); dosing schedules provide effective coverage for 12–24 hours per dose. Treatment courses are typically 5–10 days depending on indication (pneumonia and some skin infections often 10 days).
- Alcohol warning: There is no known disulfiram‑like interaction with omnicef, but avoid excessive alcohol while taking it as alcohol can worsen side effects (nausea, dizziness) and may delay recovery.
- Most common side effect: Gastrointestinal upset — diarrhoea is the most common, with nausea, vomiting and abdominal pain also frequent; other effects include rash, headache and vaginal candidiasis; seek medical attention for severe or persistent diarrhoea (risk of C. difficile).
- Would you like to try omnicef without a prescription?
Basic Omnicef Information
- INN (International Nonproprietary Name): Cefdinir
- Brand Names Available In Australia: not specified
- ATC Code: J01DD15
- Forms & Dosages: Capsules 300 mg; Oral Suspension 125 mg/5 mL and 250 mg/5 mL (reconstitutable)
- Manufacturers In Australia: not specified
- Registration Status In Australia: not specified
- OTC / Rx Classification: Prescription-only (Rx) in all major jurisdictions
Latest Research Highlights
Worried whether omnicef still works for common coughs and skin sores?
Recent surveillance from 2022–24, both in Australia and overseas, reinforces cefdinir’s established oral role for community respiratory infections and uncomplicated skin infections as noted in clinical summaries.
Clinical trial reports and observational series show short-course cefdinir regimens perform similarly to other oral third‑generation cephalosporins for community‑acquired pneumonia and acute bacterial sinusitis when pathogens are susceptible.
Paediatric dosing studies using 125 mg/5 mL and 250 mg/5 mL suspensions and 300 mg capsules report comparable cure rates in uncomplicated childhood infections compared with alternatives.
Microbiology surveillance highlights localized increases in Enterobacterales resistance to some third‑generation cephalosporins, so clinicians should check state and local antibiograms before routine use.
Safety surveillance continues to match the known profile — gastrointestinal upset and rash remain most common, with rare reports of C. difficile‑associated diarrhoea.
Paediatric reports of red stool associated with concomitant iron supplementation remain documented and are recognised as a benign interaction rather than gastrointestinal bleeding.
| Outcome | Resistance Observations | Safety Frequencies |
|---|---|---|
| Short-course efficacy for CAP and sinusitis | Localized Enterobacterales resistance pockets; review local antibiogram | Common: GI upset; Rare: C. difficile, red stool with iron |
| Comparable paediatric cure rates for uncomplicated infections | Variable Streptococcus pneumoniae susceptibility by region | Occasional rash; monitoring advised in penicillin‑allergic history |
Clinical Effectiveness In Australia
Wondering if omnicef is a sensible choice for infections seen in Australian general practice?
Cefdinir is an oral third‑generation cephalosporin used in Australia largely for community respiratory infections and uncomplicated skin and skin‑structure infections.
TGA dossier assessments and clinical usage align with international dosing where adults commonly take 300 mg every 12 hours or 600 mg once daily depending on indication.
Paediatric dosing is weight‑based using reconstitutable suspensions such as 125 mg/5 mL or 250 mg/5 mL, with a maximum paediatric dose of 600 mg per day.
PBS and real‑world dispensing data indicate good adherence for PBS‑subsidised antibiotic scripts and strong urban access through major pharmacy chains.
Telehealth services have increased outpatient prescribing reach, helping some rural patients obtain timely treatment but also raising stewardship queries.
Effectiveness compared with amoxicillin/clavulanate, cefuroxime or cefixime depends on the likely pathogen and local resistance patterns; cefdinir’s palatable suspension and simple dosing are advantages in children.
Indications And Expanded Uses
Which infections is omnicef routinely used for, and when is it an alternative?
- Approved Uses: Community‑acquired pneumonia, acute maxillary sinusitis, pharyngitis/tonsillitis, acute exacerbations of chronic bronchitis, uncomplicated skin/skin‑structure infections.
- Typical Duration: 5–10 days depending on diagnosis; pneumonia and selected skin infections often treated for 10 days.
- Off‑Label Use: Selected ENT infections or as an alternative when first‑line penicillins are unsuitable due to allergy or intolerance, used at clinician discretion.
- Paediatric Limit: Maximum 600 mg/day; weight‑based dosing applies.
| Indication | Typical Duration |
|---|---|
| Community‑acquired Pneumonia | 10 days |
| Acute Maxillary Sinusitis | 10 days |
| Pharyngitis/Tonsillitis | 5–10 days |
| Uncomplicated Skin Infection | 10 days |
Composition And Brand Landscape
Who makes omnicef and what formats will you see on the shelf?
The active ingredient is cefdinir (INN) and it is classified under ATC code J01DD15 as a third‑generation cephalosporin.
Globally the original US brand Omnicef has become generic, and other regional names include Cefzon in Japan; many markets now supply generic cefdinir formulations.
Available forms are 300 mg capsules and oral suspensions 125 mg/5 mL and 250 mg/5 mL, typically sold as reconstitutable powders with child‑friendly flavours.
| Form | Strength | Common Supplier Note |
|---|---|---|
| Capsule | 300 mg | Generics widely available globally |
| Oral Suspension | 125 mg/5 mL; 250 mg/5 mL | Reconstitutable, paediatric flavours |
In Australia, cefdinir products are primarily generics and availability or PBS listing can vary; always check ARTG or PBS entries for current sponsors and subsidy status.
Contraindications And Special Precautions
What should a pharmacist check before recommending omnicef?
- Absolute Contraindication: Known allergy to cephalosporins or prior severe hypersensitivity to beta‑lactams.
- Relative Precautions: Documented penicillin allergy (cross‑reactivity is rare but possible), significant renal impairment, and history of severe gastrointestinal disease, particularly colitis.
- Renal Considerations: For creatinine clearance below 30 mL/min, adjust the dosing interval to every 24 hours; monitor renal function in elderly patients.
- Pregnancy/Breastfeeding: Use only if clearly indicated; limited safety data mean benefit–risk assessment is required.
- Indigenous Health Considerations: Aboriginal and Torres Strait Islander patients may have different comorbidity patterns and access issues; arrange closer follow‑up where appropriate.
Counselling Points: Advise patients to stop and seek urgent care for signs of anaphylaxis or severe diarrhoea, and to report any rash.
Dosage Guidelines
How should omnicef be dosed for adults and children, and what about renal problems?
| Age/Group | Typical Regimen |
|---|---|
| Adults | 300 mg every 12 hours, or 600 mg once daily depending on indication |
| Children | 14 mg/kg/day divided q12–24h for pneumonia and sinusitis; 7 mg/kg q12h for some infections; maximum 600 mg/day |
| Renal Impairment | If CrCl <30 mL/min, extend dosing interval to every 24 hours |
- Community‑Acquired Pneumonia: Adults 300 mg q12h for 10 days; paediatric weight‑based equivalent.
- Pharyngitis/Tonsillitis: 300 mg q12h or 600 mg once daily for 5–10 days.
- Storage Note: Capsules at 20–25°C; reconstituted suspension stored at 20–25°C and discarded after 10 days.
Interactions Overview
Could omnicef react with medicines or supplements the patient already takes?
- Iron Interaction: Concomitant iron supplements or iron‑containing infant formulas can produce red stool and may reduce cefdinir absorption; separate dosing by 2–3 hours where practical.
- Nephrotoxic Drugs: Co‑administration with other nephrotoxins such as aminoglycosides warrants renal monitoring.
- Antacids and Sucralfate: Over‑the‑counter antacids and sucralfate may affect absorption; check and counsel accordingly.
- Alcohol: No specific ethanol interaction is documented, but advise avoiding alcohol while unwell.
Pharmacists should review the patient’s e‑health medication list for OTC iron, antacids or sucralfate and flag interactions before dispensing.
Cultural Perceptions And Patient Habits
How do Australians view antibiotics like omnicef and how does that affect adherence?
- Price Sensitivity: Many patients choose generics and PBS subsidies influence uptake and adherence to prescribed antibiotics.
- Pharmacy Trust: Community pharmacists at major chains are frequently the first point of advice and are trusted for clear counselling on dosing and side effects.
- Telehealth Impact: Urban patients increasingly access telehealth and online pharmacies for prescriptions while rural patients still face stock shortages and longer travel or delivery times.
- Online Concerns: Social media and patient forums often discuss side effects and red stools in children when iron is taken, increasing demand for clear counselling.
| Setting | Typical Access Pattern |
|---|---|
| Urban | Rapid access via chains and telehealth; same‑day or next‑day pickup common |
| Rural/Remote | Possible stock shortages; longer wait times and courier delivery often required |
Availability And Pricing Patterns
Where can patients buy omnicef in Australia and what will it cost them?
Cefdinir is generally supplied as a generic worldwide and availability in Australia can vary; check the ARTG for current sponsors and PBS for subsidy details.
Many cefdinir products are not PBS‑listed, which means private purchase through community pharmacies or online is often required.
In our online pharmacy, omnicef is available without a prescription, with discreet delivery to Australia in 5–14 days.
| Price Type | Estimate |
|---|---|
| PBS Price | not specified |
| Typical Private Price | Varies by supplier, formulation and pack size; not specified |
- Consumer Checklist: Check ARTG/ARTG entries, ask the pharmacist for a generic equivalent, compare capsule vs suspension options and ask about delivery to remote addresses.
- Paediatric Cost Note: Consider waste from reconstituted suspension being discarded after 10 days when budgeting for treatment.
Comparable Medicines And Preferences
What are the main alternatives to omnicef and when are they preferred?
- Common Alternatives: Amoxicillin/clavulanate (Augmentin), cefuroxime, cefixime and azithromycin.
- Pros For Cefdinir: Convenient oral dosing, broad Gram‑negative coverage relative to first‑generation agents, palatable paediatric suspension.
- Cons For Cefdinir: Stewardship concerns around third‑generation cephalosporins and potential for C. difficile; not always first line for uncomplicated streptococcal infections.
- Comparative Notes: Cefalexin (first‑generation) has narrower Gram‑negative coverage but strong streptococcal activity; amoxicillin/clavulanate often preferred for sinus and dental infections; azithromycin used in penicillin allergy but has distinct resistance patterns.
| Agent | Spectrum/Use | Stewardship Note |
|---|---|---|
| Cefdinir | Third‑gen oral cephalosporin; respiratory and uncomplicated skin infections | Reserve for appropriate bacterial infections; avoid for viral illnesses |
| Amoxicillin/Clavulanate | Broad‑spectrum penicillin with beta‑lactamase inhibition; sinus and dental infections | Often first‑line where appropriate |
Frequently Asked Questions
Q: Can I buy Omnicef without a prescription in Australia?
A: No—cefdinir is prescription‑only in major jurisdictions, but check local pharmacy options and telehealth services for remote prescribing and delivery.
Q: Is cefdinir suitable for children?
A: Yes—available as 125 mg/5 mL and 250 mg/5 mL suspensions with weight‑based dosing and a maximum paediatric dose of 600 mg/day.
Q: Why did my child’s stool appear red?
A: Concomitant iron supplements or iron‑fortified formulas can cause red‑coloured stools with cefdinir; this is usually non‑haemorrhagic but report any concerns to a clinician.
Q: Do I need to finish the course?
A: Yes—complete the full prescribed course to reduce the risk of recurrence and to help slow antimicrobial resistance.
Guidelines For Proper Use
What should pharmacists tell patients when dispensing omnicef?
- Confirm indication and duration, show the dosing schedule on the label and demonstrate measuring the suspension with an appropriate device.
- Advise the patient to complete the full course even if symptoms improve and to store capsules at 20–25°C and reconstituted suspension at 20–25°C, discarding it after 10 days.
- Document allergies in the patient’s e‑health record and check for iron supplements, antacids or sucralfate that may interact.
- Stewardship Advice: Remind patients that antibiotics do not treat viral infections and that third‑generation cephalosporins should be used only when appropriate.
- Cultural Safety: Offer plain‑language counselling and culturally appropriate leaflets for Aboriginal and Torres Strait Islander patients and involve local health workers where available.
Telehealth Follow‑Up: For e‑prescriptions advise patients on pharmacy selection, delivery options for rural patients and when to see their GP if symptoms persist or worsen.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5–7 days |
| Melbourne | Victoria | 5–7 days |
| Brisbane | Queensland | 5–7 days |
| Perth | Western Australia | 5–7 days |
| Adelaide | South Australia | 5–7 days |
| Hobart | Tasmania | 5–7 days |
| Darwin | Northern Territory | 5–7 days |
| Canberra | Australian Capital Territory | 5–7 days |
| Gold Coast | Queensland | 5–9 days |
| Newcastle | New South Wales | 5–9 days |
| Wollongong | New South Wales | 5–9 days |
| Geelong | Victoria | 5–9 days |
| Sunshine Coast | Queensland | 5–9 days |
| Townsville | Queensland | 5–9 days |
| Cairns | Queensland | 5–9 days |