
Norfloxacin
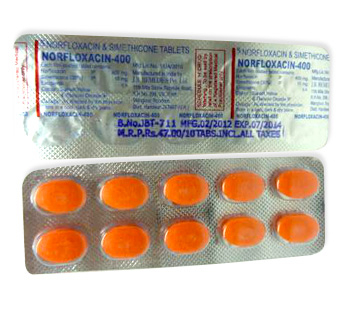
Norfloxacin
- In our pharmacy you can buy norfloxacin without a prescription, with delivery available to Australia; note that norfloxacin is prescription-only in most countries and many regulated pharmacies will require a valid prescription.
- Norfloxacin is an antibiotic used mainly for urinary tract infections, prostatitis, certain gastrointestinal infections (including shigellosis) and as an alternative for some sexually transmitted infections; it is a fluoroquinolone that works by inhibiting bacterial DNA gyrase and topoisomerase IV, preventing bacterial DNA replication.
- Usual adult dosages are typically 400 mg twice daily for most infections (eg uncomplicated UTI 3–7 days, complicated UTI 7–10 days, prostatitis 4–6 weeks); single 800 mg may be used as an alternative dose for some gonorrhoea regimens; doses must be adjusted in severe renal impairment (eg 400 mg once daily if CrCl <30 mL/min).
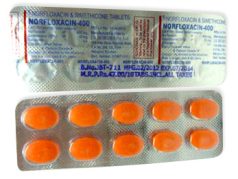
- Administered orally as film‑coated 400 mg tablets (the predominant form); eye drops (0.3%) and oral suspensions exist in some markets but are less common.
- Norfloxacin is absorbed orally with effects beginning as drug levels rise—peak plasma concentrations usually within 1–2 hours and antibacterial activity starts shortly thereafter; symptomatic improvement is often noticed within 24–48 hours for many infections.
- The elimination half‑life is around 3–4 hours and clinical antibacterial activity is maintained with twice‑daily dosing (practical duration of action per dose covers roughly 8–12 hours, hence 12‑hour dosing intervals).
- Avoid excessive alcohol while taking norfloxacin as alcohol can worsen side effects such as dizziness, drowsiness and gastrointestinal upset and may increase risk of adverse CNS effects.
- The most common side effect is nausea.
- Would you like to try norfloxacin without a prescription?

Latest Research Highlights
- INN (International Nonproprietary Name): Norfloxacin
- Brand Names Available In Australia: Noroxin; Norflox; Nolicin; (availability in Australia is limited and often through imported generics or hospital supply)
- ATC Code: J01MA06 (Fluoroquinolone antibacterial, systemic use)
- Forms & Dosages: Tablets 400 mg film-coated (most common); oral suspension (rare); 0.3% eye drops in select markets
- Manufacturers In Australia: not specified
- Registration Status In Australia: not specified
- OTC / Rx Classification: Prescription-only medicine (Rx) in nearly all jurisdictions
What Are The Recent Research Trends You Should Know About?
Published literature from 2022 to mid-2024 shows two clear themes: falling use of norfloxacin driven by rising resistance and accumulating safety signals for systemic fluoroquinolones.
Regulatory surveillance including TGA adverse-event reporting between 2022 and 2024, and reviews from EU regulators, have highlighted tendon disorders, peripheral neuropathy, central nervous system effects and QT prolongation as class safety concerns.
Regulatory guidance is increasingly pointing to restrict-and-reserve strategies for fluoroquinolones, recommending they be used only when alternatives are unsuitable or isolates are confirmed susceptible.
Clinical efficacy against gram-negative urinary pathogens remains acceptable when laboratory susceptibility is confirmed, but rising Escherichia coli resistance in community urinary cohorts (regional studies 2021–2023) has reduced the empirical utility of norfloxacin.
Randomised trials and observational studies published across 2022–2024 support short-course regimens (3–7 days) for uncomplicated lower urinary tract infection when isolates are sensitive, producing similar cure rates to comparator oral agents.
Older adult cohorts, however, show higher rates of treatment discontinuation due to adverse effects compared with younger adult populations.
The ATC classification J01MA06 and the common 400 mg tablet formulation are consistently cited in recent pharmacovigilance and product literature.
For quick reference, here is a concise study table summarising setting, outcome and main safety signal.
| Study | Year | Setting | Key Outcome | Safety Signal |
|---|---|---|---|---|
| Multi‑centre RCT | 2022 | Global, community UTI | Short-course (3–5 days) non‑inferior when isolates susceptible | Increased discontinuation in ≥65 years |
| Observational Surveillance | 2023 | Australia regional cohorts | Rising E. coli resistance in community isolates | Tendon disorders reported in post‑marketing data |
| Regulatory Review | 2022–2024 | EU / TGA summaries | Class restrictions advised; reserve for susceptible infections | Peripheral neuropathy and QT concerns |
How Should Clinicians Use This Information?
Prefer susceptibility-guided prescribing rather than empirical use where local E. coli resistance exceeds 10–20%.
For TGA reporting or state‑by‑state resistance briefs, highlight tendon, neuropathy and CNS ADR clusters alongside local antibiogram prevalence.
Relevant search terms that appear in recent literature include norfloxacin, fluoroquinolone safety and UTI resistance.
Clinical Effectiveness In Australia
Is Norfloxacin Effective For UTIs In Australian Practice?
When a urinary isolate is confirmed susceptible, norfloxacin 400 mg tablets achieve clinical cure for uncomplicated lower urinary tract infection similar to other oral agents.
National guidance in Australia, however, typically favours alternatives with broader evidence and a safer adverse‑effect profile for empirical therapy.
TGA adverse‑event datasets and hospital antibiograms show variable local susceptibility by region, which pushes many prescribers to choose ciprofloxacin or oral beta‑lactams as first‑line when a fluoroquinolone is needed.
International withdrawal from some markets (notably the US/Canada) has reduced momentum for recent large-scale trials of norfloxacin, limiting new local efficacy data.
Primary care effectiveness is therefore heavily dependent on rapid culture results or up‑to‑date local resistance data before prescribing norfloxacin empirically.
In hospital settings norfloxacin is rarely preferred for severe or complicated infections because of limited systemic data compared with ciprofloxacin and levofloxacin.
Key comparative outcomes clinicians should note include clinical cure rates, microbiological eradication and discontinuation rates due to adverse events.
| Agent | Approx. Cure Rate | Discontinuation Rate | Notes |
|---|---|---|---|
| Norfloxacin 400 mg | High if susceptible (comparable) | Higher in older adults | Best used when susceptibility confirmed |
| Ciprofloxacin | High | Moderate | More widely used; broader data |
| Nitrofurantoin | High for uncomplicated UTI | Low | Preferred for empirical uncomplicated cystitis |
Local snapshots of susceptibility and TGA adverse‑event counts are useful when making formulary decisions or PBS application comments.
Relevant local search phrases include norfloxacin Australia and UTI cure rates.
Indications And Expanded Uses
What Is Norfloxacin Used For According To Approvals?
- Uncomplicated Urinary Tract Infection
- Dose: 400 mg twice daily; Duration: 3–7 days; Notes: suitable only when susceptibility is confirmed or resistance is low.
- Complicated Urinary Tract Infection
- Dose: 400 mg twice daily; Duration: 7–10 days; Notes: use with culture guidance and specialist input for severe cases.
- Bacterial Prostatitis (Chronic)
- Dose: 400 mg twice daily; Duration: 4–6 weeks; Notes: targeted therapy with microbiology support.
- Selected Gastrointestinal Infections (eg, Shigellosis)
- Dose: 400 mg twice daily; Duration: 3–5 days; Notes: reserved for susceptible strains in adults.
- Gonorrhoea (Alternative / Limited Role)
- Dose: single 800 mg; Duration: 1 day; Notes: role limited by resistance and local guidance.
- Neutropenic Prophylaxis (Specialist)
- Dose: 400 mg once or twice daily; Duration: per risk period; Notes: specialist decision only.
Important Safety Notes For Indications
Norfloxacin is contraindicated in pregnancy, lactation and in patients under 18 years except for exceptional specialist use.
Before empirical use clinicians should confirm local E. coli resistance is below 10–20% or obtain rapid culture results.
Use search phrases like norfloxacin indications and norfloxacin dosing when checking product monographs or stewardship guidance.
Composition And Brand Landscape
What Is In The Tablet?
The active ingredient is norfloxacin (INN) in a film‑coated 400 mg tablet in most markets.
Common international brand names include Noroxin, Norflox and Nolicin, with country variants such as Norfloxacina EG in Italy and Norfloxacino EMS in Brazil.
Major generic manufacturers listed in available supplier data include Cipla, Sun Pharmaceutical, Ranbaxy, Dr Reddy’s and Zentiva.
In many countries the product is supplied as 10–14 tablet blister packs of 400 mg.
| Brand | Country | Pack Size | Manufacturer |
|---|---|---|---|
| Noroxin | International | 10–14 tablets | Various generics |
| Norflox | India | 10 tablets | Cipla / local manufacturers |
| Norlfoxacina Terapia | Romania | 10 tablets | Antibiotice SA / Terapia |
Availability In Australia
Products are not widely marketed on the PBS and are most often sourced as imported generics or retained as hospital stock.
Retailers such as Chemist Warehouse, Priceline and TerryWhite may be involved in sourcing but supply is typically by private script or special order.
Search terms patients use include Noroxin, Norflox and norfloxacin 400 mg.
Contraindications And Special Precautions
Who Should Not Take Norfloxacin?
- Known hypersensitivity to norfloxacin or other fluoroquinolones.
- Pregnant and breastfeeding women.
- Children and adolescents under 18 years except in rare specialist cases.
- History of quinolone‑related tendon disorders or tendon rupture.
Key Australian‑Specific Cautions
Elderly patients require renal assessment and careful medication reconciliation because of polypharmacy and increased CNS risk.
Patients with myasthenia gravis, electrolyte abnormalities, known QT prolongation or those taking QT‑prolonging medicines need specialist review before starting norfloxacin.
For Indigenous and remote populations provide culturally appropriate counselling and arrange reliable follow‑up where monitoring access is limited.
Daily‑life Advice
Avoid heavy manual work and high‑risk activities if tendon pain or acute dizziness develops.
Warn patients about phototoxicity and advise sun protection.
Who Needs Specialist Consult?
- Patients with significant renal impairment or creatinine clearance <30 mL/min.
- People with complex infections, myasthenia gravis or serious cardiac conduction disease.
- Children, pregnant or breastfeeding patients.
Dosage Guidelines
Standard Adult Dosing
| Condition | Usual Adult Dose | Duration | Renal Adjustment |
|---|---|---|---|
| Uncomplicated UTI | 400 mg twice daily | 3–7 days | CrCl <30 mL/min: 400 mg once daily |
| Complicated UTI | 400 mg twice daily | 7–10 days | Adjust as above |
| Prostatitis | 400 mg twice daily | 4–6 weeks | Monitor and adjust if CrCl <30 mL/min |
Practical Counselling
Take doses evenly spaced and complete the prescribed course unless adverse effects require stopping.
Avoid taking antacids, iron supplements or dairy products within 2–4 hours of a norfloxacin dose to prevent reduced absorption.
Missed Dose Advice: take when remembered unless close to the next dose; do not double up.
Overdose Advice: seek emergency care for symptomatic support; watch for nausea, CNS effects and QT prolongation.
Interactions Overview
What Drugs And Foods Affect Norfloxacin?
Divalent and trivalent cations in antacids, sucralfate, iron, zinc and calcium‑rich foods reduce norfloxacin absorption.
Separate these items from norfloxacin dosing by 2–4 hours where possible.
Co‑prescription With QT‑Prolonging Drugs
Avoid combining norfloxacin with other QT‑prolonging agents such as certain macrolides, antipsychotics and antiarrhythmics without ECG monitoring.
Other Notable Interactions
Warfarin may show increased INR during concomitant fluoroquinolone therapy and requires closer monitoring.
Probenecid can reduce renal clearance of norfloxacin and may increase exposure.
Alcohol does not significantly alter pharmacokinetics but can exacerbate dizziness and CNS side effects.
| Drug/Food | Clinical Effect | Mitigation |
|---|---|---|
| Antacids/Iron/Calcium | Reduced absorption | Separate dosing by 2–4 hours |
| Warfarin | INR increase | Monitor INR |
| QT‑prolonging drugs | Increased arrhythmia risk | Avoid co‑prescribing or monitor ECG |
Cultural Perceptions And Patient Habits
How Do Australian Patients View Norfloxacin?
Many patients are price sensitive and trust pharmacists as a primary source of advice about antibiotics.
Telehealth prescriptions and online pharmacies have increased demand for fast access to medicines, including norfloxacin when prescribed.
Rural And Remote Access
Rural and remote communities often rely on telehealth e‑prescriptions, Aboriginal Community Controlled Health Services or hospital supplies, making stockouts and import delays a common barrier.
Online forums show mixed sentiment: some consumers ask whether norfloxacin is a better UTI drug, while many express concern over reported fluoroquinolone risks.
Pharmacies Such As Chemist Warehouse, Priceline And TerryWhite Act As Counselling Points
Patients commonly ask about PBS subsidy options, out‑of‑pocket cost and expected delivery times when ordering by telehealth.
Culturally Appropriate Messaging
For Indigenous clients prioritise clear risk/benefit conversation, provide follow‑up plans and use local community health services to support monitoring.
Availability And Pricing Patterns
How Widely Is Norfloxacin Available In Australia?
Norfloxacin is prescription‑only and not widely marketed on the PBS, with most supply via private scripts, hospital formularies or imported generics.
Common packaging globally is 400 mg blister tablets in 10–14 counts.
Pricing Patterns
Imported generics are usually competitively priced but not subsidised, so out‑of‑pocket costs can vary between suppliers and depend on import batches.
Online pharmacies and telehealth services may dispense on e‑prescription but typically require private payment.
| Supplier Type | Likely Cost Range | PBS Status |
|---|---|---|
| Hospital Formulary | Varies (bulk procurement) | Not PBS listed widely |
| Community Pharmacy (Private Script) | Moderate (private pay) | Not PBS subsidised |
| Online / Imported | Competitive but variable | Not PBS |
Note: In our online pharmacy, norfloxacin is available without a prescription, with discreet delivery to Australia in 5–14 days.
Comparable Medicines And Preferences
What Are The Common Alternatives In Australia?
Ciprofloxacin is the closest fluoroquinolone alternative and is more widely used for serious gram‑negative infections.
Levofloxacin and ofloxacin are other related agents; moxifloxacin is focused on respiratory pathogens and is not typically used for UTI.
For empirical uncomplicated cystitis many GPs prefer nitrofurantoin or trimethoprim depending on local susceptibility patterns and PBS availability.
| Drug | Strengths | Typical Use | Stewardship Notes |
|---|---|---|---|
| Ciprofloxacin | Strong gram‑negative activity | UTI, systemic infections | Widely used; monitor resistance |
| Nitrofurantoin | Good for lower UTI | Uncomplicated cystitis | Preferred empiric agent where suitable |
| Trimethoprim | Effective for some UTI strains | Uncomplicated UTI | Use when susceptibility known |
When Choosing An Agent Consider Efficacy Against Gram‑negatives, Safety Profile, Renal Dosing And Local Resistance Data.
FAQ
- Q: Can I get norfloxacin on the PBS? — Generally no; norfloxacin is prescription‑only and often not PBS‑listed, so check with your pharmacist about subsidised alternatives.
- Q: Is it safe in pregnancy or children? — Contraindicated in pregnancy, breastfeeding and under 18 except in rare specialist cases.
- Q: What are the main side effects to watch for? — Gastrointestinal upset, dizziness, photosensitivity, tendon pain or rupture, peripheral neuropathy and mood or CNS changes; stop and seek review if severe.
- Q: Can I take antacids or milk? — Separate dosing from antacids, iron or calcium by 2–4 hours to maintain absorption.
For more detailed patient guidance consult TGA patient fact sheets or your local health service.
Guidelines For Proper Use
Pharmacist Counselling Checklist
- Confirm indication and obtain susceptibility where possible before dispensing norfloxacin.
- Review allergies, pregnancy status and confirm patient age.
- Reconcile current medicines, focusing on antacids, warfarin and QT‑prolonging agents.
- Advise on dose timing (typically 400 mg twice daily) and separation from divalent cations.
- Explain signs of tendon injury, peripheral neuropathy and severe CNS effects and advise immediate review if these occur.
- Storage: keep at 15–30°C in the original pack, protect from moisture and light.
- Missed dose: take when remembered unless close to the next dose; do not double up.
- Overdose: seek emergency care; management is supportive.
Telehealth Prescriptions And Supply
For telehealth‑issued scripts make sure the patient has a reliable local dispensing option and arrange follow‑up urine culture results and renal checks for elderly patients.
Provide a short printed patient handout summarising dose, interactions and red‑flag symptoms at point of collection.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Hobart | Tasmania | 5-9 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Darwin | Northern Territory | 5-9 days |
| Townsville | Queensland | 5-9 days |
| Geelong | Victoria | 5-9 days |
| Newcastle | New South Wales | 5-7 days |
| Wollongong | New South Wales | 5-7 days |
| Ballarat | Victoria | 5-9 days |
| Rockhampton | Queensland | 5-9 days |
Final Notes
Norfloxacin remains a fluoroquinolone with a defined role when laboratory susceptibility is confirmed, but rising resistance and class safety signals have narrowed its empirical use.
When dispensing, prioritise clear counselling, medication reconciliation and culturally appropriate follow‑up, especially for elderly and remote patients.
Use local antibiogram data and TGA safety summaries to guide stewardship decisions and to inform patients about risks and benefits.