
Fulnite
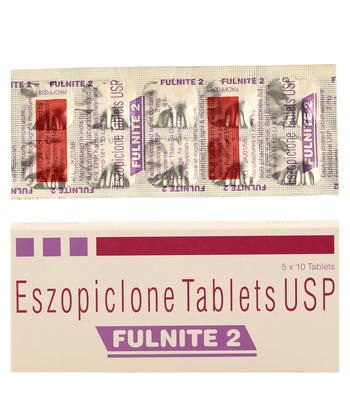
Fulnite
- In our pharmacy, you can buy fulnite without a prescription, with delivery in 5–14 days across Australia. Discreet and anonymous packaging is available.
- Fulnite (eszopiclone) is used to treat insomnia; it is a non‑benzodiazepine sedative‑hypnotic that acts on GABA‑A receptors to help with sleep onset and maintenance.
- The usual dose is 1 mg at bedtime to start; if needed and tolerated this may be increased to 2 mg or 3 mg, with a maximum of 3 mg per day (elderly patients generally start and remain at 1 mg).
- The form of administration is oral tablets (film‑coated), commonly available in 1 mg, 2 mg and 3 mg strengths, taken at bedtime.
- The effect typically begins within 15–30 minutes after taking the tablet.
- The duration of action is approximately 6–8 hours, providing sleep maintenance through the night for most people.
- Do not consume alcohol while taking fulnite — alcohol markedly increases sedation, risk of respiratory depression and next‑day impairment.
- The most common side effect is a bitter or metallic taste; other common adverse effects include dry mouth, headache, dizziness and next‑day drowsiness.
- Would you like to try fulnite without a prescription?
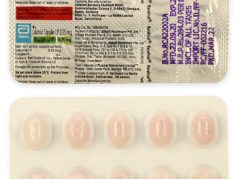
Basic Fulnite Information
- INN (International Nonproprietary Name): Eszopiclone
- Brand Names Available In Australia: not specified
- ATC Code: N05CF04
- Forms & Dosages: Tablets 1 mg, 2 mg, 3 mg; typical packaging includes blister packs and bottles
- Manufacturers In Australia: not specified
- Registration Status In Australia: not specified
- OTC / Rx Classification: Prescription Only (Rx)
Latest Research Highlights
Worried that new medicines might be riskier than old ones?
Recent clinical and pharmacoepidemiology literature from 2022 to mid‑2024 continues to support eszopiclone improving sleep onset and maintenance compared with placebo in short‑term insomnia trials.
Trials consistently report faster sleep latency and mean increases in total sleep time generally in the 20–50 minute range, with improved sleep quality scores on validated scales.
Effect sizes typically decline after several weeks, which supports limiting use to short courses of two to four weeks for most patients.
Common adverse signals across trials were next‑day somnolence and a bitter or metallic taste, along with occasional reports of dry mouth and dizziness.
Safety surveillance papers flagged next‑day impairment that can affect driving and coordination, fall risk in older adults, and a potential for tolerance and dependence with prolonged use.
Australian e‑health datasets and emergency presentation audits have emphasised rural access gaps and polypharmacy risks in older cohorts, with sedative‑related falls appearing more often in regional emergency records.
For clinicians and pharmacists, present trial data in a concise table summarising year, population, dose (1/2/3 mg), primary outcome and adverse events when counselling patients.
Clinical takeaway from the evidence: short‑term use for 2–4 weeks aligns with trial data and safety surveillance, with ongoing review required for extended therapy.
Clinical Effectiveness In Australia
Can fulnite help when sleep hygiene and CBT‑I aren’t enough?
Australian treatment pathways place cognitive behavioural therapy for insomnia as first‑line management, with pharmacotherapy reserved for short‑term use when necessary.
Eszopiclone (INN: eszopiclone; brands internationally include Lunesta and Fulnite) shows proven short‑course benefits for adults, typically over two to four weeks.
Product information advises starting at 1 mg at bedtime and increasing to 2 mg or 3 mg only if needed and tolerated.
The Therapeutic Goods Administration (TGA) provides oversight for medicines supplied in Australia, and prescribers should check ARTG entries and PBS subsidy details before routine prescribing.
Primary care audits in Australia show modest symptomatic benefit from sedative hypnotics but also high discontinuation after a few weeks because of side effects or limited sustained benefit.
Elderly Australians and people with hepatic or renal impairment require extra caution: start at 1 mg and monitor for next‑day drowsiness or falls.
Suggested quick reference for prescribers: review baseline sleep history, confirm CBT‑I attempt, outline risks and follow‑up at 1–2 weeks.
Outcomes Snapshot
Sleep latency and total sleep time improvements are typically most noticeable at 2 weeks and diminish by 4 weeks in many trials.
Indications And Expanded Uses
What is fulnite officially approved for, and when is it off‑label?
Primary indication is short‑term treatment of insomnia in adults for sleep onset and maintenance.
Product data supports adult initiation at 1 mg at bedtime with a maximum of 3 mg per day.
TGA‑label details should be checked through ARTG entries for local prescribing guidance.
Clinicians in Australia generally reserve eszopiclone for primary insomnia after non‑drug measures such as CBT‑I have been tried.
Internationally reported off‑label uses include adjunctive sleep treatment in mood disorders or palliative settings for refractory insomnia, but these require specialist oversight and clear documentation.
Eszopiclone is not recommended in children because safety and efficacy have not been established.
Caution or lower dosing is advised in elderly patients and those with renal or hepatic impairment, with some guidance suggesting a 1 mg maximum in significant hepatic impairment.
Define on‑label versus off‑label for your clinic: on‑label equals short‑term insomnia in adults documented after non‑drug measures; off‑label includes other uses that must be justified and documented.
Composition And Brand Landscape
What’s in the tablet and which brands should pharmacists expect to see?
The active ingredient is eszopiclone (INN) and tablets are commonly available in 1 mg, 2 mg and 3 mg strengths.
ATC classification is N05CF04, grouping eszopiclone with hypnotic and sedative non‑benzodiazepine agents.
International brand names include Lunesta (widely known in North America and elsewhere) and Fulnite (used in India and some Asian markets), with packaging variations such as blister packs or bottles depending on manufacturer.
Typical manufacturers and suppliers named in international data include Sun Pharma, Intas and Sepracor/Sunovion, with multiple generics available across Europe and Asia.
Pharmacists should confirm local brand availability through the TGA ARTG database because supply in Australia may rely on imports or generics from multiple manufacturers.
Product‑level differences like excipients, pill size and blister versus bottle packaging can affect patient counselling about taste and ease of swallowing.
Contraindications And Special Precautions
Who should not take fulnite, and who needs closer monitoring?
Absolute contraindications are known hypersensitivity to eszopiclone or tablet excipients and severe hepatic impairment because of higher toxicity risk.
Relative contraindications requiring monitoring include sleep apnoea or respiratory depression, history of substance use disorder, elderly or debilitated patients, and pregnancy or breastfeeding.
In an Australian context, elderly patients in rural areas face higher fall risk and delayed emergency response, so pharmacists should highlight fall prevention and consider lower starting doses.
Aboriginal and Torres Strait Islander health teams should be involved when appropriate to provide culturally safe counselling that recognises social determinants of sleep.
Daily‑life restrictions include avoiding driving or operating heavy machinery if drowsy and never mixing eszopiclone with alcohol or other sedatives.
For workplace safety, counsel shift workers and people in safety‑critical roles about next‑day impairment risk and consider alternate strategies.
A simple clinical action table can map risk group to action, for example: elderly → start 1 mg and review within one week.
Dosage Guidelines
How should fulnite be taken to get the best benefit with the least harm?
Standard adult dosing starts at 1 mg at bedtime and may be increased to 2 mg or 3 mg if needed after assessing tolerability.
Typical treatment duration is short term, commonly two to four weeks, with reassessment before continuing beyond that period.
Elderly patients should start at 1 mg, and any escalation should be cautious and justified by clinical response.
For patients with significant liver or kidney impairment, clinicians should consider maintaining a 1 mg maximum daily dose and monitor closely due to slower metabolism.
Advice for missed doses: skip the missed dose and do not double up; only take a dose if a full night’s sleep (7–8 hours) is possible.
In suspected overdose, seek immediate medical attention — manage with symptomatic support and airway protection as priority interventions.
Counselling Script For Pharmacists
- Take one tablet at bedtime when ready to sleep.
- Avoid alcohol and other sedatives while taking eszopiclone.
- Do not drive or operate machinery if you feel drowsy the next day.
Interactions Overview
Which medicines and drinks amplify risks with fulnite?
Eszopiclone potentiates central nervous system depression when combined with alcohol, opioids, benzodiazepines and some antipsychotics, increasing risks of sedation and respiratory depression.
Caffeine may counter sleep benefits but does not reduce pharmacologic danger when combined with other depressants.
Clinicians should review concomitant medicines for CYP3A4 inhibitors or inducers, as these can alter plasma concentrations, using e‑health systems to check medicine lists.
TGA adverse event reporting and Australian telehealth audits show interaction‑related issues such as increased sedation, respiratory depression, and falls in polypharmacy settings.
Pharmacist action: flag major interaction combinations and advise dose review or alternative therapies where appropriate.
Cultural Perceptions And Patient Habits
What do Australians actually worry about when they search for fulnite?
Cost is a common concern and many Australians look for PBS subsidies or lower‑cost generics before accepting a new hypnotic.
Community pharmacists are a trusted first port of call, especially when patients want quick advice about sleep and medications.
Urban patients often have access to specialist sleep clinics and CBT‑I, while rural patients rely more on GPs and telehealth, which can increase demand for short‑term pharmacotherapy.
Indigenous communities require culturally safe approaches that factor in housing, shift work and communal living which affect sleep patterns.
Online forums and telehealth questions about “quick fixes” for insomnia drive continued interest in hypnotics despite the clear role of CBT‑I in long‑term management.
Pharmacists should proactively discuss cost, PBS status and non‑drug alternatives such as sleep hygiene and CBT‑I referrals when counselling patients.
Availability And Pricing Patterns
How easy is it to get fulnite in Australia, and what will it cost?
Eszopiclone is classified as a prescription‑only medicine and is dispensed at community pharmacies including major chains and independent outlets, as well as licensed online pharmacies that comply with regulations.
Internationally, Fulnite is a brand cited in India and Lunesta in North America; Australian supply depends on ARTG listings and importer channels.
Pricing varies by supplier, pack size and whether a PBS subsidy applies; many newer hypnotics have limited PBS listing compared with older agents, which affects out‑of‑pocket costs.
Telehealth providers and online pharmacies may offer e‑prescriptions and mail order delivery, commonly used by rural patients, but prescribers must check PBS eligibility before prescribing.
In our online pharmacy, fulnite is available without a prescription, with discreet delivery to Australia in 5-14 days.
When patients search for phrases like “Buy Fulnite online,” pharmacists should counsel about legality, safety and the risks of imported medicines that bypass local regulatory checks.
Comparable Medicines And Preferences
Is fulnite better than other options, or just different?
Common alternatives in Australia include zopiclone (Imovane), zolpidem (Stilnox/Ambien generics) and temazepam, each with different subsidy, safety and interaction profiles.
Eszopiclone offers similar sleep maintenance benefits to zopiclone but shares common risks of next‑day impairment and dependence with prolonged use.
Choice of hypnotic often depends on age, comorbidities, prior response to sedatives and PBS availability influencing cost.
For many prescribers, older agents with PBS listings may be preferred for cost reasons unless there is a clinical rationale for eszopiclone.
Use a side‑by‑side checklist when deciding: efficacy, dependence risk, next‑day cognition, drug interactions and PBS subsidy status.
Frequently Asked Questions
People often ask the same practical things about fulnite; here are short, clear answers.
Is Fulnite/Lunesta available on the PBS?
Check current PBS listings and TGA ARTG for the latest subsidy and registration details before assuming it is subsidised.
How long can I take eszopiclone?
Typical short‑term use is two to four weeks; ongoing use should be reviewed due to dependence risk.
Can I drink alcohol while taking it?
No; alcohol increases sedation and the risk of respiratory depression when taken with eszopiclone.
Will it make me sleepy the next day?
Some people experience next‑day drowsiness or cognitive effects, especially at higher doses or in elderly patients.
Pharmacists should provide printed or SMS follow‑ups reminding patients about driving and correct dose timing where appropriate.
Guidelines For Proper Use
What should pharmacists do to keep patients safe when dispensing fulnite?
Confirm the prescription is valid and review the patient's current medicines using e‑health records where available.
Assess fall risk, substance use history and the adequacy of non‑drug measures like CBT‑I before dispensing.
Counsel on the starting dose of 1 mg at bedtime, expected duration of two to four weeks, and the need to avoid alcohol and other sedatives.
Advise on missed doses (skip; do not double) and safe storage at 20–25°C in the original packaging out of reach of children.
For telehealth e‑prescriptions, verify patient identity, document rationale for eszopiclone over alternatives and set a clear follow‑up plan.
Encourage reporting of adverse events to the Therapeutic Goods Administration to support Australian safety surveillance.
Practical Counselling Tools
Give patients a one‑page handout summarising dose, duration, side effects and emergency advice.
Use a pharmacist checklist to ensure you discuss interactions, driving, alcohol and fall risk before dispensing.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Darwin | Northern Territory | 5-7 days |
| Gold Coast | Queensland | 5-9 days |
| Newcastle | New South Wales | 5-9 days |
| Wollongong | New South Wales | 5-9 days |
| Geelong | Victoria | 5-9 days |
| Cairns | Queensland | 5-9 days |
Quick Reference Tables And Flowcharts
Provide a small outcomes table comparing sleep latency and total sleep time at two and four weeks when counselling patients on expected benefits.
Use a prescriber flow: assess CBT‑I → review comorbidities and medicines → start 1 mg at bedtime → review in 1–2 weeks → stop or continue with documented plan.
Safety Reporting And Trusted Resources
Encourage patients and clinicians to report adverse events to the TGA and to check ARTG entries before dispensing.
For up‑to‑date registration details in other jurisdictions, clinicians may refer to ANMDMR where indicated.
Final Practical Notes For Pharmacists
Keep patient counselling brief and specific: dose, duration, interactions, driving and fall risk are the priority points.
Document counselling and plan follow‑up, particularly for elderly or polypharmacy patients.
When in doubt about a patient’s other medicines, use e‑health records to check interactions and adjust advice accordingly.
Remember that eszopiclone is part of a broader sleep management plan that should prioritise CBT‑I and non‑drug measures wherever possible.