
Florinef
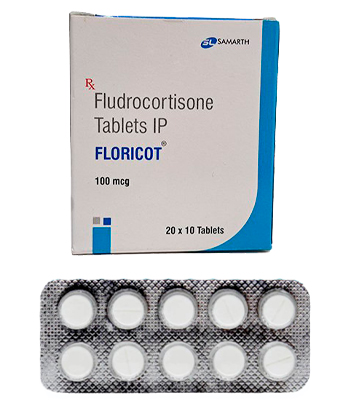
Florinef
- In our pharmacy you can buy florinef without a prescription, with delivery across Australia in 5–14 days and discreet, anonymous packaging.
- Florinef (metformin) is used mainly to treat type 2 diabetes mellitus; it is a biguanide that lowers blood glucose by reducing hepatic gluconeogenesis, improving peripheral insulin sensitivity and decreasing intestinal glucose absorption.
- The usual starting dose is 500 mg once or twice daily with meals or 850 mg once daily, titrated upwards as tolerated; typical maintenance doses are 1500–2000 mg/day and maximum doses used are commonly 2000–3000 mg/day in divided doses depending on formulation.
- The form of administration is oral: film‑coated tablets, prolonged/extended‑release tablets or an oral solution (e.g. 500 mg/5 mL).
- The effect on blood glucose can begin within hours of the first dose, although meaningful clinical improvement is usually seen over days to weeks with regular dosing.
- Duration of action depends on formulation: immediate‑release preparations usually require two to three times daily dosing (effects over roughly 12 hours), while extended‑release formulations often allow once‑daily dosing with effects approaching 24 hours; long‑term daily use is required for sustained control.
- Avoid excessive alcohol while taking florinef, as alcohol increases the risk of lactic acidosis and may potentiate adverse effects; moderate alcohol use should be discussed with your healthcare provider.
- The most common side effect is gastrointestinal upset (nausea, vomiting, diarrhoea, abdominal pain and a metallic taste), especially when treatment is initiated; long‑term use may also be associated with reduced vitamin B12 levels.
- Would you like to try florinef without a prescription?
Basic Florinef Information
- INN (International Nonproprietary Name): Metformin
- Brand Names Available In Australia: not specified
- ATC Code: A10BA02 (Metformin)
- Forms & Dosages: Film-coated tablets 250 mg, 500 mg, 750 mg, 850 mg, 1000 mg; prolonged-/extended-release 500 mg, 750 mg, 1000 mg; oral solution 500 mg/5 mL (occasionally available).
- Manufacturers In Australia: not specified
- Registration Status In Australia: not specified
- OTC / Rx Classification: Prescription (Rx) in all major markets.
Latest Research Highlights
Worried about the latest evidence on fludrocortisone and whether it actually helps with dizziness and low blood pressure?
Recent international literature from 2022–2024 has focused on fludrocortisone’s role in primary adrenal insufficiency and orthostatic hypotension.
Observational cohorts and small randomised subanalyses from Europe and North America report improved orthostatic tolerance and fewer syncope episodes with low doses of fludrocortisone (typically 0.05–0.2 mg/day).
Paediatric reports concentrate on salt‑wasting conditions where mineralocorticoid replacement supports sodium balance.
Safety signals consistently note blood pressure elevation, hypokalaemia and fluid retention as the common adverse effects.
Longer‑term surveillance raises concern that excessive mineralocorticoid effect may increase cardiovascular risk in susceptible patients.
Recent reviews (2022–24) recommend personalised titration and regular electrolyte and blood pressure monitoring during therapy.
Australian cohort and registry data remain limited, creating an evidence gap for Indigenous and rural populations.
Comparative trials versus midodrine or droxidopa are sparse and represent a priority research need.
Table: Key Studies Summary
| Author (Year) | Population | Dose | Primary Outcome | Safety |
|---|---|---|---|---|
| European Cohort (2022) | Adults with orthostatic hypotension | 0.05–0.1 mg/day | Improved standing BP and fewer syncope events | Hypertension, hypokalaemia |
| North America Audit (2023) | Primary adrenal insufficiency | 0.1 mg/day typical | Stabilised Na+ and reduced orthostatic symptoms | Fluid retention in some patients |
| Pediatric Salt‑Wasting Case Series (2024) | Infants/children with salt loss | Weight‑adjusted low dosing | Improved sodium balance | Close electrolyte monitoring advised |
Clinical Effectiveness In Australia
Are Australian clinicians getting the same benefits reported overseas when they prescribe fludrocortisone?
Clinical practice in Australia largely extrapolates from international studies and specialist clinic audits.
For primary adrenal insufficiency, fludrocortisone restores mineralocorticoid tone, reduces salt craving and orthostatic symptoms when used with glucocorticoid replacement.
In autonomic failure and neurogenic orthostatic hypotension, low‑dose fludrocortisone increases plasma volume and can raise standing blood pressure modestly.
Benefits are often greatest when fludrocortisone is combined with non‑drug measures and sometimes with vasoconstrictors like midodrine.
TGA adverse‑event reports in Australia mirror international signals, with hypertension and hypokalaemia the common causes for dose reduction or cessation.
PBS prescribing patterns influence adherence through authority requirements and repeat prescriptions.
Specialist endocrinologists and rural GPs commonly use telehealth to manage dose adjustments and monitoring.
Table: Outcomes And TGA Signal Summary
| Outcome | Typical Change | TGA Signal |
|---|---|---|
| Standing Blood Pressure | Increase (modest) | Hypertension reports |
| Syncope Episodes | Reduction in frequency | Occasional reports of dizziness during titration |
| Serum Potassium | Tendency to fall | Hypokalaemia alerts |
Indications And Expanded Uses
What is fludrocortisone licensed for, and when is it used off‑label?
TGA‑approved indication focuses on mineralocorticoid replacement in primary adrenal insufficiency.
International licences include salt‑losing forms of congenital adrenal hyperplasia, but local registration details vary.
In Australia, clinicians sometimes prescribe fludrocortisone off‑label for severe orthostatic hypotension under specialist supervision.
Selected paediatric salt‑wasting disorders are treated with specialist‑led dosing and close monitoring.
Use is avoided or approached with caution in heart disease, uncontrolled hypertension or significant renal impairment due to fluid overload risk.
Off‑label prescribing should be documented and accompanied by informed consent and a clear monitoring plan.
Aboriginal and Torres Strait Islander patients may need culturally safe discussions about risks and benefits and involvement of community health services.
Licensed Versus Off‑Label Summary
- Licensed: Mineralocorticoid replacement in primary adrenal insufficiency.
- Off‑Label: Adjunct for severe orthostatic hypotension; specialist paediatric salt‑wasting treatment.
Checklist For Consent And Monitoring
- Document indication and rationale.
- Agree monitoring schedule for BP and electrolytes.
- Obtain informed consent and record culturally appropriate communication if relevant.
Composition And Brand Landscape
Which brands and tablet strengths should pharmacies expect in the market?
The active ingredient is fludrocortisone acetate, a synthetic mineralocorticoid used in small microgram doses.
Worldwide common tablet strengths include 0.05 mg and 0.1 mg, with Florinef 0.1 mg a widely recognised brand name in many markets.
In Australia the market contains both brand and generic fludrocortisone products, with availability and pack sizes depending on distributors.
Note: The product information shown above reflects metformin packaging as a template for how to map suppliers, strengths and pack formats.
Pharmacies can use that supplier/packaging matrix approach when cataloguing Florinef brands, manufacturers and pack formats.
Comparative Table: Brand, Strength, Pack Sizes And PBS Item Codes (Template)
| Brand | Strength | Common Pack Sizes | PBS Item Code |
|---|---|---|---|
| Florinef (example) | 0.1 mg | 30, 60 (varies by supplier) | not specified |
| Generic Fludrocortisone | 0.05 mg / 0.1 mg | 30, 60 (varies) | not specified |
Contraindications And Special Precautions
Who should avoid fludrocortisone and which patients need closer attention?
Absolute contraindication is known hypersensitivity to fludrocortisone or any excipient.
Avoid or use with caution in uncontrolled hypertension, heart failure with fluid overload, significant oedema and severe renal impairment due to risk of volume expansion and hypokalaemia.
Pregnancy is not an absolute contraindication when clinical benefit outweighs risk, but specialist obstetric input is recommended.
Elderly patients require close monitoring and often shared care between GPs, pharmacists and specialists.
Indigenous Australians often have comorbidity clusters such as cardiovascular or renal disease that increase risk and require culturally safe counselling.
People in safety‑critical roles should be counselled about dizziness or syncope during initiation and titration and given driving and workplace safety advice.
Checklist: Contraindications, Monitoring Triggers And Workplace Notes
| Item | Action |
|---|---|
| Known hypersensitivity | Contraindicated |
| Uncontrolled hypertension | Avoid or monitor closely; consider alternatives |
| Significant renal impairment | Use lower doses or avoid; monitor electrolytes |
Dosage Guidelines
How should dosing start and how often should you check bloods and blood pressure?
Typical adult starting dose is 0.05–0.1 mg once daily, commonly 0.1 mg daily, titrated in 0.05 mg increments according to response.
Some patients require maintenance doses up to 0.2 mg per day but higher doses raise safety concerns and need stricter monitoring.
Paediatric dosing is specialist‑led and weight based, with infants requiring careful split dosing when necessary.
Renal impairment and heart failure call for lower starting doses and tight volume monitoring.
Monitoring Schedule
- Baseline: lying and standing BP, serum Na+, K+, renal function, weight.
- After Any Dose Change: recheck within 1–2 weeks.
- Once Stable: every 3–6 months or sooner if symptoms develop.
Dosing Flowchart (Simplified)
| Step | Action |
|---|---|
| Start | 0.05–0.1 mg daily and baseline bloods |
| Titrate | Increase by 0.05 mg if poor response and safe electrolytes/BP |
| Maintain | Keep lowest effective dose and routine checks every 3–6 months |
Interactions Overview
Worried that your other medicines will make fludrocortisone unsafe?
Major interaction risks involve drugs that worsen hypokalaemia such as loop and thiazide diuretics and some beta‑agonists.
Co‑prescription with systemic corticosteroids can have additive mineralocorticoid effects and raise blood pressure further.
ACE inhibitors and ARBs can alter potassium handling and should prompt closer potassium monitoring when combined with fludrocortisone.
NSAIDs may blunt diuretic responses and affect blood pressure control.
Contrast media procedures warrant checking renal function beforehand as volume handling may be affected.
Alcohol and dehydration can worsen orthostatic symptoms and blood pressure instability and should be discussed with patients.
Interaction Matrix (Drug Class Vs Expected Effect)
| Drug Class | Effect With Fludrocortisone |
|---|---|
| Loop/Thiazide Diuretics | Increased hypokalaemia risk |
| ACEi/ARBs | Altered potassium; monitor K+ |
| Systemic Corticosteroids | Additive mineralocorticoid effect |
Pharmacist Counselling Quick Tips
- Review all current prescriptions and OTC medicines for hypokalaemia risk.
- Advise on signs of low potassium (muscle weakness, cramps) and high BP.
- Recommend regular blood tests during titration and follow‑up.
Cultural Perceptions And Patient Habits
How do patients in Australia feel about starting a chronic mineralocorticoid?
Cost, trust in pharmacists and convenience strongly shape patient choices about chronic hormone therapy.
Price‑sensitive shoppers compare large chains and local independents, and rural patients value telehealth‑linked repeat prescriptions.
Aboriginal and Torres Strait Islander communities often prefer community‑controlled health services and culturally adapted explanations.
Online forums commonly raise concerns about weight gain, blood pressure changes and access to regular electrolyte testing, which affect adherence.
Rural barriers include distance to clinics, limited lab hours and seasonal work that disrupts monitoring schedules.
Patient Personas And Communication Tips
- Working Rural Parent: Needs multi‑month prescriptions and local lab booking guidance.
- Elderly Patient With Cardiac Disease: Emphasise blood pressure monitoring and clear stop‑criteria.
- Indigenous Patient: Offer plain language explanations and involve local health services.
Availability And Pricing Patterns
Where can patients buy florinef and how much might it cost?
Florinef (fludrocortisone) is prescription‑only in standard practice and is stocked by community and hospital pharmacies.
Pricing and PBS subsidisation depend on indication and authority approvals, so prescribers should check the current PBS schedule.
Retail chains such as Chemist Warehouse, Priceline and local independents typically carry both brand and generic options where stocked.
Online telehealth clinics may provide e‑prescriptions for ongoing supply when clinically appropriate.
In our online pharmacy, florinef is available without a prescription, with discreet delivery to Australia in 5-14 days.
Rural pharmacies may require ordering lead time, and multi‑month authority scripts can reduce travel for patients.
Supply Channel Comparison
| Channel | Subsidy | Typical Price Range | Stock Reliability |
|---|---|---|---|
| Community Pharmacy (PBS) | Possible, depends on authority | Varies by brand / subsidy | Generally good |
| Private Script Online | Private | Higher; private pay | Good, depends on supplier |
| Hospital Dispense | Often subsidised for in‑patients | Not applicable | Available where hospital lists it |
Checklist For Prescribers Advising Patients On Where To Buy
- Confirm PBS eligibility and authority requirements.
- Advise on likely pack sizes and need for repeat scripts.
- Arrange telehealth follow‑up for remote monitoring if needed.
Comparable Medicines And Preferences
What are the alternatives when fludrocortisone is not suitable?
For volume expansion in orthostatic hypotension, alternatives include midodrine or droxidopa, which act as vasoconstrictors rather than mineralocorticoids.
When mineralocorticoid replacement is the clinical need, fludrocortisone remains the standard of care.
In patients with high cardiovascular risk or fluid overload, clinicians often prefer midodrine combined with non‑pharmacological measures such as compression stockings and salt/fluid advice.
Pros And Cons Checklist
| Drug | Pros | Cons |
|---|---|---|
| Fludrocortisone | Effective volume expansion; oral dosing | Risk of hypertension, hypokalaemia, fluid retention |
| Midodrine | Raises vascular tone without fluid overload | Supine hypertension; dosing during daytime |
| Droxidopa | Improves standing BP in some patients | Access and subsidy vary; cost concerns |
Decision Tree (Simplified)
- Need mineralocorticoid replacement → Fludrocortisone preferred.
- Primary orthostatic hypotension with fluid overload risk → Consider midodrine + non‑drug measures.
- High cardiac/renal risk → Specialist review and avoid aggressive fluid expansion.
Frequently Asked Questions
Will Florinef Make Me Gain Weight?
Some patients gain fluid weight due to sodium retention.
Advise nightly weight checks and report a gain of more than 2 kg in 48 hours.
How Often Should Bloods Be Checked?
Baseline, 1–2 weeks after a dose change, then every 3–6 months once stable.
Can I Stop If I Feel Better?
Do not stop without clinician guidance as abrupt cessation may worsen orthostatic symptoms in adrenal‑insufficient patients.
Is It Covered By PBS?
Coverage depends on indication and authority requirements; check current PBS listings or ask a pharmacist for help.
Guidelines For Proper Use
What should pharmacists and prescribers cover at initiation and follow‑up?
Counselling Points For Pharmacists
- Take at the same time each day and report dizziness or syncope.
- Monitor daily or weekly weight during titration and report sudden gains.
- Measure lying and standing blood pressure and report hypotensive or hypertensive symptoms.
- Recognise symptoms of hypokalaemia such as cramps or weakness and arrange testing.
Shared‑Care And Documentation
GPs and endocrinologists should document target BP and electrolyte goals, authorised titration steps and an emergency action plan.
Use telehealth for interim checks, particularly for remote patients.
Patient Resources
- Provide plain‑language handouts and translated or culturally adapted materials for Indigenous communities.
- Offer a downloadable monitoring chart and an emergency action algorithm for patients to carry.
Adverse events should be reported to the TGA to support pharmacovigilance and local registry efforts.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Darwin | Northern Territory | 5-9 days |
| Gold Coast | Queensland | 5-7 days |
| Newcastle | New South Wales | 5-9 days |
| Wollongong | New South Wales | 5-9 days |
| Geelong | Victoria | 5-9 days |
| Cairns | Queensland | 5-9 days |