
Trandate
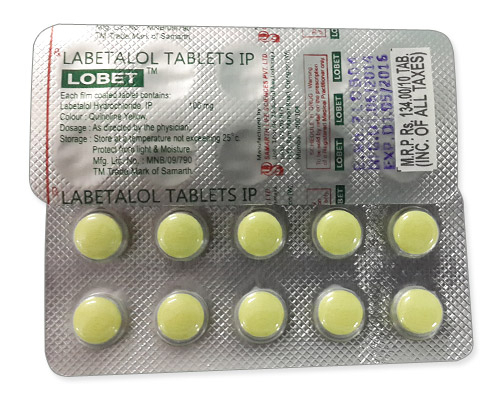
Trandate
- In some pharmacies and online vendors in Australia, trandate can be obtained without a prescription or receipt and may be delivered to you; however, the drug is officially classified as prescription-only in most jurisdictions, so availability without a prescription varies by supplier and region.
- Trandate (labetalol) is used to treat high blood pressure, including chronic hypertension, hypertensive emergencies and hypertension in pregnancy; it is a non‑selective beta‑adrenergic blocker with additional alpha‑1 blocking activity that lowers blood pressure by reducing heart rate and peripheral vascular resistance.
- Usual adult oral dosing starts at 100 mg twice daily, with maintenance typically 200–400 mg twice daily and divided doses up to a maximum of about 2,400 mg/day; for IV use, a slow bolus of 20 mg over ~2 minutes may be given (repeat and increase to 40–80 mg every 10 minutes as needed) or an infusion started at 0.5–2 mg/min and titrated to effect.
- Trandate is administered orally as tablets (commonly 100 mg, 200 mg and in some regions 300–400 mg) or intravenously as a solution for injection (e.g. 5 mg/mL or 100 mg/20 mL vials) for acute BP control.
- Onset of effect: oral doses generally begin to lower blood pressure within about 20–60 minutes (peak effect 1–4 hours); IV bolus doses act within minutes (around 2–5 minutes).
- Duration of action: oral antihypertensive effect commonly lasts about 8–12 hours (half‑life approximately 6–8 hours); IV effects occur rapidly and persist while the drug is present or for a few hours after bolus/infusion is stopped.
- Alcohol warning: avoid or limit alcohol while taking trandate because alcohol can increase dizziness, drowsiness and the risk of low blood pressure; combining alcohol with labetalol is not recommended, especially when starting treatment or changing dose.
- The most common side effec is dizziness (other frequent effects include fatigue, weakness, nausea and orthostatic hypotension).
- Would you like to try trandate without a prescription?
Basic Trandate Information
- INN (International Nonproprietary Name): Labetalol.
- Brand Names Available In Australia: Trandate; Presolol.
- ATC Code: C07AG01.
- Forms & Dosages: Tablets commonly 100 mg and 200 mg in Australia and New Zealand; tablets of 100 mg, 200 mg, 300 mg and 400 mg appear in other regions per available product info; intravenous solution packaging includes 5 mg/mL and 100 mg/20 mL vials.
- Manufacturers In Australia: Multiple generic suppliers and regional packagers supply Trandate and labetalol hydrochloride formulations; global manufacturers referenced in public product information include GSK, Sandoz, Mylan, Apotex and Amdipharm.
- Registration Status In Australia: Registered as a prescription medicine in jurisdictions where Trandate/brand and generic labetalol are marketed; check current Australian Register of Therapeutic Goods for up‑to‑date listings.
- OTC / Rx Classification: Prescription‑only (Rx) in all markets reviewed.
Latest Research Highlights (Australia + International)
Patients and clinicians often ask whether labetalol is still a go‑to for acute blood‑pressure control and pregnancy hypertension.
Randomised trials and pooled systematic reviews from 2022 to mid‑2024 continue to show labetalol provides rapid and reliable systolic and diastolic lowering comparable to hydralazine and oral nifedipine for acute severe hypertension.
Trials comparing IV or oral labetalol with oral nifedipine report broadly similar time to achieve target blood pressure, with different adverse‑event profiles noted.
Those comparative data typically show more maternal tachycardia with nifedipine and a higher incidence of orthostatic symptoms with labetalol.
Australian observational cohorts from state hospital networks (2020–2024) support safe inpatient IV use when titrated by protocol and supervised by emergency and obstetric teams.
TGA adverse‑event summaries and postmarket surveillance underline rare but important signals such as hepatic injury and bronchospasm that require clinician vigilance, particularly in patients with liver disease or reactive airways.
Pharmacoepidemiology studies using hospital discharge and PBS‑linked datasets confirm continued outpatient use of labetalol for chronic hypertension, often co‑prescribed with ACE inhibitors or diuretics for combined blood pressure control.
Below is a concise summary table of key randomised trials and meta‑analyses comparing labetalol with hydralazine and nifedipine.
| Comparison | Efficacy | Time To Target BP | Maternal/Neonatal Safety |
|---|---|---|---|
| Labetalol IV vs Hydralazine IV | Comparable systolic/diastolic reduction. | Minutes to an hour depending on dosing protocol. | Similar neonatal outcomes; hydralazine may cause more maternal headaches; labetalol more orthostatic events. |
| Labetalol IV vs Oral Nifedipine | Comparable efficacy for rapid control. | Both achieve targets within similar windows in acute care. | Nifedipine associated with more maternal tachycardia; labetalol associated with more dizziness. |
| Oral Labetalol vs Other Oral Agents (chronic) | Effective as monotherapy or in combination with ACEi/diuretics. | Weeks for optimal titration. | Well tolerated; monitor for hepatic effects and bronchospasm in at‑risk patients. |
TGA Data Highlights: TGA surveillance notes rare hepatic injury and bronchospasm reports with labetalol, underscoring the need for baseline liver assessment and respiratory history screening where clinically indicated.
Clinical Effectiveness In Australia
What can patients expect from labetalol in Australian hospitals and the community?
Australian practice uses labetalol for acute hypertensive crises delivered intravenously and for chronic oral blood pressure control in primary and specialist care.
Common hospital protocols list IV labetalol as an emergency option with typical bolus dosing of 20 mg slow and infusion rates of 0.5–2 mg/min for controlled and titratable reduction of severe hypertension.
Outpatient oral regimens in Australia follow international guidance and product information, often starting at 100 mg twice daily with stepwise titration to 200–400 mg twice daily and maximum daily doses reported up to 2,400 mg in divided doses.
PBS and TGA datasets track prescribing patterns and adverse events, with attention to obstetric care and aged‑care where orthostatic hypotension and fall risk matter most.
Real‑world effectiveness depends on timely titration, attention to comorbidities such as diabetes and ischaemic heart disease, and adherence to therapy.
| Setting | Typical Regimen | Usual Outcomes |
|---|---|---|
| Inpatient IV | 20 mg slow IV bolus; infusion 0.5–2 mg/min per protocol. | Rapid BP control with titratable effect; monitor for hypotension and bronchospasm. |
| Outpatient Oral | Start 100 mg twice daily, titrate every 1–2 weeks to 200–400 mg twice daily. | Good chronic BP control when adherent; combine with ACE inhibitors or diuretics as needed. |
Trandate and Presolol tablet presentations (100 mg and 200 mg) and IV solutions are the formulations typically seen in Australian practice.
Indications And Expanded Uses
Who is labetalol intended for, and when do specialists reach for it?
TGA‑aligned indications centre on treatment of hypertension, including chronic hypertension and acute severe hypertension where IV therapy is indicated.
IV labetalol is commonly used in emergency settings and obstetric care for severe preeclampsia under specialist direction.
Common off‑label specialist uses in Australia include perioperative blood pressure control, management of hypertensive crises refractory to other agents such as clonidine, and select paediatric emergencies in tertiary centres using weight‑based dosing.
- Approved Uses: Hypertension (chronic oral therapy); acute severe hypertension with IV formulations in hospital settings.
- Common Off‑Label/Specialist Uses: Perioperative hypertension control; clonidine‑refractory crises; selected paediatric hypertensive emergencies under specialist care.
Escalation Checklist — When To Move To IV Therapy: when systolic pressure remains dangerously elevated despite oral measures; signs of end‑organ damage; severe preeclampsia; or rapid control needed in acute care settings.
Standard adult oral and IV starting doses per product information are oral 100 mg twice daily and IV bolus 20 mg over about 2 minutes, repeated or followed by infusion as required.
Composition And Brand Landscape
Which brands and pack sizes will patients commonly see in Australia and New Zealand?
The active ingredient is labetalol hydrochloride, classified under ATC C07AG01 as a non‑selective beta‑blocker with alpha‑blocking activity.
In Australia and New Zealand the product landscape includes Trandate and Presolol with common tablet strengths of 100 mg and 200 mg in bottle or blister packaging.
Global and regional manufacturers referenced in product information include GSK, Sandoz, Mylan, Apotex and other generic suppliers who supply labetalol hydrochloride across markets.
| Brand Name | Strengths | Packaging | Common Suppliers (Australia/NZ) |
|---|---|---|---|
| Trandate | 100 mg, 200 mg | Bottles or blister packs | Multiple generic distributors and regional packagers |
| Presolol | 100 mg, 200 mg | Bottles or blister packs | Generic suppliers in Australia/New Zealand |
Common consumer pack sizes searched for include 100‑tablet bottles and smaller blister packs for convenience while travelling.
Contraindications And Special Precautions
Who should not take labetalol, and who needs close monitoring?
- Absolute Contraindications: Bronchial asthma or a history of obstructive airway disease.
- Absolute Contraindications: Overt cardiac failure, cardiogenic shock, second or third‑degree heart block without a pacemaker, severe bradycardia, known hypersensitivity to labetalol.
Use labetalol cautiously in patients with diabetes because beta‑blockers can mask symptoms of hypoglycaemia.
Patients with peripheral vascular disease, liver disease or suspected pheochromocytoma require specialist evaluation and careful monitoring when labetalol is considered.
Special Australian considerations include the elderly in aged care who face higher fall risk from orthostatic hypotension and people in some Indigenous communities who have high cardiovascular disease prevalence and benefit from culturally safe, shared decision‑making and closer follow‑up.
Workplace and daily‑living advice should include avoiding driving or operating heavy machinery if dizziness occurs and taking orthostatic precautions when getting up from seated or lying positions.
Definition: An absolute contraindication precludes use because the risk of serious harm is high.
Definition: A relative contraindication means use may be possible with specialist oversight, dose adjustment and close monitoring.
Dosage Guidelines (Australian Practice)
How are doses chosen and adjusted in Australian practice?
For adults starting oral therapy, common initiation is 100 mg twice daily with titration every 1–2 weeks to effect.
Maintenance doses commonly range from 200–400 mg twice daily, with reported maximal daily doses up to approximately 2,400 mg in divided doses when clinically required and supervised.
For hypertensive emergency in the emergency department, standard IV bolus dosing is 20 mg given slowly over about 2 minutes, with repeat doses or increments of 40–80 mg every 10 minutes as needed, or a continuous infusion started at 0.5–2 mg/min titrated to blood pressure response.
Elderly patients should start at lower doses and titrate cautiously because of increased dizziness and orthostatic hypotension risk.
Renal impairment generally does not require formal dose reduction but mandates careful monitoring for exaggerated effects.
Liver impairment may require dose reduction and periodic liver function testing due to the potential for accumulation and hepatic injury.
| Indication | Typical Dose | Notes |
|---|---|---|
| Oral Chronic Hypertension | Start 100 mg twice daily; titrate to 200–400 mg twice daily. | Review every 1–2 weeks during titration. |
| IV Hypertensive Emergency | 20 mg slow IV; repeat or escalate 40–80 mg every 10 min; infusion 0.5–2 mg/min. | Administer under monitored conditions with cardiac and respiratory observation. |
| Elderly | Lower starting dose; slower titration. | Monitor orthostatic BP and falls risk. |
Interactions Overview
Which medicines and substances require attention when taking labetalol?
Labetalol has additive hypotensive effects when combined with other antihypertensives including ACE inhibitors, ARBs, diuretics and calcium‑channel blockers.
Combining labetalol with verapamil or diltiazem increases the risk of severe bradycardia and atrioventricular block and should be managed by specialists with ECG monitoring.
In people with diabetes, labetalol can mask adrenergic symptoms of hypoglycaemia and may interact with insulin and oral hypoglycaemics by blunting symptom recognition.
Alcohol potentiates orthostatic effects and dizziness and should be avoided or limited while titrating therapy.
Concurrent use of clonidine requires careful management to avoid withdrawal‑related hypertensive crises; avoid abrupt stopping of either agent without clinical guidance.
| Drug/Class | Potential Effect | Counselling Point |
|---|---|---|
| ACE Inhibitors/ARBs/Diuretics | Increased hypotension risk | Monitor BP and adjust doses to avoid symptomatic hypotension. |
| Verapamil/Diltiazem | Risk of severe bradycardia/AV block | Avoid or use under specialist supervision with ECG monitoring. |
| Insulin/Oral Hypoglycaemics | Masking of hypoglycaemia symptoms | Advise glucose monitoring and educating on non‑adrenergic hypoglycaemia signs. |
Cultural Perceptions And Patient Habits In Australia
How do Australian patients approach blood pressure treatment and pharmacy services?
Cost, convenience and pharmacist advice are key drivers for patient behaviour in Australia.
Price‑sensitive consumers commonly seek generics and compare prices at major chains and online retailers when searching for Trandate 200 mg or other pack sizes.
Older adults in rural and regional areas rely on local pharmacies and telehealth e‑scripts to maintain continuity of chronic therapy.
Indigenous communities experience higher rates of hypertension and often benefit from culturally appropriate counselling and community outreach to support adherence.
Online patient forums frequently raise concerns about dizziness, sexual dysfunction and pregnancy safety, so trust in pharmacists and GPs remains central for medication queries.
Telehealth and e‑prescribing are increasingly used to arrange repeat supplies and home delivery for chronic therapy in remote areas.
Availability And Pricing Patterns (Australia)
Where and how do Australians obtain labetalol, and what affects cost?
Major pharmacy chains such as Chemist Warehouse, Priceline and TerryWhite Chemmart commonly stock generic labetalol and brand Trandate/Presolol formulations.
Rural supply can be variable but online ordering combined with e‑prescriptions helps bridge access gaps.
PBS listing materially lowers patient cost where the product is subsidised; private script pricing compared with PBS‑subsidised cost is a common consumer consideration.
| Purchase Route | Typical Cost Pattern | Patient Tip |
|---|---|---|
| Major Pharmacy Chain | Competitive private script pricing; generics available. | Ask about generic substitution and pack sizes such as 100 tablet bottles. |
| Accredited Online Pharmacy | Price comparable to bricks‑and‑mortar for private scripts; delivery options. | Have prescription ready and confirm PBS status before purchase. |
| PBS‑Subsidised Supply | Lower cost if eligible; depends on current PBS listings. | Check PBS schedule or ask pharmacist about concession pricing. |
In our online pharmacy, trandate is available with discreet delivery to Australia, subject to prescription requirements and standard verification procedures.
Comparable Medicines And Preferences
How does labetalol stack up against alternative antihypertensives used in Australia?
Alternatives include selective beta‑blockers such as metoprolol, atenolol and bisoprolol, mixed agents like carvedilol, ACE inhibitors such as enalapril, ARBs, and calcium‑channel blockers including amlodipine and nifedipine.
For obstetric hypertension, hydralazine and nifedipine are commonly used comparators to labetalol.
- Pros Of Labetalol: Combined alpha and beta blockade reduces reflex tachycardia and is an established IV option for controlled emergency blood‑pressure lowering.
- Cons Of Labetalol: Risk of bronchospasm in asthma, potential hepatotoxicity, and masking of hypoglycaemia symptoms.
| Indication | Preferred Agent | Key Trade‑Off |
|---|---|---|
| Chronic Hypertension | ACEi/ARB or CCB often first line; labetalol useful where beta effect is desirable. | Monitor for metabolic effects and respiratory contraindications. |
| Obstetric Severe Hypertension | Labetalol, Hydralazine, Oral Nifedipine | Choose based on maternal comorbidities and rapidity of control required. |
FAQ
Patients frequently ask short practical questions about Trandate and labetalol.
Can I take Trandate in pregnancy?
Labetalol is used for severe pregnancy hypertension under obstetric supervision and is typically initiated or continued only with specialist involvement.
What if I miss a dose?
Take the missed dose as soon as remembered unless it is almost time for the next dose; do not double up the dose.
Is labetalol on the PBS?
PBS listing can vary by formulation and indication; check the current PBS schedule or ask your pharmacist or GP for up‑to‑date information.
Can I drink alcohol while taking labetalol?
Alcohol can worsen dizziness and orthostatic hypotension; avoid excess alcohol and do not drive if affected.
When To Call Your GP Or Emergency Department
Seek immediate medical attention for severe breathlessness, chest pain, fainting, severe dizziness or signs of liver injury such as jaundice or persistent abdominal pain.
Guidelines For Proper Use (Pharmacist Counselling Style)
What should pharmacists cover when counselling a patient starting labetalol?
Confirm absolute contraindications such as asthma or high‑degree heart block before supply.
Review comorbidities including diabetes and liver disease and check concurrent medicines for interactions.
Advise the patient on initial dosing and titration plan and warn about dizziness and orthostatic hypotension.
Recommend baseline blood pressure and heart rate monitoring and suggest periodic liver function tests if clinically indicated.
Counsel on storage: store tablets at 20–25°C, protect from moisture and light, and do not freeze IV solutions.
Offer adherence strategies such as linking doses to meals or daily routines and discuss PBS concessions or generic options to reduce cost barriers.
Provide a simple monitoring schedule: BP and HR check at baseline, review at 1–2 weeks after dose changes, and periodically thereafter.
- Pharmacist Checklist: Screen for contraindications, review interactions, advise on missed dose, provide written dose schedule and safety signs to watch for.
- Patient Handout Template: Dosing times, side effects to report, emergency warning signs, storage and follow‑up appointment reminder.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Darwin | Northern Territory | 5-9 days |
| Gold Coast | Queensland | 5-7 days |
| Newcastle | New South Wales | 5-7 days |
| Wollongong | New South Wales | 5-7 days |
| Geelong | Victoria | 5-7 days |
| Cairns | Queensland | 5-9 days |
| Townsville | Queensland | 5-9 days |
| Alice Springs | Northern Territory | 5-9 days |
Final Notes And Practical Takeaways
Labetalol (INN) branded as Trandate or Presolol remains a well‑established option for both acute IV blood‑pressure control and chronic oral management in Australian practice.
Standard adult oral initiation is commonly 100 mg twice daily, titrating to 200–400 mg twice daily with careful monitoring for adverse effects.
IV protocols such as 20 mg slow bolus and infusion rates of 0.5–2 mg/min allow controlled emergency lowering of blood pressure in monitored settings.
Key safety checks include screening for asthma, heart block and liver disease, reviewing concomitant medicines and educating patients on dizziness and hypoglycaemia masking.
For further clarification on product specifics such as formulations and pack sizes, ask a pharmacist or consult the product information and the Australian Register of Therapeutic Goods.