
Femara
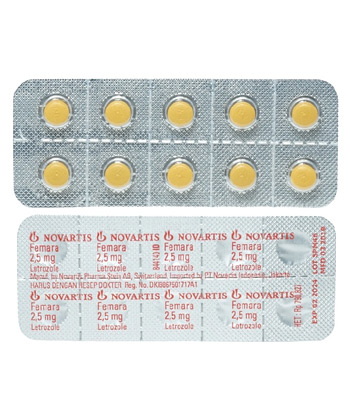
Femara
- Femara (letrozole) is a prescription‑only medicine and must legally be dispensed by a pharmacy with a valid prescription; although some online vendors may claim to sell it without a prescription, Femara is not authorised over the counter and should only be used under medical supervision.
- Femara is used to treat hormone receptor‑positive breast cancer in postmenopausal women (adjuvant, extended adjuvant and first‑line advanced/metastatic disease); it is a non‑steroidal aromatase inhibitor that blocks the aromatase enzyme to lower oestrogen production and slow oestrogen‑dependent tumour growth.
- The usual adult dose is 2.5 mg once daily orally (with or without food); adjuvant therapy commonly continues for 5 years and may be extended per clinician advice.
- Femara is supplied as oral 2.5 mg film‑coated tablets (blister packs or bottles); no injectable, topical or other forms are authorised for patient use.
- Absorption is rapid with peak plasma levels around 1 hour; aromatase inhibition begins within hours, though measurable clinical effects on tumours or biomarkers generally take weeks.
- The elimination half‑life is approximately 2 days (≈48 hours) with sustained aromatase suppression on once‑daily dosing; treatment duration depends on indication (commonly 5 years in adjuvant use, continued until progression in metastatic disease).
- There is no absolute prohibition on occasional alcohol, but avoid excessive drinking—alcohol may worsen fatigue, liver function and bone health; discuss alcohol use with your prescriber.
- The most common side effect is hot flushes.
- Would you like to try femara without a prescription?

Latest Research Highlights (Australia + International)
Basic Femara Information
- INN (International Nonproprietary Name): Letrozole.
- Brand Names Available In Australia: Femara (principal brand).
- ATC Code: L02BG04 — Aromatase Inhibitors.
- Forms & Dosages: Oral film-coated tablets, 2.5 mg; typical packaging includes blisters or bottles (7, 10, 14, 28, 30, or 100 tablets).
- Manufacturers In Australia: Alphapharm (local generic supplier) and originator supply by Novartis; additional global generics from Cipla, Sun Pharma, Hetero, Sandoz and others.
- Registration Status In Australia: TGA approved for hormone receptor‑positive breast cancer in postmenopausal women.
- OTC / Rx Classification: Prescription only (Rx) — Femara/letrozole is never available over the counter.
Recent Australian and international literature since 2022 continues to support letrozole as a core aromatase inhibitor for hormone receptor‑positive, postmenopausal breast cancer.
Meta‑analyses and registry updates from 2022–2025 highlight a disease‑free survival benefit when therapy is extended to five years in selected patients.
Comparisons with tamoxifen in postmenopausal adjuvant settings show letrozole to be either superior or at least equivalent for recurrence reduction.
Long‑term safety concerns persist, particularly for bone health and changes in cardiovascular risk markers such as cholesterol.
Australian cancer registries and TGA‑linked pharmacovigilance reports mirror global safety signals, with arthralgia, osteoporosis risk and hypercholesterolaemia the most reported adverse events.
Fertility‑clinic case series describe off‑label use of letrozole for ovulation induction, but professional guidance stresses supervised use because Femara 2.5 mg is not registered for infertility in most jurisdictions.
Key product facts from regulatory summaries: INN letrozole, brand Femara, ATC L02BG04, form 2.5 mg oral tablets; prescription only; TGA approved.
| Trial / Meta‑Analysis | Endpoints | Findings (2022–2025) |
|---|---|---|
| Extended Adjuvant Trials | Disease‑Free Survival (DFS), Bone Density | DFS benefit in selected high‑risk patients; increased bone loss noted with longer use. |
| Adjuvant Comparisons | DFS, Overall Survival (OS) | Letrozole showed parity or superiority versus tamoxifen for recurrence reduction in postmenopausal cohorts. |
| Registry Safety Updates | Adverse Events, Lipids | Arthralgia and hypercholesterolaemia remain common; osteoporosis risk reinforced. |
Safety Highlights: arthralgia, osteoporosis risk and raised cholesterol are the key signals to monitor during letrozole therapy.
Clinical Effectiveness In Australia
Are Australian outcomes for letrozole similar to global data and what does that mean for patients?
Letrozole 2.5 mg (Femara) is widely used across Australia for adjuvant, extended adjuvant and metastatic hormone receptor‑positive breast cancer.
TGA approval aligns with EMA and FDA indications for postmenopausal disease, and many eligible patients receive subsidised therapy via the PBS.
Real‑world data from state cancer registries show recurrence reduction and progression‑free outcomes comparable with international cohorts.
Switching from tamoxifen to letrozole, or starting letrozole upfront, produces outcomes that mirror trial results in postmenopausal populations.
Clinical monitoring in Australia commonly includes baseline bone mineral density, lipid profiles and periodic liver function tests.
TGA’s Database of Adverse Event Notifications reports hot flushes, arthralgia and fatigue as typical adverse events reported locally.
Australian oncologists individualise treatment duration, commonly five years of aromatase inhibition with consideration of extension to a total of ten years including prior tamoxifen in higher‑risk patients.
- PBS: Femara is subsidised for approved indications for eligible patients; check clinical criteria with your oncologist or pharmacist.
- TGA Safety Communications: Ongoing pharmacovigilance notes arthralgia, bone density loss and hypercholesterolaemia as signals.
- Definition — Disease‑Free Survival (DFS): time without evidence of cancer recurrence after primary treatment.
- Definition — Overall Survival (OS): time from treatment start until death from any cause.
- Definition — Progression‑Free Survival (PFS): length of time during treatment that a patient’s cancer does not worsen.
Indications & Expanded Uses (TGA Scope + Off‑Label)
Who is letrozole approved for, and where do clinicians still use it off‑label?
Per regulatory approvals and clinical practice, letrozole (Femara) is indicated in postmenopausal women for early adjuvant, extended adjuvant and advanced/metastatic hormone receptor‑positive breast cancer.
The standard adult dose is 2.5 mg once daily taken orally with or without food.
Letrozole is prescription only and is contraindicated in pre‑menopausal women, pregnancy and lactation.
Off‑label use includes ovulation induction in fertility clinics with low‑dose protocols, but Femara is not registered for infertility in most jurisdictions and specialist oversight is required.
Letrozole is not indicated in paediatric populations.
- Approved Uses: Adjuvant therapy for early breast cancer, extended adjuvant therapy, first‑line treatment in advanced/metastatic disease.
- Off‑Label Uses: Ovulation induction in selected cases under specialist fertility clinic supervision.
| Indication | Typical Duration |
|---|---|
| Adjuvant (early breast cancer) | Commonly 5 years |
| Extended Adjuvant | May be extended to total 5 years of aromatase inhibitor therapy or integrated into a 10‑year total including prior tamoxifen |
| Metastatic / Advanced | Continue until progression or unacceptable toxicity |
Composition & Brand Landscape (Australia Focus)
What is in the tablet and who supplies it in Australia?
The active ingredient is letrozole, the INN for the compound.
Femara 2.5 mg film‑coated tablets are the principal brand available in Australia.
Local manufacturing and supply include Alphapharm generics alongside originator supplies from Novartis and global generics from manufacturers such as Cipla and Sun Pharma.
Packaging in Australia commonly uses blister packs with tablet counts typically ranging from 7 to 30 tablets per box.
The ATC code for letrozole is L02BG04, placing it among aromatase inhibitors used in oncology.
| Product | Manufacturer | Typical Pack Sizes | PBS Status |
|---|---|---|---|
| Femara 2.5 mg | Novartis | Blister packs, 14 or 30 | Subsidised for approved indications |
| Letrozole 2.5 mg (generic) | Alphapharm | Blister packs, various (7–30) | Generic PBS listings influence dispensing |
| Imported generics | Cipla, Sun Pharma, Sandoz | Boxes of 10, 28, 30 | May be listed; availability varies |
Generic substitution is common, and PBS listings strongly influence which brand is dispensed by community pharmacies.
Contraindications & Special Precautions
Who should not take letrozole and what checks do pharmacists perform first?
Absolute contraindications include pre‑menopausal status, pregnancy and lactation, and known hypersensitivity to letrozole or any excipients.
Exercise caution in severe hepatic impairment and in severe renal dysfunction where CrCl is below 10 ml/min, due to limited data.
Pre‑existing osteoporosis or high fracture risk requires baseline bone mineral density assessment and consideration of bone‑protective therapy.
Patients with ischemic heart disease or significant cardiovascular history need lipid monitoring and appropriate cardiovascular risk management.
Indigenous and remote communities may present higher baseline comorbidity and bone disease; culturally appropriate screening and counselling are essential.
Advise patients that symptomatic hot flushes and fatigue can affect driving and workplace safety and should be managed or discussed with the clinician.
- Pre‑Treatment Checklist: Pregnancy test where relevant, baseline BMD, lipid profile, liver function tests.
- Absolute Contraindications: Pre‑menopausal women; pregnancy; lactation; hypersensitivity.
- Relative Contraindications: Severe hepatic impairment; severe renal dysfunction; significant osteoporosis; potent CYP450 interactions; ischaemic heart disease.
Dosage Guidelines
What dose should patients take and how are regimens tailored?
- Standard Adult Dose: 2.5 mg once daily, orally, with or without food.
- Adjuvant / Extended Adjuvant: commonly five years of aromatase inhibitor therapy; total duration may reach ten years including prior tamoxifen, depending on risk.
- Advanced / Metastatic Disease: continue 2.5 mg once daily until disease progression or unacceptable toxicity.
- Elderly Patients: no routine dose adjustment is required solely for age.
- Hepatic / Renal Impairment: mild–moderate impairment usually does not require dose change; severe impairment requires specialist review and caution.
- Children: not indicated; paediatric dosing not established.
- Missed Dose: take as soon as remembered unless it is near the next scheduled dose; do not double up.
- Overdose: no specific antidote; provide supportive care and monitoring.
Definitions: adjuvant (treatment given after primary therapy to reduce recurrence), extended adjuvant (continued therapy beyond standard course), metastatic (treatment for advanced disease that has spread).
Interactions Overview (Drugs, Food, Lifestyle)
Which medicines and everyday habits can affect letrozole treatment?
Letrozole has few direct food interactions, but alcohol can worsen hot flushes, fatigue and may negatively affect bone health.
Strong CYP450 inducers such as certain antiepileptics or rifampicin can reduce letrozole exposure and may require specialist input.
Potent CYP450 inhibitors could theoretically increase exposure; clinical caution and monitoring are advised when such combinations are unavoidable.
Common co‑prescriptions include bisphosphonates, denosumab, and calcium/vitamin D to protect bone health.
Statins are commonly started if monitoring shows clinically significant hypercholesterolaemia during therapy.
| Drug Class | Interaction Mechanism | Clinical Action |
|---|---|---|
| Strong CYP450 Inducers (e.g. rifampicin) | May lower letrozole plasma levels | Consult specialist; consider alternative where possible |
| Potent CYP450 Inhibitors | May increase letrozole exposure | Monitor for toxicity; adjust treatment per specialist advice |
| Bisphosphonates / Denosumab | No adverse pharmacokinetic interaction; adjunctive bone protection | Co‑prescribe when indicated for osteoporosis prevention |
| Statins | Address hypercholesterolaemia potentially unmasked by letrozole | Start statin therapy per cardiometabolic guidelines where required |
- Lifestyle Advice: moderate alcohol intake, stop smoking, and regular weight‑bearing exercise to support bone health.
- Use clinical decision support and TGA/state e‑health interaction checkers at dispensing.
Cultural Perceptions & Patient Habits In Australia
How do Australian patients approach treatment and what practical issues arise?
Australian patients are often price sensitive and rely on PBS subsidies when available.
Choice between brand and generic is frequently mediated by pharmacies and general practitioners.
Trust in community pharmacists and major chains is high, and telehealth has increased access to e‑prescriptions in urban areas.
Rural and remote patients face transport and specialist access barriers, so regional oncology outreach and teleoncology play a key role.
Continuity for monitoring such as BMD scans and blood tests is sometimes challenging in remote settings.
Patient forums commonly surface concerns about menopausal symptoms, bone loss and fertility when letrozole is discussed.
Culturally tailored counselling, including involvement of Indigenous health workers, improves understanding and adherence.
- Urban Behaviours: easy access to specialist clinics, same‑day pharmacy pickups, telehealth follow‑ups.
- Rural Behaviours: planned repeats, home delivery, coordination with regional hospital pharmacies and outreach clinics.
Patient Journey: GP → Oncology referral → Specialist prescription → Community pharmacy dispensing → Ongoing monitoring and follow‑up.
Availability & Pricing Patterns (Australia: Chains, Online, PBS)
Where patients buy Femara and what does it cost across channels?
Major pharmacy chains such as Chemist Warehouse, Priceline and TerryWhite Chemmart stock Femara and generic letrozole where available.
Community pharmacies and registered online pharmacies dispense Femara on prescription with counselling.
PBS typically subsidises letrozole for approved indications so many patients pay only the PBS co‑payment rather than the full private price.
Private prescriptions or non‑PBS use result in higher out‑of‑pocket costs and variable private pricing across pharmacies.
Price‑sensitive consumers commonly compare online and brick‑and‑mortar prices, but pharmacists remain the main source of safe counselling and monitoring.
Rural supply can experience occasional delays and regional hospital pharmacies may dispense repeats; many pharmacies offer home delivery for remote patients.
| Payment Type | Typical Cost Range |
|---|---|
| PBS‑Subsidised (concession eligible) | PBS co‑payment applies (varies by concession status) |
| Private Prescription (non‑PBS) | Higher out‑of‑pocket cost; varies by pharmacy and brand |
| Online Pharmacy Ordering | Comparable to community pharmacy, often with shipping fees; confirm PBS eligibility |
For purchases through our online pharmacy, Femara is supplied on prescription with discreet delivery to Australia in 5–14 days.
Comparable Medicines And Patient Preferences
What are the alternatives and how do patients decide between them?
Alternatives in Australia include anastrozole and exemestane, which are other aromatase inhibitors, and tamoxifen, a SERM.
Choice depends on menopausal status, comorbidity profile and how patients tolerate side effects.
Letrozole may offer marginal efficacy advantages in certain settings, but aromatase inhibitors generally cause more bone density loss compared with tamoxifen.
Exemestane is a steroidal aromatase inactivator while letrozole and anastrozole are non‑steroidal, producing different metabolic and side‑effect profiles.
Switching strategies are commonly used if intolerance occurs; clinicians tailor therapy to balance recurrence risk and adverse effects.
| Medicine | Efficacy | Bone Impact | Metabolic Effects |
|---|---|---|---|
| Letrozole | High for postmenopausal adjuvant use | Greater bone density loss risk | May raise cholesterol in some patients |
| Anastrozole | Comparable efficacy | Moderate bone impact | Similar metabolic profile to letrozole |
| Exemestane | Comparable; steroidal mechanism | Bone impact similar to non‑steroidal agents | Different androgenic metabolite profile |
| Tamoxifen | Effective, historically first‑line | Protective effect on bone in postmenopausal women | Higher thromboembolism and endometrial side‑effect risk |
Patients concerned about bone health sometimes prefer tamoxifen despite its different risk profile, while others accept aromatase inhibitor effects for reduced recurrence risk.
FAQ — 4 Common Australian Patient Questions
- Q: Can I get Femara on the PBS? A: Many approved indications for Femara are PBS‑subsidised for eligible patients; confirm eligibility with your oncologist or pharmacist.
- Q: Is it safe in younger women trying for pregnancy? A: No; letrozole is contraindicated in pregnancy and pre‑menopausal women unless used off‑label in supervised fertility clinics with specialist oversight.
- Q: How do I reduce bone risk while on letrozole? A: Baseline BMD testing, adequate calcium and vitamin D, weight‑bearing exercise and discussion about bisphosphonates or denosumab with your clinician.
- Q: What if I miss a dose? A: Take the missed dose as soon as remembered unless it is close to the next dose; do not double up doses.
Quick‑action checklist for when to call your GP or oncologist: severe new joint pain or swelling, sudden chest pain or breathlessness, or suspected pregnancy.
Practical Guidelines For Proper Use (Pharmacy Counselling & PBS Advice)
What should pharmacists tell patients when dispensing Femara?
- Confirm postmenopausal status and that the prescription is valid, since letrozole is prescription only.
- Review contraindications: pregnancy, lactation, pre‑menopause and known hypersensitivity.
- Explain dosing clearly: 2.5 mg once daily, taken at the same time each day with or without food.
- Storage: keep below 30°C, protect from moisture, and keep tablets in the original blister until use.
- Missed dose advice: take when remembered unless close to next dose; never double up.
- Discuss common side effects: hot flushes, arthralgia and fatigue, and offer management strategies or referral.
- Advise baseline monitoring: BMD, lipid profile and LFTs, with follow‑up at 6–12 months and annually as indicated.
- For PBS patients: confirm concession status, review repeat prescription timing and offer home delivery or coordination with telehealth services for remote patients.
- Provide culturally appropriate fact sheets and involve Indigenous health workers when relevant.
| Monitoring | Timing |
|---|---|
| Bone Mineral Density (BMD) | Baseline, 6–12 months if indicated, then annually |
| Lipid Profile | Baseline, 3–6 months, then periodically |
| Liver Function Tests (LFTs) | Baseline and as clinically indicated |
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5–7 days |
| Melbourne | Victoria | 5–7 days |
| Brisbane | Queensland | 5–7 days |
| Perth | Western Australia | 5–7 days |
| Adelaide | South Australia | 5–7 days |
| Canberra | Australian Capital Territory | 5–7 days |
| Hobart | Tasmania | 5–7 days |
| Newcastle | New South Wales | 5–9 days |
| Wollongong | New South Wales | 5–9 days |
| Gold Coast | Queensland | 5–9 days |
| Geelong | Victoria | 5–9 days |
| Townsville | Queensland | 5–9 days |
| Darwin | Northern Territory | 5–9 days |
| Ballarat | Victoria | 5–9 days |