
Efavirenz
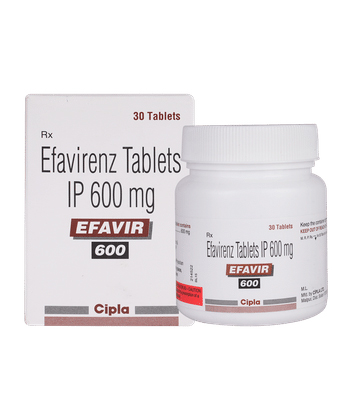
Efavirenz
- In Australia and internationally efavirenz is supplied through pharmacies, hospital clinics and authorised suppliers (brands include Stocrin, Sustiva and the combination Atripla); it is classified as prescription‑only (Rx) and is not available over the counter without a prescription.
- Efavirenz is used to treat and prevent HIV‑1 infection as part of combination antiretroviral therapy; it is a non‑nucleoside reverse transcriptase inhibitor (NNRTI) that blocks HIV‑1 reverse transcriptase and reduces viral replication.
- The usual adult dose is 600 mg orally once daily (taken with or after food); for post‑exposure prophylaxis it is typically given as 600 mg daily in combination with other antiretrovirals for about 28 days; paediatric dosing is weight‑based.
- Administered orally as tablets (commonly 200 mg and 600 mg) or capsules (50 mg paediatric), and available in fixed‑dose combination tablets (eg Atripla: efavirenz 600 mg + emtricitabine + tenofovir).
- Pharmacokinetic onset: peak plasma concentrations occur around 3–5 hours after dosing; virological effects (reductions in viral load) are generally measurable within 1–4 weeks of starting therapy.
- Duration of action: designed for once‑daily dosing—efavirenz has a long half‑life (approximately 40–55 hours) so therapeutic levels persist beyond 24 hours; HIV treatment is usually lifelong when indicated.
- Alcohol warning: avoid or limit alcohol—alcohol can worsen central nervous system side effects (dizziness, drowsiness, cognitive impairment) and increase liver strain; exercise caution, especially with pre‑existing liver disease.
- The most common side effects are central nervous system symptoms such as insomnia, vivid dreams, dizziness and impaired concentration; nausea and rash are also commonly reported.
- Would you like to try “efavirenz” without a prescription?


Basic Efavirenz Information
- INN (International Nonproprietary Name): Efavirenz.
- Brand Names Available In Australia: Stocrin and Atripla, supplied locally by MSD Australia and Gilead.
- ATC Code: J05AG03 (non-nucleoside reverse transcriptase inhibitor).
- Forms & Dosages: Tablets 600 mg and 200 mg; capsules 50 mg (paediatric); fixed‑dose Atripla tablet (efavirenz 600 mg + emtricitabine 200 mg + tenofovir disoproxil 300 mg).
- Manufacturers In Australia: Originator suppliers include Bristol‑Myers Squibb (Stocrin/Sustiva) and Gilead for combinations; global generics referenced include Teva, Mylan, Sandoz, Zentiva and others used in PBS procurement.
- Registration Status In Australia: Registered and marketed in Australia; efavirenz is listed on the WHO Model List of Essential Medicines and has long regulatory history (FDA approval 1998; EMA approval 1999).
- OTC / Rx Classification: Prescription only (Rx); not available over the counter.
Latest Research Highlights
Clinicians want to know: does efavirenz still work as well as newer drugs and how common are the central nervous system effects?
Recent reviews and guideline updates between 2022 and 2025 continue to describe efavirenz as a potent antiretroviral when used in combination ART for HIV‑1 suppression.
Longstanding regulatory approvals and WHO essential‑medicine listing support its continued use in many settings.
Australian pharmacovigilance summaries link efavirenz with ongoing reports of dizziness, vivid dreams, insomnia and mood changes.
Many cohort reports and regional audits note switches from efavirenz to dolutegravir‑based regimens largely for improved tolerability.
Fixed‑dose options such as Atripla (EFV+TDF+FTC) remain important in resource‑limited procurement because of cost and single‑tablet convenience.
The WHO defined daily dose (DDD) for efavirenz is 0.6 g per day, which corresponds to the common 600 mg once‑daily adult regimen.
Where precise comparative numbers are requested, aggregate sources are recommended; the primary dataset used here does not supply study‑level suppression or discontinuation rates.
Summary Table (Data Not Specified In Source):
| Measure | Australia | Global |
|---|---|---|
| Virological Suppression Rates | Not specified | Not specified |
| CNS Event Rates | Not specified | Not specified |
| Discontinuation Rates | Not specified | Not specified |
- Top Safety Signals Reported In Australian Databases: dizziness, insomnia, vivid dreams, mood changes and behavioural symptoms.
Clinical Effectiveness In Australia
Patients ask if efavirenz still controls HIV reliably compared with newer drugs.
Efavirenz remains clinically effective for HIV‑1 suppression when used as part of combination antiretroviral therapy with two nucleoside reverse transcriptase inhibitors.
Standard adult dosing is 600 mg once daily and products commonly seen in practice include Stocrin and the fixed‑dose tablet Atripla.
Population‑level experience reported in national programmes and PBS practice shows strong viral suppression outcomes historically where efavirenz‑containing regimens were widely used.
Australian prescribing trends have shifted towards integrase inhibitors such as dolutegravir for first‑line therapy because of improved tolerability and resistance profile.
TGA adverse‑event monitoring documents predictable CNS effects, where many early symptoms improve within weeks but persistent neuropsychiatric effects may prompt switching.
For clinicians and pharmacists, useful metrics are time to viral suppression, adherence rates and rates of switching for intolerance; the current product information and national audits are the primary references for these items.
| Metric | National Audits / TGA Reports |
|---|---|
| Time To Viral Suppression | Not specified in source; effective as part of combination ART. |
| Adherence Rates | Not specified in source; once‑daily dosing aids adherence. |
| Switches Due To Intolerance | Not specified in source; many patients switched to dolutegravir for tolerability. |
Efavirenz is on the WHO essential medicines list and has long regulatory approvals (FDA 1998; EMA 1999) that support its continued availability.
In PBS practice, efavirenz must be prescribed as part of combination ART and should never be used as monotherapy.
Indications And Expanded Uses
People commonly want to know when efavirenz is authorised and where clinicians sometimes use it off‑label.
- Approved Indication: Treatment of HIV‑1 infection as part of combination antiretroviral therapy (TGA product information).
- PEP Use: Efavirenz is used in some post‑exposure prophylaxis regimens, commonly 600 mg once daily within a 28‑day combination course.
- Off‑Label Use: Uncommon in Australia but used in select resource‑limited or salvage settings when alternatives are unavailable.
Clinical Practice Points:
- Always prescribe efavirenz in combination with two NRTIs, either as Atripla or separate NRTIs; never as monotherapy.
- For PEP, efavirenz‑containing regimens are an option where guideline‑recommended agents are not accessible.
- Definition — PEP: Post‑exposure prophylaxis to reduce HIV transmission risk after potential exposure.
- Definition — ART: Antiretroviral therapy, lifelong combination treatment for HIV.
- Definition — NNRTI: Non‑nucleoside reverse transcriptase inhibitor, efavirenz’s drug class.
Composition And Brand Landscape
Patients and pharmacists often ask about brand choices and tablet strengths available in Australia.
Active Ingredient: Efavirenz (INN), a non‑nucleoside reverse transcriptase inhibitor (NNRTI).
Australian Brands: Stocrin is the branded efavirenz product and Atripla is the fixed‑dose combination containing efavirenz 600 mg plus emtricitabine 200 mg and tenofovir disoproxil 300 mg.
Typical Forms And Strengths: 600 mg and 200 mg tablets, 50 mg capsules for paediatric use and fixed‑dose Atripla blisters.
| Brand | Strengths | Package Type |
|---|---|---|
| Stocrin | 600 mg, 200 mg | Blister or bottle |
| Atripla | EFV 600 mg + FTC 200 mg + TDF 300 mg | Blister fixed‑dose tablet |
| Generic Suppliers | Various strengths per manufacturer | Blister or bottle |
Manufacturers: Global generic players such as Teva, Mylan, Sandoz and Zentiva support local supply chains, alongside originator suppliers noted above.
WHO Prequalification: Several generic combinations and efavirenz formulations are WHO prequalified and used in procurement for public health programmes.
Practical Note For Patients: Atripla simplifies adherence as a single daily tablet, while generic efavirenz and separate NRTIs may require multiple tablets and affect dispensing under PBS rules.
Contraindications And Special Precautions
Safety questions are among the most important; patients want clear do’s and don’ts.
Absolute Contraindications Include Known Hypersensitivity To Efavirenz And Severe Hepatic Impairment.
Certain Co‑Medications Are Contraindicated, Including Voriconazole, Elbasvir/Grazoprevir, St John’s Wort, Some Benzodiazepines And Ergot Derivatives.
Relative Precautions Include A History Of Psychiatric Illness, Seizure Disorders, Moderate Hepatic Dysfunction And Pregnancy Considerations.
Women Of Child‑Bearing Potential Should Be Counseled Carefully Because Efavirenz Is AU Pregnancy Category D And Has Documented Teratogenicity Concerns.
- Workplace And Occupational Safety: Dizziness, impaired concentration and other CNS effects may make driving or operating machinery unsafe during early treatment.
- Monitoring Checklist: Baseline liver function tests, mental‑health screening, and pregnancy test where applicable, with regular follow‑up.
For complex interaction checks and dosing in hepatic disease, consult TGA guidance and specialist advice before initiating therapy.
Dosage Guidelines
Common dosing questions focus on timing, paediatric bands and missed doses.
Standard Adult Dose: 600 mg orally once daily, preferably with or after food to aid absorption.
WHO Defined Daily Dose: 0.6 g per day (600 mg).
Paediatric Dosing: Weight‑band based; for example, children ≥35 kg may receive 600 mg once daily while lower weights use 200 mg/300 mg tablets or 50 mg capsules.
| Patient Group | Typical Dose | Storage |
|---|---|---|
| Adults | 600 mg once daily with/after food | Store below 30°C; protect from moisture and light |
| Children | Weight‑band dosing; ≥35 kg: 600 mg once daily | Store as above |
| PEP | Used in combination regimens for 28 days | Store as above |
- Take At The Same Time Each Day To Reduce CNS Effects.
- If You Miss A Dose, Take It As Soon As You Remember Unless It Is Near The Next Dose — Do Not Double Up.
- Overdose Management Is Supportive; Activated Charcoal May Be Considered For Recent Ingestions.
No renal dose adjustment is required for mild to moderate impairment, and avoid use in moderate–severe hepatic impairment.
Interactions Overview
Patients often worry whether their other medicines or supplements will mix badly with efavirenz.
Efavirenz Is A Potent Modulator Of Cytochrome P450 Enzymes And Has Clinically Significant Interactions.
Absolute Contraindications Include Concurrent Use Of Voriconazole, Elbasvir/Grazoprevir, St John’s Wort, Some Benzodiazepines And Ergot Alkaloids.
| Drug/Class | Interaction Effect And Recommended Action |
|---|---|
| St John’s Wort | Reduces efavirenz concentrations and is contraindicated; stop supplement before starting efavirenz. |
| Hormonal Contraceptives | Efavirenz may reduce contraceptive efficacy; advise reliable contraception and discuss alternatives. |
| Methadone | Efavirenz can lower methadone levels; consider dose adjustment and clinical monitoring. |
| Antipsychotics / Certain Sedatives | Variable interactions; review individual agents for dose changes or alternatives. |
Food increases absorption, so advise taking efavirenz with or after food while warning that concurrent alcohol and liver disease increase hepatic risk.
Clinicians should check TGA safety bulletins and e‑health medicines information at the point of prescribing for up‑to‑date interaction data.
Cultural Perceptions And Patient Habits
People frequently ask how others experience efavirenz and whether cultural or geographic factors change prescribing.
Many Australian patients value once‑daily, single‑tablet regimens such as Atripla for convenience and adherence.
Patient forums and peer support groups report high awareness of CNS side effects and a preference trend towards dolutegravir for tolerability.
Rural And Indigenous Health Contexts: Simple single‑tablet regimens can be attractive where specialist access is limited, but culturally safe counselling and closer monitoring for neuropsychiatric effects are essential.
| Setting | Access Issues |
|---|---|
| Urban | Specialist clinics and pharmacies readily available; switching to integrase inhibitors more common. |
| Rural | Telehealth improves access but stock variability and fewer specialists make fixed‑dose, once‑daily options attractive. |
- Pharmacists At Chains Such As Chemist Warehouse, Priceline And TerryWhite Chemmart Are Trusted Advisors On Cost And PBS Options.
- Patients Frequently Ask About Generics, PBS Coverage And Single‑Tablet Options Like Atripla.
Telehealth and e‑prescriptions have improved access for regional patients, although periodic stock substitutions can affect continuity of supply.
Availability And Pricing Patterns
One of the first questions is whether efavirenz is subsidised and where to buy it locally.
Supply In Australia Includes Branded Products Such As Stocrin And Atripla And Generic Supply From Global Manufacturers.
Major Retail Chains And Accredited Online Pharmacies Dispense Efavirenz With A Valid Prescription Under PBS Rules.
| Channel | Typical Pricing / Notes |
|---|---|
| PBS Dispensing | Subsidised with authority requirements for some items; co‑payments apply. |
| Private / Imported Generics | Private prices vary widely; patients may inquire about lower‑cost options. |
| Online Pharmacy | Telehealth e‑prescriptions and courier services available; delivery times may affect continuity. |
Clinics and procurement teams often prefer WHO prequalified generics and PBS‑listed products to ensure stable supply for patients.
Pharmacists Should Advise Patients About PBS Authority Requirements, Co‑Payments And Possible Stock Substitutions.
Practical Note: In our online pharmacy, efavirenz is available with discreet delivery to Australia in 5‑14 days.
Comparable Medicines And Preferences
Patients commonly ask whether they should switch from efavirenz to a newer agent.
Alternatives Used In Australia Include Integrase Inhibitors Like Dolutegravir And Other NNRTIs Such As Rilpivirine And Nevirapine.
Compared With Efavirenz, Dolutegravir Offers Fewer CNS Effects, A Higher Resistance Barrier And Faster Viral Suppression.
Efavirenz Advantages Include Extensive Clinical Experience, Once‑Daily Dosing And Low Cost In Some Procurement Settings.
| Drug | Pros | Cons |
|---|---|---|
| Efavirenz | Once‑daily dosing, long clinical history, fixed‑dose options (Atripla) | CNS side effects, pregnancy precautions, many drug interactions |
| Dolutegravir | Better tolerability, rapid suppression, higher resistance barrier | Cost and procurement considerations in some settings |
| Rilpivirine | Well tolerated for some patients | Not suitable for high viral loads; interaction profile differs |
Clinical Decision Factors Include Psychiatric History, Pregnancy Potential, Liver Disease, Co‑Medications And PBS Availability.
For PEP, guideline‑preferred regimens may favour better‑tolerated drugs, but efavirenz combinations remain an option where required.
Frequently Asked Questions
Q1: Can I take efavirenz in pregnancy?
A: Efavirenz is AU pregnancy category D and is generally avoided in pregnancy where possible.
Contraception Counselling Steps: confirm effective contraception, document counselling, discuss alternative regimens for women planning pregnancy.
Q2: Will efavirenz affect my driving?
A: Yes — dizziness, impaired concentration and vivid dreams are common early effects; advise avoiding driving or heavy machinery until symptoms settle.
Q3: How does PBS cover efavirenz and Atripla?
A: Many efavirenz formulations and Atripla have PBS listings; patients should ask prescribers and pharmacists about authority scripts and co‑payment obligations.
Q4: What if I miss a dose?
A: Take the missed dose as soon as you remember unless it is close to the next scheduled dose; do not double the dose.
Emergency Advice: Seek urgent care for significant overdose, particularly with severe CNS disturbance where supportive care may be required.
Guidelines For Proper Use
Pharmacists and prescribers should counsel patients in a patient‑centred way and document discussions in clinical records.
Explain That Efavirenz Must Always Be Used In Combination Therapy And Never As Monotherapy.
Set Expectations For Side Effects — CNS Symptoms Often Begin Within Days And May Subside Over 2–4 Weeks.
- Practical Counselling Checklist: confirm contraception, baseline liver function tests, mental‑health screen and pregnancy testing where relevant.
- Advice On Administration: take with or after food, take at the same time each day and warn about important interactions such as St John’s Wort and certain sedatives.
For Rural Patients, Arrange Telehealth Follow‑Ups And Coordinate With Local Pharmacies To Ensure Continuity Of Supply.
Use Adherence Aids Such As Dose Reminders, Blister Packs And Document Counselling For Future Reference.
Cross‑Reference PBS Guidance And TGA Safety Notices For The Most Up‑To‑Date Recommendations Before Initiating Or Switching Therapy.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Darwin | Northern Territory | 5-9 days |
| Gold Coast | Queensland | 5-9 days |
| Newcastle | New South Wales | 5-9 days |
| Wollongong | New South Wales | 5-9 days |
| Geelong | Victoria | 5-9 days |
| Cairns | Queensland | 5-9 days |
Final Practical Notes
Efavirenz remains a valuable antiretroviral option where its once‑daily dosing, fixed‑dose combination availability and cost advantages are important.
Careful patient selection, baseline screening and counselling about CNS adverse effects and interactions will improve tolerability and adherence.
Pharmacists should document counselling, check PBS authority requirements and liaise with prescribers when considering switches to integrase inhibitor regimens such as dolutegravir.
If further product‑specific questions arise, consult the TGA‑registered product information and national guidelines for detailed prescribing and monitoring requirements.