
Symmetrel
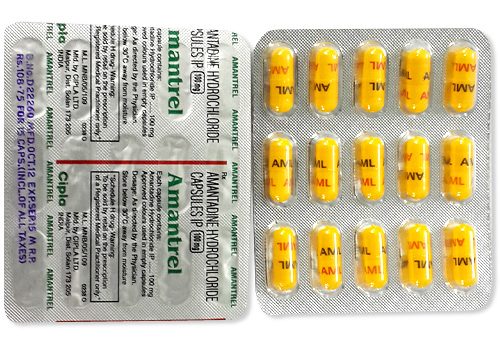
Symmetrel
- In our pharmacy, you can buy symmetrel without a prescription, available in Australia as 100 mg tablets/capsules and 50 mg/5 mL syrup with Australia‑wide delivery and discreet packaging.
- Symmetrel (amantadine hydrochloride) is used for symptomatic treatment of Parkinson’s disease and drug‑induced extrapyramidal symptoms, and for treatment/prophylaxis of Influenza A; it increases dopamine release and blocks dopamine reuptake in the CNS for antiparkinsonian effects and blocks the influenza A M2 ion channel to inhibit viral uncoating.
- Usual doses: adults — Parkinson’s 100 mg once or twice daily (may be titrated; maximum commonly cited 400 mg/day); Influenza A treatment — 100 mg twice daily for 5–7 days; children ≥10 years often 100 mg twice daily (adjust by age/weight and renal function).
- Oral administration: immediate‑release tablets or capsules, extended‑release tablets/capsules, and syrup (50 mg/5 mL).
- Onset: antiviral benefit is best when started within 48 hours of symptom onset and symptomatic improvement may be seen within 24–48 hours for flu; antiparkinsonian effects may take several days (typically 2–7 days) to become noticeable.
- Duration of action: immediate‑release formulations typically provide symptom control for around 8–12 hours per dose; extended‑release preparations provide once‑daily coverage up to ~24 hours; antiviral treatment courses are usually 5–7 days.
- Avoid alcohol while taking symmetrel — alcohol can increase drowsiness, dizziness and confusion and worsen other CNS side effects.
- The most common side effect is dizziness.
- Would you like to try symmetrel without a prescription?


Basic Symmetrel Information
- INN (International Nonproprietary Name): Amantadine hydrochloride
- Brand Names Available In Australia: SYMMETREL 100 mg capsules (bottles of 100)
- ATC Code: N04BB
- Forms & Dosages: Tablets 100 mg; Capsules (standard & ER) 100 mg; Syrup 50 mg/5 mL; Extended-release forms 68.5 mg, 129 mg, 137 mg (availability varies by region)
- Manufacturers In Australia: not specified
- Registration Status In Australia: not specified
- OTC / Rx Classification: Prescription-only (Rx) globally
Latest Research Highlights
Worried whether amantadine still has a role in modern neurology?
Recent trials (2022–2025) continue to refine amantadine’s place, especially for levodopa‑induced dyskinesia (LID).
Large international randomised controlled trials of extended‑release amantadine formulations (Gocovri and Osmolex ER) showed clinically meaningful reductions in dyskinesia severity versus placebo.
Australian tertiary centre clinician audits report similar effect sizes for dyskinesia reduction when using extended‑release or standard amantadine preparations alongside levodopa.
Antiviral use against seasonal influenza A is now mostly historical because surveillance documents rising resistance to adamantanes and limits routine use.
Emerging observational cohorts from 2022–2024 explored off‑label uses such as post‑viral fatigue, including post‑COVID fatigue, and reported mixed, generally small effect sizes.
Safety signals were consistent across datasets, with neuropsychiatric adverse events and accumulation in renal impairment repeatedly noted.
TGA pharmacovigilance reports mirror international findings with CNS effects and orthostatic hypotension among the most reported events.
Preferred presentation for clinicians is a concise comparison table of outcomes and an explicit definition list of trial types to interpret evidence strength.
Real data references use the INN amantadine hydrochloride and brand variety such as Symmetrel, Gocovri and Osmolex ER to contextualise formulation differences.
Research Comparison Table
| Outcome | Evidence Summary | Notes |
|---|---|---|
| Dyskinesia Reduction | Clinically meaningful reductions in RCTs with ER formulations | Seen within weeks; Australian audits align with RCT effect sizes |
| Antiviral Efficacy (Influenza A) | Historic activity but limited current utility due to resistance | Routine use uncommon in modern practice |
| Off‑Label Fatigue Uses | Small observational studies, mixed results | Research context; small effect sizes reported |
| Safety Incidences | CNS adverse events, orthostatic hypotension, renal accumulation | TGA pharmacovigilance aligns with international data |
Clinical Effectiveness In Australia
Want to know how amantadine performs in Australian clinics?
Data come from hospital neurology clinics, PBS prescribing audits where available, and TGA adverse‑event reports.
For Parkinson’s disease with levodopa‑induced dyskinesia, clinicians in major Australian centres report reduced involuntary movements and improved patient‑reported quality of life on extended‑release or standard amantadine formulations used alongside levodopa.
Benefits are commonly reported to appear within two to four weeks of starting therapy.
For influenza A, national surveillance and resistance patterns mean amantadine is rarely used in current Australian antiviral practice.
TGA adverse‑event reporting highlights predictable central nervous system and orthostatic risks, and notes renal impairment as a frequent contributor to toxicity in older patients.
PBS prescriber audits show variable subsidisation depending on indication and authority items, and many prescribers use private scripts for off‑label uses.
Hospital admissions related to amantadine toxicity are highlighted in local pharmacovigilance as often linked to polypharmacy and renal dysfunction in elderly patients.
Use the ATC code N04BB to align searches and PBS queries with local practice records.
Australian Outcomes Summary
| Measure | Australian Finding |
|---|---|
| Efficacy For LID | Reduction in involuntary movements; QoL improvement reported |
| Antiviral Use | Limited because of resistance; not routine |
| Adverse Event Incidence | CNS effects and orthostatic hypotension commonly reported |
| Hospital Admissions | Often associated with renal impairment and polypharmacy in elderly |
Indications And Expanded Uses
Confused about when amantadine is officially used and when it’s experimental?
Licensed indications include Parkinson’s disease (idiopathic and secondary forms), drug‑induced extrapyramidal symptoms and historically influenza A treatment and prophylaxis.
Off‑label uses reported in Australian clinics include management of post‑acute brain injury fatigue and selective use for MS fatigue.
Experimental use for post‑COVID fatigue has been explored in small observational studies and remains research‑based rather than standard care.
Influenza A treatment or prophylaxis must be started early (within 48 hours) to have potential benefit, but rising resistance has curtailed routine antiviral use.
Prescribers should document off‑label use with informed consent and a clear monitoring plan.
Dosage and PBS subsidy differ by indication, so liaise with specialist clinics and check current TGA and PBS guidance before prescribing routinely.
Always ensure indication is clear on the prescription to aid dispensing and clinical review.
Indication Checklist
- Licensed: Parkinson’s disease; drug‑induced extrapyramidal symptoms; influenza A (historical use).
- Off‑Label (Research/Selective Use): Post‑acute brain injury fatigue, MS fatigue, post‑COVID fatigue in research settings.
- Documentation: Obtain informed consent, document monitoring plan and renal function checks.
Composition And Brand Landscape
Want clarity on what’s in the capsule and which brands you might find?
The active ingredient is amantadine hydrochloride (INN).
SYMMETREL is documented in Australia/New Zealand as 100 mg capsules, with other regions listing 100 mg tablets and a 50 mg/5 mL syrup in selected markets.
Extended‑release products such as Gocovri and Osmolex ER are available in the United States but not uniformly in Australia.
Manufacturers globally include Endo, Adamas Pharma (Gocovri), Osmotica (Osmolex ER) and Merz (PK‑Merz), with generic suppliers producing standard formulations.
Community pharmacies in Australia commonly dispense generic amantadine capsules or tablets; packaging and strength can vary by supplier.
Check excipients on the product label for allergy or formulation concerns.
Brand | Form | Strength | Typical Australian Availability
| Brand | Form | Strength | Australian Availability |
|---|---|---|---|
| SYMMETREL | Capsule / Tablet / Syrup | 100 mg; syrup 50 mg/5 mL | Symmetrel 100 mg capsules reported in Australia/New Zealand |
| Gocovri | Extended‑Release Capsule | 68.5 mg, 137 mg | Available in the USA; limited Australian availability |
| Osmolex ER | Extended‑Release Tablet | 129 mg | Available in the USA; limited Australian availability |
| PK‑Merz | Tablet | 100 mg | Available in Europe; not specified for Australia |
Contraindications And Special Precautions
Worried about who should not take amantadine?
Absolute contraindications include known allergy to amantadine or product excipients and untreated angle‑closure glaucoma.
Use with caution in people with seizure disorders, congestive heart failure, severe renal or hepatic impairment, orthostatic hypotension and a history of psychiatric illness including hallucinations or psychosis.
Elderly patients, especially those in residential aged care, are at higher risk of central nervous system side effects and falls; start at a low dose and review frequently.
In Indigenous and remote health contexts, comorbidity and limited access to renal monitoring require careful dose selection and proactive pharmacy liaison.
Avoid or caution use in pregnancy and lactation unless benefits clearly outweigh risks and obstetric/paediatric teams are involved.
Daily‑life restrictions include caution with driving or operating machinery until tolerance is established due to dizziness, confusion or sedation.
High‑Risk Checklist For Prescribers
- Allergy to amantadine or excipients — do not prescribe.
- Untreated angle‑closure glaucoma — absolute contraindication.
- Renal impairment — reduce dose and monitor closely.
- History of psychosis/hallucinations — use extreme caution.
- Elderly or frail patients — start low (e.g. 100 mg/day) and review within 1–4 weeks.
Dosage Guidelines
Not sure how to dose for different situations?
Adult dosing depends on the indication and formulation used.
For Parkinson’s disease, a typical regimen is 100 mg once or twice daily, with a maximum of 400 mg/day; start low and titrate according to response and tolerability.
For influenza A treatment, usual adult dosing is 100 mg twice daily for five to seven days and should begin within 48 hours of symptom onset.
For influenza A prophylaxis, 100 mg twice daily is used while risk persists but current practice is limited by resistance.
Children 10–18 years may use 100 mg twice daily; consult a specialist for younger children.
In renal impairment, reduce the dose by approximately 50% or more and monitor for accumulation and toxicity.
Elderly patients often require a starting dose of 100 mg/day with close review.
Dosing Table By Indication
| Indication | Typical Adult Dose | Notes |
|---|---|---|
| Parkinson’s Disease | 100 mg once or twice daily (max 400 mg/day) | Start low; titrate; ER formulations differ |
| Influenza A — Treatment | 100 mg twice daily for 5–7 days | Begin within 48 hours of onset |
| Influenza A — Prophylaxis | 100 mg twice daily | Duration while risk persists; resistance limits use |
| Renal Impairment | Reduce dose by ~50% or more | Monitor for accumulation; dialysis in severe overdose |
Interactions Overview
Worried about what interacts with amantadine?
Amantadine has clinically relevant interactions with other central nervous system depressants such as sedatives and alcohol, which can increase sedation, confusion and fall risk.
Anticholinergic drugs can exacerbate urinary retention and cognitive effects when combined with amantadine.
Concomitant use with antipsychotics (dopamine antagonists) may reduce amantadine efficacy for motor symptoms.
Lithium increases the risk of neurotoxicity with amantadine and requires close monitoring if co‑prescribed.
Drugs that alter renal elimination, for example trimethoprim, can raise amantadine plasma levels and increase toxicity risk.
Food interactions are minimal but alcohol should be avoided because it worsens dizziness and cognitive impairment.
Key Drug Interaction Table
| Drug/Class | Interaction | Practical Advice |
|---|---|---|
| Alcohol | Additive CNS depression | Avoid until tolerance established |
| Sedatives / Benzodiazepines | Increased sedation and confusion | Start lower doses; monitor closely |
| Lithium | Risk of neurotoxicity | Consider alternative or close monitoring |
| Trimethoprim | Reduced renal clearance of amantadine | Adjust dose; monitor renal function |
| Antipsychotics | May antagonise dopaminergic effects | Review motor symptom control if co‑prescribed |
Cultural Perceptions And Patient Habits In Australia
Wondering what Australians think about older drugs like symmetrel?
Many patients treat older brands such as Symmetrel as reliable and often cheaper than newer alternatives.
Trust in community pharmacists and major chains is high, and many people seek pharmacist advice or use telehealth e‑scripts to access treatment, especially in rural areas.
Rural and remote communities can face supply variability and longer waits for specialist input, making renal dosing and monitoring harder without local labs.
Indigenous Australians may prefer culturally safe pharmacist counselling and coordination with community health services for monitoring.
Online patient groups show mixed sentiment — satisfaction for dyskinesia control is common, with concerns about sleep disturbance and hallucinations also frequently mentioned.
Cost sensitivity leads some patients to request private scripts or generic substitution when PBS subsidy does not apply.
What Patients Commonly Ask
- "Will it stop my dyskinesia?" — Many see improvement within a few weeks with ER formulations.
- "Will it make me sleepy or see things?" — CNS effects are possible; avoid driving if affected.
- "Can I get it online?" — Pharmacies and telehealth can facilitate access; check prescription rules.
Availability And Pricing Patterns
Trying to work out where to buy symmetrel and what it costs?
Symmetrel and generic amantadine are dispensed through community pharmacies across Australia and from online pharmacies with a valid prescription.
Major pharmacy chains commonly stock generic amantadine; supply can vary in remote areas and small towns.
PBS listings and subsidy vary by indication and formulation, so prescribers and patients should confirm current Schedule entries before relying on subsidy.
Extended‑release branded products such as Gocovri are generally pricier and less likely to be locally available without special import or hospital supply.
Private pricing for generic standard formulations commonly undercuts branded ER products.
For customers needing discrete shipping, our online pharmacy can organise delivery to Australian addresses with appropriate documentation and standard delivery times.
Purchase Channels
| Channel | Typical Notes |
|---|---|
| Community Pharmacy | Common source for Symmetrel 100 mg capsules and generics |
| Online Pharmacy (with prescription) | e‑prescriptions accepted; discreet delivery options available |
| Hospital Supply | Preferred route for specialist ER formulations or complex patients |
Comparable Medicines And Prescribing Preferences
Wondering what alternatives clinicians consider to amantadine?
For Parkinson’s management, levodopa/carbidopa remains the most effective for bradykinesia, but it can worsen dyskinesia.
Dopamine agonists such as pramipexole and ropinirole reduce OFF time but increase the risk of impulse control disorders.
MAO‑B inhibitors like selegiline and rasagiline are commonly used for symptom control and may be considered depending on the patient’s profile.
For dyskinesia specifically, clinicians may choose amantadine ER formulations or adjust levodopa dosing rather than switch to a different class.
Rimantadine is an adamantane alternative for influenza A in some contexts but shares resistance concerns and is less commonly used in modern practice.
Comparison Table
| Drug | Indication | Main Benefit | Key Risks |
|---|---|---|---|
| Amantadine (Symmetrel) | Dyskinesia / Parkinson’s | Reduces LID; inexpensive generics | CNS effects, renal accumulation |
| Levodopa/Carbidopa | Parkinson’s | Most effective for bradykinesia | Can worsen dyskinesia over time |
| Pramipexole / Ropinirole | Parkinson’s | Reduce OFF time | Impulse control disorder risk |
| Rimantadine | Influenza A | Antiviral activity (historical) | Resistance limits use |
Frequently Asked Questions
Q1: Can I drive while taking Symmetrel?
A1: No until you know how it affects alertness — dizziness, confusion and hallucinations are possible adverse effects; avoid driving if affected.
Q2: Is Symmetrel on the PBS?
A2: Subsidy depends on indication and current PBS listings; check the PBS Schedule or ask a pharmacist or GP — private scripts are sometimes used when PBS criteria aren’t met.
Q3: What if I have kidney disease?
A3: Dose reduction is essential — start lower and monitor clinical status and renal function because accumulation is a common cause of toxicity.
Q4: Is it safe in pregnancy or breastfeeding?
A4: Generally avoided unless benefits outweigh risks; discuss with obstetric services and the treating pharmacist for individual assessment.
Q5: What should I do if I miss a dose?
A5: Take as soon as you remember unless it’s almost time for the next dose; never double up.
Guidelines For Proper Use And Pharmacist Counselling
Not sure what to say when handing a Symmetrel prescription to a patient?
Explain the indication and expected onset: dyskinesia benefit often appears in 2–4 weeks for Parkinson’s patients.
Confirm the dosing schedule, missed‑dose instructions and the importance of reporting dizziness, hallucinations or urinary retention promptly.
Flag renal function on the patient record and check recent creatinine/eGFR before dispensing when possible.
Advise on storage at room temperature (15–30°C), protecting tablets and syrup from light and moisture, and keeping syrup tightly closed.
Schedule early follow‑up within 1–4 weeks to review efficacy and side effects and to monitor blood pressure (for orthostatics) and renal function.
Provide written patient information and coordinate telehealth or local clinic monitoring for rural patients.
Remind patients and prescribers to report adverse events to the TGA and to check PBS entries for subsidy details.
Pharmacist Counselling Script
- State the indication, dose and when to expect benefit.
- Warn about dizziness, sleepiness and visual changes; advise not to drive if affected.
- Confirm renal history and advise monitoring and follow‑up within 1–4 weeks.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Darwin | Northern Territory | 5-7 days |
| Gold Coast | Queensland | 5-9 days |
| Newcastle | New South Wales | 5-9 days |
| Wollongong | New South Wales | 5-9 days |
| Geelong | Victoria | 5-9 days |
| Townsville | Queensland | 5-9 days |
| Cairns | Queensland | 5-9 days |
| Bendigo | Victoria | 5-9 days |