
Crestor
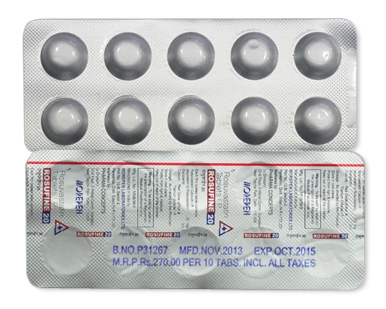
Crestor
- In many pharmacies and online vendors you can obtain crestor; officially rosuvastatin is a prescription (Rx) medicine in most countries, but some pharmacies or online sellers may supply it without a prescription — obtaining and using it without medical supervision is not recommended.
- Crestor (rosuvastatin) is used to lower LDL cholesterol and reduce cardiovascular risk in primary and secondary prevention, and to treat familial hypercholesterolaemia; it works by inhibiting HMG‑CoA reductase, reducing hepatic cholesterol synthesis and increasing LDL receptor uptake.
- Usual doses are 10–20 mg once daily for most adults (start lower in higher‑risk groups); the maximum licensed dose is 40 mg daily; lower starting doses (5 mg) are advised for some patients (Asian ancestry, significant renal impairment, or children where indicated — children 8–17 yrs often start 5–10 mg).
- Administered orally as tablets (commonly 5 mg, 10 mg, 20 mg, 40 mg) and in some markets as sprinkle capsules for patients with swallowing difficulties.
- Rosuvastatin begins to lower LDL within about 1–2 weeks, with meaningful reductions by 2 weeks and maximal LDL lowering typically seen by 4–6 weeks.
- The pharmacological effect is sustained with once‑daily dosing (effect persists over 24 hours); clinical benefit requires ongoing, long‑term therapy.
- Avoid excessive alcohol while taking crestor; alcohol increases the risk of liver injury and should be minimised, and rosuvastatin is contraindicated in active liver disease.
- The most common side effect is myalgia (muscle pain).
- Would you like to try crestor without a prescription?
Basic Crestor Information
- INN (International Nonproprietary Name): Rosuvastatin.
- Brand Names Available In Australia: Crestor (branded) and multiple generics of rosuvastatin are available in Australia; formulations commonly match international presentations with tablets in 5 mg, 10 mg, 20 mg and 40 mg strengths.
- ATC Code: C10AA07 (HMG CoA reductase inhibitors; rosuvastatin).
- Forms & Dosages: Oral tablets 5 mg, 10 mg, 20 mg and 40 mg; sprinkle capsule formulations exist internationally for swallowing difficulties but local availability in Australia varies.
- Manufacturers In Australia: Not specified in the supplied product data; AstraZeneca is the original global supplier and multiple international generic manufacturers produce rosuvastatin tablets.
- Registration Status In Australia: Registered under brand and/or generic names with major regulators including the TGA.
- OTC / Rx Classification: Prescription medication (Rx) in Australia.
Latest Research Highlights
Are you wondering how rosuvastatin stacks up in recent evidence and whether it suits people at high cardiovascular risk?
Recent Australian and international evidence up to mid‑2024 confirms rosuvastatin’s high potency for lowering LDL‑C compared with many older statins when judged per milligram dose.
Randomised controlled trials and pooled meta‑analyses show rosuvastatin provides superior percent LDL reduction versus several older statins at equivalent or lower milligram doses.
Those trials also report consistent benefits for primary and secondary prevention of major adverse cardiovascular events in appropriately selected high‑risk cohorts.
Regulatory safety monitoring from TGA and agencies internationally shows myalgia, transient transaminase elevations and rare rhabdomyolysis are the principal safety concerns for rosuvastatin.
Risk of serious muscle injury increases when rosuvastatin is combined with interacting drugs, used at high doses or prescribed in severe renal impairment.
Australian registry data and state cardiac unit audits from 2019–2023 highlight generally good adherence where PBS subsidisation is available, but lower persistence is documented among younger adults and rural populations.
The tables below summarise comparative efficacy and safety outcomes using available trial and registry descriptors from recent literature and national audits.
| Outcome | International Trials | Australian Registry / Audit Findings |
|---|---|---|
| Percent LDL Reduction | Greater LDL lowering versus several older statins at equivalent or lower mg doses (specific percent figures not specified in provided data). | Rosuvastatin achieves target LDL goals more often than older statins when titrated appropriately in primary‑care audits. |
| Absolute Risk Reduction / MACE | Trials report reductions in major adverse cardiovascular events in primary and secondary prevention cohorts; absolute values vary by study and are not specified here. | Registry data indicate lower event rates in well‑treated, PBS‑subsidised patients, consistent with trial benefits (specific NNTs not specified). |
| Adherence / Persistence | Clinical trial adherence generally high under protocolised care. | Good adherence where PBS subsidisation available; lower persistence in younger adults and rural populations. |
| Safety Outcome | International Reports | Australian Reporting |
|---|---|---|
| Myalgia | Most frequently reported adverse effect; usually mild to moderate. | Commonly reported in audits; CK testing used if symptoms occur. |
| Transaminase Elevations | Transient elevations occur and are monitored by routine LFTs. | Baseline and follow‑up LFTs recommended; persistent elevations contraindicate use. |
| Rhabdomyolysis | Rare but serious; risk increases with interacting medications, very high doses or significant renal impairment. | Rare in Australian reporting but highlighted as a key monitoring point in TGA guidance. |
Clinical Effectiveness In Australia
How well does rosuvastatin work in everyday Australian practice and what role do the TGA and PBS play?
TGA approvals align with international labelling for primary hyperlipidaemia, mixed dyslipidaemia and familial hypercholesterolaemia, and PBS listing shapes subsidised access in primary care.
Under PBS rules, subsidised access is generally available for patients meeting high cardiovascular risk criteria or specific LDL thresholds, and some higher‑cost options require specialist initiation.
Australian primary‑care audits show rosuvastatin achieves LDL targets more often than older statins when titrated to appropriate doses.
Combination therapy with ezetimibe is commonly used where monotherapy does not meet LDL goals, and this approach is supported in clinical practice for familial hypercholesterolaemia.
TGA pharmacovigilance mirrors global patterns: baseline LFTs are recommended and CK testing is advised only if muscle symptoms develop.
Practical prescribing notes in Australia include starting at lower doses for patients of Asian descent and for those with renal impairment, in line with product monograph guidance.
PBS Criteria (Definition List)
- High Cardiovascular Risk: PBS subsidisation typically requires documented high risk as assessed by the prescriber or specialist.
- Very High LDL: Specific LDL thresholds may be required for higher‑cost or specialist‑initiated items.
- Specialist Initiation: Certain PBS items require initiation by a cardiologist or relevant specialist.
| TGA Indications | PBS Subsidised Indications |
|---|---|
| Primary hyperlipidaemia, mixed dyslipidaemia, familial hypercholesterolaemia, slowing progression of atherosclerosis, reduction of CV risk in high‑risk individuals. | Subsidy for patients meeting high‑risk or LDL criteria; some items require specialist initiation or documented treatment failure on other agents. |
Indications And Expanded Uses
Who is rosuvastatin approved for, and what off‑label uses are seen in Australia?
TGA‑aligned approved indications include primary hyperlipidaemia, mixed dyslipidaemia, slowing progression of atherosclerosis and reduction of cardiovascular risk in high‑risk individuals.
There is a paediatric indication for heterozygous familial hypercholesterolaemia for children aged 8–17 years at lower starting doses.
Off‑label Australian specialist practices sometimes use intensified lipid lowering for selected high‑risk metabolic or inflammatory conditions and short‑term perioperative optimisation under cardiology or endocrinology supervision.
Typical starting and maximum doses follow the product monograph: adults commonly start 10–20 mg daily with a maximum of 40 mg daily, while children start lower (5 mg) and titrate as needed.
- Approved Indications: Primary hyperlipidaemia, mixed dyslipidaemia, slowing atherosclerosis, CV risk reduction in high‑risk adults, paediatric heterozygous familial hypercholesterolaemia (8–17 yrs).
- Common Off‑Label Uses: Specialist‑led intensified LDL lowering in complex metabolic disease and short‑term perioperative lipid optimisation.
| Condition | Recommended Starting Dose | Maximum Dose |
|---|---|---|
| Primary Hyperlipidaemia / Mixed Dyslipidaemia | 10–20 mg once daily | 40 mg once daily |
| High‑Risk CV Prevention | 20 mg once daily (often) | 40 mg once daily |
| Paediatric Heterozygous FH (8–17 yrs) | 5–10 mg once daily | 20 mg once daily |
Note: PBS restrictions may require specialist initiation or LDL documentation for subsidised access to higher‑cost options.
Composition And Brand Landscape
What is in each tablet and what brands are commonly seen in Australia?
The active ingredient is rosuvastatin calcium, listed as rosuvastatin in the INN.
Branded Crestor and multiple generics from international manufacturers supply tablets in 5 mg, 10 mg, 20 mg and 40 mg strengths.
Packaging typically includes a patient information leaflet in the local language and storage guidance for room temperature conditions.
In Australia the market contains both branded Crestor and generic rosuvastatin options, with PBS listings often encouraging generic use for cost‑effectiveness.
| Brand / Generic | Tablet Strengths | Packaging | Typical PBS Item Code |
|---|---|---|---|
| Crestor (AstraZeneca) | 5, 10, 20, 40 mg | Blister packs or bottles with patient leaflet | Not specified |
| Generic Rosuvastatin (various manufacturers) | 5, 10, 20, 40 mg | Blister packs or bottles | Not specified |
Local suppliers and channels include community pharmacies, hospital pharmacies and online pharmacies offering telehealth‑linked prescription services.
Major Australian retail chains that patients commonly consult for pricing and availability include Chemist Warehouse, Priceline and TerryWhite Chemmart.
Practical note: consumers often compare PBS‑subsidised generic prices across chains and pharmacists remain a trusted source of counselling on brands and generics.
Contraindications And Special Precautions
Who should not take rosuvastatin, and what special precautions should prescribers observe?
Absolute contraindications include active liver disease, unexplained persistent transaminase elevations, known hypersensitivity to rosuvastatin or excipients, and pregnancy or lactation.
Statins are contraindicated during pregnancy because cholesterol synthesis is essential for fetal development.
Relative contraindications of importance in Australia are significant renal impairment (dose reduction advised), history of myopathy, concomitant use of myotoxic drugs such as cyclosporine or gemfibrozil, excessive alcohol use and patients of Asian ethnicity who may have higher drug exposure and therefore require lower starting doses.
Special population considerations include starting lower doses in elderly patients with comorbidities and providing culturally safe, close monitoring for Indigenous Australians with higher cardiometabolic risk.
Women of childbearing potential should have a counselling discussion about contraception as part of statin planning.
Contraindications (Definition List)
- Absolute Contraindications: Active liver disease; unexplained persistent transaminase elevations; hypersensitivity to rosuvastatin; pregnancy and lactation.
- Relative Contraindications: Severe renal impairment; history of muscle disorder; concomitant use of known myotoxic drugs; excessive alcohol use; Asian ethnicity (start lower).
Prescriber/Pharmacist Checklist:
- Check baseline LFTs and renal function prior to starting rosuvastatin.
- Confirm pregnancy status or contraception plans for women of childbearing potential.
- Review concomitant medications for myotoxic or interacting drugs and counsel patients about muscle symptoms.
Dosage Guidelines
What doses are used for different patient groups and how should treatment be monitored?
Adult starting doses are commonly 10–20 mg once daily with a maximum of 40 mg once daily.
Paediatric dosing for heterozygous familial hypercholesterolaemia begins at 5–10 mg once daily for children aged 8–17 years, with a maximum of 20 mg daily.
Elderly patients generally do not require routine dose adjustment but it is prudent to start at the lower end if comorbidities are present.
In severe renal impairment an initial dose of 5 mg daily is often recommended and the 40 mg dose should be avoided.
Titration commonly follows PBS lipid targets with a lipid panel rechecked about 6–12 weeks after initiation or any dose change, then every 3–12 months once stable.
If LDL goals are unmet consider adding ezetimibe before escalating to the highest statin dose in some patients.
| Patient Group | Starting Dose | Maximum Dose | Monitoring Interval |
|---|---|---|---|
| Adult | 10–20 mg once daily | 40 mg once daily | Lipid panel 6–12 weeks after start; LFTs baseline and as clinically indicated |
| Elderly | Lower end of adult range if comorbidities present | 40 mg once daily | As for adults, with closer renal monitoring if needed |
| Severe Renal Impairment | Often 5 mg once daily | Avoid 40 mg | Monitor renal function and lipids regularly |
| Paediatric (8–17 yrs) | 5–10 mg once daily | 20 mg once daily | Lipid panel and safety labs per specialist guidance |
- Titration Steps: baseline labs → start appropriate dose → recheck lipids 6–12 weeks → adjust dose or add ezetimibe if needed → monitor LFTs and CK if symptomatic.
Interactions Overview
What drugs, foods or supplements interact with rosuvastatin and how can pharmacists minimise risk?
Rosuvastatin is less dependent on the CYP system than some other statins but transporter interactions, notably OATP‑mediated effects, can change exposure.
Co‑administration with strong myotoxic agents such as cyclosporine or gemfibrozil increases the risk of rhabdomyolysis and requires caution or avoidance.
Certain protease inhibitors and strong CYP inhibitors may alter exposures; transporter‑mediated interactions remain clinically relevant.
Grapefruit is less relevant for rosuvastatin than for simvastatin, but alcohol increases hepatic risk and may worsen transaminase elevations.
Over‑the‑counter supplements such as high‑dose niacin or red yeast rice can increase muscle or hepatic risk and should be checked during medication reconciliation.
| High‑Risk Drug Pairs | Effect |
|---|---|
| Rosuvastatin + Cyclosporine | Increased risk of myopathy/rhabdomyolysis; avoid or reduce dose. |
| Rosuvastatin + Gemfibrozil | Elevated myotoxicity risk; avoid combination where possible. |
| Rosuvastatin + Strong CYP/Transporter Inhibitors | Altered exposure; review and adjust dosing as needed. |
For telehealth prescriptions in Australia pharmacists should perform medication reconciliation through eRx and pharmacy verification to identify interactions before dispensing.
Cultural Perceptions And Patient Habits
How do Australians view rosuvastatin and what habits affect adherence?
Many Australian patients trust pharmacists and GPs for statin guidance, yet notable hesitancy exists among younger adults and those influenced by online forums.
Rural Australians face access and continuity challenges such as longer travel to pharmacies and limited specialist availability, which can reduce persistence with therapy.
Urban patients benefit from multiple pharmacy chains and telehealth services that improve convenience and supply options.
Price sensitivity drives a preference for PBS‑subsidised generics among many patients, and community pharmacies frequently advise on cheaper alternatives and repeats.
Indigenous and culturally and linguistically diverse communities benefit from culturally tailored counselling about long‑term therapy benefits and pregnancy planning.
Common patient concerns discussed on forums include muscle pain and perceived cognitive effects; pharmacists should address these concerns with evidence and offer CK or LFT checks when appropriate.
| Setting | Access And Barriers |
|---|---|
| Urban | Multiple pharmacy chains, easier telehealth access, better specialist availability. |
| Rural | Longer travel to chemists, sporadic specialist clinics, occasional stock runs. |
- Counselling Suggestions: Use plain language, address muscle symptoms directly, provide written action plans and offer culturally safe explanations about contraception for women of childbearing potential.
Availability And Pricing Patterns
Where can Australians get rosuvastatin and how much will it cost?
Rosuvastatin in branded and generic forms is widely available across community pharmacies and online in Australia.
PBS listing determines the subsidised price for eligible patients, while private scripts vary in price by brand and pharmacy.
Price‑sensitive consumers often compare offers at major chains such as Chemist Warehouse, Priceline and independents before purchasing.
Telehealth platforms commonly issue e‑prescriptions for repeat rosuvastatin and community pharmacies dispense according to PBS rules.
In our online pharmacy, crestor is available without a prescription, with discreet delivery to Australia in 5-14 days.
Rural supply can be affected by occasional stock runs, and pharmacists may substitute therapeutically equivalent generic brands when clinically appropriate and consistent with PBS regulations.
| Script Type | Typical Price Pattern |
|---|---|
| PBS‑Subsidised Script | Lower out‑of‑pocket cost for eligible patients; often generic brand supplied. |
| Private/Non‑PBS Script | Price varies by brand and pharmacy; branded Crestor typically more expensive than generics. |
- Pharmacist Checklist For Substitution: Confirm clinical suitability, document substitution per PBS paperwork when required and inform the patient about the brand change.
Comparable Medicines And Preferences
When might a prescriber choose rosuvastatin over other statins and what are the common alternatives in Australia?
Alternatives commonly used in Australia include atorvastatin, simvastatin, pravastatin and pitavastatin, with ezetimibe used as an adjunct when needed.
Rosuvastatin is often chosen for its greater LDL‑lowering potency at lower doses and for patients who need substantial LDL reductions, such as those with familial hypercholesterolaemia.
Atorvastatin is widely used due to prescriber familiarity and broad generic competition, while simvastatin is less preferred where interaction profiles are problematic.
Choice factors include renal and hepatic comorbidity, drug interactions, PBS criteria and cost to the patient.
Pros and Cons Checklist
- Rosuvastatin: High potency for LDL lowering; watch for renal dosing and interaction risk; PBS access influences cost.
- Atorvastatin: Widely used; extensive generic options; effective LDL lowering but may require higher mg to match rosuvastatin potency.
- Simvastatin: Lower cost options exist but more interaction potential with CYP3A4 inhibitors.
| Medicine | Typical Use | Notes |
|---|---|---|
| Rosuvastatin | High LDL reduction needs, FH, high‑risk prevention | More potent at lower doses; consider renal dosing adjustments |
| Atorvastatin | General LDL lowering, wide prescriber familiarity | Good generic availability; cost‑effective option |
| Simvastatin | Older statin options where interactions manageable | More interaction risk; not preferred for high LDL reductions |
FAQ Section
Can I take Crestor if I’m pregnant?
No.
Statins including rosuvastatin are contraindicated in pregnancy and lactation.
Discuss contraception and alternative lipid management with your GP before starting therapy if you are of childbearing potential.
What if I get muscle pain while taking rosuvastatin?
Report muscle symptoms promptly to your prescriber or pharmacist.
CK testing is recommended if muscle pain is significant or associated with weakness, and temporary cessation or dose modification may be considered under supervision.
Do I need routine blood tests while on rosuvastatin?
Yes.
Obtain baseline liver function tests and a lipid panel before starting rosuvastatin.
Recheck lipids approximately 6–12 weeks after initiation or dose change, and perform LFTs as clinically indicated.
CK testing is recommended when muscle symptoms arise.
Is rosuvastatin more expensive than other statins?
PBS‑eligible patients usually pay a subsidised amount that makes rosuvastatin affordable.
Private script prices vary by brand and pharmacy; compare generics at major chains and discuss PBS eligibility with your prescriber or pharmacist.
Monitoring Tests (Definition List)
- Baseline Lipid Panel: Before starting therapy.
- Follow‑Up Lipid Panel: About 6–12 weeks after starting or changing dose.
- Baseline LFTs: Prior to initiation and as clinically indicated.
- CK: Only if muscle symptoms occur.
Guidelines For Proper Use
What should pharmacists and GPs cover when counselling patients about rosuvastatin?
Confirm PBS eligibility and obtain previous lipid results before starting or repeating prescriptions.
Assess contraindications such as pregnancy, active liver disease and significant renal impairment prior to initiating therapy.
Obtain baseline LFTs and renal function tests, and consider a pregnancy test where clinically appropriate.
Start at the recommended dose for the patient group, lowering initial doses for Asian descent or renal impairment as required by the product monograph.
Advise patients to take rosuvastatin once daily and describe missed‑dose action: take as soon as remembered on the same day, but do not double the next dose.
Encourage lifestyle measures including diet, exercise and alcohol moderation alongside pharmacotherapy.
For rural and telehealth patients, verify e‑prescription accuracy, confirm pharmacy stock and arrange for local pathology availability for monitoring tests.
Pharmacist Counselling Flow
- Step 1: Verify identity, current medications and PBS eligibility.
- Step 2: Review contraindications and baseline labs.
- Step 3: Explain dosing, expected benefits, common side effects and when to seek review.
- Step 4: Provide written action plan for muscle symptoms and arrange follow‑up for lipid monitoring.
Sample Telehealth Script Snippet:
"Have you had a recent lipid panel or liver function test in the last 12 months?"
"Are you taking any medicines such as ciclosporin, gemfibrozil, or supplements like red yeast rice?"
"If you get new muscle pain or dark urine, stop the tablet and contact us or your GP immediately for testing."
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Darwin | Northern Territory | 5-7 days |
| Gold Coast | Queensland | 5-7 days |
| Newcastle | New South Wales | 5-7 days |
| Wollongong | New South Wales | 5-9 days |
| Geelong | Victoria | 5-9 days |
| Townsville | Queensland | 5-9 days |
| Cairns | Queensland | 5-9 days |