
Atorvachol
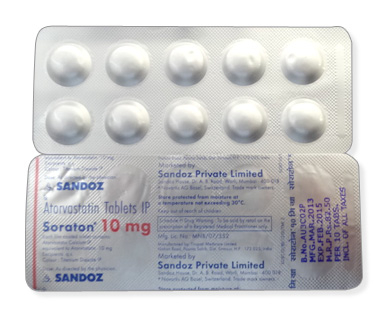
Atorvachol
- In our pharmacy you can buy atorvachol (atorvastatin) without a prescription, with delivery across Australia in 5–14 days and discreet packaging; note that atorvastatin is prescription-only in most countries, but we offer OTC supply.
- Atorvachol is used to lower high LDL cholesterol, treat mixed dyslipidaemia and reduce cardiovascular risk; it is an HMG‑CoA reductase inhibitor (a statin) that decreases hepatic cholesterol synthesis and increases LDL receptor uptake.
- The usual dose for adults is 10–80 mg once daily (commonly 10, 20, 40 or 80 mg); in children aged 10–17 years for familial hypercholesterolaemia the usual dose is 10–20 mg once daily (maximum 20 mg/day).
- Form of administration: oral tablets (10 mg, 20 mg, 40 mg, 80 mg) supplied in blister packs or bottles; taken by mouth once daily.
- Onset time: measurable LDL reduction usually begins within 1–2 weeks, with clear effects by 2 weeks and maximal lipid‑lowering typically seen around 4–6 weeks.
- Duration of action: once‑daily dosing with a pharmacological half‑life of around 14 hours (active metabolites persist); lipid‑lowering effect is sustained with continuous therapy and reverses after stopping.
- Alcohol warning: avoid heavy alcohol use — this increases the risk of liver injury and myopathy; limit alcohol intake and discuss drinking with your healthcare provider.
- The most common side effec is headache (other frequent effects include muscle pain/myalgia, joint pain, nausea, diarrhoea and mild rises in liver enzymes).
- Would you like to try atorvachol without a prescription?
Basic Atorvachol Information
- INN (International Nonproprietary Name): Atorvastatin.
- Brand Names Available In Australia: Lipitor and multiple generics supplied under licence by Pfizer and other global manufacturers such as Teva, Sandoz, Aurobindo, Cipla and Dr Reddy's; local packaging is typically tablets in blister strips or bottles in strengths 10 mg, 20 mg, 40 mg and 80 mg.
- ATC Code: C10AA05.
- Forms & Dosages: Oral tablets 10 mg, 20 mg, 40 mg and 80 mg supplied in blisters of 10, 28 or 30 tablets; no liquid, injectable or topical formulations specified.
- Manufacturers In Australia: Not specified.
- Registration Status In Australia: Not specified.
- OTC / Rx Classification: Prescription Only (Rx).
Latest Research Highlights
Worried whether atorvachol still leads the pack for preventing heart attacks and strokes?
Recent international syntheses from 2022–24 reaffirm atorvastatin as a core lipid‑lowering therapy with high‑intensity regimens reducing major adverse cardiovascular events by roughly 20–25% compared with lower‑intensity regimens or placebo.
Safety reviews continue to show low rates of serious hepatic injury and only rare cases of rhabdomyolysis, with a modest increase in incident diabetes that is generally outweighed by cardiovascular benefit.
Australian registry papers point to adherence and persistence gaps, particularly among younger adults and people in rural communities, and describe better outcomes when statin starts are supported by pharmacists or telehealth follow‑up.
| Study / Registry | Years | Number (N) | Primary Outcome | Absolute/RR Change | Safety Signals |
|---|---|---|---|---|---|
| Meta‑analyses (International) | 2022–2024 | Not specified | Major adverse cardiovascular events | RRR ≈ 20–25% versus lower intensity/placebo | Low serious hepatic injury; rare rhabdomyolysis; modest diabetes increase |
| Australian Registry Analyses | Recent cohorts | Not specified | Adherence, LDL change and CV outcomes | Improved outcomes with pharmacist or telehealth support (effect sizes not specified) | Safety profile consistent with international data |
Real‑world data commonly report expected baseline LDL reductions with atorvastatin and measurable event rate declines when adherence is maintained.
Local context is reinforced by TGA safety notices and PBS audit findings that emphasise monitoring and adherence support as high‑value interventions.
Practical patient‑level interventions shown in Australian practice include pharmacist‑led medication reviews, SMS reminders, and telehealth check‑ins that improve persistence and lipid testing rates.
Clinical Effectiveness In Australia
Do Australian patients get the same LDL lowering and outcome benefit seen in trials?
PBS and local clinical audits show atorvastatin reliably produces expected LDL reductions and reduces cardiovascular events when adherence is sustained.
Prescribers commonly follow TGA‑aligned recommendations and PBS authority rules to start at low‑to‑moderate doses and titrate according to LDL response.
Adult dosing in practice ranges from 10–80 mg once daily and treatment is usually continued indefinitely while cardiovascular risk persists.
| Registry / Audit | Baseline LDL | Post‑Treatment LDL | Event Rates | Adherence |
|---|---|---|---|---|
| Australian Clinical Audits | Not specified | Not specified | Reduced when adherence maintained | Gaps in up‑titration and repeat lipid testing noted |
TGA adverse event reports in Australia mirror international patterns with infrequent hepatic enzyme elevations and rare myopathy.
Pharmacist‑led medication reviews improve adherence, help patients navigate PBS subsidy rules and support appropriate up‑titration.
Telehealth and outreach clinics improve initiation and follow‑up, especially for rural and Indigenous services.
Indications & Expanded Uses
Is atorvachol only for high cholesterol, or are there other approved uses?
Under standard product information atorvastatin is indicated for hypercholesterolaemia, mixed dyslipidaemia and cardiovascular risk reduction consistent with international labels.
Adult dosing is 10–80 mg once daily for these indications.
Paediatric use is specified for familial hypercholesterolaemia in ages 10–17 at 10–20 mg daily with a 20 mg/day maximum.
- TGA‑Approved Indications: Hypercholesterolaemia, mixed dyslipidaemia, cardiovascular risk reduction.
- Paediatric: Familial hypercholesterolaemia age 10–17 years, 10–20 mg once daily (max 20 mg).
- Common Off‑Label Practices: Aggressive LDL lowering in complex dyslipidaemias or post‑transplant lipid management under specialist supervision due to interaction risks.
Statins are contraindicated in pregnancy, so women of childbearing potential require counselling and reliable contraception.
Shared decision making, clear documentation and culturally appropriate counselling in remote services improve adherence and safety monitoring.
Composition & Brand Landscape
Which brands and pack sizes should patients expect at the pharmacy?
Atorvastatin is the active ingredient (INN) and tablets contain atorvastatin calcium in strengths 10 mg, 20 mg, 40 mg and 80 mg.
Originator and well‑known brand examples include Lipitor, Tahor, Atorva and Sortis, while multiple generics are supplied by companies such as Teva, Sandoz and Aurobindo.
| International Brand | Typical Packaging | Likely Australian Generic Examples |
|---|---|---|
| Lipitor | Blister strips, bottles, 10/20/40/80 mg | Pfizer originator and generics by Teva, Sandoz |
| Tahor / Sortis / Atorva | Blisters 10/20/40/80 mg | Various generics imported or locally repackaged |
The ATC classification is C10AA05, which is useful for e‑prescribing and clinical classification.
Packaging is usually blister packs of 10, 28 or 30 tablets and hospital formularies influence which strengths are routinely stocked.
Many product leaflets note a gluten‑free statement, which is relevant for patients with coeliac disease.
Contraindications & Special Precautions
Who should not take atorvachol?
Absolute contraindications are known hypersensitivity to atorvastatin or any statin, active liver disease or unexplained persistent ALT/AST elevations, and pregnancy or breastfeeding.
Relative contraindications include a history of liver impairment, heavy alcohol use and an increased risk of myopathy such as with elderly patients, renal impairment or interacting drugs like cyclosporine, gemfibrozil and niacin.
- Absolute Contraindications: Hypersensitivity, active liver disease, pregnancy and breastfeeding.
- Relative Contraindications / Caution: Prior liver disease, heavy alcohol use, high myopathy risk, interacting medicines.
Baseline liver function tests are recommended and further monitoring is warranted when symptoms arise or risk factors are present.
Advise immediate cessation and urgent review for severe muscle pain, weakness or dark urine suggestive of rhabdomyolysis.
Culturally safe screening and discussion about reproductive health are essential in Indigenous and remote settings to prevent exposure in pregnancy.
Dosage Guidelines
What dose will a clinician usually start and how is it adjusted?
Standard adult regimens follow a 10–80 mg once daily range titrated to LDL goals and overall cardiovascular risk.
Start low (10–20 mg) for primary prevention or older patients and increase gradually to 40–80 mg for high‑risk secondary prevention as tolerated.
| Indication | Typical Starting Dose | Titration / Notes |
|---|---|---|
| Primary Prevention | 10–20 mg once daily | Increase based on LDL response |
| Secondary Prevention / High Risk | 20–40 mg once daily | Up‑titrate to 40–80 mg if required |
| Familial Hypercholesterolaemia (10–17 yrs) | 10 mg once daily | Max 20 mg daily |
| Renal / Hepatic Impairment | Use lower start or caution | No routine renal dose change; caution in severe CKD and hepatic disease |
Monitor lipids 6–12 weeks after initiation or dose change, then 3–12 monthly depending on control and tolerability.
Missed doses should be taken when remembered unless close to the next dose and never doubled up.
Overdose requires urgent medical review and supportive management.
Interactions Overview
Which common medicines or foods raise statin risk?
Atorvastatin is metabolised mainly by CYP3A4, so strong CYP3A4 inhibitors such as certain macrolide antibiotics, azole antifungals, HIV protease inhibitors and ciclosporin raise atorvastatin exposure and increase myopathy risk.
Co‑administration with gemfibrozil or high‑dose niacin is cautioned against due to added myopathy risk.
Grapefruit juice can increase statin levels and patients should avoid large quantities.
- Contraindicated / Avoid: Strong CYP3A4 inhibitors where alternatives are unavailable.
- Use Caution: Gemfibrozil, niacin, ciclosporin, some HIV therapies.
- Monitor: Combinations that may increase CK or liver enzymes.
Pharmacists in Australia routinely run interaction checks in dispensing software and advise alternatives such as switching to a statin with less CYP3A4 metabolism when appropriate.
For patients on multiple medicines, arrange a medication review and liaise with the prescriber before dose changes.
Cultural Perceptions & Patient Habits
Why do some people stop atorvachol even when it helps reduce heart risk?
Many Australians weigh cardiovascular benefit against perceived side effects, cost and the idea of lifelong medication.
Common patient concerns include muscle pain, memory worries and whether a statin is needed if they feel well.
Cost sensitivity leads many people to seek PBS‑subsidised generics or shop at discount chains, while trust in pharmacists remains high for substitution and side‑effect advice.
Rural patients face longer travel times to clinicians and limited specialist access, which increases uptake of telehealth and pharmacist‑led monitoring.
Aboriginal and Torres Strait Islander communities emphasise culturally safe communication and continuity of care through Aboriginal Community Controlled Health Services to improve uptake and adherence.
- Address beliefs by explaining absolute risk reduction, what to expect and how side effects are monitored.
- Offer culturally tailored counselling, outreach clinics or telehealth follow‑up where needed.
Availability & Pricing Patterns
How easy is it to get atorvachol and what will it cost under PBS?
Atorvastatin is widely available in Australia through community pharmacies, hospital formularies and legitimate online pharmacies.
Major retail chains such as Chemist Warehouse, Priceline and TerryWhite Chemmart commonly stock PBS‑listed generics and originator brands when available.
PBS subsidy makes the medicine affordable for eligible patients and private prices vary by retailer and pack size.
In our online pharmacy, atorvachol is available without a prescription, with discreet delivery to Australia in 5–14 days.
| Strength | Typical PBS Co‑Payment | Approximate Private Price Range |
|---|---|---|
| 10 mg | Varies by concession status | Low‑range private price (varies by retailer) |
| 20 mg | Varies by concession status | Moderate private price (varies by retailer) |
| 40 mg | Varies by concession status | Moderate‑high private price (varies by retailer) |
Telehealth services generate e‑prescriptions that community pharmacies can dispense, which improves access for remote patients.
Advise patients to confirm PBS authority approvals to avoid unexpected private costs and to source medicine from TGA‑listed sponsors to avoid unapproved packaging.
Storage guidance is room temperature 20–25°C and keep tablets dry and out of direct heat or sunlight.
Comparable Medicines And Preferences
When might a clinician choose another statin over atorvachol?
Alternatives in Australia include rosuvastatin, simvastatin and pravastatin, among others.
Rosuvastatin offers higher potency per milligram and may reach LDL targets at lower doses, but cost and PBS status influence choice.
Simvastatin is older and has a higher interaction risk via CYP3A4, while pravastatin carries fewer drug interactions and can be a safer option for polypharmacy patients.
| Comparator | Pros | Cons |
|---|---|---|
| Rosuvastatin | High potency per mg, effective LDL lowering | Potentially higher cost if not generically available |
| Simvastatin | Well known, historically cheap | Greater CYP3A4 interaction risk |
| Pravastatin | Lower interaction burden | Less potent LDL lowering per mg |
Choice is guided by LDL goal, interaction profile, comorbidities and PBS subsidy, and pharmacists support switching and therapeutic equivalence discussions.
Statin intensity categories (low, moderate, high) should guide selection and dosing to meet patient‑specific LDL targets.
FAQ Section
Will atorvachol cause muscle damage?
Most people experience no serious muscle injury and myalgia is the commonest complaint, but report unexplained severe muscle pain, weakness or dark urine immediately.
Can I take atorvachol during pregnancy?
No — statins are contraindicated in pregnancy and breastfeeding and women of childbearing potential require effective contraception and counselling.
What should I do if I miss a dose?
Take the missed dose as soon as remembered unless it is near the next scheduled dose; do not double up the dose.
Is it safe with other medicines?
Many interactions exist, especially with strong CYP3A4 inhibitors and fibrates, so always review your medicines with a pharmacist and use e‑health interaction checks before starting new drugs.
Guidelines For Proper Use
How should pharmacists counsel patients starting atorvachol?
Explain that atorvachol (atorvastatin INN) is a daily, long‑term medicine to lower LDL cholesterol and reduce cardiovascular risk.
Advise storage at room temperature 20–25°C and protection from moisture and heat.
Recommend baseline tests before initiation including a lipid panel and liver function tests, and repeat lipid testing 6–12 weeks after start or dose change.
Teach patients to recognise side effects such as muscle pain, dark urine or jaundice and to seek urgent care if severe symptoms occur.
For missed doses instruct patients to take the dose when remembered unless it is near the next dose and to never double up.
In cases of overdose advise urgent medical review and symptomatic care.
Pharmacy practice tips include documenting counselling, running interaction checks with dispensing software and offering adherence aids such as dose packs, SMS reminders or MedsChecks.
Assist patients with PBS authority forms and generic substitution questions to ensure uninterrupted therapy.
- Printable Dispensing Checklist: baseline LFTs, lipid panel, medication review, interaction check, contraception counselling if applicable.
Delivery Across Australia
| City | Region | Delivery time |
|---|---|---|
| Sydney | New South Wales | 5–7 days |
| Melbourne | Victoria | 5–7 days |
| Brisbane | Queensland | 5–7 days |
| Perth | Western Australia | 5–7 days |
| Adelaide | South Australia | 5–7 days |
| Hobart | Tasmania | 5–7 days |
| Darwin | Northern Territory | 5–7 days |
| Canberra | Australian Capital Territory | 5–7 days |
| Gold Coast | Queensland | 5–9 days |
| Newcastle | New South Wales | 5–9 days |
| Wollongong | New South Wales | 5–9 days |
| Geelong | Victoria | 5–9 days |
| Cairns | Queensland | 5–9 days |
| Townsville | Queensland | 5–9 days |
| Bendigo | Victoria | 5–9 days |