
Citalopram
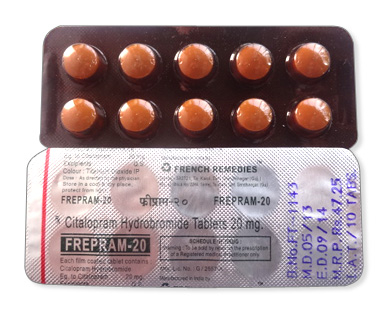
Citalopram
- You can obtain citalopram from community and hospital pharmacies in Australia and other regulated markets; it is a prescription-only (Rx) medicine and is not sold over the counter — while some online vendors may claim to supply without a prescription, this is not legal or recommended; always consult a prescriber or pharmacist.
- Citalopram is used to treat major depressive disorder, obsessive–compulsive disorder, panic disorder and social phobia; it is a selective serotonin reuptake inhibitor (SSRI) that works by blocking the reuptake of serotonin, increasing its availability in the brain.
- The usual adult dose for major depressive disorder is 20 mg once daily (can be increased to 40 mg/day as tolerated); for some anxiety disorders clinicians may start at 10–20 mg and increase to 20–40 mg; elderly patients and those with hepatic impairment are usually limited to a maximum of 20 mg/day.
- Citalopram is administered orally: tablets or film‑coated tablets (10 mg, 20 mg, 40 mg) and oral solution/drops (commonly 10 mg/mL or 20 mg/mL); intravenous formulations exist rarely for hospital use.
- Some patients may notice improvement within 1–4 weeks, although meaningful antidepressant effects often take several weeks to develop.
- Citalopram is given once daily and has an elimination half‑life of roughly 35 hours; treatment courses are typically continued for months, with at least 6 months’ continuation after symptom remission for major depression.
- Avoid or minimise alcohol while taking citalopram — alcohol can increase drowsiness, worsen mood symptoms and heighten side effects.
- The most common side effect is nausea (other frequent effects include dry mouth, sweating, fatigue, tremor, diarrhoea, somnolence, insomnia, headache and sexual dysfunction).
- Would you like to try citalopram without a prescription?


Basic Citalopram Information
- INN (International Nonproprietary Name): Citalopram
- Brand Names Available In Australia: Talohexal; Celapram
- ATC Code: N06AB04
- Forms & Dosages: Oral tablets 10 mg, 20 mg, 40 mg; film-coated tablets 10 mg, 20 mg, 40 mg; oral solution/drops 10 mg/mL and 20 mg/mL; rare IV formulations reported elsewhere
- Manufacturers In Australia: Arena Group, Actavis (now Teva), Zentiva, Sandoz, Hexal (plus global suppliers including Lundbeck, Teva and others)
- Registration Status In Australia: Registered and supplied under prescription-only status (Rx)
- OTC / Rx Classification: Prescription only (Rx); not available over-the-counter in regulated markets
Latest Research Highlights (Australian And International, 2022–2025)
Clinicians ask whether citalopram still performs well compared with newer treatments.
Meta-analyses from 2022–2025 report modest but consistent benefit of citalopram for major depressive disorder versus placebo.
Early clinical response is commonly observed from one to four weeks, with full effect often by six to eight weeks.
Systematic reviews continue to emphasise a dose-related risk of QT prolongation, particularly above 40 mg daily and in older patients.
These safety findings have informed TGA-style caution that mirrors international regulator advice on limiting doses in the elderly.
Australian PBS-linked cohort analyses and telehealth prescribing audits show stable prescription volumes and a marked rise in remote initiation since 2020.
Randomised controlled trials and real-world studies from 2022–2025 repeatedly identify sexual dysfunction and withdrawal phenomena as frequent reasons for stopping treatment.
Pharmacogenomic studies note variability in CYP2C19 metabolism affecting plasma levels, though routine genotyping uptake in Australia remains limited.
TGA and international pharmacovigilance reports between 2022 and 2025 flag rare cardiac arrhythmias and serotonin syndrome when combined with MAOIs or other serotonergic agents.
Regulatory surveillance also reiterates an increased suicidal ideation signal mainly in people under 25 years of age, consistent with prior guidance.
Clinical Effectiveness In Australia (PBS Outcomes & TGA Data)
Patients want to know how citalopram performs in everyday Australian practice.
PBS dispensing trends show citalopram remains among the common SSRI options alongside escitalopram and sertraline.
Real-world effectiveness measured by remission proxies—repeat prescribing and mental-health follow-ups—aligns with international effect sizes for first-line SSRIs.
TGA adverse event reports emphasise QT-related events at higher doses and in older adults, supporting a maximum 20 mg/day recommendation for people aged 65 and over.
Telehealth-driven prescribing has improved access in rural and remote Australia, although post-initiation follow-up engagement varies across regions.
PBS-subsidised patients generally show higher continuation rates, suggesting cost and subsidy affect adherence and real-world outcomes.
Small datasets comparing PBS dispensed volumes, hospital admissions for antidepressant overdose and TGA adverse event counts provide a pragmatic snapshot for prescribers and pharmacists.
Overall, hospital admission data and TGA reports indicate safety signals are uncommon but clinically important when risk factors exist.
Indications And Expanded Uses (TGA Approved And Off‑Label)
Patients often ask what conditions citalopram treats and when specialists might use it off‑label.
TGA-aligned indications include major depressive disorder and anxiety-related disorders such as panic disorder and social phobia, with dosing guidance per product information.
Many jurisdictions also list obsessive-compulsive disorder among recognised indications, and specialists may manage dosing differently for OCD.
Standard adult starting dose for MDD is 20 mg daily, with increases up to 40 mg daily in younger adults where appropriate.
Specialist-led lower starting doses are common for panic disorder and OCD, often beginning at 10 mg and titrating cautiously.
Off‑label uses seen in Australian clinical practice include neuropathic pain management and agitation in some neuropsychiatric settings, typically prescribed by specialists after risk–benefit discussion.
Contraindications include concurrent MAOI use and pimozide, and ECG assessment is suggested for patients with cardiac risk factors.
Duration guidance follows usual practice: continue for at least six months after remission for a first episode of MDD and longer for recurrent illness.
- Approved Uses: Major depressive disorder, panic disorder, social phobia, (OCD in many jurisdictions).
- Off‑Label Uses: Neuropathic pain, specialist-managed agitation (after specialist review).
Composition And Brand Landscape (Active Ingredient, Australian Brands)
People commonly ask whether brand or generic matters for therapy and price.
The active ingredient is citalopram (commonly listed as citalopram hydrobromide in formulations) and the ATC code is N06AB04.
Australian brands available include Celapram and Talohexal alongside multiple generics supplied by known manufacturers.
Local manufacturers and suppliers include Arena, Teva (Actavis), Zentiva, Sandoz and Hexal, with Lundbeck as an originator globally.
Dosage forms supplied in Australia are tablets in 10 mg, 20 mg and 40 mg strengths and occasionally oral solutions sourced from imports.
Packaging is typically foil blisters or bottles, and competitive generic supply helps keep prices contained under the PBS.
| Brand | Manufacturer | Strengths | Packaging |
|---|---|---|---|
| Celapram | Local Supplier | 10 mg, 20 mg, 40 mg | Foil Blisters |
| Talohexal | Hexal | 10 mg, 20 mg, 40 mg | Bottles / Blisters |
| Generic Citalopram | Teva / Sandoz / Arena / Zentiva | 10 mg, 20 mg, 40 mg | Blisters / Bottles |
Contraindications And Special Precautions (Elderly, Pregnancy, Indigenous Health)
People worry about safety if they are older, pregnant or have other conditions.
Absolute contraindications are hypersensitivity to SSRIs, concurrent use with MAOIs within two weeks, and co‑administration with pimozide or known QT‑prolonging drugs.
Elderly patients (aged 65 and over) should usually be limited to 20 mg daily because of increased QT prolongation risk and pharmacological sensitivity.
Hepatic or renal impairment calls for lower starting doses and a 20 mg/day maximum in many cases; severe organ dysfunction may warrant avoidance.
A history of seizures or bipolar disorder requires specialist input because SSRIs can lower seizure thresholds or precipitate mania.
Pregnancy and breastfeeding require individual risk–benefit discussion with a specialist or treating clinician, and shared decision-making is recommended.
In Aboriginal and Torres Strait Islander health contexts, culturally safe discussions are essential and involvement of Aboriginal Health Workers and local services is strongly encouraged.
- Contraindications: Hypersensitivity, MAOI within two weeks, pimozide/co‑administered QT drugs.
- Precautions: Elderly ≤20 mg/day, liver/renal impairment, seizure history, bipolar disorder, pregnancy/breastfeeding counsel.
Dosage Guidelines (Australian Practice, Comorbidity Adjustments)
Patients often ask what dose to start and how to adjust when other health issues are present.
Standard adult initiation for major depressive disorder is 20 mg once daily, taken morning or evening according to tolerance.
If needed and tolerated, adults may be titrated up to 40 mg/day, noting QT risks at higher doses.
Elderly patients and those with hepatic impairment generally start lower and are usually limited to 20 mg/day.
Panic disorder and OCD often start at lower doses, such as 10 mg daily, with gradual increases to 20–40 mg under specialist care.
Renal impairment merits a cautious start and close monitoring; severe renal disease usually leads clinicians to avoid use where possible.
Paediatric use under 18 years is not generally recommended due to limited safety and efficacy data.
Tapering is recommended to reduce withdrawal symptoms, typically reducing dose by 10–25% stepwise over weeks depending on duration and dose.
| Condition | Start Dose | Target | Max |
|---|---|---|---|
| Major Depressive Disorder | 20 mg/day | 20–40 mg/day | 40 mg/day |
| Older Adults (≥65) | 10–20 mg/day | 20 mg/day | 20 mg/day |
| Panic / OCD | 10 mg/day | 20–40 mg/day | 40 mg/day |
Interactions Overview (Drugs, Food, Alcohol)
People frequently ask what medicines and substances to avoid while taking citalopram.
Major contraindicated combinations include MAOIs and pimozide because of risk of serotonin syndrome and serious cardiac events respectively.
Other serotonergic agents—triptans, SNRIs, certain antipsychotics and linezolid—raise serotonin syndrome risk and should be reviewed before co‑prescribing.
Drugs that prolong the QT interval or alter electrolytes, and potent CYP enzyme inhibitors or inducers, may change citalopram plasma levels and increase risk.
Over-the-counter alcohol is not recommended while taking citalopram because it increases sedation and can worsen depressive symptoms.
Caffeine and coffee have no direct pharmacokinetic interaction but can increase anxiety and disturb sleep for some patients.
Pharmacist-led medication reconciliation via e‑health records is useful to spot high‑risk agents before dispensing.
| Drug Class | Risk | Action |
|---|---|---|
| MAOIs | Serotonin syndrome | Contraindicated; wait 2 weeks after stopping MAOI |
| QT‑prolonging drugs (e.g. pimozide) | Arrhythmia, torsades | Avoid combination; consider ECG |
| Other serotonergic agents | Serotonin syndrome | Monitor closely; adjust therapy |
Cultural Perceptions And Patient Habits (Australian Patient Insights)
What do Australian patients say about citalopram in forums and at the chemist?
Price sensitivity is common and many patients rely on PBS subsidy to continue treatment without financial strain.
There is strong trust in community pharmacists at chains such as Chemist Warehouse, Priceline and TerryWhite Chemmart for counselling and privacy.
Acceptance of telehealth e‑prescriptions has grown since COVID, easing access for many people in outer suburbs and regional areas.
Rural patients still report access delays and shorter follow-up compared with city peers, and Indigenous communities emphasise culturally safe care and local engagement.
Common patient concerns flagged in forums include sexual side effects, weight changes and withdrawal symptoms when stopping treatment.
Pharmacists often act as first-line advisers on switching between brand and generic citalopram and helping with adherence strategies.
- Patient Priorities: clear counselling, affordable PBS-subsidised options, privacy and reliable follow-up.
- Community Themes: concern about sexual side effects; preference for pharmacist support and telehealth convenience.
Availability And Pricing Patterns (Retail Chains, Online, PBS)
People need to know where to buy citalopram and what it will cost.
Citalopram is available through major Australian retail chains and accredited online pharmacies, often on PBS subsidy for eligible patients.
PBS listing status substantially reduces cost for concessional patients compared with private purchase of generics or brands.
Competitive supply from multiple manufacturers keeps private prices relatively low, and retailers may run discount strategies for private-price customers.
Supply chains benefit from several suppliers including Arena, Teva, Sandoz and Hexal, which reduces stock‑risk but occasional shortages still occur.
When an item is out of stock, pharmacists may therapeutically substitute an equivalent generic brand in line with regulations and prescriber consent where required.
In our online pharmacy, citalopram can be ordered with a valid prescription and we offer discreet delivery across Australia in 5–14 days.
| Purchase Route | Price Driver | Patient Action If Out Of Stock |
|---|---|---|
| PBS Dispensing | Subsidy, concessional status | Request substitution or repeat script via GP |
| Private Purchase | Generic competition, retailer discount | Ask pharmacist for therapeutically equivalent generic |
| Online / Telehealth | Convenience, delivery fees | Check delivery estimates and prescription validity |
Comparable Medicines And Preferences (Alternatives, Pros And Cons)
Clinicians choosing an SSRI balance efficacy, tolerability and patient context.
Escitalopram is often cited as better tolerated with similar efficacy but can be costlier depending on PBS status and brand.
Sertraline is frequently preferred for anxiety disorders due to evidence and tolerability in that subgroup.
Fluoxetine has a long half‑life which can be useful for adherence or when gradual discontinuation is a concern.
Paroxetine carries a higher anticholinergic burden and more problematic withdrawal profile for some patients.
Strengths of citalopram include established efficacy, broad generic availability and flexible dosing from 10–40 mg.
Limitations include dose‑dependent QT risk which affects elderly prescribing and sexual dysfunction which is commonly reported.
- Considerations For Choice: cardiac comorbidity, pregnancy planning, interaction potential, PBS listing and cost.
- Prescribing Tip: choose the SSRI that best matches the patient’s comorbidities and tolerance history.
Frequently Asked Questions
-
How Long Until It Works?
Many people notice early improvements in mood or sleep within one to four weeks.
A full antidepressant response usually takes six to eight weeks, so continue therapy unless advised otherwise.
-
Can I Drink Alcohol?
Alcohol is not recommended while taking citalopram because it can increase drowsiness and worsen mood symptoms.
-
What If I Miss A Dose?
Take the missed dose when you remember unless it is near the time for the next dose.
Do not double up to make up for a missed dose.
-
Is It On The PBS And How Much Will It Cost?
Many formulations of citalopram are PBS-subsidised for eligible patients; final cost depends on concession status and the dispensed brand or generic.
Community pharmacists can check PBS entitlements and advise on costs and alternatives.
Guidelines For Proper Use (Pharmacist Counselling And National Guidance)
Pharmacists should provide clear, practical counselling consistent with TGA and PBS guidance.
Verify the indication, check for MAOI or pimozide use, and screen for QT risk factors during the initial consultation.
Assess age, hepatic and renal function and recommend a baseline ECG when higher doses or cardiac disease are present.
Counsel on common side effects such as nausea, sleep changes and sexual dysfunction and explain gradual tapering to reduce withdrawal risk.
Document the supply in the e‑health record and encourage reporting of adverse events to the TGA when appropriate.
Use culturally respectful language, involve family or Aboriginal Health Workers where appropriate, and offer a follow‑up call within one to two weeks.
- Counselling Checklist: confirm indication, review medicines, advise start dose, warn about alcohol, offer written info and follow-up.
- PBS Prescribing Note Template: indication, dose, duration, monitoring plan, ECG requirement (if any) and follow-up timeframe.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5–7 days |
| Melbourne | Victoria | 5–7 days |
| Brisbane | Queensland | 5–7 days |
| Perth | Western Australia | 5–7 days |
| Adelaide | South Australia | 5–7 days |
| Canberra | Australian Capital Territory | 5–7 days |
| Hobart | Tasmania | 5–9 days |
| Darwin | Northern Territory | 5–9 days |
| Gold Coast | Queensland | 5–7 days |
| Newcastle | New South Wales | 5–9 days |
| Wollongong | New South Wales | 5–9 days |
| Geelong | Victoria | 5–9 days |