
Cipramil
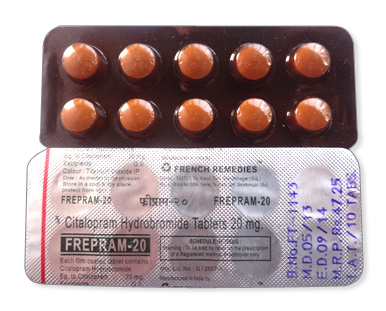
Cipramil
- In our pharmacy, you can buy cipramil without a prescription, with delivery across Australia and discreet packaging; however, cipramil (citalopram) is prescription-only in most jurisdictions and using it without medical supervision carries risks—consult a healthcare professional if possible.
- Cipramil (citalopram) is used to treat major depressive disorder and works as a selective serotonin reuptake inhibitor (SSRI), increasing serotonin levels in the brain by blocking its reuptake into neurons.
- The usual adult dose is to start at 20 mg once daily; typical maintenance is 20–40 mg once daily, with a maximum recommended dose of 40 mg/day (elderly, hepatic impairment or CYP2C19 poor metabolisers: max 20 mg/day).
- Administered orally as tablets (commonly 10 mg, 20 mg, 40 mg) or as an oral solution in some regions.
- Some people notice early improvements in 1–2 weeks, but clinically meaningful antidepressant effects usually take 4–6 weeks to emerge.
- Duration of action supports once-daily dosing; citalopram has a plasma half-life around 35 hours, so effects are maintained with daily intake.
- Avoid or limit alcohol while taking cipramil — alcohol can worsen depression and increase drowsiness, dizziness and other adverse effects.
- The most common side effec is nausea.
- Would you like to try cipramil without a prescription?
Basic Cipramil Information
- INN (International Nonproprietary Name): Citalopram
- Brand Names Available In Australia: not specified
- ATC Code: N06AB04
- Forms & Dosages: Tablets 10 mg, 20 mg, 40 mg; oral solution 10 mg/mL in some regions
- Manufacturers In Australia: not specified
- Registration Status In Australia: not specified
- OTC / Rx Classification: Prescription only (Rx)
Latest Research Highlights
Worried about whether citalopram still belongs in modern practice?
Recent systematic reviews and pooled analyses between 2022 and 2025 continue to rank citalopram among established SSRIs for major depressive disorder.
Effect sizes are described as modest but clinically meaningful for many patients, and comparable to other SSRIs.
Safety signals remain important in the evidence base.
Pooled analyses reinforce a dose‑dependent risk of QT prolongation when doses exceed 40 mg per day.
Guidance from recent analyses emphasises a lower maximum dose in older adults and CYP2C19 poor metabolisers.
Real‑world pharmacoepidemiology from primary care cohorts shows better adherence when cost barriers are reduced.
Discontinuation symptoms are consistently reported across trials and observational work.
Australian research highlights telehealth prescriptions boosting access while noting monitoring gaps in rural communities.
| Outcome | 2022–2025 Findings |
|---|---|
| Efficacy | Modest, clinically meaningful benefits similar to other SSRIs |
| Discontinuation | Withdrawal symptoms commonly reported after abrupt stop |
| QT Events | Risk dose‑dependent; concerns above 40 mg/day; lower caps for elderly/CYP2C19 poor metabolisers |
Clinical takeaways are straightforward.
Monitor ECG risk factors before dose escalation.
Counsel patients on withdrawal and plan gradual tapering.
Prefer lower starting doses for at‑risk groups such as older adults and known poor metabolisers.
Clinical Effectiveness In Australia
Are Australians actually getting the same benefit from citalopram as seen in trials?
In general practice and psychiatry settings across Australia, citalopram is a recognised SSRI choice for major depressive disorder.
Effectiveness in routine care mirrors international trial outcomes when patients complete adequate courses.
Expect an initial response after a minimum of four to six weeks and typical treatment durations of six to nine months for a single episode.
Standard starting dose in practice is 20 mg once daily with usual ranges of 20–40 mg daily.
TGA adverse‑event reporting reflects the common side effects seen globally such as nausea, insomnia and sexual dysfunction.
The TGA has also flagged occasional hyponatraemia or SIADH, especially in older patients.
PBS‑subsidised access and generic availability reduce out‑of‑pocket cost and are associated with improved persistence in observational datasets.
Pharmacists and GPs commonly advise ECG or electrolyte monitoring for patients with cardiac risks or complex polypharmacy.
- Monitoring Checkpoints: ECG where cardiac risk exists.
- Monitoring Checkpoints: Electrolytes if on diuretics or at risk of hyponatraemia.
- Monitoring Checkpoints: Medication review for interactions and concomitant anticoagulant use.
- Monitoring Checkpoints: Dose review at 2–4 weeks for tolerability and early response.
Indications & Expanded Uses
What is citalopram approved for and when is off‑label considered?
Primary, evidence‑backed indication is major depressive disorder.
Many clinicians prescribe citalopram off‑label for anxiety disorders, obsessive‑compulsive disorder and panic disorder depending on clinical judgement.
Citalopram is classified as an SSRI with ATC code N06AB04.
Australian practice usually mirrors international guidance in using citalopram as first‑line for suitable cases or as an alternative when other SSRIs are not tolerated.
Off‑label prescribing requires clear documentation and informed consent, especially in younger patients because of the risk of increased suicidality.
Pregnancy and breastfeeding require careful risk–benefit review and often specialist input.
- TGA‑Approved Indication: Major depressive disorder.
- Common Off‑Label Uses: Generalised anxiety disorder, OCD, panic disorder (use case dependent).
- Monitoring Expectations: Regular review of mood, side effects and safety monitoring when used off‑label.
Composition & Brand Landscape
Which formulations and brands are commonly encountered?
The active substance is the International Nonproprietary Name, citalopram.
Originator brands include Lundbeck’s Cipramil in Europe and Celexa in other markets such as the United States.
Generics are widely available and tablets are commonly supplied in 10 mg, 20 mg and 40 mg strengths.
Packaging varies between blister packs and bottles, and some regions offer a 10 mg/mL oral solution.
| Brand | Strengths | Likely PBS Listing Status |
|---|---|---|
| Cipramil | 10 mg, 20 mg, 40 mg | Generic/PBS listings vary by brand and formulation |
| Celexa | 10 mg, 20 mg, 40 mg | Brand availability depends on supplier; generics common |
| Generic Citalopram | 10 mg, 20 mg, 40 mg | Often PBS‑subsidised when listed |
In Australia, multiple generic manufacturers supply citalopram to the market; check the PBS for current subsidised brands and listings.
Pack labels may read either Citalopram or a brand name such as Cipramil or Celexa, so always check excipients if the patient has allergies.
Common retail outlets include community pharmacy chains and accredited online pharmacies such as Chemist Warehouse, Priceline and TerryWhite Chemmart.
Contraindications & Special Precautions
Who should avoid citalopram or take extra care?
Absolute contraindications include concomitant use with MAO inhibitors and with pimozide, and known hypersensitivity to the drug.
Relative contraindications require caution and monitoring.
These include a personal or family history of long QT syndrome, bradycardia, significant electrolyte disturbances and recent major cardiac events.
Elderly patients are at higher risk of QT prolongation and hyponatraemia and should generally be capped at 20 mg per day.
Pregnant or breastfeeding women should have specialist review to weigh maternal benefits against potential risks.
Consider Indigenous health contexts where comorbidities and access barriers can affect monitoring and follow‑up.
Advise patients not to drive or operate heavy machinery if drowsy or cognitively impaired after starting therapy.
- Absolute Contraindications: MAO inhibitors, pimozide, known hypersensitivity.
- Relative Contraindications: QT prolongation history, serious cardiac disease, seizure disorder, electrolyte imbalance.
- Monitoring Checklist: ECG if cardiac risk or interacting drugs are present.
- Monitoring Checklist: Check electrolytes where diuretics or dehydration are concerns.
Dosage Guidelines
How should citalopram be started, adjusted and stopped?
The usual adult starting dose is 20 mg once daily, with a typical therapeutic range of 20–40 mg once daily.
Do not exceed 40 mg per day because of the QT prolongation risk.
Special populations such as elderly patients over 60 years, those with hepatic impairment and CYP2C19 poor metabolisers should be limited to a maximum of 20 mg once daily.
Renal mild to moderate impairment generally does not require dose adjustment, but clinical monitoring is advised.
Expect some benefit within two to four weeks and advise continuation for six to 12 months after remission for a first episode.
Taper gradually when stopping to reduce withdrawal symptoms such as dizziness, sensory disturbances and mood changes.
- Initiation: Start 20 mg once daily for most adults.
- Titration: Increase cautiously to 40 mg only if needed and no cardiac risk factors are present.
- Monitoring At 2–4 Weeks: Check tolerability and early response; review interactions and adherence.
- Tapering: Reduce dose gradually over weeks when discontinuing rather than stopping abruptly.
For telehealth prescriptions, establish a clear remote monitoring plan and local pharmacy contact for supply and follow‑up.
Interactions Overview
Which medicines and drinks cause problems with citalopram?
Absolute interaction risks include MAO inhibitors and pimozide because of serious cardiac and serotonin‑related risks.
SSRIs like citalopram increase bleeding risk when used with antiplatelet or anticoagulant medicines and also when combined with NSAIDs.
CYP2C19 inhibitors can raise citalopram blood levels, so dose reductions may be necessary in these cases.
Alcohol is not strictly contraindicated, but it can worsen sedation and reduce antidepressant benefit and should be limited during treatment, especially while dosing is being adjusted.
Caffeine itself has no major pharmacokinetic interaction but can worsen anxiety and sleep disturbances.
| Interacting Drug Class | Mechanism | Management |
|---|---|---|
| MAO Inhibitors | Serotonin syndrome, severe reactions | Do not co‑prescribe; observe washout periods |
| Pimozide | Increased QT prolongation risk | Avoid combination |
| Anticoagulants / Antiplatelets | Increased bleeding risk | Monitor bleeding, consider dose review |
| CYP2C19 Inhibitors | Increased citalopram levels | Consider lower max dose, monitor for toxicity |
TGA adverse‑event data and e‑health reports note medication reconciliation gaps in aged‑care and rural regions, which increases interaction risk.
Cultural Perceptions & Patient Habits
What do Australians say about taking citalopram?
Community feedback and forums show cautious acceptance of SSRIs such as citalopram, with strong trust placed in pharmacists and GPs for guidance.
Cost sensitivity is real and PBS subsidies or discount pharmacy chains strongly influence whether patients continue therapy.
Rural and remote patients report telehealth prescriptions improve access but also reduce opportunities for face‑to‑face monitoring and timely ECGs or blood tests.
Culturally appropriate engagement with Indigenous health services improves uptake and ongoing care.
Online reviews commonly mention sexual side effects and withdrawal experiences as top concerns, and patients appreciate proactive counselling about these risks.
- Patient Concerns: Sexual side effects, weight changes and withdrawal symptoms.
- Access Barriers: Cost, pharmacy stock variation and limited local monitoring in remote areas.
- Communication Tips: Use clear, culturally sensitive language and set expectations about time to benefit and follow‑up plans.
Availability & Pricing Patterns
Where can Australians buy citalopram and how much will it cost?
Citalopram is available through community pharmacies and accredited online pharmacies that verify prescriptions.
Major chains include Chemist Warehouse, Priceline and TerryWhite Chemmart, along with many independent pharmacies.
PBS listing status varies by brand and formulation, and generic options typically reduce the patient cost when PBS‑subsidised.
Private, unsubsidised purchase leads to higher out‑of‑pocket expenses, and price‑sensitive shoppers often compare unit prices across chains.
| Purchase Route | Typical Cost Pattern |
|---|---|
| PBS‑Subsidised Generic | Lowest out‑of‑pocket cost for concession and general patients when listed |
| Private Purchase (Brand) | Higher cost; varies by supplier and pharmacy |
| Online Pharmacy | Competitive pricing but ensure accredited supplier and verified prescription |
Stock and brand substitution can vary between urban and rural pharmacies, so patients should check local availability and PBS listings for exact cost.
In our online pharmacy, cipramil is available without a prescription, with discreet delivery to Australia in 5-14 days.
Comparable Medicines And Preferences
How does citalopram compare with other SSRIs commonly used in Australia?
Common alternatives include escitalopram, sertraline, fluoxetine and paroxetine.
Escitalopram is often chosen for tolerability reasons.
Sertraline is frequently used when comorbid anxiety or insomnia is prominent.
Fluoxetine has a long half‑life that can be advantageous for adherence or where missed doses are an issue.
Choice of agent depends on prior response, side‑effect sensitivity, cardiac risk, drug interactions and PBS status.
- Pros/Cons Checklist: Side effects profile comparison for sexual dysfunction and sedation.
- Pros/Cons Checklist: Interaction burden and monitoring needs such as ECG for QT risk.
- Pros/Cons Checklist: PBS coverage and cost differences that affect persistence.
Discussing these practical differences with the patient helps tailor treatment and improve adherence in real‑world settings.
FAQ Section
Will citalopram make me gain weight?
Some people report weight changes while on citalopram, but substantial weight gain is uncommon.
Monitor diet and exercise, and discuss alternative medicines if weight becomes a problem.
Is citalopram safe in pregnancy?
Safety in pregnancy requires specialist review.
Decisions weigh maternal benefit against possible fetal risks and may involve psychiatry input.
How long until it works and can I stop suddenly?
Expect initial benefits after two to four weeks and a minimum acute course of four to six weeks.
Do not stop suddenly; taper slowly to reduce withdrawal symptoms.
Do I need an ECG?
An ECG is not routine for all adults.
Consider ECG for patients with cardiac disease, on interacting medicines, electrolyte disturbances or at higher doses.
Guidelines For Proper Use
What should pharmacists say when dispensing citalopram?
Begin by verifying the indication and current medicines, with particular attention to MAO inhibitors, pimozide and anticoagulants.
Advise a starting dose of 20 mg once daily for most adults and a maximum of 40 mg per day unless there are risk factors.
For elderly patients, those with hepatic impairment or known CYP2C19 poor metaboliser status, limit the dose to 20 mg once daily.
Warn about common side effects including nausea, insomnia and sexual dysfunction and the possibility of withdrawal on abrupt cessation.
Recommend baseline checks including BP/HR, medication reconciliation and consider ECG and electrolyte testing where cardiac risk exists.
Discuss PBS concession eligibility, options for generic substitution and supply through major pharmacy chains or accredited online pharmacies.
Set follow‑up at two to four weeks and again at six to 12 weeks to review response and tolerability.
- Initiation: Confirm indication and review medications for interactions.
- Monitoring: Check ECG and electrolytes for patients with cardiac risk or relevant comorbidity.
- Escalation: Only increase dose after assessing tolerability and absence of QT risk factors.
- Cessation/Taper: Reduce dose gradually over weeks rather than stopping abruptly.
Use culturally appropriate communication for Indigenous patients and arrange telehealth follow‑up plans for rural patients where face‑to‑face monitoring is limited.
Delivery Across Australia
| City | Region | Delivery time |
|---|---|---|
| Sydney | New South Wales | 5–7 days |
| Melbourne | Victoria | 5–7 days |
| Brisbane | Queensland | 5–7 days |
| Perth | Western Australia | 5–7 days |
| Adelaide | South Australia | 5–7 days |
| Hobart | Tasmania | 5–7 days |
| Canberra | Australian Capital Territory | 5–7 days |
| Darwin | Northern Territory | 5–9 days |
| Gold Coast | Queensland | 5–9 days |
| Newcastle | New South Wales | 5–9 days |
| Wollongong | New South Wales | 5–9 days |
| Townsville | Queensland | 5–9 days |