
Chloroquine
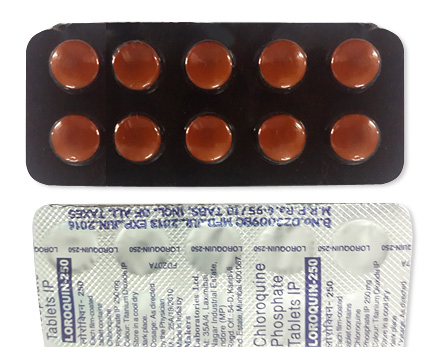
Chloroquine
- In our pharmacy, you can buy chloroquine without a prescription, with delivery across Australia in 5–14 days and discreet packaging; note that chloroquine is prescription-only in most countries, so purchase without a prescription may not be legal everywhere.
- Chloroquine is used to treat acute malaria, certain protozoal infections (amebiasis) and as a disease‑modifying agent in rheumatic conditions (eg, rheumatoid arthritis, SLE); it acts as an antiprotozoal/antimalarial by concentrating in the parasite food vacuole to inhibit haem polymerisation and raises lysosomal pH, plus it has immunomodulatory effects in rheumatic disease.
- Usual doses: for acute malaria in adults 600 mg base initially, then 300 mg base at 6, 24 and 48 hours (total 1.5 g base); for rheumatoid disease 250–500 mg daily; paediatric doses are weight‑based (eg, 10 mg/kg initial, then 5 mg/kg at 6, 24 and 48 hours for malaria).
- Forms of administration: oral tablets (commonly 100 mg, 150 mg, 250 mg, 500 mg), syrup/solution for children (eg, 50 mg/5 ml) and limited-use injectable preparations.
- Onset time: symptom relief for malaria is often within 24–48 hours; for rheumatologic effects onset is slower and may take several weeks to months.
- Duration of action: chloroquine is long‑acting with a prolonged terminal half‑life (drug may persist in tissues for weeks to months); an acute antimalarial course is typically three days, while rheumatology treatment is maintained long‑term.
- Alcohol warning: avoid excessive alcohol while taking chloroquine—alcohol can worsen liver injury and gastrointestinal or neurological side effects; use cautiously in people with liver disease.
- The most common side effect is nausea (others include headache, itching—especially in some populations—loss of appetite and abdominal pain; long‑term/high‑dose use risks retinopathy and cardiomyopathy).
- Would you like to try chloroquine without a prescription?
Latest Research Highlights
Basic Chloroquine Information
- INN (International Nonproprietary Name): Chloroquine
- Brand Names Available In Australia: Aralen (United States); Nivaquine (France); Lariago, Emquin (India); Emzor Chloroquine, Nivaquine (Nigeria); Reuquinol, Difosfato de Cloroquina (Brazil); Chloroquin (Southeast Asia). Exact packaging and availability should be verified with Australian registries.
- ATC Code: P01BA01 — Chloroquine (antimalarial agent) within antiprotozoals/antimalarials.
- Forms & Dosages: Tablets 100 mg, 150 mg, 250 mg, 500 mg; syrup 50 mg/5 ml (paediatric); limited injectable forms (150 mg base/ml).
- Manufacturers In Australia: not specified (international suppliers include Sanofi, Ipca Laboratories, Bayer, Novartis; local manufacture varies by market).
- Registration Status In Australia: not specified (chloroquine remains registered for antimalarial and selected rheumatology uses in many countries; check TGA listings for local status).
- OTC / Rx Classification: Prescription Only (Rx) in nearly all countries due to toxicity risk and need for monitoring.
Worried about recent studies and safety signals for chloroquine?
Recent international research from 2022–2024 reconfirms chloroquine’s narrow, evidence-based role as an antimalarial for chloroquine-sensitive species while artemisinin-based combination therapies have largely superseded it where resistance is common.
Large randomised trials and pooled systematic reviews after 2020 found no clinical benefit for COVID-19 and raised concerns about cardiac toxicity and neurotoxicity at higher or unsupervised doses.
Australian pharmacovigilance and TGA safety reports noted sporadic off‑label use after the pandemic with QTc prolongation signals in some adverse-event reports.
Rheumatology cohorts in high-income settings continued to show benefit for systemic lupus erythematosus and rheumatoid arthritis at low maintenance doses, with ophthalmic risk linked to cumulative dose and duration.
Resistance mapping from Southeast Asia, Africa and South America shows variable chloroquine sensitivity, useful for some P. vivax pockets but not first-line for most endemic P. falciparum.
Clinical safety emphasis remains on cardiac monitoring and retinal screening when chloroquine or hydroxychloroquine is used long term.
Clinical Effectiveness In Australia
Are Australians still treated with chloroquine and when is it effective?
Chloroquine’s footprint in Australia is small and largely specialist-driven, with TGA registration maintained for specific antimalarial and some rheumatology uses.
PBS listing for chloroquine is limited, and most antimalarial treatment for travellers uses artemisinin-based combinations or atovaquone/proguanil instead.
For confirmed chloroquine-sensitive P. vivax or legacy P. falciparum strains, the standard acute regimen (600 mg base initial then 300 mg at 6, 24 and 48 hours) remains effective in achieving cure.
WHO and Australian infectious-disease guidance typically favour artemisinin-based combination therapies where resistance or treatment failures are likely.
TGA adverse-event surveillance emphasises cardiotoxicity (QT prolongation, arrhythmia) and retinopathy with long-term use, driving routine ophthalmology screening in rheumatology practice.
Hospital procurement and state data show minimal routine chloroquine dispensing compared with hydroxychloroquine and newer antimalarials.
Pharmacists should confirm the intended indication and check My Health Record for prior antimalarial exposure before dispensing chloroquine tablets in Australia.
Indications And Expanded Uses
What is chloroquine officially used for, and where do clinicians use it off‑label?
TGA-registered indications generally include antimalarial treatment for chloroquine-sensitive infections and selected rheumatologic uses, similar to international approvals.
Clinically in Australia, chloroquine is used for acute chloroquine-sensitive malaria and as maintenance therapy for some SLE or RA cases, though hydroxychloroquine is often preferred.
Occasional parasitic indications such as adjunctive treatment for amebiasis are recognised by clinicians in specific scenarios.
Off‑label use spiked during the COVID‑19 pandemic but was discouraged after efficacy and safety reviews from major authorities.
Infectious-disease specialists now generally reserve chloroquine for documented sensitivity or when alternatives are contraindicated.
Rheumatologists favour low-dose, weight-adjusted regimens and baseline and ongoing retinal screening to balance benefit with risk.
Pregnancy and breastfeeding require specialist review and tailored decision-making, with many clinicians opting for alternatives when appropriate.
- TGA-Approved: Antimalarial treatment; selected rheumatologic indications.
- Off-Label (historical): COVID‑19 (not recommended); limited parasitic uses.
Composition And Brand Landscape
Which brands and strengths of chloroquine might you encounter?
The active ingredient is chloroquine, supplied as base or as phosphate salt under the INN chloroquine and ATC code P01BA01.
Global brand names include Aralen (US), Nivaquine (France), Lariago and Emquin (India), and regional generics such as Emzor and Reuquinol.
Formulations internationally include tablets 100–500 mg, paediatric syrup (50 mg/5 ml) and limited injectable preparations at 150 mg base/ml.
In Australia, commercial availability is limited and stock is typically sourced via hospital formularies or special orders rather than routine retail shelves.
Manufacturing sources are predominantly international, so pharmacists performing special imports check batch provenance and TGA import authorisations.
When advising travellers, clinicians and pharmacists commonly recommend alternatives that are more readily stocked and PBS-covered.
- Common Tablet Strengths: 100 mg, 150 mg, 250 mg, 500 mg.
- Typical Supply Channels In Australia: Hospital pharmacy, special import, travel clinic supply.
Contraindications And Special Precautions
Who should not take chloroquine and which patients need extra caution?
Absolute contraindications include known hypersensitivity to chloroquine or related compounds, preexisting retinal disease, and a history of epilepsy.
Relative contraindications requiring close monitoring include liver or renal impairment, psoriasis, porphyria, myasthenia gravis and significant alcohol misuse.
Concurrent use with QT-prolonging drugs is a key safety concern because of additive cardiac toxicity risk.
Special Australian considerations include older people in residential aged care who have higher arrhythmia risk and First Nations patients with comorbid chronic conditions who need culturally safe monitoring plans.
Pregnancy and breastfeeding require specialist input; clinicians should weigh risks and benefits carefully.
Daily-life advice includes avoiding heavy machinery or driving if dizziness or blurred vision occurs and limiting alcohol to reduce GI and neuro adverse effects.
- High-Risk Checks Pre-Prescription: ECG if cardiac disease or interacting medications; baseline retinal exam for planned long-term therapy.
- Emergency Note: Overdose is life-threatening; seek emergency care for arrhythmia or seizures.
Dosage Guidelines
How is chloroquine dosed for different conditions in Australia?
Standard adult acute malaria dosing is 600 mg base initially, then 300 mg base at 6, 24 and 48 hours (total 1.5 g base).
Paediatric malaria dosing is weight-based: 10 mg/kg base initially followed by 5 mg/kg base at 6, 24 and 48 hours.
Rheumatology maintenance doses are typically 250–500 mg daily, adjusted by weight and cumulative exposure to reduce retinopathy risk.
Amebiasis regimens used as adjuncts may start at 600 mg base daily for two days then 300 mg daily for 2–3 weeks under supervision.
Dose adjustments are required in hepatic or renal impairment, in the elderly, and always for children on a mg/kg basis.
Pharmacists must be careful converting base versus phosphate salt strengths and confirm the formulation when counselling on chloroquine dosage.
- Malaria (Adult): 600 mg base then 300 mg at 6, 24, 48 hours.
- Rheumatology (Adult): 250–500 mg once daily, with regular monitoring.
Interactions Overview
Which medicines and foods should you avoid with chloroquine?
Major interaction risk comes from additive QT-prolonging agents such as macrolide antibiotics, fluoroquinolones and some antipsychotics, increasing arrhythmia risk.
Other interactions include drugs that lower seizure threshold and agents that affect hepatic metabolism, which can alter chloroquine levels.
Concurrent hydroxychloroquine use is redundant and increases toxicity risk without added benefit.
TGA reports after the pandemic recorded interaction-related admissions where unsupervised combinations contributed to adverse cardiac events.
Alcohol can worsen liver toxicity and neuro side effects, so counsel patients to minimise alcohol while taking chloroquine.
Community pharmacists should check My Health Record and current medicines before dispensing chloroquine tablets in Australia to identify interacting therapies.
- High-Risk Drug Classes: Macrolides, fluoroquinolones, antiarrhythmics, certain antipsychotics, anaesthetics.
Cultural Perceptions And Patient Habits
How do Australian patients view chloroquine and what access issues arise?
Many Australians trust pharmacists and PBS guidance and are cost-conscious, often searching popular chains or online pharmacies for price and availability.
During the COVID‑19 period, social media and forums amplified off‑label interest, leading to supply pressure and many community questions handled by pharmacists.
Rural and remote communities face limited local stock and longer waits for special imports, increasing reliance on telehealth prescriptions and hospital formularies.
First Nations patients may need culturally appropriate counselling and logistic support for monitoring such as retinal checks, where access barriers exist.
Because chloroquine has limited PBS presence, routine community use is reduced and specialist or hospital supply becomes more important for continuity of care.
Pharmacies offering travel consultations lean toward alternatives that are easier to source and supported by PBS reimbursement for travellers.
Availability And Pricing Patterns
Where can Australians get chloroquine and what will it cost?
Chloroquine is prescription-only and not commonly stocked by mainstream retail pharmacies; major chains usually order on request or dispense hydroxychloroquine instead.
Online pharmacies and telehealth services can facilitate e‑prescriptions, but the supply often comes from hospital stock or special importers, affecting price and lead time.
PBS coverage is sparse for chloroquine; when not PBS-listed, private prices vary widely depending on brand and import costs.
Rural clinics typically rely on hospital formularies or special-access schemes, which can add delivery time compared with urban pharmacies.
In our online pharmacy, chloroquine is available without a prescription, with discreet delivery to Australia in 5–14 days.
Storage guidance requires room temperature (15–25°C) and secure keeping out of reach of children to prevent accidental ingestion.
| Supply Channel | Typical Cost Pattern |
|---|---|
| Hospital Formulary | Often supplied; covered for inpatients or specialist clinics |
| Special Import / Travel Clinic | Variable private cost; lead time 5–14 days |
| Retail Pharmacy (on request) | May incur ordering fee; limited stock |
Comparable Medicines And Preferences
What are the practical alternatives to chloroquine in Australia?
Hydroxychloroquine offers a better safety profile for long-term rheumatic disease management and is preferred by many rheumatologists.
Artemisinin-based combination therapies (ACTs) are first-line for most malaria cases in areas with chloroquine resistance and are commonly used for travellers.
Mefloquine is reserved for particular resistant regions and primaquine is used for radical cure of P. vivax infections alongside blood schizonticides.
Atovaquone/proguanil is another traveller-friendly option that is PBS-listed in some indications and well suited to short-notice procurement.
Choice depends on local resistance patterns, pregnancy status, comorbidities and PBS coverage that affects affordability and adherence.
- Pros/Cons Quick Guide: Chloroquine — low cost, but resistance and cardiac/retinal risks; Hydroxychloroquine — safer for rheumatology; ACTs — best for resistant malaria.
Frequently Asked Questions
Can I buy chloroquine over the counter in Australia?
No — chloroquine is Prescription Only (Rx) in Australia; consult your GP, specialist or an accredited telehealth clinician for a valid prescription.
Is chloroquine safe for long-term arthritis treatment?
Long-term use requires specialist oversight, dose limits (commonly 250–500 mg daily) and regular ophthalmology screening to detect retinopathy; hydroxychloroquine is often preferred for chronic rheumatic disease.
Can I use chloroquine for COVID‑19?
No — high-quality trials showed no benefit for COVID‑19 and regulators including the TGA advise against off‑label use due to safety concerns.
What should I do for a missed dose or suspected overdose?
If you miss a dose, take it as soon as you remember unless it is almost time for the next dose; do not double-dose.
For overdose, seek emergency care immediately; chloroquine overdose can cause life-threatening arrhythmias, seizures and respiratory problems.
Guidelines For Proper Use
What should pharmacists counsel patients about when dispensing chloroquine?
Confirm the indication, check prescription validity and ensure dosing is clearly calculated by base versus salt strength.
Review My Health Record or medication history for interacting medicines and ask about cardiac history, vision problems and seizure disorders.
Advise baseline retinal screening before long-term use and annual screening thereafter, and obtain ECG where cardiac risk or QT-prolonging co‑medications exist.
Provide clear storage advice: store at 15–25°C, protect from light and moisture, and keep out of reach of children.
When PBS does not cover therapy, discuss cost, sourcing (special import versus hospital supply) and safer alternatives such as hydroxychloroquine or ACTs.
Document culturally appropriate follow-up plans for Indigenous and rural patients, and provide written action plans and emergency overdose instructions.
| Monitoring Point | Timeline |
|---|---|
| Baseline retinal exam | Before starting long-term therapy |
| Annual retinal screening | Annually after the first year or earlier if cumulative dose high |
| ECG | Baseline if cardiac risk factors; repeat if symptoms or interacting drugs added |
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Darwin | Northern Territory | 5-7 days |
| Gold Coast | Queensland | 5-7 days |
| Newcastle | New South Wales | 5-9 days |
| Wollongong | New South Wales | 5-9 days |
| Cairns | Queensland | 5-9 days |
| Townsville | Queensland | 5-9 days |
| Geelong | Victoria | 5-9 days |
| Bendigo | Victoria | 5-9 days |