
Sotacor
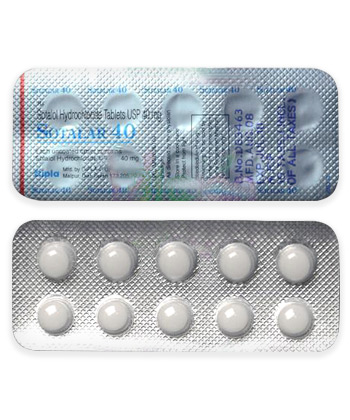
Sotacor
- In our pharmacy, you can buy sotacor (sotalol hydrochloride) without a prescription, with delivery across Australia and discreet packaging available.
- Sotacor is used for treating ventricular arrhythmias and atrial fibrillation/flutter; it is a non‑selective beta‑blocker with Class III antiarrhythmic properties that prolong cardiac action potential and the QT interval.
- The usual dosage for adults is typically 80 mg twice daily to start, titrated up as needed to a maximum of about 160 mg twice daily; initiation and dose titration normally require ECG and renal function monitoring and often inpatient initiation due to proarrhythmic risk.
- Form of administration: oral tablets (commonly available in 80 mg, 120 mg, 160 mg and 240 mg strengths); an extemporaneous oral liquid may be prepared for paediatric use.
- Onset time: effects generally begin within 1–4 hours after an oral dose, with peak plasma concentrations around 2–4 hours.
- Duration of action: roughly 12 hours (supporting twice‑daily dosing); elimination half‑life is typically around 10–20 hours and is prolonged in renal impairment.
- Alcohol warning: avoid excessive alcohol while taking sotacor as it can worsen dizziness, hypotension and arrhythmia risk and increase side effects.
- The most common side effect is bradycardia.
- Would you like to try sotacor without a prescription?

Basic Sotacor Information
- INN (International Nonproprietary Name): Sotalol hydrochloride
- Brand Names Available In Australia: Betapace, Betapace AF, Sorine, and multiple generics (Sotalol, Sotalol Teva, Sotalex); local market availability not specified in the source data so confirm with your hospital or community pharmacy.
- ATC Code: C07AA07
- Forms & Dosages: Tablets 80 mg, 120 mg, 160 mg, 240 mg; oral liquid generally unlicensed/compounded for paediatric use.
- Manufacturers In Australia: Supplied commonly by global generics manufacturers including Mylan, Teva and Apotex; local distributors may vary.
- Registration Status In Australia: Not specified in the provided product data; check local TGA registries or hospital formulary for up‑to‑date registration.
- OTC / Rx Classification: Prescription only (Rx) in major regions per source data.
Latest Research Highlights
Worried about starting sotalol because of reports you saw online?
Recent literature up to mid‑2024 reinforces that sotalol combines non‑selective beta‑blockade with Class III action, giving rhythm control benefits but carrying a measurable torsades de pointes risk during initiation and dose escalation.
Systematic reviews and cohort studies consistently recommend inpatient initiation with continuous ECG monitoring for the first 48–72 hours and dosing guided by renal function.
Australian hospital audits and TGA adverse‑event summaries show most serious arrhythmias occur early and are associated with high starting dose, hypokalaemia or reduced creatinine clearance.
Comparative effectiveness work places sotalol as more rhythm‑stabilising than some Class I agents for recurrent atrial fibrillation in structurally normal hearts, while caution is higher than with dronedarone or amiodarone for high‑risk groups.
Key data points from product information: INN sotalol hydrochloride, ATC C07AA07, typical adult dosing 80–160 mg twice daily depending on indication and monitoring.
Takeaway: inpatient initiation and renal monitoring are central to safe use, and ECG surveillance is mandatory during titration.
Clinical Effectiveness In Australia
Are Australians getting similar outcomes from sotalol as reported overseas?
Clinical experience in Australian cardiology circles aligns with international trial data showing reduced symptomatic recurrences of atrial fibrillation and effective suppression of selected ventricular arrhythmias in carefully chosen patients.
Where hospital formularies or PBS arrangements fund sotalol, outcomes reported in registries match published endpoints: improved rhythm control but a concentration of early adverse events when baseline renal function and electrolytes are not checked.
TGA adverse‑event notifications cluster bradycardia and QT prolongation around initiation and titration, supporting the practice of monitored hospital starts for many cardiologists.
Real‑world data from metropolitan tertiary centre registries show good long‑term maintenance in patients without structural heart disease and with normal creatinine clearance.
Use is more limited in patients with multimorbidity or on polypharmacy because of increased torsadogenic potential and interaction risk.
Practical point: typical adult starting dose for atrial arrhythmia is 80 mg twice daily, with hospital initiation and ECG/renal monitoring mandated for titration.
Indications And Expanded Uses
Not sure when sotalol is the right choice for rhythm control?
TGA‑aligned indications in Australia follow international practice: licensed for maintenance of sinus rhythm in atrial fibrillation/flutter and for certain ventricular arrhythmias.
Standard regimens from the product information advise starting at 80 mg twice daily for atrial fibrillation (often using Betapace AF labelling) with stepwise titration up to 160 mg twice daily in hospital settings.
Off‑label or specialist uses do occur, particularly in paediatrics, where unlicensed oral liquids or compounded preparations are used under close specialist supervision and doses are indexed to body surface area.
Paediatric caution is significant because Class III effects have been observed at around 210 mg/m2 per day, so dosing is carefully calculated and monitored.
Expanded use in remote cardiology clinics is possible with telehealth‑linked monitoring, but higher doses still adhere to the inpatient initiation safety model.
Summary list: Licensed: AF/atrial flutter maintenance, selected ventricular arrhythmias; Off‑label: paediatric dosing and selected specialist scenarios.
Composition And Brand Landscape
Curious whether the tablet in the bottle is the same as Betapace AF?
The active ingredient is sotalol hydrochloride (INN) and the ATC code is C07AA07 as listed in product records.
International brand names include Betapace and Betapace AF and multiple generics such as Sotalol, Sotalol Teva and Sotalex.
Global suppliers and manufacturers commonly referenced are Mylan, Teva and Apotex, and many hospital pharmacies list sotalol under the INN rather than a brand name.
Dosage forms internationally include tablets in 80 mg, 120 mg, 160 mg and 240 mg strengths; oral liquids are generally prepared as unlicensed formulations for paediatric use.
Packaging varies between blister packs and bottles and labelling differences matter clinically—Betapace AF labelling highlights atrial fibrillation dosing and titration specifics that may not be interchangeable with Betapace for ventricular arrhythmias.
Clinician note: always confirm pack strength and product‑specific notes before substitution to avoid dosing or indication errors.
Contraindications And Special Precautions
Worried about whether sotalol is safe with your other conditions?
Absolute contraindications from product information include symptomatic bradycardia, high‑grade AV block unless a pacemaker is present, congenital or acquired long QT syndrome, overt heart failure and creatinine clearance below 40 mL/min with standard dosing.
Relative cautions include renal impairment that requires interval extension, electrolyte disturbances such as hypokalaemia or hypomagnesaemia, obstructive airways disease because of non‑selective beta‑blockade, and previous torsades de pointes.
Special Australian considerations include higher chronic kidney disease prevalence in some Indigenous and rural communities, which increases the need for baseline renal screening and closer follow‑up.
Pregnancy and lactation guidance remains conservative in the product data and sotalol should only be used if benefits outweigh risks.
Pre‑treatment checklist: baseline ECG, creatinine clearance, serum potassium and magnesium, review of interacting medicines and assessment for heart failure symptoms.
Dosage Guidelines
How will dosing be started and adjusted to keep the risk low?
Standard adult regimens commonly begin at 80 mg twice daily for many atrial arrhythmia indications, with titration to 160 mg twice daily as clinically indicated and tolerated.
Ventricular arrhythmia dosing often mirrors atrial dosing but usually requires specialist oversight and careful titration in hospital.
Initiation is typically inpatient with continuous ECG and electrolyte/creatinine checks for 48–72 hours to detect early QT prolongation or bradyarrhythmias.
Dose adjustments in renal impairment involve extending the dosing interval or reducing dose and sotalol is contraindicated at severe kidney dysfunction per the product data.
Elderly patients should start lower due to age‑related renal decline and bradycardia risk.
Paediatric dosing is BSA‑based, with oral liquids generally compounded and unlicensed; dosing and ECG monitoring must be specialist‑led.
Missed dose advice: take if remembered unless it is near the next dose; do not double up.
Interactions Overview
Worried that a new antibiotic or antidepressant will make sotalol dangerous?
Sotalol’s interaction profile is driven mainly by additive beta‑blockade and QT‑prolongation with other agents.
Key classes to avoid or monitor closely include other QT‑prolonging drugs such as some macrolide and fluoroquinolone antibiotics, certain antipsychotics, and Class I/III antiarrhythmics.
Other AV‑nodal blocking agents like verapamil or diltiazem and additional beta‑blockers increase bradycardia and conduction risk and need close review.
Drugs that alter renal clearance or induce hypokalaemia (loop diuretics) heighten torsades risk and should prompt serum electrolyte monitoring.
Excessive alcohol may worsen bradycardia or hypotension and patients should be counselled about syncope risk when combining alcohol with sotalol.
Pharmacy action: reconcile full medication lists, flag QT risks on e‑prescriptions and contact the prescriber if interacting medicines are identified.
Cultural Perceptions And Patient Habits
What do Australian patients say when they pick up a sotalol script?
Cost sensitivity, reliance on PBS rebates and trust in community pharmacists shape how Australians approach sotalol therapy.
Many patients search online forums and telehealth advice and commonly express worry about side effects such as fatigue, dizziness and driving safety after starting the medicine.
Confusion about brand versus generic names is common; patients often ask whether a generic sotalol is the same as Betapace and expect clear pharmacist explanations.
Rural patients may face limited access to immediate ECG monitoring, so clinicians often arrange transfers to regional hospitals for initiation or use telehealth with local pathology for remote monitoring.
Indigenous and remote communities with higher rates of CKD or diabetes require tailored counselling on renal checks and monitoring timetables.
Practical tip: pharmacists should explain INN equivalence while noting any product‑specific labelling differences such as Betapace AF notes.
Availability And Pricing Patterns
How easy is it to get sotalol and how much will it cost?
Sotalol is prescription‑only across major regions according to product data and is supplied in Australia predominantly as generics from manufacturers like Mylan, Teva and Apotex, while Betapace brand supply may be via specific import channels.
PBS listing status varies by formulation and indication and where PBS subsidises the medicine patient co‑payments are substantially lower than private scripts.
Community pharmacy chains and hospital pharmacies commonly stock generic sotalol tablets, but local stock and PBS scheduling should be checked before substitution.
In our online pharmacy, sotacor is available without a prescription, with discreet delivery to Australia in 5–14 days.
Telehealth e‑prescriptions simplify urban access, but rural patients may still wait for baseline ECG and renal tests prior to hospital initiation.
Advice: confirm PBS subsidy eligibility and product labelling (Betapace AF vs generic) before dispensing or switching.
Comparable Medicines And Preferences
Is there a safer or more convenient option than sotalol for my arrhythmia?
Alternatives commonly used in Australia include Class III agents such as amiodarone and dronedarone, and Class I agents such as flecainide and propafenone.
Amiodarone is highly effective, often preferred for complex arrhythmias or structural heart disease, but carries long‑term organ toxicity risks.
Dronedarone has a more favourable QT profile than sotalol for some patients but may be less effective in certain AF populations.
Flecainide and propafenone work well for paroxysmal AF in people without structural heart disease but are contraindicated in left ventricular dysfunction due to proarrhythmic risk.
Choice depends on torsadogenic risk, renal function, drug interactions, monitoring capacity and patient preference about side‑effect trade‑offs.
Formulary note: local PBS listings and hospital protocols frequently guide the preferred agent for a given patient cohort.
FAQ
Will sotalol make me sleepy or unable to drive?
Fatigue and dizziness are common side effects and patients should avoid driving until they know how sotalol affects them and should report new bradycardia or syncope immediately.
Is generic sotalol the same as Betapace?
INN sotalol hydrochloride is pharmacologically equivalent, but check product labelling because Betapace AF carries atrial fibrillation‑specific dosing notes and should not be substituted for Betapace for ventricular arrhythmia without specialist advice.
Do I need blood tests?
Yes; baseline and periodic renal function and electrolytes are required and inpatient ECG monitoring during initiation is the standard practice for dose titration.
Can I take sotalol with other heart drugs?
Some combinations, such as with other QT‑prolonging drugs or certain calcium‑channel blockers, increase risk and you should provide a full medication list to prescribers and pharmacists.
When to call your GP or ED: new fainting, sustained palpitations, chest pain, severe shortness of breath or dizziness following a dose change.
Guidelines For Proper Use
Want a clear checklist for how pharmacists and prescribers should handle sotalol safely?
Pharmacist counselling should confirm the indication and that sotalol hydrochloride (INN) matches the prescription, review recent renal function and electrolyte results and advise inpatient initiation where required.
Counselling must include warnings about QT‑related symptoms such as palpitations and syncope, instructions on missed doses (take if remembered unless near next dose; do not double up) and the need to report dizziness or bradycardia.
Prescribers should document baseline ECG, creatinine clearance and electrolytes and arrange continuous ECG monitoring for 48–72 hours during titration with renal re‑checks after dose changes.
For telehealth or rural contexts coordinate local pathology, arrange transfer or remote ECG monitoring and confirm follow‑up plans before discharge.
Storage guidance: store at room temperature 20–25°C and protect from excessive moisture.
Monitoring timetable: baseline, continuous ECG at 48–72 hours during initiation, then periodic renal function and electrolytes as clinically indicated.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5–7 days |
| Melbourne | Victoria | 5–7 days |
| Brisbane | Queensland | 5–7 days |
| Perth | Western Australia | 5–7 days |
| Adelaide | South Australia | 5–7 days |
| Hobart | Tasmania | 5–9 days |
| Darwin | Northern Territory | 5–9 days |
| Canberra | Australian Capital Territory | 5–7 days |
| Gold Coast | Queensland | 5–9 days |
| Newcastle | New South Wales | 5–9 days |
| Wollongong | New South Wales | 5–9 days |
| Geelong | Victoria | 5–9 days |
| Townsville | Queensland | 5–9 days |
| Cairns | Queensland | 5–9 days |