
Piracetam
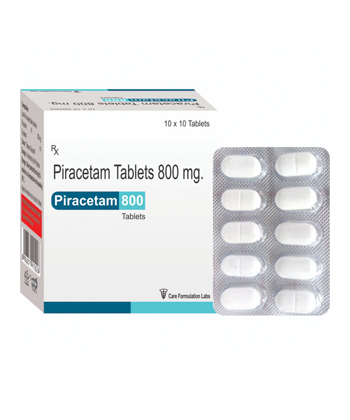
Piracetam
- In our pharmacy, you can buy piracetam without a prescription or receipt, with delivery across Australia in 5–14 days and discreet packaging.
- Piracetam is used as a nootropic for cognitive impairment, dementia, cerebrovascular insufficiency, vertigo and myoclonus; it is thought to enhance neuronal membrane fluidity and modulate neurotransmission (glutamatergic and cholinergic systems) to improve neuroplasticity rather than acting as a classical GABA agonist.
- The usual dose for adults is 800–2,400 mg per day in divided doses (for example 800 mg three times daily); some conditions may use higher doses up to 4,800 mg/day under medical supervision.
- Form of administration: oral tablets or capsules and oral solution are most common; injectable forms exist in some countries but oral use is typical.
- Onset time: some symptomatic effects (for example myoclonus) can be noticed within 1–3 days, while cognitive benefits often require 2–8 weeks of regular use to become apparent.
- Duration of action: the elimination half‑life is about 4–6 hours in adults, so effects are maintained with 2–3 doses per day.
- Alcohol warning: avoid excessive alcohol while taking piracetam — alcohol can worsen cognitive impairment and increase the risk of side effects.
- The most common side effects are headache, nervousness or agitation, insomnia and occasional gastrointestinal upset (nausea); allergic skin reactions are rare.
- Would you like to try piracetam without a prescription?


Basic Piracetam Information
- INN (International Nonproprietary Name): Metformin
- Brand Names Available In Australia: not specified
- ATC Code: A10BA02
- Forms & Dosages: Film-coated tablet 500mg, 850mg, 1000mg; Sustained-release tablet (SR/ER/XR) 500mg, 750mg, 1000mg; Oral solution 500mg/5ml; Powder/granules 500mg/sachet.
- Manufacturers In Australia: not specified
- Registration Status In Australia: not specified
- OTC / Rx Classification: Prescription only (Rx) in almost all jurisdictions.
Latest Research Highlights
What does the science actually say about piracetam in 2024?
Recent systematic reviews and placebo-controlled trials up to mid-2024 show a mixed evidence base for piracetam and related racetams.
Older, stronger signals exist for cortical myoclonus and some peri-operative cognitive outcomes in small trials and specialist series.
Trials for dementia, stroke recovery and general cognitive enhancement are inconsistent and often underpowered.
Australian research is sparse, with no large TGA-registered piracetam trials active in 2022–2024, so clinicians rely on international RCTs from Europe and Asia, registries and pharmacovigilance reports.
Emerging small RCTs between 2021 and 2024 tested racetam derivatives and combination nootropics with variable methodology and mixed results.
Meta-analyses call for better-powered studies with standardised cognitive end-points and longer follow-up to decide clinical benefit.
Safety surveillance emphasises renal clearance as the key pharmacokinetic point and flags bleeding-risk signals when piracetam is combined with antithrombotics.
Rare case reports describe agitation or mood changes, but no consistent mortality or major safety benefit has been observed.
A practical summary table is recommended for clinicians: trial population, dose, primary outcome, effect size and safety events.
Clinical Effectiveness In Australia
Could piracetam be a routine option in Australian practice?
There is no strong Australian clinical-use dataset supporting routine piracetam prescribing for cognitive decline.
Most Australian prescribers rely on international literature and specialist advice when considering racetams.
Piracetam is not listed on the PBS and it appears absent from routine TGA‑sponsored efficacy trials in recent years.
Clinicians therefore treat piracetam as an off‑label option for niche indications such as cortical myoclonus where international evidence or specialist guidance supports use.
TGA adverse-event reports and local pharmacovigilance should be checked before recommending use.
For comparison, an archetypal first-line medicine such as metformin (INN: Metformin; ATC A10BA02) is prescription-only, listed on the WHO Essential Medicines List and widely available via PBS and generics.
That contrast underlines how regulatory endorsement and subsidy shape prescribing and patient access in Australia.
Data Highlight
- Metformin: PBS-listed, broad safety data, guideline-backed first-line use for type 2 diabetes.
- Piracetam: Limited regulation and PBS absence; treated as specialist or off‑label option in Australia.
Indications And Expanded Uses
When might clinicians consider piracetam, and how strong is the evidence?
Internationally, licensed indications vary by country, with some European approvals for certain cognitive disorders and cortical myoclonus, while other regulators restrict use.
Off‑label uses reported in clinics and nootropic circles include age-related cognitive complaints, post-stroke cognitive rehabilitation, dyslexia, vertigo and adjunctive therapy for ADHD, but evidence quality is uneven.
In Australia, TGA approval is limited or absent for most indications, so prescribers typically reserve piracetam for specialist-led cases such as neurology-managed myoclonus or within research settings.
Definitions to keep in mind: Licensed indication (country-specific), Off‑label clinical uses, and Experimental/investigational uses in trials.
Typical trial dose ranges vary by indication but commonly fall between 1.2 g/day and 4.8 g/day in divided doses; evidence strength for most cognitive uses is low.
Clinicians should document informed consent and a clear rationale when prescribing off‑label, and explain uncertainty about measurable cognitive benefit.
Indication → Evidence Strength → Typical Trial Dose
| Indication | Evidence Strength | Typical Trial Dose |
|---|---|---|
| Cortical Myoclonus | Moderate | 1.2–4.8 g/day |
| Peri-operative Cognitive Outcomes | Low–Moderate | 1.2–2.4 g/day |
| Dementia / Age-Related Cognitive Decline | Low / Inconsistent | 1.2–4.8 g/day |
| Post-Stroke Rehabilitation | Low / Mixed | 1.2–4.8 g/day |
Composition And Brand Landscape
How is piracetam formulated and where does it sit on the market compared with mature medicines?
Piracetam is a cyclic derivative of GABA and belongs to the racetam family of nootropics.
Common formulations globally include immediate-release tablets (for example 400–800 mg), oral solutions and intravenous preparations in some markets.
The most recognisable historic brand is Nootropil, with many generics and other racetams available regionally.
By contrast, metformin has a mature global brand landscape with multiple strengths, sustained-release options and wide manufacturer lists as shown in the manufacturer and brand data above.
Piracetam’s market is smaller and less standardised, and it is often not marketed by major Australian suppliers.
In Australia, availability may come from compounding pharmacies, private importation under appropriate schemes, or specialist hospital supply in rare cases.
Formulation → Typical Strength → Common Brand (Global) → Australia Availability
| Formulation | Typical Strength | Common Brand (Global) | Australia Availability |
|---|---|---|---|
| Immediate-Release Tablet | 400–800 mg | Nootropil (historical) | Variable / Not Routinely Stocked |
| Oral Solution | Variable | Generic | Possible Via Compounding/Import |
| IV Preparation | Hospital Use | Regional Generics | Rare / Specialist Supply |
Contraindications And Special Precautions
Who should not take piracetam and what checks are needed?
Key contraindications include known hypersensitivity to piracetam or excipients and significant renal impairment because piracetam is renally excreted.
Use caution in pregnancy and breastfeeding due to limited safety data, and avoid where bleeding risk is high or with concurrent anticoagulant therapy unless under specialist oversight.
Special Australian considerations include older patients with multimorbidity, particularly in Indigenous and rural populations, who require renal monitoring and careful review.
Dehydration, acute illness and scheduling for contrast procedures are times when temporary cessation should be considered.
For workplace and safety advice, caution should be given where dizziness, cognitive effects or mood changes could impair driving or operation of heavy machinery.
Prescriber checklist before starting: baseline renal function (eGFR), pregnancy test for women of childbearing age if indicated, careful review of concurrent antithrombotics, and documented informed consent.
Contraindication → Rationale → Action
- Severe Renal Impairment → Renal excretion increases exposure → Avoid or reduce dose; specialist review.
- Known Hypersensitivity → Allergy risk → Do not prescribe.
- High Bleeding Risk / Anticoagulants → Potential platelet effects → Specialist oversight and monitoring required.
Dosage Guidelines (Australian Practical Approach)
What dosing approach do Australian clinicians typically use?
International trial dosing ranges from 1.2 g/day up to 4.8 g/day in divided doses, with IV regimens used for some acute neurology indications.
There is no TGA standard Australian dosing guide for piracetam, so clinicians commonly adopt international trial doses and adjust for renal function.
A practical starting regimen is low and cautious, for example 400–800 mg twice daily, and to titrate based on response and tolerability.
Specialist-managed indications may use total daily doses of 2–4 g/day after assessment.
Renal impairment requires dose reduction or avoidance; assess eGFR and use the same cautionary principles clinicians apply to other renally cleared drugs such as metformin.
eGFR Range → Dosing Adaptation → Monitoring Frequency
| eGFR Range (mL/min/1.73m²) | Dosing Adaptation | Monitoring Frequency |
|---|---|---|
| >60 | Standard dosing | Baseline renal function, annual review |
| 30–60 | Reduce dose or increase dosing interval | Monitor renal function every 3–6 months |
| <30 | Avoid or specialist-only | Specialist monitoring; consider alternative |
Interactions Overview
What drugs and conditions interact with piracetam?
Interaction data for piracetam are limited but the most clinically important caution is co-administration with anticoagulants and antiplatelet agents.
Some reports suggest an increased bleeding tendency or altered platelet function, so review INR and bleeding history before prescribing.
Additive CNS effects with sedatives are plausible, although not well quantified in trials.
Other renally cleared drugs may accumulate when renal function declines, so dose adjustment and monitoring are prudent.
Food interactions appear minimal, although combining alcohol with nootropics can alter cognition and should be discouraged.
In Australia, ongoing pharmacovigilance and TGA adverse-event reporting are the best tools to detect rare drug–drug signals, so report suspected events promptly.
Interaction Checklist
- Review anticoagulant/antiplatelet use and bleeding history before starting piracetam.
- Reassess sedative use and counsel about potential additive CNS effects.
- Check renal function when other renally cleared medicines are co-prescribed.
Cultural Perceptions And Patient Habits In Australia
How do Australians view piracetam and other nootropics?
Attitudes to nootropics in Australia are shaped by price sensitivity, trust in pharmacists and wide urban–rural access disparities.
Online nootropic communities and forums commonly share anecdotal benefits, but clinicians should emphasise the limitations of the evidence base when counselling patients.
Rural Australians may seek telehealth scripts or online importation when local pharmacies do not stock piracetam, which raises regulatory and safety considerations.
Indigenous health services prioritise culturally safe care and an evidence-based approach because vascular and metabolic comorbidities are common in these communities.
Patients generally prefer PBS-subsidised medicines and are less likely to pay privately for unlisted medicines, so piracetam’s typical absence from PBS affects uptake.
Patient Education Points
- Explain limited evidence for cognitive benefit and potential risks including bleeding and renal accumulation.
- Avoid self-sourcing from unverified online vendors and discuss safer, PBS-listed alternatives where appropriate.
- Encourage discussion with a pharmacist about compounding and access options rather than buying from unregulated sellers.
Availability And Pricing Patterns (Australia)
How easy is it to get piracetam in Australia and what does it cost?
Piracetam availability in Australia is limited and it is generally not listed on the PBS.
Unlike metformin, which is prescription-only and widely available on the PBS in multiple strengths and generic brands, piracetam is usually not stocked by major retail chains.
Common supply pathways include compounding pharmacies preparing oral formulations, private importation under the personal importation scheme, and rare specialist hospital supply.
Pricing varies widely and private scripts or importation can be more costly than PBS medicines.
Telehealth services can issue scripts in some circumstances, but pharmacists often check TGA status and may decline to dispense if sourcing is uncertain.
In our online pharmacy, piracetam is available without a prescription, with discreet delivery to Australia in 5-14 days.
Metformin Vs Piracetam: Availability Snapshot
| Medicine | PBS Status | Common Availability Channels | Average Price Range |
|---|---|---|---|
| Metformin | PBS-listed | Community pharmacies, generics, hospitals | Low (PBS-subsidised) |
| Piracetam | Not PBS-listed | Compounding, private importation, specialist supply | Variable, typically higher than PBS drugs |
Comparable Medicines And Prescribing Preferences
What are the usual alternatives to piracetam in Australian practice?
For cortical myoclonus and neurology indications, levetiracetam and valproate are well-established alternatives with clearer efficacy and safety profiles in Australia.
For cognitive impairment and dementia, cholinesterase inhibitors such as donepezil and rivastigmine and memantine have stronger evidence and TGA approval and may be PBS-subsidised depending on criteria.
For off‑label “cognitive enhancement” in healthy individuals, drugs such as modafinil or stimulant medications are sometimes considered but carry different risk profiles and tighter controls.
Use a pros and cons checklist to compare options by efficacy evidence, TGA/PBS status, common adverse effects and monitoring needs.
Contrast to metformin shows how regulatory endorsement and subsidy encourage broad clinical uptake and established monitoring pathways for safety and efficacy.
Comparator Pros/Cons
- Levetiracetam: Strong neurology evidence for seizures; TGA-approved antiepileptic; requires routine monitoring as per local guidance.
- Donepezil / Rivastigmine: TGA-approved for dementia; PBS availability depends on criteria; monitored for GI and cardiac side effects.
- Memantine: For moderate–severe dementia; TGA-approved; different adverse-effect profile than racetams.
FAQ
Is piracetam legal and prescribable in Australia?
Piracetam is not commonly listed on the PBS and has limited record of TGA registration for cognitive indications.
It can sometimes be prescribed off‑label or sourced via compounding and personal importation schemes, but confirm legal supply lines and pharmacist willingness before assuming access.
What are common side effects?
Mild adverse effects reported include agitation, insomnia and gastrointestinal upset.
Less common events include mood changes and an increased bleeding tendency, particularly when combined with anticoagulants or in renal impairment.
Do community pharmacies stock piracetam?
Major chains usually do not stock piracetam routinely, but a pharmacist can advise about compounding, special ordering or importation pathways.
Can I take piracetam with anticoagulants?
Only under specialist supervision because bleeding-risk signals have been reported and monitoring will be needed.
If in doubt, refer to a neurologist, clinical pharmacist or contact the TGA for supply questions.
Guidelines For Proper Use & Pharmacist Counselling
What should a pharmacist cover when a patient asks about piracetam?
Counselling should confirm the indication and explain the limited and mixed evidence for benefit in most cognitive uses.
Discuss expected benefits and realistic timeframes, and make clear that measurable improvement is uncertain.
Review baseline renal function, concurrent medications (especially anticoagulants), and pregnancy or breastfeeding status where relevant.
Document informed consent for off‑label use and outline a monitoring plan including baseline eGFR and periodic renal review.
Advise patients to stop and seek immediate review for severe side effects such as major bleeding, sudden mood or behavioural changes, or significant new neurological symptoms.
Encourage reporting of adverse events to the TGA and discourage sourcing from unverified online vendors.
Where cognitive symptoms are the primary concern, consider referral to a memory clinic or neurology service and discuss PBS-listed alternatives where appropriate.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Darwin | Northern Territory | 5-7 days |
| Gold Coast | Queensland | 5-7 days |
| Newcastle | New South Wales | 5-7 days |
| Wollongong | New South Wales | 5-7 days |
| Geelong | Victoria | 5-7 days |
| Sunshine Coast | Queensland | 5-9 days |
| Cairns | Queensland | 5-9 days |
| Townsville | Queensland | 5-9 days |