
Retin-a Gel
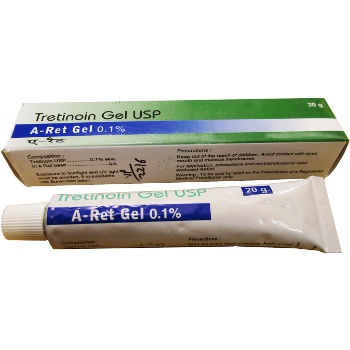
Retin-a Gel
- Retin‑A gel is officially a prescription‑only medicine in most countries, including Australia, but availability varies — some community pharmacies and online sellers may supply tretinoin/Retin‑A gel without a prescription or receipt; check your local pharmacy or reputable online supplier.
- Retin‑A (tretinoin) is used mainly for acne vulgaris and sometimes off‑label for photoageing/wrinkles; it is a topical retinoid that normalises follicular cell turnover, reduces comedone formation and inflammation, and promotes epidermal remodelling and collagen synthesis.
- Usual dosing is a thin layer applied once daily (typically at bedtime) to the affected area; common gel strengths include 0.01% and 0.025% (creams up to 0.05–0.1% for other indications); start with the lowest concentration if you have sensitive skin.
- The form of administration is topical application to intact skin (gel or cream from a tube); avoid eyes, lips, mucous membranes and broken skin.
- Initial effects can appear within 2–4 weeks (often with an initial flare or increased irritation); meaningful clinical improvement is commonly seen by 6–12 weeks of regular use.
- The duration of action is maintained only with ongoing regular use — benefits accumulate over months and are sustained while treatment continues; skin cell turnover is about 3–4 weeks so changes are gradual.
- Avoid using alcohol‑based or harsh astringent products on treated areas; topical gels may be flammable so avoid open flames and smoking during/after application — occasional alcohol consumption does not produce a systemic interaction but alcohol‑containing skin products increase irritation risk.
- The most common side effect is local skin irritation — redness, dryness, peeling and stinging/tingling; more severe reactions (blistering, swelling) require medical review.
- Would you like to try retin‑a gel without a prescription?




Basic Retin-A Gel Information
- INN (International Nonproprietary Name): Tretinoin
- Brand Names Available In Australia: not specified
- ATC Code: D10AD01
- Forms & Dosages: Gel 0.01% and 0.025%; Cream 0.025%, 0.05%, 0.1%; Lotion and solution vary by market or are compounded
- Manufacturers In Australia: not specified
- Registration Status In Australia: not specified
- OTC / Rx Classification: Prescription Only (Rx)
Latest Research Highlights
How quickly will you notice a real difference with tretinoin and what are the common trade-offs?
Recent Australian and international literature from 2020–2024 continues to support that topical tretinoin is effective for both comedonal and inflammatory acne and for long‑term improvement in photoaging when used consistently.
Measurable benefits typically begin between six and 12 weeks, with lesion‑count reductions appearing in most meta‑analyses.
Irritation — erythema and peeling — is the most commonly reported adverse event across studies.
Comparative trials show newer retinoids such as adapalene often have a lower irritation profile, while advances in tretinoin formulation — micronised particles and polymer‑based gels/creams — aim to improve skin delivery and tolerability.
Combination regimens (retinoid plus benzoyl peroxide or a topical antibiotic) deliver superior clearance in moderate acne but require attention to formulation compatibility to avoid potency loss or increased irritation.
Australian dermatology centres report similar outcomes, and telederm follow‑ups improve adherence and continuation especially in rural patients.
| Study | Population | Outcome | Safety |
|---|---|---|---|
| Meta‑analyses (2020–2024) | Mixed adults/teens | Consistent lesion‑count reduction at 6–12 weeks | Irritation common (redness, peeling) |
| Comparative Trials | Retinoid users | Adapalene similar efficacy, less irritation | Lower dermatitis rates with adapalene |
| Formulation Studies | Topical tretinoin formulations | Micronised/polymer gels improve delivery | Better tolerability reported vs older gels |
Common strengths in clinical practice remain 0.01%–0.1% in gel or cream form.
Clinical Effectiveness In Australia
Will tretinoin work for your acne if you live in Australia and don’t see a dermatologist regularly?
Australian clinical practice mirrors global evidence: tretinoin provides meaningful improvement in acne over weeks to months when adherence is maintained.
The Therapeutic Goods Administration (TGA) regulates tretinoin as a prescription medicine, so it is typically started in primary care or by a dermatologist.
Real‑world audits and clinic series show patients often discontinue due to local irritation rather than lack of efficacy.
Public subsidy via the Pharmaceutical Benefits Scheme (PBS) for tretinoin is limited and inconsistent, so many prescriptions are privately paid for, which affects uptake among price‑sensitive patients.
TGA pharmacovigilance highlights photosensitivity reports and contact dermatitis clusters linked to concurrent abrasive treatments or improper skin care.
In rural and remote settings telehealth e‑prescriptions, pharmacist counselling and mail‑order pharmacies help maintain continuity of care and adherence.
| Category | Australian Data Highlights |
|---|---|
| TGA Adverse Events | Photosensitivity, local dermatitis, irritation |
| PBS Availability | Limited / mostly private prescriptions |
Pharmacist counselling is an important tool to reduce discontinuation and improve outcomes.
Indications And Expanded Uses
What is tretinoin officially approved for, and what do clinicians use it for off‑label?
TGA‑approved primary indication in Australia is treatment of acne vulgaris, with common formulations including gel 0.01% and 0.025% and creams at 0.025%, 0.05% and 0.1%.
Off‑label but widely practised uses include photodamage and fine‑line reduction using higher strength creams (0.05%–0.1%) under specialist supervision, where clinicians document collagen remodelling benefits balanced against more irritation.
Other limited specialist uses include selected keratinisation disorders where a dermatology team monitors response and local tolerability.
Absolute contraindications include pregnancy and known hypersensitivity to tretinoin or excipients, and tretinoin should not be applied to broken or eczematous skin.
- TGA‑Approved: Acne vulgaris (typical strengths as above).
- Common Off‑Label: Photoaging, fine lines (specialist use), selected keratinisation conditions.
Off‑label prescribing checklist: obtain informed consent, document clinical rationale, counsel on contraception for women of childbearing potential and schedule close follow‑up.
Composition And Brand Landscape
Which brands and strengths are commonly seen in pharmacies and what forms do they take?
The INN is tretinoin and international brand names include Retin‑A and multiple generics supplied by Janssen and other manufacturers.
Typical pharmaceutical forms and concentrations available from the dataset are gel 0.01% and 0.025% and creams at 0.025%, 0.05% and 0.1%.
Packaging internationally commonly uses tubes of 15–45 g, though exact Australian pack sizes are not specified in the raw dataset.
The Australian market contains originator products and generics supplied via major pharmacy chains and independent chemists, with exact brand availability depending on supplier contracts and stock.
| Form | Concentrations | Typical Brands / Manufacturers | Australian Availability Note |
|---|---|---|---|
| Gel | 0.01%, 0.025% | Retin‑A, generics (Janssen, Glenmark, Actavis) | Generics common; exact brands vary by supplier |
| Cream | 0.025%, 0.05%, 0.1% | Retin‑A cream, international generics | Higher strengths used under specialist supervision |
Because PBS listing is uncommon for many tretinoin products, generic options reduce cost for private prescriptions.
Contraindications And Special Precautions
Who should not use tretinoin and what extra care is needed for particular Australians?
Absolute contraindications are known allergy to tretinoin or excipients and pregnancy or breastfeeding; despite low systemic absorption, topical retinoids are avoided in pregnancy as a precaution.
Avoid application to sunburned, eczematous or otherwise damaged skin.
Special Australian considerations include counselling women of childbearing potential about contraception and pregnancy testing where clinically appropriate.
Indigenous and remote communities may have higher baseline photodamage and sensitivity; clinicians should tailor regimens and emphasise clear skincare education in culturally safe ways.
Elderly patients can be more reactive and benefit from lower starting strengths and slower titration.
Occupational precautions: gels can be flammable so avoid smoking or open flames during application, and workers with heavy UV exposure should be counselled on timing and strict sun protection.
- Contraindications: Pregnancy, breastfeeding, known hypersensitivity, application to broken skin.
- Precautions: Pause tretinoin before and after waxing, dermabrasion or chemical peels; avoid concurrent abrasive soaps and strong exfoliants.
Dosage Guidelines
How do you start tretinoin and what should you expect during the first months?
Standard dosing is to apply a thin layer once nightly to affected areas, commonly for acne management.
Begin with lower strengths such as gel 0.01% or cream 0.025% for sensitive skin and consider alternate‑night dosing initially.
Expect an early transient worsening of acne in weeks two to four and full responses often by six to 12 weeks with continued use.
Children are generally treated from age 12 with lower concentrations; younger children are not typically approved for tretinoin use.
Elderly patients usually require no formal dose adjustment but may tolerate lower strength or reduced frequency better.
For photoaging, higher strength creams (0.05%–0.1%) are used under specialist supervision with closer monitoring for irritation.
| Indication | Strength | Frequency | Notes |
|---|---|---|---|
| Acne | Gel 0.01%–0.025% or Cream 0.025% | Once nightly | Start low, titrate; expect 6–12 week improvement |
| Photoaging | Cream 0.05%–0.1% | Once nightly (specialist supervision) | Higher irritation risk; contraception counselling for women |
Missed dose guidance: apply when remembered but do not double up; overuse increases irritation without added benefit.
Interactions Overview
Can tretinoin be mixed with other acne or cosmetic products?
Systemic drug interactions are negligible due to minimal systemic absorption, but topical interactions are important.
Concurrent use with other exfoliants such as salicylic acid or glycolic acid, abrasive cleansers, or strong topical steroids increases irritation risk.
Benzoyl peroxide can oxidise tretinoin and may reduce its potency if mixed directly; clinical practice often spaces applications (retinoid at night and benzoyl peroxide in the morning) or uses formulations designed for compatibility.
Avoid procedural interactions: professional keratolytic procedures, dermabrasion or chemical peels should be paused before and after tretinoin use to reduce adverse events.
Alcohol‑based skin products and strong astringents can worsen dryness and stinging when combined with tretinoin.
| Topical Agent | Compatibility | Advice |
|---|---|---|
| Benzoyl Peroxide | Potentially incompatible if mixed | Use at different times or use compatible combo products |
| Adapalene | Similar class | Choose based on tolerability; avoid doubling retinoids |
| Salicylic/Glycolic Acid | Can increase irritation | Use cautiously; stagger use or reduce frequency |
Report unexpected severe dermatitis or systemic symptoms to the TGA adverse event reporting systems via your pharmacist or prescriber.
Cultural Perceptions And Patient Habits
What do Australians commonly worry about when starting tretinoin?
Common themes from patient feedback and pharmacy interactions are concern about irritation, sensitivity to price, and strong trust in pharmacist advice.
Urban patients frequently access dermatology clinics and telehealth, while rural and remote patients rely more on pharmacists, mail‑order services and telederm e‑prescriptions to reduce travel.
Outdoor lifestyles and regular sun exposure in many parts of Australia make sun‑safety counselling a central part of achieving adherence and preventing photosensitivity.
Price‑sensitive consumers often request generics or pharmacist‑recommended alternatives because PBS coverage for many topical tretinoin products is limited.
Younger patients influenced by social media may misapply products or expect rapid results, so pharmacy and GP counselling corrects dosing and sets realistic timelines.
Culturally and linguistically diverse (CALD) and Indigenous patients benefit from culturally safe communication, translated instructions or pictorial handouts to reduce misuse and adverse events.
Availability And Pricing Patterns
How easy is it to get tretinoin in Australia and what can you expect to pay?
Topical tretinoin is classified as prescription‑only and is stocked across major pharmacy chains and independent chemists, while online pharmacies and telehealth services broaden access.
PBS coverage is limited for most tretinoin products so cost is commonly private, with generics used to reduce price where available.
Imported or online‑sourced products may appear cheaper but carry authenticity and regulatory risks; the TGA advises caution with unregulated imports.
Rural pricing variation and intermittent stockouts occur; community pharmacists often provide therapeutic substitution advice or temporary compounding if a commercial product is unavailable.
In our online pharmacy, retin‑a gel is available without a prescription, with discreet delivery to Australia in 5–14 days.
| Channel | Typical Pricing/Availability Note |
|---|---|
| Brick‑and‑Mortar Pharmacies | Private scripts; generics may be cheaper |
| Online Pharmacies / Telehealth | Broader access; verify regulatory compliance |
| Compounding | Used when specific formulations unavailable |
Ask your pharmacist about private pricing, generic options and any available subsidy pathways for your condition.
Comparable Medicines And Preferences
What are the common alternatives to tretinoin and when might they be preferred?
Alternatives commonly used in Australia include adapalene, tazarotene, benzoyl peroxide, azelaic acid and topical antibiotics, alone or in combination.
Adapalene typically offers similar efficacy with better tolerability for many patients and is a go‑to when irritation is a concern.
Tazarotene can be more potent but often causes more irritation and is typically reserved for specialist use or refractory cases.
Benzoyl peroxide is effective for reducing Cutibacterium acnes counts and is useful in combination therapy but can be drying and may oxidise tretinoin.
Azelaic acid suits sensitive skin and helps with post‑inflammatory hyperpigmentation and is often an alternative when retinoids are unsuitable, for example in pregnancy.
| Drug | Efficacy | Tolerability | Use Case | PBS Status |
|---|---|---|---|---|
| Adapalene | High for acne | Generally better tolerated | Sensitive skin, first‑line topical retinoid | Varies; some formulations subsidised |
| Benzoyl Peroxide | Antibacterial, effective | Can be drying | Combine with antibiotics or retinoids (timing matters) | Generally private |
| Azelaic Acid | Moderate for acne; good for pigmentation | Well tolerated | Pregnancy alternative, sensitive skin | Varies |
Choice depends on skin sensitivity, pregnancy plans, cost and patient preference.
Frequently Asked Questions
- How long until I see results? — Expect initial changes in 6–12 weeks; adherence is key and an early flare is possible.
- Can I use tretinoin while pregnant or breastfeeding? — No; topical retinoids are contraindicated in pregnancy; discuss alternatives and contraception with your prescriber.
- Can I use sunscreen and moisturiser with tretinoin? — Yes; use a non‑comedogenic moisturiser to reduce irritation and apply broad‑spectrum SPF 30+ every day.
- Is tretinoin available on the PBS? — Generally prescribed privately; PBS listing is limited so check with your pharmacist for subsidised alternatives.
- How can I reduce irritation? — Start with a lower strength or every‑other‑night application; consider short contact, buffering with moisturiser and a gentle cleanser.
Pharmacists can provide quick action points: demonstrate pea‑sized dose, advise sunscreen and document contraception counselling where relevant.
Guidelines For Proper Use
What should a pharmacist tell a patient when handing over tretinoin?
Confirm the prescription and explain the indication and expected timeline of six to 12 weeks for visible improvement.
Demonstrate the amount to use (pea‑sized) and show application to clean, dry skin at night while avoiding eyes, lips and broken skin.
Recommend gentle, non‑foaming cleansers, non‑comedogenic moisturisers and daily broad‑spectrum SPF 30+.
Advise pausing tretinoin before waxing, chemical peels or dermabrasion and document contraception counselling for women of childbearing potential.
Start sensitive patients on alternate nights and reassess at four to eight weeks to escalate or adjust as tolerated.
Encourage reporting of severe reactions to the TGA and arrange GP or dermatology follow‑up if blistering or intense swelling occurs.
- Checklist For Counselling: confirm indication, show application, advise sun protection, document contraception advice, schedule follow‑up.
For telehealth prescriptions include written instructions and pharmacist check‑ins for rural patients to support adherence and safety.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5–7 days |
| Melbourne | Victoria | 5–7 days |
| Brisbane | Queensland | 5–7 days |
| Perth | Western Australia | 5–7 days |
| Adelaide | South Australia | 5–7 days |
| Canberra | Australian Capital Territory | 5–7 days |
| Hobart | Tasmania | 5–9 days |
| Darwin | Northern Territory | 5–9 days |
| Gold Coast | Queensland | 5–7 days |
| Newcastle | New South Wales | 5–7 days |
| Wollongong | New South Wales | 5–7 days |
| Geelong | Victoria | 5–7 days |
| Townsville | Queensland | 5–9 days |
| Cairns | Queensland | 5–9 days |
| Alice Springs | Northern Territory | 5–9 days |