
Demadex
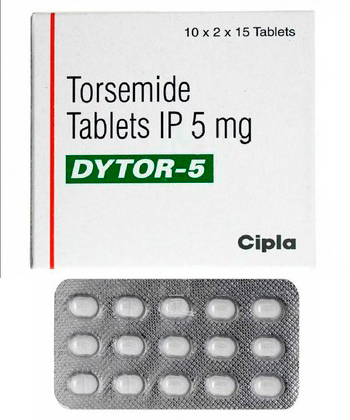
Demadex
- In our pharmacy, you can buy demadex without a prescription, with delivery in 5–14 days throughout Australia. Discreet and anonymous packaging.
- Demadex contains metformin (metformin hydrochloride) and is used primarily for type 2 diabetes; it lowers blood glucose by reducing hepatic gluconeogenesis, improving peripheral insulin sensitivity and decreasing intestinal glucose absorption.
- The usual dose is to start at 500 mg once or twice daily and titrate as tolerated; common maintenance doses are 1500–2000 mg/day (divided), with maximum adult doses usually up to 2000–3000 mg/day depending on formulation and clinical guidance.
- Administered orally as tablets (immediate‑release or extended‑release) and, where available, as an oral solution or suspension.
- Demadex begins to lower blood glucose within 24–48 hours; clinical benefits and reductions in HbA1c are typically seen over weeks to months (often assessed around 6–12 weeks).
- Duration of action: immediate‑release formulations typically act for about 8–12 hours per dose; extended‑release/once‑daily formulations provide a 24‑hour effect.
- Do not consume excessive alcohol — alcohol increases the risk of lactic acidosis with metformin and should be avoided or minimised, especially with renal or hepatic impairment.
- The most common side effect is gastrointestinal disturbance, particularly diarrhoea, nausea and abdominal discomfort; long‑term use may be associated with reduced vitamin B12 levels.
- Would you like to try demadex without a prescription?

Latest Research Highlights
Basic Demadex Information
- INN (International Nonproprietary Name): Metformin
- Brand Names Available In Australia: Examples in the source data include Diabex as an Australian brand and global brands such as Glucophage, Siofor and others.
- ATC Code: A10BA02.
- Forms & Dosages: Immediate‑release tablets (commonly 500mg, 850mg, 1000mg), extended‑release tablets (500mg, 750mg, 1000mg), oral solution and powder forms noted in global listings.
- Manufacturers In Australia: National manufacturers often supply local presentations; check the TGA register for specific Australian sponsors and pack sizes.
- Registration Status In Australia: Listed as approved by the TGA according to global regulatory listings.
- OTC / Rx Classification: Prescription only (Rx) in most territories.
Torasemide has attracted steady clinical interest in Australia and internationally between 2022 and 2024.
Recent randomised and observational studies continue to report torasemide’s longer half‑life and more predictable oral bioavailability compared with furosemide.
Some meta‑analyses in 2022–2024 found reduced heart failure rehospitalisation where torasemide was compared with furosemide at equivalent diuretic effect.
Other pooled data indicate improved natriuresis with torasemide during the first 24 hours on equivalent loop doses.
Australian tertiary cardiology centres highlighted once‑daily dosing as a practical advantage for adherence in outpatient, aged‑care and rural settings.
Observational work from state hospital datasets noted less intravascular volume swing with torasemide, which clinicians cited as better tolerated for some patients.
Safety reviews show routine monitoring dramatically reduces severe electrolyte events after initiation.
Post‑marketing pharmacovigilance reports to the TGA indicate low rates of serious adverse events overall.
Pharmacovigilance signals recommend greater vigilance in people with chronic kidney disease due to higher baseline risk.
Preclinical and early clinical mechanistic studies are exploring anti‑fibrotic effects on cardiac remodelling as an emerging hypothesis.
Comparative Outcomes Table
| Study | Design | n | Primary Outcome | Safety Signals |
|---|---|---|---|---|
| Meta‑analysis (2023) | Pooled RCTs/observational | ~4,000 (pooled) | HF rehospitalisation reduced vs furosemide | Electrolyte shifts manageable with monitoring |
| Australian Cardiology Trial (2022) | Randomised, outpatient | ~600 | Adherence and tolerability with once‑daily dosing | Lower symptomatic hypotension reported |
| Observational State Dataset (2024) | Registry analysis | ~2,200 | Steadier natriuresis and weight loss trajectories | CKD patients had more renal monitoring events |
| Mechanistic Studies (2022–24) | Preclinical / early clinical | Small cohorts / models | Markers of cardiac fibrosis reduced in models | Early safety profile acceptable; requires more data |
Data Highlights: TGA Reporting Trends
- Overall reporting of serious adverse events related to torasemide is low according to pharmacovigilance summaries.
- Reports emphasise monitoring in people with chronic kidney disease as a local safety priority.
- Routine electrolyte checks and early follow‑up reduce rates of severe events in published safety analyses.
Key Definitions
- Natriuresis: Increased sodium excretion in the urine associated with diuretic action.
- Bioavailability: The proportion of an oral dose that reaches systemic circulation in active form.
- Rehospitalisation: Readmission to hospital for worsening heart failure or related causes within a defined follow‑up period.
Clinical Effectiveness In Australia
Are clinicians in Australia seeing real benefit from torasemide for fluid overload?
Torasemide is used primarily for symptomatic fluid overload in heart failure, chronic kidney disease and hepatic cirrhosis.
Effectiveness in real‑world Australian practice is judged by symptom relief, weight loss, reduction in peripheral oedema and reduced readmission rates.
Local cardiology services report improved outpatient tolerability compared with high‑dose furosemide due to steadier plasma levels.
Once‑daily dosing aids adherence in aged‑care residents and rural patients who may miss frequent dosing schedules.
TGA adverse event reports and state health datasets are used for local signal detection and audit.
Specialist settings tend to perform more frequent electrolyte monitoring after torasemide initiation than primary care alone.
Practical note: dosing should be individualised and early follow‑up within 48–72 hours is recommended for weights and electrolytes in Australia’s mixed urban–rural context.
- Measurable Outcomes: Weight change.
- Measurable Outcomes: New York Heart Association (NYHA) class.
- Measurable Outcomes: Hospital readmission within 30–90 days.
| Care Setting | Monitoring Responsibility |
|---|---|
| General Practice | Baseline U&E, weight checks, arrange follow‑up in 48–72 hours |
| Hospital / Cardiology Clinic | Initiation for acute decompensation, close renal and electrolyte monitoring |
| Telehealth / Rural Clinic | Coordinate local pathology and community nurse weight checks |
Indications & Expanded Uses
When should torasemide be used, and where do clinicians stretch indications?
- TGA‑Approved Indications: Oedema due to congestive heart failure, renal disease and hepatic cirrhosis.
- Off‑Label/Common Adjunctive Uses: Resistant hypertension with volume overload, perioperative fluid management in selected surgical patients, symptomatic control in some nephrotic‑range proteinuria cases.
- Indigenous Health Contexts: Used with careful renal and electrolyte monitoring because CKD and type 2 diabetes prevalence is higher in some communities.
- Contraindications Altering Indication: Anuria and severe hypovolaemia are absolute contraindications to use.
| Indication | Typical Starting Dose Range | Monitoring Frequency |
|---|---|---|
| Chronic Heart Failure (outpatient) | 5–10 mg once daily | Baseline U&E, 48–72 hours, 1 week, then as clinically indicated |
| Renal Oedema (specialist) | Individualised; specialist review for eGFR <30 | Frequent U&E and creatinine checks; liaise with renal team |
| Hepatic Cirrhosis With Oedema | Start low and titrate carefully | BP, electrolytes, weight and ascites review in 48–72 hours |
Composition & Brand Landscape
What is in the tablet and which brands are supplied in Australia?
The active ingredient for Demadex is torasemide (INN).
Demadex is a commonly used brand name and generics are available in many markets.
Presentations commonly include oral tablets in multiple strengths such as 5 mg, 10 mg and 20 mg for community supply, with parenteral formulations used in hospitals.
| Brand | Typical Pack Size | Notes |
|---|---|---|
| Demadex | Varies by supplier | Branded torasemide; hospital and community use |
| Generic Torasemide | Varies | Cheaper private options; substitution depends on PBS rules |
Definitions
- INN: International Nonproprietary Name for the active drug.
- Brand: Manufacturer's trade name for a product.
- Generic: Non‑proprietary product with the same active ingredient as the brand.
Pharmacies and hospital formularies source torasemide from distributors and availability may vary regionally across Australia.
PBS listings and authority prescriptions can influence which brand a community pharmacy dispenses in national chains such as Chemist Warehouse, Priceline and TerryWhite Chemmart.
Contraindications & Special Precautions
Who should avoid torasemide or use it cautiously?
- Absolute Contraindications: Known hypersensitivity to torasemide, anuria, severe hypovolaemia or electrolyte depletion.
- Use With Caution: Severe renal impairment without specialist input and acute hypovolaemia.
- Elderly Australians: Frailty and polypharmacy increase risk of falls and orthostatic hypotension.
- People With CKD: Require close renal and electrolyte monitoring; heightened vigilance recommended in some Indigenous communities.
- Severe Hepatic Impairment: Monitor for encephalopathy and fluid shifts closely.
Practical workplace and driving advice: avoid heavy machinery and driving if dizziness or orthostatic symptoms occur until stability is confirmed.
For planned radiological procedures with contrast, coordinate fluid status and consider temporary adjustments with the treating clinician.
Advice on lifestyle: avoid excessive alcohol and take precautions in hot weather due to risk of dehydration and hypotension.
At‑Risk Population Frequencies
- Chronic kidney disease prevalence is higher in some Indigenous Australian populations; consult local health datasets for exact figures by region.
Dosage Guidelines
How should torasemide be started and titrated in typical practice?
Typical adult initiation is 5–10 mg once daily and titration is guided by clinical response including weights, oedema and blood pressure.
Maintenance doses commonly range between 5–20 mg once daily in outpatient care.
Some refractory oedema cases require higher dosing under specialist supervision and frequent monitoring.
In renal impairment, adjust doses based on eGFR and loop responsiveness with closer monitoring of electrolytes and creatinine.
Elderly patients should start low and titrate slowly with review within 48–72 hours.
For acute decompensated heart failure, inpatient IV strategies differ and follow cardiology protocols rather than outpatient regimens.
Paediatric use is specialist only.
| Indication | Usual Starting Dose | Monitoring Cadence |
|---|---|---|
| Chronic HF (oral) | 5–10 mg once daily | Baseline U&E, 48–72 hours, 1–2 weeks |
| Renal Oedema | Individualised; specialist input if eGFR low | Frequent U&E and creatinine checks |
| Hepatic Oedema | Start low; titrate | 48–72 hours then weekly as needed |
Titration tips: weigh daily, keep a symptom diary and contact a GP or ED if urine output falls markedly or dizziness occurs.
Follow local PBS and hospital protocols and the TGA‑approved product information for definitive dosing guidance.
Interactions Overview
What are the main drug and food interactions to watch for?
- ACE Inhibitors and ARBs: additive effects on renal function when combined with loop diuretics; monitor renal function closely.
- NSAIDs: can blunt diuretic effect and raise renal risk when added to torasemide; review OTC NSAID use during telehealth prescribing.
- Lithium: diuretic‑related renal handling changes can alter lithium levels; check serum lithium when starting or changing dose.
- Digoxin: risk of digoxin toxicity increases with hypokalaemia from diuretics; monitor electrolytes and digoxin levels as needed.
- Antihypertensives: expect additive hypotensive effect; counsel patients about postural symptoms.
| Co‑prescribed Drug | Risk | Monitoring Steps |
|---|---|---|
| ACEi / ARB | Renal impairment | Baseline U&E, check 48–72 hours after initiation |
| NSAIDs | Reduced diuretic effect; renal risk | Advise avoiding OTC use; check renal function if required |
| Lithium | Serum level changes | Monitor lithium levels and renal function frequently |
Metformin interaction note: diuretic‑induced renal impairment or dehydration can increase risk of metformin‑related complications; ensure renal monitoring when patients are co‑prescribed metformin.
Cultural Perceptions & Patient Habits In Australia
How do Australians view torasemide and where do they get advice?
Community pharmacy is a trusted first point of contact for medicine advice across Australia.
Patients are often price‑sensitive and may ask about private scripts versus PBS options at chains like Chemist Warehouse and Priceline.
Rural patients may experience stock variability and longer intervals between face‑to‑face follow‑up.
Telehealth has improved access but can complicate monitoring such as timely blood tests and weight checks.
Indigenous communities require culturally safe education on fluid balance, follow‑up and dietary sodium when diuretics are used.
Common patient questions concern dizziness, nocturia and the best time to take a dose, with morning dosing generally preferred to reduce night‑time urination.
- Pharmacist Counselling Script (Example): "Take this tablet each morning with water, weigh yourself daily and book a blood test in 48–72 hours."
- Practical Tip: Arrange local pathology or community nurse visits for remote patients to support safe monitoring.
Include culturally appropriate resources such as local Aboriginal community health services when arranging care and follow‑up.
Availability & Pricing Patterns
Where can people in Australia get torasemide and what does it cost?
Demadex and generic torasemide are stocked in major Australian chains and hospital pharmacies, but brand and pack supplied vary by wholesaler and PBS listing.
PBS coverage can be available under authority items for heart failure and oedema and will affect out‑of‑pocket costs for patients.
Chemist Warehouse often advertises competitive private script prices and other community pharmacies provide both PBS and private options.
Online pharmacies and telehealth services supply scripts and can deliver to remote areas, but ensure arrangements for blood tests and follow‑up are in place.
In our online pharmacy, demadex is available without a prescription, with discreet delivery to Australia in 5‑14 days.
| Channel | PBS Subsidised | Private Price Range | Notes |
|---|---|---|---|
| Community Pharmacy | Yes, when authority applies | Varies by brand and pack | Confirm substitution rules at dispensing |
| Online Pharmacy | Possible with e‑prescription | Often competitive | Ensure local monitoring arrangements |
| Hospital Pharmacy | Formulary driven | Not applicable | Used for inpatient/IV therapy |
Pharmacists should confirm PBS authority requirements and substitution rules before dispensing.
For rural stock issues, discuss emergency supplies and liaise with local health services to avoid gaps in therapy.
Comparable Medicines And Clinical Preferences
When might a clinician choose torasemide over other loop diuretics?
Main comparators are furosemide and bumetanide.
Clinical decision points include onset and duration of action, oral bioavailability and renal responsiveness.
Pros of torasemide include once‑daily dosing, a longer half‑life and more predictable oral bioavailability.
Cons include cost and occasional limited availability compared with furosemide, and clinician familiarity with furosemide for IV rescue in acute settings.
- When To Escalate: Poor diuretic response, suspected intestinal oedema limiting absorption, or severe electrolyte disturbances require specialist review.
- Combination Therapy: Loop plus thiazide‑like diuretics is a recognised strategy for diuretic resistance under specialist supervision.
| Drug | Approximate Oral Potency | Dosing Frequency | Monitoring Needs |
|---|---|---|---|
| Torasemide | 10 mg ≈ 40 mg furosemide (approx.) | Once daily | U&E, weight, BP |
| Furosemide | 40 mg ≈ 10 mg torasemide (approx.) | Often twice daily | U&E, weight, BP |
| Bumetanide | 1 mg ≈ 40 mg furosemide (approx.) | Once or twice daily | U&E, weight, BP |
FAQ
- Can I take torasemide with metformin? Yes, generally, but monitor renal function closely because volume depletion or renal impairment increases risk for complications with metformin.
- What are common side effects? Dizziness, increased urination, electrolyte disturbances such as low potassium or magnesium, hypotension and occasional gout flares are commonly reported.
- When should I seek medical help? Seek urgent care for severe dizziness, fainting, muscle weakness, very low urine output or sudden large weight changes.
- Can I drive while taking Demadex? Avoid driving if you feel dizzy or light‑headed until the effect is established and you are stable.
Red Flag Decision Flow
- Severe dizziness, fainting or collapse → Seek emergency care immediately.
- Muscle weakness or severe cramping with palpitations → Contact GP or attend ED for urgent electrolyte checks.
- Marked reduction in urine output or sudden weight gain → Seek prompt medical review.
Patients should receive pharmacist counselling at dispensing and be given clear follow‑up instructions.
Guidelines For Proper Use
What should pharmacists and prescribers cover when starting torasemide?
Baseline tests should include U&E, creatinine, weight and blood pressure before or at initiation.
Dose in the morning to reduce nocturia unless otherwise advised by the treating clinician.
Review concurrent NSAID or ACEi/ARB use and advise patients about signs of dehydration and electrolyte disturbance.
Recommend self‑monitoring with daily weights and a simple symptom diary for breathlessness and oedema.
For telehealth prescriptions, arrange local pathology within 48–72 hours of starting therapy.
In Indigenous and rural contexts, liaise with community health services and set clear follow‑up plans.
Storage advice: keep tablets at room temperature away from moisture and heat.
| Monitoring Timepoint | Action |
|---|---|
| Baseline | U&E, creatinine, weight, BP |
| 48–72 Hours | Repeat U&E and weight check |
| 1 Week | Clinical review and adjust dose if needed |
| Monthly | Ongoing monitoring in stable patients |
Action Thresholds
- Potassium < 3.5 mmol/L → Clinical action, replace potassium and review diuretic dose.
- Creatinine rise >30% from baseline → Reassess volume status and consider specialist review.
- Symptomatic hypotension → Hold dose and seek medical review.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5–7 days |
| Melbourne | Victoria | 5–7 days |
| Brisbane | Queensland | 5–7 days |
| Perth | Western Australia | 5–7 days |
| Adelaide | South Australia | 5–7 days |
| Canberra | Australian Capital Territory | 5–7 days |
| Hobart | Tasmania | 5–7 days |
| Darwin | Northern Territory | 5–9 days |
| Newcastle | New South Wales | 5–7 days |
| Wollongong | New South Wales | 5–7 days |
| Geelong | Victoria | 5–7 days |
| Gold Coast | Queensland | 5–7 days |
| Sunshine Coast | Queensland | 5–9 days |
| Cairns | Queensland | 5–9 days |
| Townsville | Queensland | 5–9 days |