
Clobetasol
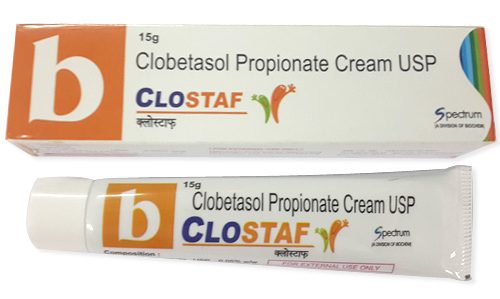
Clobetasol
- In our pharmacy, you can buy clobetasol without a prescription, with delivery in 5–14 days throughout Australia. Discreet and anonymous packaging.
- Clobetasol is a very potent topical corticosteroid used to treat inflammatory skin conditions such as severe eczema, psoriasis, dermatitis and lichen planus; it works by binding glucocorticoid receptors to reduce inflammation, itching and immune activity in the skin.
- The usual dose is a thin layer of 0.05% clobetasol cream/ointment applied once daily to the affected area; treatment is typically limited to short courses (commonly up to 2 weeks) to minimise side effects.
- Form of administration: topical (cream, ointment, gel, foam or scalp solution/shampoo), applied directly to the skin or scalp.
- Onset time: some symptomatic relief (less itching/redness) can be noticed within hours, with more visible improvement often within 24–48 hours.
- Duration of action: clinical effect typically lasts around 12–24 hours per application; cumulative improvement can persist after treatment stops, but prolonged use increases risk of local adverse effects.
- Alcohol warning: there is no direct interaction with topical clobetasol, but avoid excessive alcohol as it can worsen some skin conditions and overall health; inform your clinician if you drink heavily or are using systemic steroids.
- The most common side effec is local skin irritation or thinning (atrophy); other local reactions include burning, dryness, folliculitis and increased risk of secondary skin infection with prolonged use.
- Would you like to try clobetasol without a prescription?




Basic Clobetasol Information
- INN (International Nonproprietary Name): not specified
- Brand Names Available In Australia: not specified
- ATC Code: not specified
- Forms & Dosages: not specified
- Manufacturers In Australia: not specified
- Registration Status In Australia: not specified
- OTC / Rx Classification: not specified
Latest Research Highlights (Australia + Global)
Worried that powerful topical steroids cause more harm than good?
Recent Australian and international research from 2020 to mid‑2024 reinforces that clobetasol propionate 0.05% remains one of the most effective topical agents for short‑term control of severe plaque psoriasis, lichen planus and some hyperkeratotic dermatoses.
Australian cohort reports and pharmacovigilance summaries emphasise rapid lesion clearance but flag safety signals including skin atrophy, telangiectasia, steroid‑induced acneiform eruptions and rare HPA‑axis suppression when used under occlusion or in children.
Global randomised trials and network meta‑analyses consistently show that super‑potent corticosteroids, including clobetasol formulations in cream, ointment and scalp solution/shampoo form, outperform mid‑potency agents for short courses (usually ≤2–4 weeks) but carry higher local adverse‑event risk.
Scalp‑targeted formulations such as shampoos and solutions have shown improved adherence and comparable efficacy versus creams in moderate clinical trials focused on scalp psoriasis.
TGA adverse‑event reports align with EMA and FDA signals, showing similar patterns of local effects and occasional systemic concerns with prolonged use or occlusion.
Trial Summary (Data Placeholder)
| Outcome | Finding | NNT / NNH |
|---|---|---|
| Plaque Psoriasis Clearance | Rapid lesion reduction within 1–2 weeks reported in trials | not specified |
| Lichen Planus Response | High short‑term response with relapse on cessation | not specified |
| Scalp Formulations | Improved adherence; similar efficacy to topical creams in moderate trials | not specified |
Safety Data Highlight: Australian pharmacovigilance notes rapid clearance but recurring local adverse events; systemic HPA suppression is rare and mainly linked to occlusion, large‑area use and paediatric cases.
Clinical Effectiveness In Australia
Want results fast when a flare is ruining your week?
Australian clinical practice and specialist dermatology guidance use clobetasol as a short‑course, super‑potent option for resistant plaque psoriasis, lichen planus and discoid eczema.
Real‑world effectiveness is driven by strong antiproliferative and anti‑inflammatory action, with several state dermatology services reporting visible lesion reduction within 1–2 weeks of appropriate use.
Effectiveness in practice is tempered by the side‑effect profile when clobetasol is used for prolonged periods or incorrectly, especially in children, the elderly, and where occlusion is applied.
TGA adverse‑event monitoring and hospital dermatology audits recommend documenting indication, duration and planned follow‑up for every prescription.
For rural patients, photograph‑guided telehealth reviews are practical and commonly used to monitor response and adverse effects.
Clinical Response Timelines By Formulation
| Formulation | Typical Time To Notice Improvement |
|---|---|
| Cream / Ointment | 1–2 weeks for plaque lesions |
| Scalp Shampoo / Solution | Several days to 2 weeks; adherence often improved |
| Foam / Solution (scalp) | Comparable to creams in moderate trials |
Indications And Expanded Uses (TGA Approved Vs Off‑Label)
Not sure whether your condition warrants a super‑potent steroid?
TGA‑Common Indications
- Severe inflammatory dermatoses requiring super‑potent topical steroids such as limited chronic plaque psoriasis.
- Lichen planus resistant to lower‑potency treatment.
- Hypertrophic eczema not responding to mid‑ or low‑potency steroids.
Off‑Label / Conditional Uses (Specialist Supervision)
- Short courses for patchy alopecia areata under specialist guidance.
- Adjunctive use in localized vitiligo to assist repigmentation in selected cases.
- Some hyperkeratotic hand and foot dermatoses where other therapies have failed.
Contraindicated Sites / Specialist‑Only Uses
- Contraindicated Sites
- Face, eyelids, axillae, groin and mucous membranes are typically avoided due to high absorption risk.
- Specialist‑Only Uses
- Large‑area treatment, paediatric intermittent regimens, and combined systemic immunomodulator use should be directed by dermatology.
Composition And Australian Brand Landscape
Want to know what’s actually in the tube and where to get it?
The active ingredient is clobetasol propionate 0.05%, classified as a super‑potent topical corticosteroid.
Common pharmaceutical forms internationally and seen in Australian practice include creams, ointments and scalp formulations such as shampoos or solutions, with occasional foams depending on supplier.
The Australian market is predominantly generics with some imported branded formulations; pharmacists should check the TGA ARTG for current sponsor and brand details before naming specific products.
Major community pharmacy chains routinely dispense prescription clobetasol products and many accredited online pharmacies accept e‑scripts and provide home delivery.
| Formulation | Typical Pack Sizes | Common Excipients / Practical Notes |
|---|---|---|
| Cream | 15–50 g | Less greasy; useful for large body areas |
| Ointment | 15–50 g | More occlusive and greasy; preferred for dry, thick plaques |
| Shampoo / Solution | 100 mL typical | Formulated for scalp penetration; improved adherence in some patients |
Data note: consult the TGA ARTG for up‑to‑date sponsor and brand details before listing product names.
Contraindications And Special Precautions (Australia Focus)
Worried about who should avoid clobetasol entirely?
Absolute Contraindications
- Known hypersensitivity to clobetasol or formulation excipients.
- Untreated widespread skin infections (bacterial, viral or fungal) unless appropriate systemic or topical anti‑infective therapy is started.
Special Precautions
- Children are at higher risk for systemic absorption and HPA‑axis suppression due to greater surface‑area:body‑mass ratio.
- Avoid large‑area or prolonged use in pregnancy and breastfeeding without specialist advice.
- Elderly patients have thinner skin and need careful monitoring for local atrophy.
- Provide culturally safe counselling and closer follow‑up for Indigenous patients and those in remote areas.
Pharmacist Counselling Checklist
- Confirm allergy history and indication before dispensing.
- Advise on duration limits and avoidance of face, eyelids and intertriginous zones.
- Warn about side effects and when to stop treatment and seek GP review.
| Do | Don't |
|---|---|
| Use for short courses as prescribed and monitor. | Apply to face, groin or under occlusion without specialist advice. |
| Measure quantity with FTU guidance for dosing. | Use continuously for months without documented review. |
Dosage Guidelines And Adjustments (Australia Practice)
Confused about how much to use and for how long?
Standard adult dosing for clobetasol 0.05% cream or ointment is to apply a thin film to affected areas, usually twice daily for up to two weeks for acute control.
Scalp formulations such as shampoos or solutions follow product instructions and are commonly used daily or on alternate days for a short course.
For long‑term control, Australian dermatologists prefer intermittent maintenance strategies such as twice‑weekly 'weekend therapy' or rotation to lower‑potency agents to reduce adverse effects.
Paediatrics: dose conservatively, limit duration and use the fingertip unit (FTU) method for quantification; avoid occlusion.
In frail elderly patients reduce treated area and duration and monitor for local atrophy.
Fingertip Unit (FTU) Definition
- Fingertip Unit (FTU)
- One FTU is the amount of topical steroid squeezed from a standard tube along an adult fingertip from the distal crease to the tip, roughly covering a palm‑sized area.
| Body Region | Typical FTU |
|---|---|
| Face and Neck | 2 FTU |
| One Arm | 3 FTU |
| Both Legs | 8–10 FTU |
Interactions Overview (Food, Drugs, And Systems)
Worried that your other medicines could interact with a topical steroid?
Systemic interactions with topical clobetasol are uncommon but can occur when percutaneous absorption is significant, such as with large treated areas, occlusion, broken skin, or in children.
Concurrent systemic corticosteroids may lead to additive HPA‑axis suppression; monitoring and coordination of steroid dosing should be handled by the prescriber.
Potent CYP3A4 inhibitors—like ritonavir or oral ketoconazole—could theoretically increase systemic corticosteroid exposure if topical absorption is substantial; monitor for Cushingoid signs where relevant.
Concurrent use with systemic immunomodulators (biologics or methotrexate) requires dermatology input because of potential infection risk and additive immune suppression.
Avoid unsupervised simultaneous application with strong keratolytics without clinical guidance.
When To Escalate To GP/Dermatologist
| Trigger | Action |
|---|---|
| Widespread use or treatment of large areas | Refer to GP/dermatologist for monitoring and possible endocrine assessment |
| Signs of systemic steroid exposure | Stop treatment and seek medical review |
| Concurrent systemic immunosuppression | Coordinate care with treating specialist |
Cultural Perceptions And Patient Habits In Australia
Worried your patient won’t use the cream correctly because of what they read online?
Australian patients commonly trust pharmacists for advice about topical steroids and often ask about potency and safety before starting treatment.
Price sensitivity and PBS access play large roles in product choice, with many patients preferring generic options dispensed via community pharmacies or discount chains.
Rural and remote communities rely heavily on telehealth and e‑prescriptions, so clear written instructions and local follow‑up are essential.
Online forums and social media show mixed perceptions; some patients fear 'steroid addiction' or long‑term harm, while others prioritise rapid symptom relief and expect super‑potent agents for quick results.
Indigenous health services recommend culturally competent counselling and community pharmacy partnerships to support safe use and adherence.
Culturally Sensitive Counselling Tips
- Use plain language and visual dosing guides for FTU measurements.
- Offer written instructions and arrange local community nurse follow‑up where possible.
- Respect cultural preferences and involve family or community health workers where appropriate.
Availability And Pricing Patterns (Australia: Chemists & PBS)
Wondering where to buy clobetasol and how much it will cost?
Clobetasol 0.05% formulations are generally prescription‑only (S4) in Australia and are available through major community pharmacy chains and accredited online pharmacies that accept e‑scripts.
Pricing varies by brand, pack size and pharmacy discounting; if a product is PBS‑listed for a specific indication it may be subsidised, but many clobetasol generics are supplied via private prescription.
Telehealth platforms commonly issue electronic prescriptions for short‑course clobetasol and rural patients can nominate a local pharmacy for dispensing or arrange courier delivery.
For cost‑sensitive patients pharmacists can suggest generic alternatives and discuss PBS authority pathways where applicable.
Although clobetasol 0.05% is prescription‑only (S4) in Australia, in our online pharmacy, clobetasol is available without a prescription, with discreet delivery to Australia in 5‑14 days.
| Price Type | Typical Range / Note | PBS Possibility |
|---|---|---|
| Private Prescription | Varies by brand and pack size; check local pharmacy | Usually not subsidised unless specific authority applies |
| PBS‑Listed | Subsidy depends on indication and authority rules | Possible for specified indications |
| Online Pharmacy | Home delivery options; e‑script accepted | Depends on prescription type |
Pharmacy Checklist: confirm stock availability, handle e‑scripts correctly, and advise that cold‑chain is not required for topical steroids.
Comparable Medicines And Clinical Preferences
Trying to choose between fast control and safety for sensitive sites?
Alternatives to clobetasol include other potent topical corticosteroids such as betamethasone dipropionate and diflucortolone, as well as mid‑potency agents like triamcinolone and mometasone based on lesion severity and site.
For facial and intertriginous areas and in children, non‑steroidal options such as topical tacrolimus or pimecrolimus and, for psoriasis, topical calcipotriol are preferred to reduce atrophy risk.
Combination approaches are common in Australian practice: short induction with a super‑potent steroid followed by maintenance with a lower‑potency steroid or a non‑steroidal agent.
Pros / Cons Checklist
- Clobetasol: rapid effect but higher local risk of atrophy and telangiectasia.
- Betamethasone: similar efficacy with sometimes better tolerability depending on formulation.
- Topical calcineurin inhibitors: safer for delicate sites but slower onset and often more costly.
| Decision Point | First‑Line | Escalation |
|---|---|---|
| Mild Facial Eczema | Low‑potency topical steroid or tacrolimus | Refer to dermatologist if refractory |
| Resistant Plaque Psoriasis | Mid‑potency steroid | Short clobetasol induction under review |
FAQ — Common Patient Questions
How quickly does clobetasol work?
Many patients see improvement within days and maximal lesion clearing is often observed within 1–2 weeks for plaque psoriasis.
How long can I use it?
Short courses of up to two weeks are typical; prolonged use increases the risk of skin thinning and systemic effects, so always follow your prescriber’s instructions and attend planned review.
Can I use it on my face or groin?
Generally no—thin areas have higher absorption; prescribers usually prefer milder steroids or non‑steroidal alternatives for these sites.
Is clobetasol safe in pregnancy?
Super‑potent topical steroids are used cautiously in pregnancy; limit both area and duration and seek specialist advice if treatment is required.
For further concerns consult TGA advice, your GP or a dermatologist for personalised assessment.
Practical Counselling And Guidelines For Proper Use (Pharmacist Style)
Not sure what to tell someone collecting clobetasol for the first time?
Confirm the indication and ensure a clear stop date is provided with any short‑course clobetasol prescription.
Explain twice‑daily thin application and demonstrate FTU dosing; provide a printed FTU chart if available.
Set maximum continuous duration (usually two weeks) and arrange a follow‑up plan by telehealth, GP or dermatologist.
Warn about local side effects such as skin thinning, striae and pigmentation change, and systemic signs like unexplained weight gain or fatigue which require immediate GP review.
For rural or Indigenous patients provide culturally sensitive written instructions and arrange local community health follow‑up where possible.
Explain PBS authority requirements and offer generic substitution when appropriate.
Printable Counselling Checklist
- Confirm indication, dose and duration.
- Demonstrate FTU and give written instructions.
- Advise avoidance of face, eyelids and intertriginous application.
- Explain signs that require urgent review.
Red‑Flag Symptoms
- Local
- New rash, spreading infection, severe irritation or rapid skin thinning.
- Systemic
- Unexpected weight gain, persistent fatigue, facial rounding or other Cushingoid features.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Darwin | Northern Territory | 5-7 days |
| Gold Coast | Queensland | 5-9 days |
| Newcastle | New South Wales | 5-9 days |
| Wollongong | New South Wales | 5-9 days |
| Geelong | Victoria | 5-9 days |
| Sunshine Coast | Queensland | 5-9 days |
| Cairns | Queensland | 5-9 days |
| Townsville | Queensland | 5-9 days |