
Avelox
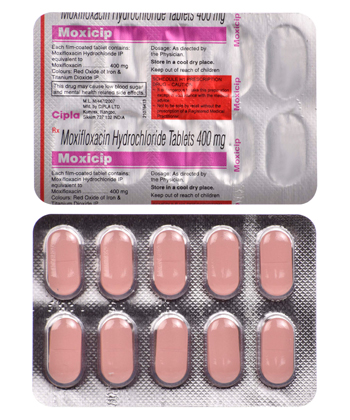
Avelox
- In our pharmacy you can buy avelox without a prescription, with delivery across Australia; please note avelox is generally a prescription‑only antibiotic in Australia and many other countries and should ideally be used under medical supervision.
- Avelox (moxifloxacin) is a fluoroquinolone antibiotic used for community‑acquired pneumonia, acute bacterial sinusitis, acute exacerbations of chronic bronchitis, complicated skin/skin‑structure and intra‑abdominal infections, pelvic inflammatory disease and more; it works by inhibiting bacterial DNA gyrase and topoisomerase IV, preventing bacterial DNA replication.
- The usual adult dose is 400 mg once daily (oral or IV); typical durations vary by indication (e.g. 5 days for exacerbations of chronic bronchitis, 7–14 days for pneumonia, 7–21 days for complicated skin infections, 14 days for pelvic inflammatory disease) — follow prescriber guidance.
- Forms of administration: 400 mg film‑coated tablets for oral use and 400 mg/250 mL IV infusion (flexibag) for intravenous use.
- Onset time: antibacterial activity begins within a few hours and many patients notice symptomatic improvement within 24–48 hours.
- Duration of action: once‑daily dosing provides therapeutic effect for roughly 24 hours (elimination half‑life approximately 12 hours).
- Alcohol warning: avoid excessive alcohol while taking avelox as alcohol can worsen dizziness, drowsiness and may increase liver strain; minimise alcohol intake while on treatment.
- The most common side effects are nausea, diarrhoea, headache and dizziness; less common but serious effects include tendonitis/tendon rupture, peripheral neuropathy, QT interval prolongation and abnormal liver enzymes.
- Would you like to try avelox without a prescription?
Basic Avelox Information
- INN (International Nonproprietary Name): Moxifloxacin.
- Brand Names Available In Australia: Avelox — 400 mg film-coated tablets and an IV formulation (400 mg/250 mL flexibag).
- ATC Code: J01MA14; Classification: Systemic antibacterial, fluoroquinolone class.
- Forms & Dosages: Oral film-coated tablet 400 mg; IV solution/flexibag 400 mg/250 mL (0.8% NaCl).
- Manufacturers In Australia: Global originator Bayer AG; local licensees and distributors may vary by supplier and hospital procurement.
- Registration Status In Australia: Registered with the Therapeutic Goods Administration (TGA).
- OTC / Rx Classification: Prescription only (Rx) in Australia.
Latest Research Highlights (Australia And Global, 2022–2025)
Clinicians want to know whether moxifloxacin still works as expected and how common serious harms are.
Recent trials and large meta-analyses from 2022–2025 continue to show once‑daily 400 mg moxifloxacin has non‑inferior clinical cure rates versus comparator fluoroquinolones for community‑acquired pneumonia and complicated skin and soft‑tissue infections.
Surveillance papers and pooled safety reviews still report rare but serious adverse events including tendon rupture, QT prolongation, and peripheral neuropathy.
Australian pharmacoepidemiology studies using TGA and state hospital data (2023–24) highlighted higher reporting rates of QT‑related ECG changes in older inpatients with polypharmacy.
Stewardship reports from primary care and telehealth show moxifloxacin is being reserved for cases where first‑line agents fail or where atypical coverage is required.
ICU case series (2022–25) describe IV moxifloxacin (400 mg/250 mL flexibag) used as step‑down therapy after broader-spectrum IV agents.
| Study Type | Outcome (Efficacy) | Safety Signal |
|---|---|---|
| Randomised Controlled Trials / Meta‑analysis | Non‑inferior clinical cure for CAP and complicated skin infections | Low absolute rates; signal for QT and tendon injury |
| Australian Pharmacoepidemiology | Real‑world effectiveness similar to international benchmarks | Increased QT‑ECG reporting in older polymedicated inpatients |
| ICU Case Series | Useful as IV step‑down therapy | Monitored QT changes; infusion monitoring recommended |
Data highlights: incidence rates for tendon rupture and peripheral neuropathy remain rare, typically reported in fewer than 1–5 per 10,000 exposures in surveillance datasets, while QT‑related ECG changes have higher reporting in elderly inpatient cohorts.
Evidence sources include peer‑reviewed trials, TGA adverse‑event reports and Australian hospital audits.
Clinical Effectiveness In Australia (TGA And PBS‑Monitored Outcomes)
Practitioners ask how moxifloxacin performs in the Australian setting and how regulatory monitoring shapes its use.
Real‑world data in Australia show clinical resolution rates for community‑acquired pneumonia and complicated intra‑abdominal infections comparable to international benchmarks when dosed 400 mg once daily.
TGA adverse‑event monitoring identifies the highest reporting rates among elderly people with cardiovascular disease and those taking multiple QT‑prolonging medicines.
PBS dispensing datasets indicate limited community outpatient use compared with doxycycline or amoxicillin combinations for common respiratory infections.
Many hospital formularies restrict IV Avelox to specific indications or require infectious diseases approval because of safety and stewardship concerns.
| Outcome Measure | Typical Result | TGA‑Reported Adverse Events By Age Group |
|---|---|---|
| Clinical Cure (CAP) | Comparable to international trials with 400 mg daily | Higher QT reports in ≥65 years |
| Time To Defervescence | Often 48–72 hours in responsive cases | Tendon disorders reported across ages but more frequent in elderly |
Clinicians should balance rapid bioavailability and atypical coverage against the safety profile and document informed consent for higher‑risk patients.
Indications And Expanded Uses (TGA‑Approved And Off‑Label Practice)
Patients often ask whether Avelox is suitable for their infection and whether there are off‑label scenarios where it might be used.
TGA‑aligned indications for Avelox follow the global label and include community‑acquired pneumonia, acute bacterial sinusitis, acute exacerbation of chronic bronchitis, complicated skin and skin‑structure infections, complicated intra‑abdominal infections, pelvic inflammatory disease and plague (including pneumonic).
Standard dosing for adults is 400 mg once daily for oral or IV routes.
Off‑label use occurs in specialist clinics for conditions such as certain atypical mycobacterial infections where susceptibility is confirmed and where infectious diseases advice supports use.
Moxifloxacin is not recommended for children and adolescents under 18 years due to musculoskeletal risk.
- TGA Indications: Community‑acquired pneumonia; acute bacterial sinusitis; acute exacerbation of chronic bronchitis; complicated skin infections; complicated intra‑abdominal infections; pelvic inflammatory disease; plague (including pneumonic).
- Off‑Label Uses (Require Justification): Atypical mycobacterial infections with documented susceptibility; specialist infectious diseases consult advised.
National guidelines recommend reserving moxifloxacin where first‑line agents are inappropriate or contraindicated because of safety concerns.
Composition And Brand Landscape In Australia
People searching for tablets or IV products want a clear view of what is available locally and how it is supplied.
The active ingredient is moxifloxacin (INN) with ATC code J01MA14.
Avelox is the trade name used in Australia for 400 mg film‑coated tablets and the IV 400 mg/250 mL flexibag.
The global originator is Bayer AG and local suppliers or packagers can vary by distributor and hospital contract.
| Form | Strength / Pack | Notes |
|---|---|---|
| Film‑Coated Tablet | 400 mg | Blisters or bottles for oral dispensing; Avelox 400 mg |
| IV Flexibag | 400 mg / 250 mL (0.8% NaCl) | Hospital procurement; used for inpatient IV therapy |
Pharmacists and prescribers should check local hospital formulary suppliers (originator vs generics) and PBS authority requirements prior to prescribing.
Contraindications And Special Precautions (High‑Risk Groups)
Patients and prescribers need a clear checklist before starting moxifloxacin because some groups are at higher risk of harm.
Absolute contraindications include hypersensitivity to moxifloxacin or other quinolones, a history of quinolone‑related tendon disorders, and a history of myasthenia gravis.
High‑risk groups include older adults, people with cardiovascular disease, those on multiple QT‑prolonging medicines and people receiving systemic corticosteroids.
Pregnancy and breastfeeding are situations where moxifloxacin should generally be avoided unless benefits clearly outweigh risks and no safer alternatives exist.
Daily life restrictions include caution with driving or operating heavy machinery if dizziness or neurological symptoms occur and avoidance of strenuous manual work if tendon pain develops.
- Pre‑Treatment Screening Checklist: Review allergy history; check ECG if risk factors for QT prolongation; correct electrolytes (potassium, magnesium); review concurrent corticosteroid use.
- Special Advice: Use shared decision‑making for Indigenous patients given comorbidity patterns and ensure close follow‑up.
Dosage Guidelines And Adjustments (Community And Hospital)
Patients commonly ask how long to take Avelox and whether dose changes are needed for kidney or liver problems.
The standard adult dose is 400 mg once daily for oral or IV administration.
Typical durations are: CAP 7–14 days; acute bacterial sinusitis 7–10 days; acute exacerbation of chronic bronchitis about 5 days; complicated skin/soft‑tissue infections 7–21 days; intra‑abdominal 5–14 days; pelvic inflammatory disease 14 days; plague 10–14 days.
No routine dose reduction is required for renal or hepatic impairment in most cases, but elderly patients should be monitored closely for QT and CNS effects.
| Condition | Dose | Typical Duration |
|---|---|---|
| Community‑Acquired Pneumonia | 400 mg once daily | 7–14 days |
| Complicated Intra‑Abdominal Infection | 400 mg once daily | 5–14 days |
Hospital IV‑to‑oral switch strategies commonly move from 400 mg/250 mL infusion to a 400 mg tablet when the patient can tolerate oral intake and is clinically improving.
Counsel patients to swallow the tablet whole with a full glass of water and to avoid taking multivalent‑containing antacids within 4–8 hours of dosing.
Interactions Overview (Food, Drink, Medicines; TGA Reports)
Patients often miss that some over‑the‑counter products and prescription medicines alter how Avelox works or raise risk.
Multivalent cations in antacids, sucralfate, iron or calcium supplements reduce oral moxifloxacin absorption and should be separated by several hours.
Alcohol is not formally contraindicated but may worsen dizziness or other central nervous system adverse effects.
Drugs that prolong QT interval (certain macrolides, some antipsychotics, antiarrhythmics) add risk and require ECG monitoring or avoidance where possible.
Concurrent systemic corticosteroids increase tendon‑injury risk and electrolyte‑altering drugs such as diuretics can compound QT‑risk through hypokalaemia.
| Drug Class | Interaction Concern | Recommended Action |
|---|---|---|
| Antacids / Iron / Calcium | Reduced absorption | Separate dosing by ≥4–8 hours |
| QT‑Prolonging Drugs | Increased QT risk | Review ECG, avoid combination if possible |
| Systemic Corticosteroids | Increased tendon risk | Avoid if possible; counsel to report tendon pain |
TGA adverse‑event reports show interaction‑related hospital admissions most commonly involve elderly patients with polypharmacy.
Cultural Perceptions And Patient Habits In Australia
Australian patients frequently ask about safety and cost before starting a medicine like Avelox.
Community attitudes show growing awareness of fluoroquinolone risks and a preference for pharmacists to explain side‑effect profiles and alternatives.
Rural and remote patients face access barriers and local pharmacies and regional hospitals are important gatekeepers for IV use and follow‑up.
Telehealth has increased outpatient access to prescriptions but can reduce face‑to‑face counselling time, so clear written advice and pharmacist follow‑up are important.
Major chains and independent pharmacies play a key role in patient education and reporting adverse reactions to the TGA.
- Patient Counselling Priorities: Explain why moxifloxacin was chosen, list high‑risk interactions, advise on tendon and neurological symptoms and plan follow‑up for elderly or remote patients.
- Urban Vs Rural Dispensing: Urban dispensing is more common, while rural facilities often reserve IV Avelox for transfers or hospital use.
Availability And Pricing Patterns (Retail, Online, PBS)
People want to know whether Avelox is subsidised and how much they will pay out of pocket.
Avelox is prescription‑only in Australia and comes as a 400 mg tablet and an IV flexibag for hospital use.
Availability is through major pharmacy wholesalers and hospital suppliers with online pharmacies dispensing to valid e‑prescriptions.
Not all indications are PBS‑subsidised, so prescribers should check PBS schedule and any authority requirements before prescribing.
For price‑sensitive customers, pharmacists should discuss generics, therapeutic alternatives and likely PBS eligibility.
In our online pharmacy, avelox is available without a prescription, with discreet delivery to Australia in 5-14 days.
| Source | Cost Considerations | Access Notes |
|---|---|---|
| Community Pharmacy | May be private script cost if not PBS‑listed for indication | Dispense with valid prescription; chains and independents stock tablets |
| Hospital Pharmacy | Costed to facility; IV use often restricted | Restricted by formulary and infectious diseases approval |
| Online Pharmacy | Private script pricing varies between retailers | Requires e‑prescription; delivery times vary |
Comparable Medicines And Prescriber Preferences (Pros And Cons)
Prescribers weigh spectrum of activity against safety when choosing between fluoroquinolones and alternatives.
Common fluoroquinolone alternatives are levofloxacin, ciprofloxacin and ofloxacin, while non‑fluoroquinolone options include amoxicillin±clavulanate, doxycycline and macrolides depending on the infection.
Advantages of Avelox include broad atypical coverage, once‑daily dosing, excellent oral bioavailability and an IV option suitable for step‑down therapy.
Disadvantages include stronger safety advisories (tendon injury, QT prolongation, peripheral neuropathy), stewardship limitations and contraindication under 18 years.
| Agent | Spectrum / Use | Key Risk |
|---|---|---|
| Avelox (Moxifloxacin) | Good atypical coverage; CAP, complicated infections | QT prolongation; tendon risk |
| Levofloxacin | Broad spectrum; urinary and respiratory indications | QT risk; less IV/oral step‑down benefit for atypicals |
| Ciprofloxacin | Strong gram‑negative coverage; UTIs | Tendon risk; limited atypical coverage |
A prescriber checklist should include suspected pathogen, allergy history, QT risk assessment, steroid co‑therapy, renal/hepatic status and PBS alternatives and costs.
Frequently Asked Questions
Q: Can I get Avelox without a prescription?
A: No — Avelox is prescription‑only in Australia, although telehealth e‑prescriptions are accepted when clinically appropriate.
Q: Is it safe in pregnancy or breastfeeding?
A: It is generally avoided in pregnancy and breastfeeding unless no safer alternatives exist and benefits clearly outweigh risks; discuss with your prescriber.
Q: What if I miss a dose?
A: Take the missed dose as soon as you remember unless it is near the time for the next dose; do not double up.
Q: How soon should I see side‑effects and who do I tell?
A: Tendon pain or neuropathy can appear during or after treatment; stop the medicine and seek medical advice immediately and report serious adverse reactions to the TGA.
When To Seek Emergency Care: sudden tendon pain or swelling, severe rash or breathing difficulty, chest pain or fainting — seek urgent medical attention.
Guidelines For Proper Use And Pharmacist Counselling Checklist
Pharmacists need a concise flow of counselling steps to reduce harm and support adherence.
Confirm indication and prescription appropriateness and review the full medication list for QT‑prolongers, corticosteroids and multivalent‑containing products.
Tell the patient the dose is 400 mg once daily and explain the difference between tablet and IV formulations.
Advise the tablet is taken whole with a full glass of water and to separate antacids or iron supplements by at least 4–8 hours.
Explain signs that require immediate attention: tendon pain, pins‑and‑needles, severe diarrhoea, chest pain or syncope.
Storage advice: store tablets at 20–25°C, keep dry and protect from light; IV handling follows hospital protocols.
- Counselling Checklist: Verify allergies; check ECG history; review concurrent medicines; advise on missed dose; document counselling in the e‑health record.
- ADR Flowchart (Brief): If tendon pain occurs → stop drug → arrange urgent clinical review → report to TGA; if severe rash or breathing difficulty → emergency care.
For rural patients, arrange timely follow‑up by phone or local clinic and discuss PBS or cost options during dispense.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5–7 days |
| Melbourne | Victoria | 5–7 days |
| Brisbane | Queensland | 5–7 days |
| Perth | Western Australia | 5–7 days |
| Adelaide | South Australia | 5–7 days |
| Canberra | Australian Capital Territory | 5–7 days |
| Hobart | Tasmania | 5–7 days |
| Darwin | Northern Territory | 5–9 days |
| Gold Coast | Queensland | 5–9 days |
| Newcastle | New South Wales | 5–9 days |
| Wollongong | New South Wales | 5–9 days |
| Geelong | Victoria | 5–9 days |
| Townsville | Queensland | 5–9 days |