
Theophylline
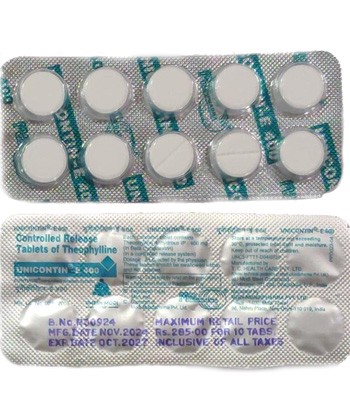
Theophylline
- In our pharmacy, you can buy theophylline without a prescription, with delivery in 5–14 days throughout Australia. Discreet and anonymous packaging.
- Theophylline is used to treat asthma and chronic obstructive pulmonary disease (COPD) and to stimulate breathing in certain situations; it is a methylxanthine bronchodilator that works mainly as a non‑selective phosphodiesterase inhibitor and adenosine receptor antagonist, increasing intracellular cAMP and producing bronchodilation and central respiratory stimulation.
- The usual dose is typically 200–400 mg per day in divided doses for immediate‑release formulations or 300–400 mg once daily for sustained‑release formulations; target therapeutic plasma concentrations are generally 10–20 mg/L (10–20 µg/mL).
- The form of administration is oral (tablets or capsules, immediate‑ or sustained‑release) and intravenous infusion in acute or hospital settings.
- The effect of the medication begins within about 30–60 minutes after an oral dose (intravenous administration works faster, often within 15–30 minutes).
- The duration of action is around 4–8 hours for immediate‑release preparations and approximately 12–24 hours for sustained‑release formulations.
- Do not consume alcohol or limit alcohol intake, as alcohol can increase side effects and alter theophylline metabolism, raising the risk of toxicity.
- The most common side effect is nausea (other frequently reported effects include headache, insomnia, tremor and palpitations).
- Would you like to try theophylline without a prescription?


Latest Research Highlights — Australian + Global Evidence
- INN (International Nonproprietary Name): not specified
- Brand Names Available In Australia: not specified
- ATC Code: not specified
- Forms & Dosages: not specified
- Manufacturers In Australia: not specified
- Registration Status In Australia: not specified
- OTC / Rx Classification: not specified
Are older oral bronchodilators still useful in 2024?
Recent literature to mid‑2024 continues to show theophylline as a second‑line, older bronchodilator with declining routine use in asthma but limited niche benefit in COPD and selected acute settings.
Systematic reviews and guideline updates including GINA and contemporary COPD reviews conclude inhaled therapies outperform oral methylxanthines for both control and safety.
Where theophylline remains used it is mainly as an add‑on when inhaled therapy is insufficient or unavailable, or in some hospital settings where IV aminophylline is indicated.
Australian hospital audits and small cohort studies report modest mean FEV1 gains often under 10%, alongside a higher rate of adverse events and added monitoring burden.
Neonatal practice in Australia has largely replaced theophylline with caffeine citrate for apnoea of prematurity due to clearer safety and dosing advantages.
Pharmacokinetic research emphasises highly variable clearance mediated by CYP1A2, and marked interaction potential with agents such as ciprofloxacin and fluvoxamine, plus lifestyle factors like smoking.
Key safety signal remains the narrow therapeutic window where toxicity—nausea, tremor, arrhythmia and seizures—increases above serum concentrations typically greater than 20 mg/L.
| Study Type | Outcome Summary | Practical Note |
|---|---|---|
| Systematic Reviews (Global) | Inhaled LABA/LAMA/ICS combinations outperform oral theophylline for control and safety. | Supports inhaled optimisation before theophylline add‑on. |
| Australian Hospital Audits | Small FEV1 gains (<10%) but increased adverse events and monitoring needs. | Useful niche role in COPD where inhaled therapy is inadequate or inaccessible. |
| Neonatal Cohorts | Caffeine citrate preferred over theophylline for apnoea of prematurity. | Theophylline appears only in resource‑limited settings for neonates. |
Data Highlight: Aim for steady‑state serum theophylline ~10–20 mg/L for acute therapy, with many clinicians preferring 10–15 mg/L for chronic maintenance to reduce side effects.
Clinical Effectiveness In Australia — TGA & Real‑World Outcomes
Who in Australia still prescribes theophylline and why?
Australian clinical registries and TGA adverse‑event reports show limited but ongoing use of theophylline in outpatient COPD and selected hospital contexts.
TGA product listings permit approved bronchodilator formulations, and prescribing patterns in the community favour modified‑release products such as Nuelin SR for maintenance dosing.
Real‑world data typically show small improvements in symptoms and FEV1 compared with placebo, but with a higher rate of side effects and treatment discontinuation than modern inhaled combinations.
PBS subsidy and listing details vary by formulation and indication; clinicians commonly prescribe generically or rely on hospital supply for IV aminophylline infusions in acute care.
Practical outcome in Australian cohorts is that benefit is most consistent when inhaled therapy cannot be tolerated, not available, or is insufficient—especially in severe COPD with persistent symptoms.
Regular monitoring, including serum theophylline levels and ECG where indicated, has been associated with fewer serious adverse events in observational studies from Australian centres.
| TGA Registered Indication | PBS Subsidy Status | Typical Monitoring Frequency |
|---|---|---|
| Adjunct Bronchodilator For Chronic Airways Disease | Check Current PBS Schedule | Serum levels 3–5 days after change, then periodic (eg, 3–6 months) |
| IV Aminophylline For Selected Acute Use | Hospital Supply (variable PBS listing) | Serum levels during infusion; ECG if cardiac risk |
Indications & Expanded Uses (TGA/Off‑Label)
When might a clinician consider theophylline in practice?
Typical TGA‑aligned indications include adjunct bronchodilator therapy for chronic obstructive airways disease and as an add‑on in some chronic asthma regimens when inhaled therapies are insufficient or unsuitable.
Historically IV aminophylline was used for acute severe asthma; contemporary emergency and ICU guidelines now prefer nebulised bronchodilators and systemic corticosteroids, reserving IV aminophylline for selected intensive‑care cases.
Off‑label or less common uses seen in Australian practice include short‑term oral theophylline in remote settings where inhaler devices or spacer education are unavailable, symptomatic relief for refractory nocturnal asthma, and occasional use in adult sleep‑related hypoventilation strategies.
Neonatal use for apnoea of prematurity has largely shifted to caffeine citrate, and theophylline is now rare in Australian neonatal units except where resources are limited.
- Approved: Adjunct bronchodilator in COPD; add‑on in select asthma cases.
- Off‑Label: Remote‑setting short courses, nocturnal symptom relief, rare adult ventilatory support roles.
| Indication | When To Consider | Monitoring Requirements |
|---|---|---|
| Maintenance COPD | If inhaled therapy ineffective or not tolerated | Baseline then steady‑state serum checks; liver function |
| Severe Acute Exacerbation (IV Aminophylline) | ICU‑only, selected refractory cases | Serum levels during infusion; ECG monitoring |
Composition & Brand Landscape In Australia
What formulations are seen in community and hospital practice?
The active ingredient is theophylline, a methylxanthine bronchodilator with central nervous system stimulant properties.
Common Australian formulations include immediate‑release tablets or capsules, sustained/modified‑release oral tablets commonly marketed as Nuelin SR in Australia, and IV aminophylline preparations for parenteral use.
Typical oral strengths encountered in practice include 200 mg, 250 mg and 300 mg modified‑release tablets, though exact market availability varies by supplier and stock.
Generic theophylline products are present in community pharmacies while brand recognition remains strongest for Nuelin‑labelled SR products.
| Formulation Type | Common Strengths | Route | Typical Packaging |
|---|---|---|---|
| Modified‑Release Tablets (SR/CR) | 200 mg, 250 mg, 300 mg | Oral | Blister packs or bottles |
| Immediate‑Release Tablets/Capsules | Various | Oral | Bottles / blister |
| Aminophylline For Injection | IV ampoules (hospital preparations) | Parenteral | Ampoules for infusion |
Brands Noted In Practice: Nuelin SR and several generics; check PBS schedule for subsidy and availability at time of prescribing.
Contraindications & Special Precautions
Who should avoid theophylline or be treated with extra caution?
Absolute contraindications include known hypersensitivity to theophylline or formulation excipients.
Important relative contraindications and precautions include significant hepatic impairment due to reduced clearance, uncontrolled cardiac arrhythmias or severe coronary disease because of arrhythmia risk, and pre‑existing seizure disorders since high serum levels lower seizure threshold.
Pregnancy and lactation require specialist input because theophylline crosses the placenta and is excreted in breast milk; use only if benefits outweigh risks.
Elderly patients often need lower starting doses and closer monitoring because of reduced clearance and comorbidities that increase interaction risk.
In Indigenous and remote populations it is important to provide culturally appropriate counselling and adherence support, recognising that comorbidities such as hepatic disease and alcohol use can alter theophylline metabolism.
- High‑Risk Checklist: Severe liver disease; unstable cardiac disease; history of seizures; pregnancy without specialist advice; inability to comply with monitoring.
- Driving/Work Safety: Dizziness, tremor or seizures may impair driving or machinery operation—advise caution.
Dosage Guidelines & Therapeutic Monitoring
How is dosing adjusted to balance benefit and safety?
Oral modified‑release regimens in adults typically start around 200–400 mg once or twice daily depending on formulation and clinical need, with individualisation required.
Acute severe exacerbations historically used IV aminophylline with a loading dose near 5–6 mg/kg over 20 minutes followed by an infusion titrated to serum levels, but local ICU protocols should be followed.
Therapeutic drug monitoring is central to safe use—target steady‑state serum concentrations commonly cited as 10–20 mg/L for acute therapy, with many clinicians preferring 10–15 mg/L for chronic maintenance to reduce side‑effects.
Check trough serum theophylline 3–5 days after initiation or after a dose change, and sooner if interacting drugs are started or if toxicity is suspected.
Routine monitoring should include liver function, electrolytes and ECG when cardiac risk is present.
| Route | Example Dose | Monitoring |
|---|---|---|
| Oral SR (Maintenance) | 200–400 mg once or twice daily (individualised) | Level 3–5 days after change; then periodic 3–6 months if stable |
| IV Aminophylline (Acute) | Loading ~5–6 mg/kg then infusion per local ICU protocol | Serum level during infusion; ECG if indicated |
Dose Adjustments: Increase dose in cigarette smokers due to higher clearance; decrease dose in hepatic impairment and when co‑prescribed with CYP1A2 inhibitors.
Interactions Overview — Drugs, Food & Lifestyle
What commonly interacts with theophylline and what should patients avoid?
Theophylline is mainly metabolised via CYP1A2 and has many clinically significant interactions.
Strong CYP1A2 inhibitors that raise theophylline levels include ciprofloxacin, fluvoxamine and cimetidine—dose reduction or closer monitoring is required if these are co‑prescribed.
Inducers that lower theophylline levels include tobacco smoking, carbamazepine, phenytoin and rifampicin, and dosing may need to increase with persistent inducers.
Macrolide antibiotics and some antifungals can also elevate concentrations; monitor levels if these are used.
Caffeine and related methylxanthines add to stimulant effects and side‑effects, so counsel patients to limit coffee, energy drinks and some over‑the‑counter stimulants.
| Agent | Effect / Advice |
|---|---|
| Ciprofloxacin, Fluvoxamine | Increase serum theophylline → reduce dose or intensify monitoring |
| Carbamazepine, Phenytoin, Rifampicin | Decrease serum theophylline → may require dose increase |
| Tobacco Smoking | Induces clearance → smokers may need higher doses; stopping smoking requires dose reassessment |
| Caffeine | Increases stimulant side effects → advise limitation |
Patient Checklist: Tell your pharmacist about all medicines, antibiotics and herbal supplements, stick to a consistent caffeine intake and notify clinicians when you stop or start smoking.
Cultural Perceptions & Patient Habits In Australia
How do Australians feel about taking an older oral bronchodilator that needs blood tests?
Many patients prefer inhaled therapies for asthma and COPD and are sceptical about older oral medicines that require routine serum monitoring.
Online and community forums commonly show confusion about why blood tests are needed and concern about side effects, which makes pharmacist counselling a trusted touchpoint.
Price sensitivity and reliance on PBS influence uptake, and discount retailers often drive generic prescribing and patient choice.
Rural and remote patients may have limited access to inhaler education and specialist review, which sometimes leads clinicians to consider oral options where reliable follow‑up cannot be guaranteed.
Indigenous health contexts need culturally competent education that links monitoring to safety, explains the effect of smoking on dosing, and supports smoking cessation as part of respiratory care.
Telehealth and e‑prescribing have improved access to specialist advice and repeat prescriptions but can make timely blood testing more challenging for some patients.
- "I was told I'd need blood tests every few months; I didn't expect that with a tablet." — anonymised patient forum comment.
- "Living remotely, carrying spacers and inhalers is hard; our clinic sometimes uses an oral option until follow‑up is possible." — anonymised clinician note.
Culturally relevant counselling tips include clear explanations of monitoring purpose, arranging local pathology in advance, using plain language and involving family or community health workers where appropriate.
Availability & Pricing Patterns (Australia)
Where can patients obtain theophylline and what does it cost?
Theophylline SR products such as Nuelin SR and generics are stocked in major Australian pharmacy chains including Chemist Warehouse, Priceline and TerryWhite Chemmart, while IV aminophylline is primarily hospital stock.
PBS subsidy varies by formulation and approved indication, so prescribers and pharmacists should confirm the current PBS schedule at the time of prescribing.
Retail prices for generics and branded SR formulations are typically competitive, and discount chains often run promotions or price‑match on older oral agents.
Online pharmacies and telehealth services can dispense oral SR products, but ensure patients have local access to required blood tests before ordering.
| Supply Channel | Availability | Likely Cost | Monitoring Implication |
|---|---|---|---|
| Community Pharmacy (Chains) | SR Tablets, Generics, Nuelin SR | Private purchase or PBS where listed | Arrange pathology and follow‑up locally |
| Hospital Pharmacy | IV Aminophylline and bulk supply | Hospital supply (PBS/hospital budget) | Inpatient monitoring available |
| Online Pharmacy / Telehealth | Oral SR (private scripts) | Private price; watch for promotions | Ensure local pathology access before dose changes |
In our online pharmacy, theophylline is available without a prescription, with discreet delivery to Australia in 5–14 days.
Comparable Medicines And Clinician Preference Checklist
What should clinicians try before reaching for theophylline?
Modern alternatives include inhaled long‑acting beta2 agonists, long‑acting muscarinic antagonists, inhaled corticosteroids and fixed‑dose combination inhalers, which provide better efficacy and safety for most patients.
For nocturnal symptoms, optimising inhaler technique and timing is preferred before considering systemic options.
In acute exacerbations, nebulised beta2 agonists, systemic corticosteroids and oxygen are first‑line; IV aminophylline is now rarely first choice.
- Pros Of Theophylline: Oral route useful where inhaled delivery is impractical; low cost; possible modest anti‑inflammatory effects at low concentrations.
- Cons: Narrow therapeutic index, frequent monitoring, many drug interactions and tolerability issues.
Decision Tree For Clinicians: Optimise Inhaled Therapy → Consider LAMA Or Leukotriene Antagonist Add‑On → Trial Theophylline Only If Alternatives Unsuitable Or Inaccessible.
FAQ — Common Patient Questions
Patients often ask whether theophylline is safe and how monitoring works.
Q: Is theophylline safe?
A: Theophylline can be safe if carefully monitored, but it has a narrow therapeutic window and requires regular serum monitoring to reduce the risk of serious toxicity.
Q: How often do I need blood tests?
A: Check a trough serum theophylline level 3–5 days after starting or changing the dose, then at intervals determined by stability—commonly every 3–6 months—or sooner if symptoms or interacting medicines occur.
Q: Can I drink coffee?
A: Limit caffeine intake because it adds to stimulant effects and may worsen side effects such as tremor and palpitations.
Q: If I stop smoking will my dose change?
A: Yes—smoking increases theophylline clearance; stopping can raise serum levels and usually requires dose reduction and monitoring.
When To Ring Your Pharmacist Or GP: severe nausea, persistent palpitations, tremor, confusion, fainting or any seizure activity.
Guidelines For Proper Use — Pharmacist Counselling & PBS/TGA Notes
What should be covered in a single counselling session?
Counselling points include the reason for therapy as an add‑on bronchodilator, the importance of taking modified‑release tablets whole (do not crush), and adhering to timing to maintain steady levels.
Explain signs of toxicity—nausea, palpitations, tremor, confusion and seizures—and advise immediate medical review if these occur.
Reinforce the need for baseline and scheduled serum levels, and the importance of notifying all clinicians when starting antibiotics, SSRIs or when changing smoking habits.
Storage advice: keep in a cool, dry place out of reach of children and pets.
For prescribers, document the indication, planned monitoring schedule, potential interactions checked and provide a printed patient information sheet outlining when to seek help.
Regulatory reminder: check current TGA product information and the PBS for up‑to‑date subsidy and indication details; hospital protocols should be used for IV aminophylline dosing.
One‑Page Patient Handout Template (Key Lines): purpose of medicine; how to take SR tablets; when blood tests are needed; warning signs; contact details for urgent advice.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Darwin | Northern Territory | 5-7 days |
| Gold Coast | Queensland | 5-9 days |
| Newcastle | New South Wales | 5-9 days |
| Wollongong | New South Wales | 5-9 days |
| Geelong | Victoria | 5-9 days |
| Sunshine Coast | Queensland | 5-9 days |
| Cairns | Queensland | 5-9 days |
| Townsville | Queensland | 5-9 days |