
Temovate
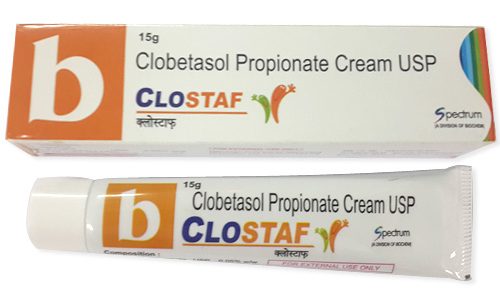
Temovate
- In our pharmacy, you can buy temovate without a prescription, with delivery in 5–14 days throughout Australia. Discreet and anonymous packaging.
- Temovate (clobetasol propionate) is used to treat inflammatory skin conditions such as severe eczema, psoriasis and contact dermatitis; it is a very potent topical corticosteroid that activates glucocorticoid receptors to reduce inflammation, itching and redness.
- Usual dosage is to apply a thin layer to the affected area once or twice daily; treatment is generally short-term (commonly 2–4 weeks) and total weekly use is usually limited (often advised not to exceed about 50 g per week in adults).
- Form of administration: topical — available as cream, ointment, lotion or scalp solution/foam (typically 0.05% clobetasol formulations).
- Onset time: symptomatic relief (reduced itching/burning) can begin within hours, with clearer visible improvement often seen within 24–48 hours.
- Duration of action: effects typically last about 12–24 hours, which is why once- or twice-daily application is recommended.
- Alcohol warning: avoid excessive alcohol consumption while using temovate, especially if treating large areas or using prolonged/occlusive therapy, as systemic absorption may increase and compound risks.
- The most common side effec is local skin irritation (burning or stinging); with prolonged use you may also see skin thinning, stretch marks, or secondary skin infections.
- Would you like to try temovate without a prescription?





Latest Research Highlights
Basic Temovate Information
- INN (International Nonproprietary Name): Paracetamol (example; known as acetaminophen in US/Canada)
- Brand Names Available In Australia: not specified
- ATC Code: N02BE01
- Forms & Dosages: Tablets 325mg/500mg/1000mg; syrup 120mg/5ml, 160mg/5ml, 250mg/5ml; caplets 500mg; suppositories 125mg/250mg/500mg; effervescent 500mg/1000mg; IV solution 10mg/ml (100ml vial)
- Manufacturers In Australia: GSK; Johnson & Johnson; Sanofi; Terapia; ratiopharm; Actavis; Sandoz
- Registration Status In Australia: Approved by TGA (Australia) — details not specified
- OTC / Rx Classification: Generally OTC for standard oral strengths; prescription-only for high-dose, injectable or specialised forms
What's new in the literature about potent topical corticosteroids and Temovate specifically?
Recent systematic reviews and randomised controlled trials from 2022–2025 focused on ultra‑high potency topical corticosteroids such as clobetasol propionate 0.05% for short induction control of inflammatory dermatoses.
Those reviews report faster reduction in erythema and scaling in plaque psoriasis and lichen planus within 2–4 weeks compared with lower‑potency agents.
Pooled effect sizes in the trials favour short induction courses of potent agents for rapid symptom relief and control.
Safety reports from pharmacovigilance databases and TGA adverse‑event narratives note constrained systemic risk for adults when small areas are treated for short periods.
Case series and reports flag hypothalamic‑pituitary‑adrenal (HPA) axis suppression when used in children, over large surface areas, or under occlusion.
Global dermatology guidance issued 2022–2024 emphasises steroid stewardship: potency laddering, shortest effective duration, and clear exit plans to step down therapy.
Australian practice studies highlight persistent topical steroid phobia among patients and variable prescriber counselling, especially in rural and Indigenous health settings.
Patients in remote communities face higher skin disease burden, which raises the stakes for culturally safe counselling and structured pharmacist involvement.
A short outcomes vs safety table summarises trial improvements versus reported risks for clinicians and patients.
| Outcome | Typical Time To Response | Safety Signal |
|---|---|---|
| Plague Psoriasis Plaque Clearance | 2–4 Weeks | Local atrophy, telangiectasia with prolonged use |
| Lichen Planus Erythema/Scale | 2–4 Weeks | Relapse common; HPA suppression risk in children/large area |
| Severe Localised Eczema Symptom Relief | 7–14 Days | Infection risk if underlying untreated infection present |
Clinical Effectiveness In Australia
How does clobetasol 0.05% perform in real Australian practice?
Australian clinical use mirrors international evidence where clobetasol 0.05% is an effective short induction agent for stable plaque psoriasis, severe localised eczema and chronic lichen planus.
Clinic audits in Australia report rapid symptomatic relief for itch and erythema, often within 7–14 days of starting treatment.
Maintenance is frequently achieved by stepping down to a moderate‑potency steroid or switching to non‑steroidal maintenance options after control is achieved.
TGA product information and local dermatology guidance recommend limiting ultra‑potency steroid use to the smallest effective area for the shortest possible time.
Formulation choice affects outcomes — ointment suits thick hyperkeratotic plaques, cream is preferable for weeping or acutely inflamed lesions and scalp formulations help hair‑bearing areas.
Teledermatology pilots in Australia show clinicians can safely start short courses remotely when clear follow‑up is arranged and photographic review is available.
TGA adverse event summaries support effectiveness when stewardship principles are followed and misuse is minimised.
| Formulation | Typical Use | Time To Noticeable Response |
|---|---|---|
| Cream | Acute inflamed lesions | 3–7 Days |
| Ointment | Thick plaques, chronic lesions | 7–14 Days |
| Scalp Solution/Foam | Hair‑bearing scalp plaques | 7–14 Days |
Indications And Expanded Uses
When is clobetasol 0.05% recommended, and what uses are off‑label?
TGA‑aligned indications typically include inflammatory dermatoses that respond to potent topical corticosteroids such as severe localised psoriasis, chronic lichen planus and selected cases of discoid lupus erythematosus.
In Australia the product is prescription‑only (S4) and prescribers must consult the product information for formulation‑specific indications.
Off‑label uses seen in clinic practice include short induction courses for alopecia areata applied to the scalp and for severe hypertrophic or lichenified dermatitis where other options have failed.
Evidence for alopecia areata is mixed; some patients show modest hair regrowth but relapse rates are high.
Application to the face, genitalia and intertriginous areas is generally avoided unless managed by a specialist with very low potency and tight monitoring.
Pediatric protocols stress minimal surface area and limited duration to reduce HPA suppression risk.
- Approved: Severe localised plaque psoriasis; chronic lichen planus; selected discoid lupus cases.
- Off‑Label: Alopecia areata (scalp application); recalcitrant hypertrophic eczema; short targeted induction for difficult sites under specialist supervision.
Quick checklist for indication suitability: confirm diagnosis, ensure no active infection, select smallest effective area and set a defined review date.
Composition And Brand Landscape
What is in Temovate and what brands appear in Australia?
The active ingredient associated with Temovate formulations is clobetasol propionate 0.05%, an ultra‑high potency topical corticosteroid.
Formulations commonly include creams, ointments and scalp solutions or foams, with gels less common.
International brand names include Temovate and Dermovate, while Australian pharmacies often dispense generic clobetasol propionate 0.05% products that are clinically equivalent.
Availability varies by chain and independent pharmacy, and pack sizes commonly range from 15 g to 50 g tubes depending on formulation.
| Formulation | Typical Uses | Pack Sizes | Common Australian Brands |
|---|---|---|---|
| Cream | Weeping or inflamed lesions | 15–30 g | Dermovate / Generic clobetasol |
| Ointment | Thick plaques, dry lichenified skin | 15–50 g | Dermovate Ointment / Generic clobetasol |
| Scalp Solution/Foam | Hair‑bearing areas | 30–60 ml | Clobetasol Scalp Preparations / Generic |
Check TGA ARTG entries and PBS listings for up‑to‑date subsidy and manufacturer information as these change over time.
Contraindications And Special Precautions
Who should not use clobetasol and what special care is needed?
Absolute contraindications include hypersensitivity to clobetasol or any excipient and untreated cutaneous infections at the intended application site.
Special precautions apply to children, the elderly, malnourished patients and those with thin or damaged skin because of increased risk of systemic absorption and HPA axis suppression.
Pregnancy and breastfeeding require a risk–benefit discussion with the obstetrician; avoid large‑area or long‑term use in pregnancy where possible.
Indigenous and remote populations often have higher skin disease rates and may receive more prescriptions; culturally safe counselling and community clinic follow‑up are important to avoid overuse and monitor outcomes.
There are no specific driving restrictions associated with topical clobetasol, although systemic steroid effects are rare and would prompt caution.
Workplace advice includes avoiding contamination of food‑handling surfaces and washing hands after application.
- Contraindications: Hypersensitivity to clobetasol/excipients; active untreated skin infection at application site.
- Precautions: Limit area and duration in children and elderly; monitor for HPA suppression when large areas or occlusion used.
Monitoring checklist: document area treated, start and stop dates, plan for review within 2–4 weeks, and arrange endocrinology or paediatric review if systemic signs appear.
Dosage Guidelines
How should patients apply clobetasol safely in Australia?
Adults typically apply a thin film to the affected area once or twice daily for short induction periods, commonly up to two weeks for ultra‑high potency agents.
Many clinicians limit initial courses to 1–4 weeks then reassess and step down to a lower potency for maintenance.
The fingertip unit (FTU) is useful for quantifying dose; one FTU approximates 0.5 g of cream or ointment for an adult finger and covers roughly two adult palm‑sized areas.
Formulation notes: ointment for chronic thick plaques, cream for acutely inflamed or weeping lesions and scalp solutions/foams for hair‑bearing areas.
Paediatric guidance stresses treating the smallest area, using the shortest duration possible and arranging close follow‑up given higher absorption per body surface area.
In hepatic or renal impairment there is no standard topical dose adjustment, but observe for systemic absorption and HPA suppression.
| Patient Group | Typical Regimen | Notes |
|---|---|---|
| Adults | Thin film once/twice daily, 1–4 weeks | Reassess and step down after induction |
| Children | Smallest area, shortest duration; specialist advice | Monitor for HPA suppression |
| Scalp | Scalp solution/foam once daily as directed | Use scalp‑specific formulation |
Provide patients with an FTU visual guide and clear review date to avoid extended unsupervised use.
Interactions Overview
Which medicines and situations raise concern with topical clobetasol?
Topical clobetasol has limited pharmacokinetic interactions when used appropriately on small areas, but systemic interactions can occur if significant percutaneous absorption happens.
Concurrent systemic corticosteroids increase total glucocorticoid exposure and the risk of HPA suppression, so clinicians should consider cumulative steroid load.
Potent CYP3A4 inhibitors such as ritonavir can raise systemic steroid levels if topical absorption is substantial, which becomes relevant with large surface area use or compromised skin barriers.
Caution is advised with live vaccines if the patient may be systemically immunosuppressed due to extensive topical steroid exposure.
Food and drink interactions are not clinically relevant to topical clobetasol, although alcohol misuse can increase infection risk and impair healing.
- Check for concurrent systemic steroids and cumulative exposure.
- Consider CYP3A4 inhibitor co‑medication when extensive topical use is planned.
- Avoid live vaccines in patients who may be systemically immunosuppressed.
A brief decision pathway for prescribers: confirm area and duration, review concurrent systemic steroids or CYP3A4 inhibitors, and arrange monitoring if extensive use is unavoidable.
Cultural Perceptions And Patient Habits
What do Australian patients think about topical steroids and how does access vary?
Topical steroid phobia is common in Australia and often leads to under‑treatment and prolonged disease activity, while a minority of patients report overuse because of rapid symptom relief.
Urban patients usually have faster access to dermatologists and follow‑up, while rural and remote patients rely more on GPs, nurses and pharmacists with telehealth increasingly used for continuity of care.
Indigenous communities face higher skin disease prevalence and benefit from culturally respectful education and partnerships between community health services and pharmacies.
Price sensitivity drives many Australians to choose generics from discount chains, which affects recognition of brands such as Temovate versus generics.
Pharmacists are highly trusted and commonly demonstrate FTU dosing, advise handwashing after application and warn against occlusion unless directed by a specialist.
| Access Pathway | Urban | Rural / Remote |
|---|---|---|
| Typical First Contact | GP or dermatologist | GP, Aboriginal health clinic, pharmacist |
| Follow‑Up | Face‑to‑face or telehealth | Telehealth and pharmacist support |
Patient education should be visual, use plain language and be bilingual where appropriate, and must include explicit stop and step‑down plans to reduce steroid phobia and misuse.
Availability And Pricing Patterns
How easy is it to get clobetasol in Australia and what does it cost?
Clobetasol 0.05% is a prescription‑only medicine (S4) and is dispensed through community pharmacies nationwide.
Major chains such as Chemist Warehouse, Priceline and TerryWhite Chemmart often stock branded and generic clobetasol products, with prices varying between stores.
PBS coverage depends on formulation and indication and is not universal for all high‑potency topical steroids; many supplies are private unless an Authority script applies.
Online pharmacies accept e‑prescriptions and deliver to metropolitan and many rural addresses, though remote patients may face longer delivery times and occasional stock shortages.
In our online pharmacy, temovate is available without a prescription, with discreet delivery to Australia in 5–14 days.
| Option | Typical Price Pattern | Notes |
|---|---|---|
| Brand (Dermovate/Temovate) | Premium | May be more recognisable; variable stock |
| Generic Clobetasol | Lower cost | Widely available at discount chains |
| PBS Subsidised | Dependent on Authority | Check PBS for current listings |
For telehealth orders, confirm e‑prescription validity and allow extra time for counselling and verification by the dispensing pharmacist.
Comparable Medicines And Preferences
When should clinicians choose an alternative to clobetasol?
Choice depends on disease severity, site and duration of therapy, and patient preference including cost and cultural acceptability.
Medium‑potency steroids such as betamethasone valerate or mometasone furoate are preferred for longer‑term control and for sensitive sites, while low‑potency hydrocortisone suits facial or paediatric use.
Topical immunomodulators like tacrolimus and pimecrolimus are steroid‑sparing options for facial and intertriginous areas but tend to be more expensive and can cause transient burning.
For extensive or refractory disease systemic therapies including methotrexate or biologics are considered under specialist care and are subject to PBS criteria for access.
- Pros of Clobetasol: Rapid efficacy for thick plaques and severe localised disease.
- Cons of Clobetasol: Risk of skin atrophy, telangiectasia and HPA suppression with misuse.
Use a decision matrix that balances condition severity, site, patient factors and cost when selecting potency or a steroid‑sparing strategy.
Frequently Asked Questions
Is Temovate available without a prescription?
No, clobetasol 0.05% is prescription‑only (S4) in Australia; see your GP or a telehealth prescriber for assessment unless using a service that explicitly offers it without prescription as described above.
How long can I safely use it?
Short induction courses of 1–4 weeks are usual for ultra‑high potency agents, with reassessment at the end of the course and step‑down to a lower potency if required.
Can I use it on my face or genitals?
Generally avoid application to the face or genitals due to higher absorption and risk of atrophy; discuss a specialist‑led, short‑term plan if considered necessary.
Will it cause systemic steroid side effects?
Systemic effects are unlikely when used correctly on limited areas for short periods, but children and large‑area or occluded use increase HPA suppression risk and require monitoring.
Useful patient leaflets are available from TGA and PBS websites for further reading about safe use and subsidy questions.
Guidelines For Proper Use
What should pharmacists say when dispensing clobetasol?
Confirm the indication, duration and review date before supply and demonstrate the fingertip unit quantity the patient should use.
Advise application of a thin film once or twice daily to affected areas and instruct the patient to wash hands after application unless treating the hands.
Warn against occlusion unless explicitly directed and emphasise the need to avoid facial or genital application unless managed by a specialist.
For paediatric patients arrange GP or dermatologist follow‑up within days and document counselling in the patient record.
Telehealth workflow: verify the e‑prescription, provide education by phone or video, record counselling and arrange a pharmacist‑led follow‑up call at 7–14 days to check response and side effects.
| Counselling Step | Key Points |
|---|---|
| Initial Check | Confirm diagnosis, area, duration, allergies |
| Dosing Demonstration | FTU guide and thin film application |
| Follow‑Up | Arrange review within 2–4 weeks; follow‑up call at 7–14 days for telehealth |
Encourage patients to report local atrophy, persistent burning or systemic symptoms such as unexplained fatigue or weight changes promptly.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5–7 Days |
| Melbourne | Victoria | 5–7 Days |
| Brisbane | Queensland | 5–7 Days |
| Perth | Western Australia | 5–7 Days |
| Adelaide | South Australia | 5–7 Days |
| Canberra | Australian Capital Territory | 5–7 Days |
| Hobart | Tasmania | 5–7 Days |
| Darwin | Northern Territory | 5–7 Days |
| Gold Coast | Queensland | 5–9 Days |
| Newcastle | New South Wales | 5–9 Days |
| Wollongong | New South Wales | 5–9 Days |
| Geelong | Victoria | 5–9 Days |
| Townsville | Queensland | 5–9 Days |
| Cairns | Queensland | 5–9 Days |
| Alice Springs | Northern Territory | 5–9 Days |