
Tamsulosin
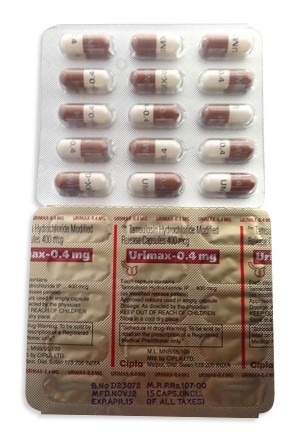
Tamsulosin
- In our pharmacy you can buy tamsulosin without a prescription, with delivery across Australia (discreet packaging available); availability may vary by outlet.
- Tamsulosin is used to relieve lower urinary tract symptoms (LUTS) due to benign prostatic hyperplasia (BPH). It is a selective alpha‑1A adrenergic antagonist that relaxes smooth muscle in the prostate and bladder neck to improve urine flow.
- The usual dose is 0.4 mg once daily, taken after the same meal each day; a 0.2 mg dose is used in some regions and lower doses may be prescribed for specific patients.
- Administered orally as capsules or tablets (commonly modified‑release 0.4 mg capsules); combination products with dutasteride/finasteride are also available.
- Onset time: pharmacological effects begin within hours (peak plasma concentration ~4–6 hours for modified‑release), but noticeable symptom improvement is often seen within days to a few weeks.
- Duration of action: designed for once‑daily dosing with therapeutic effect lasting about 24 hours (elimination half‑life generally ~9–13 hours depending on formulation).
- Alcohol warning: avoid excessive alcohol as it can increase dizziness and the risk of orthostatic hypotension; do not drive or operate machinery until you know how tamsulosin affects you.
- The most common side effect is dizziness, particularly on standing (orthostatic hypotension); other common effects include abnormal ejaculation, headache, nasal congestion, fatigue and gastrointestinal upset.
- Would you like to try tamsulosin without a prescription?
Basic Tamsulosin Information
- INN (International Nonproprietary Name): Tamsulosin.
- Brand Names Available In Australia: not specified.
- ATC Code: G04CA02.
- Forms & Dosages: 0.4 mg modified‑release oral capsule is the standard global formulation; 0.2 mg formulations exist in some markets.
- Manufacturers In Australia: not specified.
- Registration Status In Australia: not specified.
- OTC / Rx Classification: Prescription Only (Rx).
Latest Research Highlights
Are you wondering whether tamsulosin still stacks up in recent studies?
Recent Australian and international work from 2022–2024 continues to support tamsulosin as a first‑line alpha‑1A selective agent for symptomatic relief of lower urinary tract symptoms associated with benign prostatic hyperplasia.
Randomised trials and meta‑analyses report consistent short‑term improvements in symptom scores (IPSS) and peak urinary flow (Qmax), with many patients noticing benefit within days to weeks.
Combination therapy studies pairing tamsulosin with 5‑alpha‑reductase inhibitors show better long‑term reduction in progression for larger prostates but do not usually bring faster symptom relief.
Safety observations remain aligned with the known profile: orthostatic dizziness, ejaculatory disturbance, nasal congestion and rare angioedema have been reported.
Intraoperative floppy iris syndrome is a recognised perioperative concern that should be communicated before cataract surgery.
Australian pharmacovigilance summaries to the Therapeutic Goods Administration mirror global reports up to mid‑2024 without new class‑wide warnings.
Gaps in the evidence include limited Australian long‑term real‑world adherence studies and sparse outcomes data for rural and Indigenous populations.
| Trial Endpoint | Typical Effect Observed | Safety Observations | Australian Vs Global Cohort |
|---|---|---|---|
| IPSS Improvement | Short‑term symptomatic improvement reported | Dizziness, ejaculatory change, nasal congestion | Global: consistent trial data; Australian: limited long‑term real‑world data |
| Qmax (Peak Flow) | Measurable increase in peak urinary flow | Generally well tolerated; monitor hypotension in frail patients | Global trials robust; Australian comparative data sparse |
Clinical Effectiveness In Australia
What do Australian doctors and pharmacists see in everyday practice?
Tamsulosin is widely used in Australian primary care and by urologists for symptomatic BPH management and is typically prescribed in line with PBS and routine‑funding considerations.
Real‑world effectiveness in Australia matches clinical trial findings with many patients reporting meaningful symptom relief and objective improvements in urinary flow measures.
The Therapeutic Goods Administration adverse event monitoring confirms expected patterns and indicates severe hypotension events are uncommon.
Clinicians should still watch for syncope or falls in frail older men and those with significant cardiovascular disease.
PBS claims data inform prescribing volumes and adherence metrics, but regional variation exists with metropolitan patients generally accessing urology follow‑up more readily than rural patients.
Telehealth e‑prescriptions and community pharmacists at chains such as Chemist Warehouse, Priceline and TerryWhite Chemmart support initiation and adherence counselling.
Standard dosing in Australia is 0.4 mg once daily taken after the same meal to reduce orthostatic effects.
| Measure | Trial Outcomes | Australian Real‑World Notes |
|---|---|---|
| IPSS | Short‑term symptom score improvement | Similar patient‑reported relief; follow‑up varies by region |
| Adverse Events | Orthostatic dizziness; ejaculatory change | TGA reports mirror global profile; severe events uncommon |
Indications And Expanded Uses
Who should consider taking tamsulosin and when is it used off‑label?
The TGA‑labelled indication in Australia is relief of lower urinary tract symptoms associated with benign prostatic hyperplasia in adult men.
Tamsulosin is a prescription‑only medicine and is not indicated for hypertension or female use, and it is contraindicated in children.
Off‑label uses encountered in practice include medical expulsive therapy for ureteric stones and facilitation of urinary catheter removal in select patients, though evidence for these uses is mixed and weaker than for BPH.
Clinicians must exclude prostate cancer before attributing urinary symptoms solely to BPH and should consider combination regimens with dutasteride or finasteride when prostate volume reduction is required.
Combination therapy is generally guided by prostate size, PSA and risk‑reduction goals.
- Approved: Relief of LUTS associated with BPH in adult men.
- Off‑Label: Ureteric stone expulsive therapy and catheter facilitation (evidence variable).
- Combination Therapy: Paired with 5‑alpha‑reductase inhibitors when prostate shrinkage is desired.
Primary care clinicians should follow local protocols and obtain informed consent when using off‑label approaches.
Composition And Brand Landscape
What’s inside the capsule and which brands might you see?
The active ingredient is tamsulosin hydrochloride, INN tamsulosin, classified under ATC code G04CA02.
The most common formulation globally is a modified‑release 0.4 mg capsule intended for once‑daily dosing after the same meal.
Global and generic manufacturers include Teva, Sandoz, Mylan, Sun Pharma and others, and notable international brand names include Flomax, Omnic, Harnal, Urimax and regionals.
In Australia the market is dominated by generics and branded MR presentations supplied through community pharmacies and hospital formularies.
Packaging is commonly 30 capsules per blister pack and local ARTG/TGA listings and PBS item numbers should be checked for exact product codes.
| Brand Name (Sample) | Manufacturer | Typical Pack Size |
|---|---|---|
| Flomax | Boehringer Ingelheim (international) | 30 capsules |
| Omnic | Astellas (international) | 30 capsules |
| Generic Tamsulosin | Teva, Sandoz, Mylan et al. | 30 capsules |
Contraindications And Special Precautions
Who should avoid tamsulosin and what safety checks matter?
Absolute contraindications include known hypersensitivity to tamsulosin or excipients and a history of orthostatic hypotension.
Severe hepatic impairment is generally a contraindication and severe renal impairment (CrCl < 10 mL/min) calls for caution.
Use with caution in people with significant cardiovascular disease due to risk of syncope.
Special Australian considerations include frail older adults, Aboriginal and Torres Strait Islander men with higher multimorbidity, and patients in safety‑critical roles such as heavy machinery operators or commercial drivers.
Pre‑surgical caution is important: inform ophthalmologists before cataract surgery because of the intraoperative floppy iris syndrome risk.
- Absolute Contraindications: Hypersensitivity to tamsulosin or excipients; history of orthostatic hypotension; severe hepatic impairment.
- Relative Contraindications: Severe renal impairment, significant cardiovascular disease, concurrent potent CYP inhibitors.
Pharmacists should use a short safety checklist covering falls risk, current antihypertensives and planned eye surgery before supply or counselling.
Dosage Guidelines
How should tamsulosin be taken for best results and safety?
The standard adult regimen is 0.4 mg once daily, taken after the same meal each day to reduce the chance of orthostatic hypotension and to improve absorption consistency.
Lower 0.2 mg formulations exist in some countries but 0.4 mg MR is the most common globally.
Tamsulosin is not indicated for children and routine dose reduction is not required for elderly patients, although careful monitoring for hypotension and falls is advised.
No dose adjustment is required for mild to moderate renal or hepatic impairment, but severe renal impairment (CrCl < 10 mL/min) and severe hepatic impairment warrant caution or avoidance.
Treatment is often long‑term and should be reassessed periodically for symptom benefit and the need for combination therapy.
If a dose is missed, the patient should take it as soon as they remember unless it is close to the next scheduled dose, and they should not double up.
In overdose, hypotension and syncope are possible and supportive emergency management is required.
Interactions Overview
Which medicines and substances can cause problems with tamsulosin?
Tamsulosin is metabolised by CYP3A4 and CYP2D6, so strong inhibitors of these enzymes may increase plasma concentrations and the risk of adverse effects.
Pharmacodynamic interactions are clinically important: combining tamsulosin with other antihypertensives, nitrates or PDE5 inhibitors can potentiate hypotension and syncope.
Alcohol may accentuate orthostatic effects and should be discussed with patients when counselling.
Avoid combining tamsulosin with other alpha‑adrenergic antagonists unless under specialist supervision because of additive blood‑pressure effects.
| Concomitant Drug | Interaction Type | Recommended Action |
|---|---|---|
| PDE5 Inhibitors (e.g. sildenafil) | Pharmacodynamic – increased hypotension risk | Warn patient; monitor blood pressure; consider timing/dose adjustments |
| CYP3A4/CYP2D6 Inhibitors (e.g. strong antifungals) | Pharmacokinetic – increased tamsulosin exposure | Monitor for adverse effects; consider specialist advice |
| Other Alpha Blockers | Additive hypotensive effects | Avoid combination unless supervised |
Use My Health Record and up‑to‑date medication lists when prescribing or dispensing to flag risky combinations in polypharmacy patients.
Cultural Perceptions And Patient Habits
Why do many Australian men delay treatment for urinary symptoms?
Stigma and a stoic attitude often lead men to normalise urinary symptoms as part of ageing and delay seeking help.
Price sensitivity is important and many patients favour lower‑cost generics or discount deals at large chains, with PBS subsidy status strongly influencing adherence.
Rural patients face longer waits for urology review and reduced pharmacy variety, making telehealth e‑prescriptions and community pharmacist counselling vital for access.
Trust in pharmacists is high and pharmacist‑led medication reviews and opportunistic screening can improve uptake and ongoing adherence.
Cultural competence is essential for Indigenous patients; use culturally safe communication and situate BPH management within broader multimorbidity care.
- Barriers: stigma, cost, limited rural specialist access, perceived normal ageing.
- Facilitators: pharmacist counselling, telehealth follow‑ups, pill organisers and medication synchronisation.
Practical strategies such as synchronised dispensing, SMS reminders and brief pharmacist scripts can increase persistence with tamsulosin therapy.
Availability And Pricing Patterns
How easy is it to get tamsulosin in Australia and what will it cost?
Tamsulosin is widely available through major community pharmacy chains such as Chemist Warehouse, Priceline and TerryWhite Chemmart and via accredited online pharmacies and telehealth services.
PBS listing status affects out‑of‑pocket cost; where subsidised, patients pay a reduced co‑payment while private prescriptions vary by brand and retailer.
Generics from Teva, Sandoz and others dominate the supply and normally ensure steady availability, but clinicians and pharmacists should verify ARTG/TGA entries and PBS item numbers when prescribing.
In our online pharmacy, tamsulosin is available without a prescription, with discreet delivery to Australia in 5-14 days.
| Purchase Route | Typical Pricing Range | Notes |
|---|---|---|
| PBS‑subsidised Prescription | Reduced co‑payment (varies) | Check current PBS schedule and patient eligibility |
| Private Prescription / Retail | Generics vary; discount retailers often cheapest | Compare prices across community chains |
| Online Pharmacy / Telehealth | Varies; delivery fees possible | Delivery options helpful for rural patients |
Comparable Medicines And Preferences
What are the alternative medicines and when might a clinician choose them?
Alternatives include other alpha‑blockers such as alfuzosin, doxazosin and silodosin and 5‑alpha‑reductase inhibitors like finasteride and dutasteride.
Alfuzosin is less selective, doxazosin has notable antihypertensive effects and silodosin is highly alpha‑1A selective but associated with higher rates of ejaculatory dysfunction.
Finasteride and dutasteride reduce prostate volume over months and are preferred when long‑term size reduction or PSA/prostate volume considerations justify their use.
Choice depends on symptom severity, prostate size and PSA, comorbid hypotension, sexual function priorities, cost and PBS coverage, and patient preference.
| Comparator | Pros | Cons |
|---|---|---|
| Alfuzosin | Effective for LUTS | Less selective than tamsulosin |
| Silodosin | High alpha‑1A selectivity | Higher ejaculatory dysfunction rates |
| Finasteride / Dutasteride | Reduce prostate size; lower progression risk | Months to effect; sexual side effects possible |
A simple prescriber algorithm should weigh symptom burden, prostate size, fall risk and patient goals when selecting or combining therapies.
FAQ Section
How quickly does tamsulosin work?
Many patients notice symptom relief within days to a few weeks, though maximal benefit can take longer for some individuals.
Can tamsulosin cause erectile dysfunction?
Tamsulosin is not primarily associated with erectile dysfunction but commonly causes ejaculatory disorders such as reduced or absent ejaculation.
Do I need to stop tamsulosin before cataract surgery?
Inform your ophthalmologist prior to eye surgery because tamsulosin has been linked to intraoperative floppy iris syndrome and surgical teams may adapt technique.
Is it covered by PBS?
PBS coverage varies by formulation and indication; patients should check the current PBS schedule or ask their local pharmacy about subsidy status.
Missed dose / overdose guidance:
Do not double up if a dose is missed; take the next dose as scheduled and seek medical help for severe hypotension or fainting after an overdose.
Guidelines For Proper Use
What should pharmacists and prescribers say when counselling a patient starting tamsulosin?
Use plain, culturally appropriate language and screen for dizziness risk, current antihypertensives and planned cataract surgery.
Advise taking 0.4 mg after the same meal each day and to avoid sudden standing until tolerance is established.
Reinforce that treatment is often long‑term and that follow‑up including PSA, symptom scoring and renal function where indicated is required.
Document counselling in My Health Record where appropriate and report adverse events to the TGA.
For PBS patients, explain co‑payment rules and the option of generic substitution for cost savings.
For rural and remote patients, suggest telehealth follow‑ups and medication delivery or synchronised dispensing to reduce discontinuation.
- Counselling Checklist: Confirm indication, check other antihypertensives, advise meal timing, warn about dizziness and ejaculatory effects, schedule follow‑up.
- Short Script Example: "Take one 0.4 mg capsule after the same meal daily; stand slowly and let us know if you feel faint or have changes to ejaculation."
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Darwin | Northern Territory | 5-7 days |
| Gold Coast | Queensland | 5-9 days |
| Newcastle | New South Wales | 5-9 days |
| Wollongong | New South Wales | 5-9 days |
| Geelong | Victoria | 5-9 days |
| Sunshine Coast | Queensland | 5-9 days |
| Cairns | Queensland | 5-9 days |