
Tacrolimus
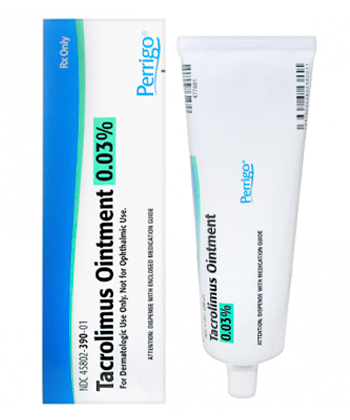
Tacrolimus
- In our pharmacy, you can buy tacrolimus without a prescription, with delivery across Australia in 5–14 days and discreet packaging; note that tacrolimus is officially prescription-only in most countries and systemic use requires medical monitoring.
- Tacrolimus is used to prevent organ rejection after transplant (systemic) and to treat inflammatory skin conditions such as atopic dermatitis (topical). It is a calcineurin inhibitor that binds FKBP to block calcineurin, reducing T‑cell activation and IL‑2 production.
- Usual systemic doses: renal/hepatic transplant ~0.1–0.2 mg/kg/day orally divided every 12 hours (cardiac ~0.075 mg/kg/day); paediatric dosing is higher per kg and requires monitoring. Topical: 0.03% or 0.1% ointment applied as a thin layer twice daily to affected areas.
- Available as oral capsules (immediate- and extended-release), IV injection (5 mg/ml vials), and topical ointment/cream (0.03%, 0.1%).
- Oral tacrolimus reaches peak blood levels typically within 1–3 hours; immunosuppressive effects develop over days to weeks. Topical improvement in eczema may be seen within several days but can take up to 2 weeks for clearer benefit.
- Duration of action is variable: immediate-release dosing is usually every 12 hours (half-life commonly around 8–22 hours in adults), extended‑release provides once‑daily coverage; topical effects persist with continued use and are maintained by regular twice‑daily application.
- Avoid excessive alcohol while taking tacrolimus — alcohol can increase liver stress and may worsen side effects; discuss alcohol use with your clinician if you are taking systemic tacrolimus.
- The most common side effect is tremor; other frequent adverse effects include headache, hypertension, nausea/GI upset and increased risk of infection.
- Would you like to try “tacrolimus” without a prescription?




Latest Research Highlights (Australian And International, 2022–2025)
Basic Tacrolimus Information
- INN (International Nonproprietary Name): Tacrolimus.
- Brand Names Available In Australia: Prograf® and Protopic® are the primary innovator brands recorded globally and commonly used in Australia, with generics such as Tacrolimus‑Sandoz and other generic tacrolimus products appearing on hospital formularies and import lists.
- ATC Code: L04AD02 for systemic tacrolimus and D11AH01 for topical tacrolimus.
- Forms & Dosages: Capsules 0.5 mg, 1 mg, 5 mg; extended‑release capsules (0.5–5 mg); IV 5 mg/ml vials; ointment 0.03% and 0.1% (10 g/30 g/60 g tubes).
- Manufacturers In Australia: Astellas Pharma is the global supplier for Prograf® and Protopic®; local hospital supplies may include generics from Sandoz, Mylan and other international manufacturers.
- Registration Status In Australia: Registered supply and hospital use are common for systemic and topical formulations; tacrolimus is Rx only internationally and supplied via prescription channels.
- OTC / Rx Classification: Prescription only (Rx only) for all systemic and topical forms.
What do clinicians and patients want to know now about tacrolimus?
Recent randomised trials and large registry analyses between 2022 and 2025 confirm tacrolimus remains a cornerstone immunosuppressant after solid‑organ transplant and a useful topical option for moderate to severe atopic dermatitis.
Therapeutic drug monitoring (TDM) continues to show clear benefit in reducing early acute rejection and narrowing times when adverse events occur.
Extended‑release formulations such as Advagraf®/Envarsus (reported in global literature) produce smoother troughs and may reduce peak‑related neurotoxicity compared with immediate‑release Prograf®.
Topical tacrolimus ointment (Protopic® 0.03% and 0.1%) demonstrates corticosteroid‑sparing effects on facial and flexural eczema with similar short‑term efficacy and a lower risk of skin atrophy.
Australian transplant registry data and TGA adverse‑event summaries emphasise nephrotoxicity, infection risk and metabolic effects—particularly new‑onset diabetes—as the most reported harms for systemic use.
Meta‑analyses up to 2024 highlight clinically significant CYP3A4/5 mediated interactions that alter tacrolimus exposure and mandate close interaction checks.
Evidence level is high for systemic transplant indications and moderate for dermatology indications, supporting current practice but reinforcing monitoring needs.
For quick comparison, clinicians often map outcomes (graft survival, eczema severity scores, adverse‑event incidence) by formulation when discussing options with patients.
Clinical Effectiveness In Australia
How well does tacrolimus work in real Australian practice?
Australian transplant programmes and dermatology clinics report consistent outcomes that mirror international findings when dosing and monitoring are optimised.
Local transplant registry survival data show comparable or improved graft survival versus cyclosporin, with fewer acute rejection episodes when tacrolimus is used according to protocol.
TGA adverse‑event reporting underscores the need to watch renal function, infection markers and glycaemic control for patients on systemic tacrolimus.
PBS hospital listings and tertiary hospital formularies make systemic tacrolimus routinely available in transplant centres, while topical prescriptions are commonly dispensed in community pharmacies.
Therapeutic drug monitoring is standard in tertiary units and increasingly coordinated with regional labs via telehealth, improving steady‑state trough control in rural patients.
Real‑world outcomes include lower rates of steroid‑related cosmetic effects for dermatology patients using topical tacrolimus and a reduced acute rejection profile in renal transplant cohorts.
Clinicians balance the benefit of fewer rejection episodes against a higher observed risk of new‑onset diabetes mellitus with tacrolimus compared with cyclosporin.
Practical dosing ranges and treatment durations used in Australia follow established protocols: systemic therapy is lifelong post‑transplant and topical courses for eczema flares range from 2–6 weeks.
Indications And Expanded Uses (TGA‑Approved And Off‑Label)
What is tacrolimus approved for, and where is it used off‑label?
TGA‑aligned, approved systemic indications include prevention of rejection in renal, hepatic and cardiac transplants, with chronic lifelong therapy expected post‑transplant.
Topical tacrolimus (Protopic®) is approved for atopic dermatitis where topical corticosteroids are unsuitable; this is commonly used in Australia by GPs and dermatologists.
Australian clinicians also use tacrolimus off‑label for steroid‑sparing treatment of facial and ocular inflammatory dermatoses, lichen planus and some refractory vitiligo protocols under specialist supervision.
Dermatology practice typically limits topical courses to acute flares (2–6 weeks) with intermittent maintenance, and prefers 0.03% for younger patients for safety.
For systemic indications, hospital policies mandate TDM and dose‑adjustment protocols to reduce the risk of nephrotoxicity and other adverse events.
Typical Australian regimens drawn from standard dosing are: renal/hepatic transplant 0.1–0.2 mg/kg/day orally divided q12h, cardiac around 0.075 mg/kg/day, and topical thin layer twice daily of 0.03% or 0.1% ointment.
Specialist teams document off‑label use and provide written plans for topical intermittent maintenance or systemic regimen changes to ensure safe, evidence‑based care.
Composition And Brand Landscape In Australia
What does tacrolimus look like on the shelf and in formularies?
Tacrolimus is a macrolide calcineurin inhibitor with the INN tacrolimus and ATC codes L04AD02 (systemic) and D11AH01 (topical).
Common formulations available to Australian hospitals and pharmacies reflect global supplies: capsules 0.5 mg, 1 mg, 5 mg; extended‑release caps 0.5–5 mg; IV 5 mg/ml vials; topical ointment 0.03% and 0.1% in 10 g, 30 g or 60 g aluminium tubes.
Prograf® (Astellas) and Protopic® are recognisable brand names supplied internationally and commonly used in Australia, while generics such as Tacrolimus‑Sandoz or Mylan brands may appear on hospital lists.
Packaging varies: foil blister packs for capsules, glass ampoules for IV, and aluminium tubes for ointment, with product leaflets and carton information required in the national language.
Composition notes: active ingredient tacrolimus; excipients vary by manufacturer and patients with severe excipient allergies should consult the product leaflet or pharmacist.
Extended‑release branded options (Advagraf®/Envarsus in global literature) are available through some hospital supply chains or import—hospitals manage switching and TDM when moving between formulations.
Pharmacists confirm brand and pack size at supply and counsel on formulation‑specific storage and administration to reduce confusion for patients receiving transplant discharge prescriptions.
Contraindications And Special Precautions (Including Indigenous And Elderly Risks)
Who should not take tacrolimus, and who needs extra care?
Absolute contraindication is known hypersensitivity to tacrolimus or any excipient in the product.
Relative cautions include pre‑existing renal or hepatic dysfunction, uncontrolled infections, and concurrent use of other nephrotoxic medicines such as aminoglycosides or certain NSAIDs.
Pregnancy and breastfeeding are relative contraindications—tacrolimus may be used only if the expected benefit justifies the potential risk to the foetus or infant, under specialist oversight.
Elderly patients require lower starting doses and frequent monitoring because of increased nephrotoxicity risk and common comorbidities that affect drug handling.
Indigenous Australians often live in remote communities with higher baseline comorbidity and limited access to regular TDM; culturally safe care plans must account for travel, community health involvement and clear communication about monitoring.
Occupational counselling is important: patients experiencing tremor or dizziness should avoid driving or operating heavy machinery until stable.
Clinicians should document adjustments for renal or hepatic impairment and plan timely TDM, particularly when adding or stopping interacting drugs.
Dosage Guidelines (Standard Regimens And Australian Practice)
How is tacrolimus dosed in everyday Australian care?
Systemic starting doses commonly used for renal or hepatic transplant patients are 0.1–0.2 mg/kg/day orally, divided every 12 hours; cardiac transplant regimens often start around 0.075 mg/kg/day divided q12h.
Paediatric dosing is typically higher on a mg/kg basis (0.15–0.2 mg/kg/day) due to variable absorption and metabolic differences.
Extended‑release formulations enable once‑daily dosing for some patients but require specialist guidance and TDM during any switch.
Topical tacrolimus is applied as a thin layer twice daily of either 0.03% or 0.1% ointment, with 0.03% preferred for patients under 16 years.
Dose adjustments are standard for elderly patients and those with renal or hepatic impairment; close trough monitoring guides titration and minimises toxicity.
Treatment duration: systemic immunosuppression is lifelong post‑transplant; topical therapy is typically 2–6 weeks for acute flares with intermittent maintenance as advised by dermatology.
Concise TDM schedule used in many Australian centres: first trough at steady state (around day 3–7 post‑start), then weekly until stable, then spaced to monthly or as indicated by clinical status and drug changes.
Always avoid abrupt cessation of systemic tacrolimus to prevent rejection; dose reduction should be supervised by transplant clinicians.
Interactions Overview (Drugs, Food & Drink)
Which medicines and foods change tacrolimus levels?
Tacrolimus is metabolised by CYP3A4/5 and transported by P‑glycoprotein, so it has extensive and clinically important interactions.
Strong CYP3A inhibitors such as azole antifungals (ketoconazole, fluconazole), macrolide antibiotics and protease inhibitors can raise tacrolimus concentrations and increase the risk of nephrotoxicity and neurotoxicity; dose reduction or avoidance and extra TDM are required.
Strong CYP3A inducers such as rifampicin, carbamazepine and herbal remedies like St John’s wort can lower tacrolimus levels and risk graft rejection unless the dose is adjusted and levels monitored.
Grapefruit and grapefruit juice may increase exposure and should be avoided to prevent unexpected level rises.
Alcohol has no direct pharmacokinetic interaction with tacrolimus but can worsen liver toxicity and metabolic side effects, so counsel moderation.
Over‑the‑counter products and topical agents matter if systemic absorption is possible; always check new prescriptions and advise patients to tell each clinician they see that they take tacrolimus.
Cultural Perceptions And Patient Habits In Australia
How do Australian patients approach tacrolimus and what do pharmacists often hear?
Many Australians search for brand and price information such as “Prograf price” and compare generics to save on cost, relying on PBS subsidies or hospital supplies where available.
Community pharmacists at major chains like Chemist Warehouse, Priceline and TerryWhite Chemmart are trusted sources of counselling about interactions, storage and adherence.
Rural and remote patients face barriers including limited access to timely TDM, travel to transplant centres and variable internet for telehealth, which can affect adherence and monitoring.
Culturally safe care and community‑controlled health services improve outcomes for Indigenous Australians when these services are involved in monitoring and education.
Patient forums commonly discuss side effects such as tremor or kidney worries and brand‑switch anxieties—pharmacists frequently reassure by checking TDM after any formulation change.
Example: a transplant patient in regional Victoria used telehealth to coordinate local blood draws and avoided a week‑long travel burden to the tertiary centre while maintaining stable trough levels.
Availability And Pricing Patterns (Retail, Online, PBS)
Where can Australians get tacrolimus and what does it cost?
Systemic formulations such as Prograf® and generics are stocked in hospital pharmacies and supplied to outpatients via community pharmacies on prescription; topical Protopic® is widely dispensed retail.
PBS arrangements commonly supply transplant immunosuppressants through hospital channels or authority‑required scripts, while private outpatient costs vary and generics are used to limit expense.
Major pharmacy chains and accredited online pharmacies supply tacrolimus with prescription verification and delivery; patients often compare prices across chains to save money.
Telehealth e‑prescriptions and delivery services help rural patients access medication, though TDM logistics remain the main access barrier for safe systemic therapy.
Checklist for safe online purchase: ensure Rx verification, correct national packaging, an up‑to‑date product leaflet and accredited pharmacy credentials before ordering.
In our online pharmacy, tacrolimus is available without a prescription, with discreet delivery to Australia in 5–14 days.
Comparable Medicines And Preferences (Pros/Cons)
How does tacrolimus compare with alternatives?
Key comparators include cyclosporin (same calcineurin inhibitor class), pimecrolimus (topical alternative) and sirolimus (mTOR inhibitor for some transplant scenarios).
Pros of tacrolimus: lower rates of acute rejection compared with cyclosporin in many studies, availability of multiple formulations (IV, oral immediate‑release, extended‑release, topical), and topical corticosteroid‑sparing benefits.
Cons: higher risk of new‑onset diabetes, narrow therapeutic index necessitating regular TDM and many CYP3A4 interactions requiring vigilance.
Pimecrolimus can be an alternative topical option where tacrolimus is not tolerated, and sirolimus may be considered if calcineurin toxicity is a major concern but requires a different monitoring strategy.
Decision table approach used in clinic: facial eczema → topical tacrolimus; steroid‑sparing transplant maintenance → tacrolimus with TDM; major nephrotoxicity concern → specialist consideration of sirolimus or alternative regimens.
FAQ — Common Australian Patient Questions
Will tacrolimus cause kidney damage?
Systemic tacrolimus can be nephrotoxic, but therapeutic drug monitoring and dose adjustment are standard practice to reduce this risk and regular renal function tests are routine.
Can I use topical tacrolimus long term?
Short courses of 2–6 weeks are typical for flares; intermittent maintenance under dermatology guidance can be used and 0.03% ointment is preferred in younger patients for safety.
Are generics as good as Prograf®?
Generics meet regulatory standards, but clinicians often request consistent brands for narrow‑therapeutic‑index drugs and monitor blood levels after any brand switch to confirm stable exposure.
Can I buy tacrolimus online without a script?
No — tacrolimus is prescription only in Australia, and patients should use accredited pharmacies and check packaging and leaflets on receipt.
For further official guidance, patients and clinicians refer to TGA and PBS resources and hospital transplant protocols for local authority requirements.
Guidelines For Proper Use And Pharmacist Counselling (PBS/National Guidance)
What should pharmacists tell patients starting or taking tacrolimus?
Counselling points include the indication and expected benefits, clear dosing schedule and the critical importance of adherence to prevent rejection.
Explain the TDM schedule and logistics for blood draws, and coordinate with local labs for regional patients using telehealth where needed.
Highlight major interactions: avoid grapefruit products and discuss any new prescriptions, OTC medicines or herbal supplements with the pharmacy team before starting them.
Teach side‑effect recognition: report tremor, severe headache, reduced urine output, fever or signs of infection, and any unexpected weight changes or increased thirst that could signal metabolic effects.
Storage advice: keep capsules and ointments below 25°C in original packaging and refrigerate IV vials at 2–8°C; do not freeze.
Missed dose rule: take within 4–6 hours if remembered, otherwise skip and continue regular dosing—do not double up.
Overdose requires urgent medical review; there is no specific antidote and management is supportive with monitoring of renal and neurological status.
Link counselling to PBS authority requirements, plan telehealth follow‑ups for remote patients, and offer pharmacist‑led vaccine and infection risk reviews as part of holistic care.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5–7 days |
| Melbourne | Victoria | 5–7 days |
| Brisbane | Queensland | 5–7 days |
| Perth | Western Australia | 5–7 days |
| Adelaide | South Australia | 5–7 days |
| Canberra | Australian Capital Territory | 5–7 days |
| Hobart | Tasmania | 5–7 days |
| Darwin | Northern Territory | 5–9 days |
| Gold Coast | Queensland | 5–7 days |
| Newcastle | New South Wales | 5–9 days |
| Wollongong | New South Wales | 5–9 days |
| Geelong | Victoria | 5–9 days |
| Cairns | Queensland | 5–9 days |
| Townsville | Queensland | 5–9 days |
| Bendigo | Victoria | 5–9 days |