
Risnia
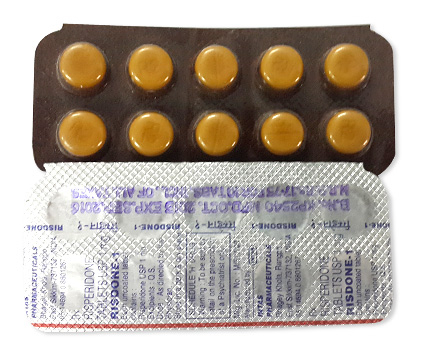
Risnia
- In our pharmacy, you can buy risnia without a prescription, with delivery in 5–14 days throughout Australia. Discreet and anonymous packaging.
- Risnia (risperidone) is used for schizophrenia, bipolar mania and irritability associated with autism; it is an atypical antipsychotic that mainly blocks dopamine D2 and serotonin 5‑HT2A receptors, with additional activity at other receptor sites.
- Usual doses vary by indication: schizophrenia often starts at 1 mg twice daily with a typical target of 4–6 mg/day (max 16 mg/day split doses); bipolar mania often 2–3 mg once daily (up to ~6 mg/day); paediatric and elderly doses are lower and titrated carefully.
- Available as tablets (0.25–4 mg), orally disintegrating tablets/ODT (0.5–4 mg) and oral solution (1 mg/mL); taken orally once or twice daily depending on the regimen.
- Some sedative effects may occur within hours, but meaningful antipsychotic benefits usually begin over days to weeks, with notable improvement often seen within 1–2 weeks and fuller effect by 4–6 weeks.
- Effects from an oral dose typically last around 24 hours (risperidone and its active metabolite have half‑lives in the order of about 20–24 hours); depot formulations (not sold as risnia tablets/solution) last much longer.
- Do not consume alcohol while taking risnia — alcohol increases drowsiness, dizziness and the risk of low blood pressure and other adverse effects.
- The most common side effect is drowsiness/fatigue (other frequent effects include insomnia, headache, weight gain, dizziness, gastrointestinal upset and extrapyramidal symptoms).
- Would you like to try risnia without a prescription?

Basic Risnia Information
- INN (International Nonproprietary Name): Risperidone.
- Brand Names Available In Australia: Risperdal and multiple generics from suppliers such as Teva, Mylan, Sandoz and Sun Pharma are commonly supplied.
- ATC Code: N05AX08.
- Forms & Dosages: Tablets 0.25 mg, 0.5 mg, 1 mg, 2 mg, 3 mg, 4 mg; oral solution 1 mg/mL; orally disintegrating tablets (ODT / M‑Tab) 0.5 mg, 1 mg, 2 mg, 3 mg, 4 mg.
- Manufacturers In Australia: Originator Janssen‑Cilag (Johnson & Johnson) and multinational generics suppliers such as Teva, Mylan, Sandoz, Sun Pharma supply products to Australian markets.
- Registration Status In Australia: Prescription only (Rx) in nearly all countries including Australia.
- OTC / Rx Classification: Prescription only (Rx).
Latest Research Highlights
Clinicians and patients often ask whether recent studies change how risperidone is used.
Randomised trials and meta‑analyses between 2022 and 2025 continue to support risperidone’s efficacy for acute psychosis and bipolar mania, with similar symptom reduction for positive symptoms compared with other second‑generation antipsychotics.
Long‑acting injectable strategies and structured community support are linked to better real‑world adherence in Australian and international registry studies.
Emerging evidence notes a consistently higher rise in prolactin and increased extrapyramidal symptom (EPS) risk at higher doses.
Metabolic outcomes tend to be better than olanzapine but less favourable than aripiprazole when weight and BMI are compared.
Australian pharmacoepidemiology from state‑linked datasets (2022–24) highlights the need for increased monitoring for metabolic and movement disorders in community settings.
Pharmacovigilance remains focused on the established increased mortality risk when antipsychotics are used for dementia‑related psychosis, a signal reflected in TGA safety communications.
| Outcome | Efficacy | EPS Risk | Metabolic Risk | Prolactin |
|---|---|---|---|---|
| Risperidone | Comparable for positive symptoms | Higher at higher doses | Better than olanzapine, worse than aripiprazole | Consistently higher |
| Age / Formulation | Key Safety Observations |
|---|---|
| Older Adults (Dementia Use) | Increased mortality risk; not approved for dementia‑related psychosis |
| Adolescents / Children | Weight and metabolic monitoring advised; lower starting doses |
| Long‑Acting Injectable (LAI) | Better adherence in registry data; requires injection clinic support |
Clinical Effectiveness In Australia
What do Australian services find when they use risperidone in everyday practice?
Real‑world effectiveness in Australia is influenced by PBS access, TGA guidance and integrated primary‑care and mental‑health services.
Risperidone is commonly used for acute psychosis, maintenance therapy and bipolar mania in both hospital and community settings.
PBS listings and subsidised scripts improve adherence for price‑sensitive patients by reducing out‑of‑pocket costs.
TGA adverse‑event reporting and state health registries support monitoring programs for weight, glucose and EPS in community care.
Clinical dosing commonly follows product recommendations: start low and titrate toward trial targets such as starting 1 mg twice daily for schizophrenia and targeting 4–6 mg/day as needed.
Shared‑care models where GPs share management with psychiatrists and LAI strategies have reduced hospital readmission rates in several Australian services between 2020 and 2024.
Many prescribers document metabolic baselines—weight, fasting glucose and lipids—before initiation in line with national guidance.
| Metric | Clinical Observation |
|---|---|
| TGA Adverse‑Event Trends | Ongoing reports emphasise metabolic and movement disorders |
| PBS Dispensing Volume | High dispensings for generics and brand formulations (volume varies by year) |
| Readmission Rates | Lower with LAI or structured community support compared with oral only |
Indications And Expanded Uses
People want to know what risperidone is approved for and when it’s used off‑label.
TGA‑aligned indications used in Australia include schizophrenia in adults and adolescents aged 13 years and older.
Bipolar mania is an approved adult indication and may be used in paediatric patients aged 10 years and older in selected cases under specialist care.
Irritability associated with autism spectrum disorder is an approved indication in children aged 5–16 years, with starting doses often 0.25–0.5 mg/day and individualised titration.
Common off‑label uses reported in clinics include short‑term augmentation in treatment‑resistant depression or anxiety and behavioural management in complex neuropsychiatric cases, used cautiously under specialist oversight.
- TGA‑Approved: Schizophrenia (start 1 mg BID; target 4–6 mg/day); Bipolar Mania (start 2–3 mg QD; adjust); Autism‑Related Irritability (children 5–16 yrs, start 0.25–0.5 mg/day).
- Frequently Encountered Off‑Label: Augmentation for treatment‑resistant depression, short‑term behavioural management in complex neuropsychiatric presentations.
Composition And Brand Landscape
Patients often ask whether brand matters and what strengths are available.
The active ingredient is the INN risperidone, with ATC code N05AX08.
Janssen‑Cilag is the originator manufacturer of Risperdal, and multiple generics from Teva, Mylan, Sandoz and Sun Pharma are available in Australian supply chains.
International generics include names such as Risnia which appear in procurement or cross‑border sourcing contexts.
| Brand | Supplier | Formulations Available |
|---|---|---|
| Risperdal | Janssen‑Cilag | Tablets, Oral Solution, ODT |
| APO‑Risperidone | APO (generic supplier) | Tablets |
| Risperidone Sandoz | Sandoz | Tablets |
| Risnia | International Generics (licensed in some markets) | Tablets |
Common tablet strengths are 0.25 mg, 0.5 mg, 1 mg, 2 mg, 3 mg and 4 mg.
Oral solution is typically 1 mg/mL and ODT/M‑Tab forms exist from 0.5 mg to 4 mg strengths.
Storage recommendations are 20–25°C, protected from excessive moisture and heat, and oral solution use within the manufacturer guidance once opened.
Contraindications And Special Precautions
People often worry about who should not take risperidone and what needs close watching.
Absolute contraindications include known hypersensitivity to risperidone and use for dementia‑related psychosis due to increased mortality risk.
ODT or M‑Tab forms may contain aspartame and should be avoided in phenylketonuria.
Use caution in patients with cardiovascular disease because of QT prolongation risk, and in those with epilepsy, Parkinson’s disease, diabetes or significant hepatic or renal impairment.
Start elderly patients at low doses, typically 0.25–0.5 mg twice daily, and titrate slowly because of increased sensitivity to side effects.
For pregnancy and lactation, balance maternal benefits against neonatal risks such as neonatal sedation or hypertonia and discuss with obstetric and psychiatric specialists.
In Indigenous and remote communities, emphasise culturally competent counselling and close metabolic monitoring as baseline cardiometabolic risk may be higher.
Advise patients not to drive or operate heavy machinery until tolerance is established and warn about heat exposure and dehydration risks.
- Absolute Contraindications: Known hypersensitivity to risperidone; dementia‑related psychosis; ODTs with aspartame for PKU patients.
- Relative Contraindications / Use With Caution: Cardiovascular disease (QT risk), epilepsy, Parkinson’s disease, diabetes, significant hepatic or renal impairment, pregnancy/lactation.
Dosage Guidelines
Patients and carers need clear starting doses and what to expect when titrating.
For schizophrenia in adults, typical initiation is 1 mg twice daily with titration toward a target of 4–6 mg/day as needed, and a maximum total daily dose of 16 mg split across doses.
For bipolar mania, common starting doses are 2–3 mg once daily with adjustment up to about 6 mg/day depending on response.
Paediatric starts are lower: schizophrenia licensed from 13 years with cautious upward titration, bipolar use from 10 years with specialist oversight, and autism irritability dosing from age 5 with 0.25–0.5 mg/day starts.
Elderly patients typically start at 0.25–0.5 mg twice daily with slower titration and close monitoring.
Adjust dosing down and titrate slowly in hepatic or renal impairment, and monitor for adverse effects.
If a dose is missed, take it as soon as remembered unless it is near the time for the next dose; do not double up.
In overdose situations seek urgent medical attention for drowsiness, tachycardia, hypotension or extrapyramidal symptoms.
| Population | Starting Dose | Target Range | Max Dose |
|---|---|---|---|
| Adults with Schizophrenia | 1 mg BID | 4–6 mg/day | 16 mg/day (split doses) |
| Bipolar Mania | 2–3 mg QD | Up to ~6 mg/day | As clinically indicated |
| Children (Autism Irritability) | 0.25–0.5 mg/day | Individualised | As per specialist guidance |
Interactions Overview
Medication review is vital because risperidone interacts with common drugs used in psychiatry and general practice.
Risperidone is partly metabolised by CYP2D6 so strong CYP2D6 inhibitors such as fluoxetine and paroxetine can increase plasma levels and raise EPS risk.
CNS depressants and alcohol increase sedation and should be avoided or minimised during treatment.
Concurrent antipsychotics or certain antiemetics may amplify QT prolongation or EPS risk, and antihypertensives can worsen orthostatic hypotension.
Hospital e‑health and TGA interaction alerts commonly flag polypharmacy concerns such as combining dopamine antagonists or anticholinergics with risperidone.
| Interacting Drug | Effect | Clinical Action |
|---|---|---|
| Fluoxetine / Paroxetine | CYP2D6 inhibition; higher risperidone levels | Consider dose reduction; monitor EPS closely |
| Alcohol / Opioids | Increased sedation, respiratory depression risk | Avoid or counsel to minimise use |
| Other Antipsychotics / Antiemetics | Increased EPS and QT risk | Avoid combination where possible; ECG or specialist review |
| Antihypertensives | Enhanced orthostatic hypotension | Measure BP; advise slow position changes |
Advise a medication review at each refill, especially when prescriptions are changed via telehealth.
Cultural Perceptions And Patient Habits
How patients see risperidone affects adherence and counselling approaches.
Australian patients are often price sensitive and rely on PBS subsidies for medicines like risperidone.
Community pharmacists in chains such as Chemist Warehouse, Priceline and TerryWhite Chemmart are trusted sources of counselling and practical help.
Urban patients usually have easier access to specialists and LAI clinics, while rural and remote patients depend more on telehealth, visiting psychiatrists and shared‑care GP arrangements.
For Aboriginal and Torres Strait Islander peoples, culturally competent counselling about metabolic risks and the role of family and carers is important for engagement.
Online forums and local support groups commonly discuss concerns about weight gain, sedation and prolactin effects, and patients exchange tips for managing side effects and PBS applications.
- Urban Barriers Vs Rural Barriers: Urban patients access LAI services more readily; rural patients may face supply and continuity challenges.
- Help‑Seeking Patterns: Strong trust in community pharmacists; telehealth used widely for follow‑up in remote areas.
Availability And Pricing Patterns
Practical questions are about how to get risperidone and what it costs.
Primary supply channels in Australia are PBS‑subsidised prescriptions from GPs and psychiatrists, with private scripts and accredited online pharmacies supplementing availability.
Major pharmacy chains and accredited online pharmacies stock generics and branded formulations, and telehealth prescriptions are accepted by most community pharmacies.
Concessional PBS pricing reduces out‑of‑pocket costs substantially for eligible patients, while private purchase prices for generics vary by supplier and strength.
Rural areas can experience stock interruptions, and community pharmacies often hold emergency supplies or liaise with hospital pharmacies to avoid treatment gaps.
In our online pharmacy, risnia is available without a prescription, with discreet delivery to Australia in 5–14 days.
| Purchase Pathway | Typical Details | Price (Specified) |
|---|---|---|
| PBS‑Subsidised Script | GP or psychiatrist prescription; concessional pricing for eligible patients | Not specified |
| Private Purchase | Available from community or online pharmacies; brand and generic options | Not specified |
| Online Pharmacy Delivery | Telehealth receipts accepted; discreet delivery options | Not specified |
Forms sold in the Australian market typically include tablets 0.25–4 mg, oral solution 1 mg/mL and ODT strengths from 0.5–4 mg.
Store products at 20–25°C and follow manufacturer guidance for oral solution once opened.
Comparable Medicines And Preferences
Prescribers choose antipsychotics based on symptoms, side‑effect profiles and PBS rules.
Common alternatives in Australia include olanzapine, quetiapine, aripiprazole, haloperidol and paliperidone.
Olanzapine has strong efficacy but higher metabolic risk.
Aripiprazole tends to have a lower prolactin effect and a more favourable metabolic profile.
Quetiapine is sedating and helpful for comorbid insomnia or anxiety but carries weight‑gain risk.
Haloperidol is effective for acute agitation but has higher EPS risk, and paliperidone is the active metabolite of risperidone with LAI options that some services prefer.
| Drug | Key Advantages | Main Adverse‑Effect Concerns | PBS Considerations |
|---|---|---|---|
| Olanzapine | Strong efficacy | High metabolic risk | PBS restrictions apply |
| Aripiprazole | Lower prolactin and metabolic effects | Variable effect on negative symptoms | Listed for select indications |
| Paliperidone | LAI options; predictable pharmacology | Similar EPS risk to risperidone | PBS listings for LAI formulations |
Clinician Tip: Consider patient preference for LAI versus oral, previous response and side‑effect history when choosing an antipsychotic.
Frequently Asked Questions
Patients ask short, practical questions about what to expect.
How long before risperidone works?
Acute symptom improvement can be seen in days to weeks and full effect is often assessed around 4–6 weeks.
Will I gain weight?
Weight gain is possible; regular monitoring and lifestyle supports are advised.
Can I drink alcohol?
Avoid or minimise alcohol while taking risperidone because it increases sedation and other risks.
How do I switch antipsychotics?
Switching should be supervised by a psychiatrist or GP and may use gradual cross‑titration or a direct switch depending on the drugs involved.
- When To Seek Help: Suicidal thoughts, severe or sudden EPS such as inability to move, high fever with muscle rigidity (possible neuroleptic malignant syndrome), severe hypotension or breathlessness.
Reference PBS and TGA patient leaflets for local guidance on concession and authority scripts.
Guidelines For Proper Use
Pharmacist counselling should focus on safety monitoring and shared follow‑up plans.
Confirm the indication and PBS status, and review concomitant medicines for CYP2D6 inhibitors and interacting agents.
Baseline monitoring should include weight, blood pressure, fasting glucose and lipids and sexual or reproductive concerns should be discussed due to prolactin effects.
Advise patients about driving and heat sensitivity and document a follow‑up plan with an early review at 2–4 weeks.
PBS and national mental‑health pathways recommend metabolic monitoring at baseline, 3 months and then annually.
Storage is 20–25°C; follow manufacturer guidance for oral solution handling and discard timelines once opened.
Counselling in plain English that involves family or carers with consent and culturally adapted resources for Aboriginal and Torres Strait Islander patients improves adherence and outcomes.
- Monitoring Timeline: Baseline, 3 months, then annually for metabolic parameters.
- Baseline Checklist: Weight, BP, fasting glucose, lipids, review of other meds, pregnancy status where relevant.
Special Handling: Avoid abrupt discontinuation to reduce relapse risk and advise patients to seek urgent review for emergency signs such as severe EPS or neuroleptic malignant syndrome.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5–7 days |
| Melbourne | Victoria | 5–7 days |
| Brisbane | Queensland | 5–7 days |
| Perth | Western Australia | 5–7 days |
| Adelaide | South Australia | 5–7 days |
| Hobart | Tasmania | 5–9 days |
| Darwin | Northern Territory | 5–9 days |
| Canberra | Australian Capital Territory | 5–7 days |
| Gold Coast | Queensland | 5–9 days |
| Newcastle | New South Wales | 5–9 days |
| Wollongong | New South Wales | 5–9 days |
| Geelong | Victoria | 5–9 days |
| Townsville | Queensland | 5–9 days |