
Nupentin
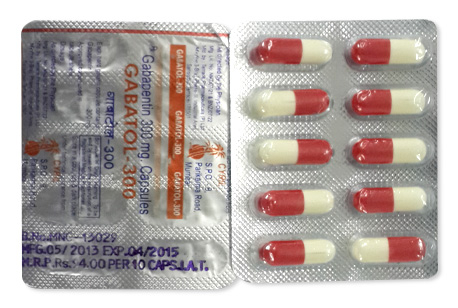
Nupentin
- In our pharmacy, you can buy nupentin without a prescription, with delivery in 5–14 days throughout Australia. Discreet and anonymous packaging.
- Nupentin (gabapentin) is used for partial seizures (epilepsy), neuropathic pain including postherpetic neuralgia and diabetic neuropathy, and in some extended‑release formulations for restless legs syndrome; it works by binding to the α2δ subunit of voltage‑gated calcium channels in the central nervous system to reduce excitatory neurotransmitter release.
- Usual adult doses: for epilepsy usually start 300 mg on day 1 and titrate to 900–1,800 mg/day divided into three doses (some patients up to 2,400–3,600 mg/day for neuropathic pain); neuropathic pain often titrated from 300 mg to 1,800–3,600 mg/day in divided doses; restless legs syndrome (extended‑release brands) commonly 600 mg once daily. Dosing must be reduced in renal impairment; paediatric dosing differs by weight.
- Administered orally as capsules (100 mg, 300 mg, 400 mg), tablets (600 mg, 800 mg), oral solution (250 mg/5 mL) and extended‑release tablets (brand dependent).
- Onset of effect is typically within 1–3 hours after an oral dose (peak plasma levels around 2–3 hours).
- Duration of action for immediate‑release nupentin is roughly 6–8 hours (elimination half‑life about 5–7 hours), while extended‑release formulations provide once‑daily coverage as per the specific product.
- Avoid alcohol — it increases dizziness and drowsiness and can worsen breathing problems, especially if combined with opioids or other central nervous system depressants.
- The most common side effect is dizziness.
- Would you like to try nupentin without a prescription?
Basic Nupentin Information
- INN (International Nonproprietary Name): Gabapentin
- Brand Names Available In Australia: Neurontin and multiple generics from manufacturers such as Teva, Sandoz and Mylan/Viatris (local brand availability varies)
- ATC Code: N03AX12
- Forms & Dosages: Capsules 100 mg, 300 mg, 400 mg; Tablets 600 mg, 800 mg; Oral solution 250 mg/5 mL; Extended‑release tablets available in some markets
- Manufacturers In Australia: not specified
- Registration Status In Australia: Registered with TGA under standard indications for partial (focal) seizures and neuropathic pain; prescription‑only
- OTC / Rx Classification: Prescription‑only (Rx)
- Indications & Standard Dosages: Epilepsy (partial seizures) — titrate to 900–1800 mg/day in three divided doses; Neuropathic pain (PHN, diabetic neuropathy) — titrate to 1800–3600 mg/day in divided doses; Restless legs (extended‑release products in other markets)
- Dosage Adjustments: Children ≥3 years: start 10–15 mg/kg/day; elderly and renal impairment require adjustment; gabapentin is renally excreted
- Missed Dose Instructions: Take when remembered unless close to next dose; do not double dose; extended‑release products have specific guidance
- Overdose: Drowsiness, slurred speech, lethargy, diarrhoea; severe cases may cause respiratory depression particularly with CNS depressants; haemodialysis may be considered in severe overdose with renal impairment
- Storage & Transport Guidelines: Store at 20–25°C; protect from moisture and excessive heat; check solution bottle labelling for refrigeration guidance
- Absolute Contraindications: Known hypersensitivity to gabapentin or excipients
- Relative Contraindications / Warnings: Renal insufficiency, concomitant opioids or other CNS depressants, history of mood disorders, pregnancy and lactation — use only if benefit justifies risk
- Common Side Effects: Very common — dizziness and somnolence; common — fatigue, peripheral oedema, ataxia, weight gain, nausea
- Competitors / Similar Products: Pregabalin (Lyrica), carbamazepine, lamotrigine, topiramate, duloxetine, amitriptyline
Latest Research Highlights
Patients ask whether gabapentin still works for nerve pain and what recent studies show.
Recent pooled analyses and randomised trials continue to show a therapeutic signal for gabapentin in established neuropathic pain states such as postherpetic neuralgia and some diabetic neuropathies.
The effect sizes versus placebo are generally moderate in these indications, with many meta‑analyses reporting consistent, clinically meaningful reductions in neuropathic pain scores.
Evidence for off‑label uses such as fibromyalgia, chronic low‑back pain and some anxiety presentations remains smaller or inconsistent, with lower quality data and mixed trial results.
Safety research continues to highlight central nervous system adverse events including dizziness and somnolence as very common side effects.
Pharmacovigilance signals emphasise greater respiratory depression risk when gabapentin is combined with opioids or other sedatives, and accumulation in renal impairment.
Australian data streams such as TGA adverse‑event reports and PBS dispensing statistics echo international findings and underline rising community prescribing and closer monitoring needs in older adults and people on multiple medicines.
Outcomes table (compact):
- PHN / Diabetic Neuropathy: Moderate efficacy vs placebo.
- Fibromyalgia / Low‑Back Pain: Inconsistent / small benefits.
- Epilepsy (adjunct): Established efficacy for partial seizures.
Safety observations table (compact):
- CNS Effects: Dizziness, somnolence — very common.
- Respiratory: Augmented risk with opioids/CNS depressants.
- Renal: Dose accumulation; require dose reduction.
Clinical Effectiveness In Australia
Clinicians and patients often want to know how gabapentin performs in everyday Australian practice.
In Australia gabapentin is used mainly for partial (focal) seizures and neuropathic pain in line with TGA approvals and international guidance.
PBS and TGA data collections describe real‑world symptom reductions in postherpetic neuralgia and diabetic neuropathy cohorts, though individual response varies and many patients require careful dose titration to reach benefit.
Effectiveness is moderated by adherence, renal function and concurrent central nervous system medicines because gabapentin is renally excreted and commonly causes dizziness and somnolence.
TGA adverse‑event monitoring mirrors international concerns with sedation and dizzy spells, and rare reports of respiratory depression when gabapentin is combined with opioids or other sedatives.
For epilepsy gabapentin is commonly used as an adjunctive or alternative option for partial seizures with divided dosing schedules.
Discontinuation should be gradual to reduce seizure recurrence risk; dosing ranges commonly used are 900–1800 mg/day for epilepsy and up to 1800–3600 mg/day for neuropathic pain.
Short outcomes table for clinicians:
- PBS‑coded Indication | Typical Effect Size | NNT Range — PHN/diabetic neuropathy | Moderate | Variable across trials.
Indications And Expanded Uses
Patients often ask what gabapentin is officially for, and what it’s used for off‑label.
TGA‑aligned indications for gabapentin reflect international approvals: partial‑onset (focal) seizures and neuropathic pain including postherpetic neuralgia and diabetic neuropathy.
Extended‑release formulations such as Gralise and Horizant are licensed in other markets for conditions like postherpetic neuralgia or restless legs syndrome, but those specific listings may not match TGA registrations in Australia.
Off‑label prescribing in Australia occurs for fibromyalgia, chronic low‑back pain and certain anxiety presentations, but trial evidence for these uses is generally low‑to‑moderate and inconsistent.
Paediatric use is established for epilepsy in specified age ranges with weight‑based dosing starting from 10–15 mg/kg/day.
Prescribers should document off‑label rationale and monitor outcomes closely when using gabapentin outside its approved indications.
Definition list:
- Approved (TGA) Uses: Partial seizures; neuropathic pain (PHN, diabetic neuropathy).
- Common Off‑Label Uses: Fibromyalgia, chronic low‑back pain, some anxiety disorders, certain pain syndromes.
- Evidence Strength: High for epilepsy (adjunct); Moderate for PHN/diabetic neuropathy; Low/Variable for many off‑label uses.
Composition And Brand Landscape
People searching for Neurontin or gabapentin capsules want to know what’s available and how brands differ.
The active substance is gabapentin (INN) and the ATC classification is N03AX12, placing it among other antiepileptics not fitting classic chemical groups.
Neurontin is the originator brand historically supplied by Pfizer, with multiple generics manufactured by firms such as Teva, Sandoz and Mylan/Viatris dominating supply after patent expiry.
Common Australian pharmacy presentations reflect global norms: capsules 100 mg, 300 mg and 400 mg; tablets 600 mg and 800 mg; and oral solution 250 mg/5 mL in measured bottles.
Extended‑release products exist but their availability and registration vary by region and brand name.
Packaging is typically blister packs of 10, 30 or 90 items, or bottles for solution presentations.
Brand/generic checklist for prescribers and e‑commerce pages:
- Cost: Generics generally cheaper post‑patent.
- PBS Availability: Check PBS listings for subsidy before assuming patient cost.
- Tolerability: Side‑effect profile driven by dose rather than brand in most cases.
Contraindications And Special Precautions
Patients commonly worry about who should not take gabapentin and when extra care is needed.
Absolute contraindication is a known hypersensitivity to gabapentin or any formulation excipients.
Key precautions include renal impairment because gabapentin is renally excreted and will accumulate unless doses are reduced per product information.
Concurrent opioid or other CNS‑depressant therapy raises the risk of respiratory depression and requires extra monitoring and counselling.
Elderly patients have greater susceptibility to sedation, dizziness and falls and may require lower starting doses and closer follow‑up.
Patients with a history of mood disorders or suicidal ideation should be monitored for behavioural changes while on gabapentin.
Pregnancy and lactation are relative precautions: use only if the expected benefit outweighs the potential risk.
Special attention is needed for Indigenous and remote communities where comorbid renal disease and polypharmacy are more common; culturally appropriate counselling and renal checks are essential.
- Checklist For Prescribers/Pharmacists: Verify hypersensitivity, check renal function, review opioid/CNS depressant co‑medications, advise occupational precautions (driving/machinery), document off‑label use if applicable.
Dosage Guidelines
Patients frequently ask how to start gabapentin and how fast to increase the dose.
Standard adult epilepsy initiation commonly follows a brief titration: 300 mg on day one, 300 mg twice daily on day two and 300 mg three times daily on day three, then titrate to maintenance of 900–1800 mg/day in three divided doses.
For neuropathic pain a typical approach is to start at 300 mg daily then increase by about 300 mg every 1–3 days as tolerated to reach effect, with common maintenance ranges of 1800–3600 mg/day split across doses.
Children aged three years and older use weight‑based dosing for epilepsy: start 10–15 mg/kg/day divided into three doses and titrate to maintenance of up to approximately 40 mg/kg/day.
Renal impairment requires proportional dose reduction based on creatinine clearance — consult the product prescribing information for a renal dosing table.
Extended‑release dosing differs by brand and indication; check the brand’s specific instructions for schedules and missed‑dose rules.
- Dosing Table (condensed): Epilepsy start 300 mg → maintenance 900–1800 mg/day; Neuropathic pain start 300 mg → maintenance 1800–3600 mg/day; adjust for renal function and paediatric weight‑based dosing.
Interactions Overview
People want to know which medicines to avoid with gabapentin and which combinations need extra caution.
Most clinically important interactions are pharmacodynamic rather than metabolic: additive central nervous system depression with opioids, benzodiazepines, alcohol and some antipsychotics can increase sedation and the risk of respiratory depression.
Antacids containing aluminium or magnesium can reduce gabapentin absorption if taken at the same time, so separate dosing by at least two hours when practical.
Gabapentin undergoes minimal hepatic metabolism and produces few CYP‑mediated interactions, but polypharmacy in multimorbid patients still raises the likelihood of clinically important combinations.
TGA and international pharmacovigilance reports particularly flag serious respiratory events when gabapentin is combined with opioid therapy or given to patients with existing respiratory compromise.
Dispensing and prescribing systems should include EMR alerts for opioid co‑prescription and a concise interaction checklist at the point of supply.
- Quick Interaction Table: Opioids — increased respiratory depression risk (action: avoid or reduce dose and monitor); Antacids — reduce absorption (action: separate by 2 hours); Alcohol/benzodiazepines — increased sedation (action: counsel and avoid where possible).
Cultural Perceptions And Patient Habits
Patients often compare prices and ask community pharmacists for practical advice on switching brands or managing side effects.
Australian consumers are cost‑conscious and frequently check PBS subsidy status and private prices via major retailers and online pharmacies when searching for Neurontin or gabapentin capsules.
Online forums and local GP clinics discuss gabapentin both for nerve pain and off‑label uses; common patient‑reported concerns are sedation, dizziness and weight change.
Rural and remote patients may face longer waits for renal testing and specialist review, and often rely on telehealth and community pharmacies for repeat prescriptions and medication counselling.
Indigenous communities require culturally safe counselling and greater attention to comorbid renal disease and polypharmacy when gabapentin is considered.
Community pharmacists are highly trusted and play a key role in advising patients about generic substitution, side‑effect management and safe use of gabapentin with other medicines.
- Access Notes: Urban patients typically have quick pharmacy access; rural patients rely more on mail order or telehealth for repeat supplies.
Availability And Pricing Patterns
People need clear guidance about where to buy gabapentin and what it might cost in Australia.
Gabapentin generics are widely available across Australian community pharmacies including major chains and independent stores, and online pharmacies supply repeats and new prescriptions under e‑prescription rules.
PBS subsidy status materially affects out‑of‑pocket cost, so clinicians and patients should check the current PBS schedule and any authority requirements before assuming coverage.
Common pack sizes follow global norms — blister packs of 10, 30 or 90 capsules/tablets and solution bottles around 450–473 mL for oral suspension.
Generics predominate post‑patent expiry, but consumers still search for brand names such as Neurontin online when price or perceived tolerability is a concern.
For convenience, many urban patients use click‑and‑collect or mail order services, while rural patients commonly rely on regional dispensing and longer delivery windows.
In our online pharmacy, nupentin is available without a prescription, with discreet delivery to Australia in 5‑14 days.
Comparable Medicines And Preferences
Patients and prescribers often ask whether pregabalin or another medicine is preferable to gabapentin.
Alternatives for neuropathic pain and seizure management in Australia include pregabalin, tricyclic antidepressants such as amitriptyline, SNRIs like duloxetine, and antiepileptics such as carbamazepine, lamotrigine and topiramate.
Pregabalin is structurally related and offers more predictable bioavailability and sometimes faster titration, but it can be costlier and has a similar side‑effect profile including dizziness and somnolence.
Tricyclics and SNRIs are effective for many neuropathic pain syndromes but bring anticholinergic effects, cardiovascular considerations and different contraindications compared with gabapentin.
Choice of agent depends on indication, comorbidities, renal function, interaction potential and PBS subsidy status for the patient.
- Decision Matrix (condensed): Indication → First‑Line Options → Considerations — Neuropathic pain → Gabapentin/pregabalin/amitriptyline/duloxetine → Check renal function, sedation risk, PBS coverage.
Frequently Asked Questions
Q: Is gabapentin covered by the PBS?
A: Coverage depends on the indication, formulation and pack size; check the PBS schedule and any authority requirements for subsidy eligibility.
Q: Can I drive while taking gabapentin?
A: Avoid driving or operating heavy machinery until you know how gabapentin affects you because dizziness and somnolence are very common.
Q: What should I do if I miss a dose?
A: Take the missed dose as soon as you remember unless it is close to the next dose; do not double up; follow brand‑specific guidance for extended‑release products.
Q: Is gabapentin addictive?
A: Gabapentin is not classified as a classical dependence medicine, but misuse and diversion have been reported internationally; monitor for drug‑seeking behaviour and escalating doses, particularly when combined with opioids.
Q: What are signs of overdose?
A: Drowsiness, slurred speech and lethargy are common overdose features; severe cases can involve respiratory depression, particularly with CNS depressants — seek urgent care if suspected.
Guidelines For Proper Use
Pharmacists and prescribers want a practical checklist to ensure safe initiation and supply of gabapentin.
Confirm the indication and that the intended use aligns with TGA‑approved indications or that off‑label rationale is documented and monitored.
Review renal function and adjust dosing per the product prescribing information, especially in older patients and those with chronic kidney disease.
Counsel patients about common adverse effects — dizziness, somnolence, peripheral oedema and possible weight change — and advise not to stop abruptly to avoid seizure recurrence.
Warn about additive sedation with alcohol, opioids and benzodiazepines and recommend avoiding these combinations when possible.
Use a dispensing checklist: check medicines list for opioids/CNS depressants, recommend baseline renal testing if indicated, discuss PBS subsidy options and provide a medication‑use leaflet with storage advice (store at 20–25°C).
Provide a short counselling script at supply and schedule follow‑up for dose optimisation and side‑effect review.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5–7 days |
| Melbourne | Victoria | 5–7 days |
| Brisbane | Queensland | 5–7 days |
| Perth | Western Australia | 5–7 days |
| Adelaide | South Australia | 5–7 days |
| Canberra | Australian Capital Territory | 5–7 days |
| Hobart | Tasmania | 5–7 days |
| Darwin | Northern Territory | 5–7 days |
| Newcastle | New South Wales | 5–7 days |
| Wollongong | New South Wales | 5–9 days |
| Geelong | Victoria | 5–9 days |
| Cairns | Queensland | 5–9 days |
| Townsville | Queensland | 5–9 days |