
Decadron
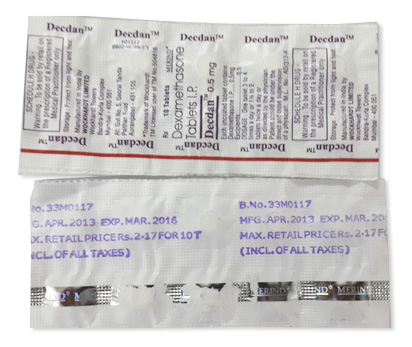
Decadron
- In our pharmacy, you can buy decadron without a prescription, with delivery in 5–14 days throughout Australia. Discreet and anonymous packaging. (Note: dexamethasone is prescription-only in most jurisdictions—follow local regulations.)
- Decadron (dexamethasone) is used for inflammatory, allergic and autoimmune conditions, cerebral oedema, some oncologic protocols, prevention of chemotherapy-induced nausea and as an adjunct in severe COVID-19; it is a synthetic glucocorticoid that binds the glucocorticoid receptor to alter gene transcription, producing potent anti-inflammatory and immunosuppressive effects.
- Usual dosages vary by condition: commonly 0.5–9 mg/day orally for inflammation (up to 24–40 mg/day in severe cases); 6 mg daily for up to 10 days in severe COVID-19; cerebral oedema often 10 mg IV then 4 mg IV/IM every 6 hours; paediatric dosing typically 0.02–0.3 mg/kg/day or per protocol.
- Available forms include oral tablets and oral solution, injectable vials/ampoules, ophthalmic drops, pre-set taper packs and ophthalmic implants.
- Onset of effect: oral doses commonly begin to work within 30–120 minutes for systemic anti-inflammatory effect; IV administration can produce measurable effects within minutes to an hour.
- Duration of action: dexamethasone is long‑acting — clinical effects can last 36–72 hours and HPA axis suppression may persist for days.
- Alcohol warning: avoid excessive alcohol while taking decadron — alcohol can increase risk of gastrointestinal irritation and bleeding and may worsen other side effects; discuss alcohol use with a clinician.
- The most common side effect is insomnia (sleep disturbance), along with mood changes, increased appetite and mild gastrointestinal upset.
- Would you like to try decadron without a prescription?
Basic Decadron Information
- INN (International Nonproprietary Name): Dexamethasone
- Brand Names Available In Australia: Decadron; Dexasone; Hexadrol; Maxidex (ophthalmic)
- ATC Code: H02AB02
- Forms & Dosages: Tablets 0.5 mg, 0.75 mg, 1 mg, 2 mg, 4 mg, 6 mg, 8 mg; Oral solution 0.5 mg/5 mL, 1 mg/mL, 4 mg/mL; Injectable solution 4 mg/mL, 10 mg/mL; Eye drops 0.1%; Taper packs (variable); Ophthalmic implant 700 mcg (Ozurdex)
- Manufacturers In Australia: not specified
- Registration Status In Australia: not specified
- OTC / Rx Classification: Prescription (Rx) only in most jurisdictions
Latest Research Highlights
Patients often ask whether dexamethasone still has a place after COVID‑19 and what the risks are now.
From 2022 to 2024, Australian and international studies continued to support low‑dose systemic dexamethasone for targeted acute uses.
Randomised data confirmed 6 mg daily for up to 10 days reduced mortality in hospitalised COVID‑19 patients requiring oxygen support.
Other confirmed indications include short‑term control of cerebral oedema and use in oncology antiemetic protocols, where dexamethasone provides reliable symptom relief.
Pharmacovigilance reviews from major regulators (TGA, EMA, FDA) highlighted three recurring serious events: hyperglycaemia, secondary infections and neuropsychiatric effects.
Australian ICU commentary (ANZICS) reinforced the need for close glucose and infection surveillance during systemic steroid use in critical care.
Meta‑analyses across 2022–2024 show harms rise with longer courses; therapy beyond two weeks is associated with dose‑dependent adverse outcomes.
The World Health Organization lists dexamethasone on the Essential Medicines List, reflecting its importance in selected acute settings.
For patients, the take‑home is straightforward: short, low‑dose courses can be lifesaving or symptom‑relieving in specific situations, but risks must be checked and recorded.
Always document shared decision‑making when considering prolonged therapy.
| Outcome | Effect Size / Finding | Certainty | Key Safety Observations |
|---|---|---|---|
| Mortality (Severe COVID‑19) | 6 mg daily reduced mortality in oxygen‑dependent hospitalised patients | High (RCT meta‑analysis) | Monitor hyperglycaemia; infection surveillance |
| Cerebral Oedema | Rapid symptom relief; standard regimens used in neurosurgical practice | Moderate | Metabolic effects; psychiatric changes at higher doses |
| Oncology Antiemetic Protocols | Effective as single or short course adjunct to reduce nausea | Moderate | Short courses generally safe; longer cycles require monitoring |
| Acute Inflammatory Flares | Reliable short‑term symptom relief (3–10 days) | Moderate | Hyperglycaemia common; infection risk with systemic use |
| Prolonged Therapy (>2 weeks) | Increased harms: osteoporosis, infections, adrenal suppression | High | Dose‑dependent harms; taper recommended |
Clinical Effectiveness In Australia
People want to know how dexamethasone is actually used in Australian hospitals and community settings.
Australian clinical audits and TGA safety reports show dexamethasone gives predictable anti‑inflammatory and immunosuppressive effects across indicated uses.
In hospitals, dexamethasone is standard for cerebral oedema, specific chemotherapy regimens and severe asthma exacerbations where IV or high‑dose oral routes are used.
In critical care for COVID‑19, Australian practice aligned with international trials using low‑dose 6 mg daily in oxygen‑dependent patients.
PBS and hospital funding differ by formulation and indication, and many parenteral and oncology uses are supplied through public hospitals rather than community PBS scripts.
TGA adverse event reporting continues to highlight metabolic and psychiatric events as leading causes of serious reports.
Clinicians should document indication, expected duration and a monitoring plan on the prescription to support continuity of care, especially for rural patients who may access hospital ampoules while community pharmacies supply oral formulations.
| Setting | Common Use Case | Typical Dosing | Monitoring Required |
|---|---|---|---|
| Hospital (Inpatient/ICU) | Cerebral oedema; severe asthma; COVID‑19 critical care; oncology IV regimens | 10 mg IV then 4 mg IV/IM q6h (cerebral oedema); 6 mg daily (COVID‑19) | Glucose, infection signs, BP, mental state |
| Community Pharmacy | Short oral courses for acute inflammation; ophthalmic drops; taper packs | 0.5–9 mg/day depending on indication; short courses 3–10 days | Diabetes review, BP, mood; advise GP if prolonged |
Indications And Expanded Uses
Patients often ask whether a use is approved or off‑label and what that means for safety.
TGA‑approved indications cover a broad range of inflammatory, allergic and endocrine disorders and many adjunct oncology uses, consistent with global practice.
Common TGA‑approved and widely accepted indications include cerebral oedema, severe asthma exacerbations, adrenal insufficiency replacement scenarios, certain autoimmune flares and antiemetic adjuncts in chemotherapy.
Evidence‑backed off‑label practices in Australia include single perioperative doses as part of antiemetic bundles and short courses for severe asthma flares.
Ophthalmology uses include topical drops and an implant (Ozurdex) for retinal inflammatory conditions, which are established treatments.
Oncology protocols may use high‑dose cyclical dexamethasone (for example 40 mg on specific days) as part of combination regimens.
Safety data supports short courses of 3–10 days for acute flares; prolonged therapy needs tapering and formal monitoring.
- TGA‑Approved/Established Uses: Cerebral oedema; severe asthma exacerbation; antiemetic adjunct in chemotherapy; selected endocrine and inflammatory disorders.
- Common Off‑Label But Evidence‑Backed Uses In Australia: Single perioperative dose for nausea prevention; short oral courses for acute flares; ophthalmic implant (Ozurdex) for retinal disease.
When care involves pregnant women or children, explain explicitly whether a use is off‑label and discuss risks versus benefits with the treating team.
Composition And Brand Landscape
Patients need to recognise packaging and strengths to avoid dosing errors.
The active ingredient is dexamethasone (INN) and the ATC classification is H02AB02.
In Australia, the active ingredient is marketed under brand names including Decadron, Dexasone, Hexadrol and the ophthalmic product Maxidex.
Generic suppliers include major international manufacturers and distributors, though specific Australian manufacturers are not specified in the available data.
Available forms and strengths from product information include tablets from 0.5 mg to 8 mg, oral solutions, injectables, ophthalmic drops 0.1% and the Ozurdex 700 mcg implant.
| Form | Common Strengths | Typical Packaging | Common Brands In Australia |
|---|---|---|---|
| Tablets | 0.5, 0.75, 1, 2, 4, 6, 8 mg | Blister packs of 10, 30, 100 | Decadron; Dexasone; Generic |
| Oral Solution | 0.5 mg/5 mL; 1 mg/mL; 4 mg/mL | Bottles with droppers | Generics |
| Injectable | 4 mg/mL; 10 mg/mL | 1 mL, 2 mL, 5 mL vials | Decadron vials; generics |
| Ophthalmic | 0.1% drops; 700 mcg implant | Dropper bottles; single‑use implant | Maxidex; Ozurdex |
Show patients the packaging and confirm the strength at dispensing because multiple tablet strengths are common and can cause confusion.
Contraindications And Special Precautions
Who should worry about taking dexamethasone and what monitoring is needed?
Absolute contraindications include known hypersensitivity to dexamethasone, systemic fungal infections and giving live vaccines during systemic therapy.
Relative contraindications that require careful assessment or monitoring include diabetes, peptic ulcer disease, uncontrolled infections, severe psychiatric illness, glaucoma and severe osteoporosis.
Some Australian populations have higher baseline risks that matter clinically.
For example, diabetes prevalence is higher in some Aboriginal and Torres Strait Islander communities and in rural areas, which increases the likelihood of steroid‑related hyperglycaemia and the need for glucose monitoring.
Dexamethasone crosses the placenta; use in pregnancy is reserved for situations where expected benefits outweigh risks and requires obstetric discussion.
Daily life precautions include caution with driving or machinery if sleep disturbances, severe mood changes or blurred vision occur, and workplace safety adjustments for physical roles if necessary.
- Known Hypersensitivity → Avoid completely → Document allergy and recommend alternative.
- Systemic Fungal Infection → Contraindicated → Treat infection first; avoid systemic steroids.
- Diabetes Mellitus → Risk of hyperglycaemia → Monitor capillary glucose, liaise with GP/diabetes team.
- Psychiatric Illness → Risk of mood/psychotic effects → Baseline mental health review and early follow‑up.
- Pregnancy → Crosses placenta → Use only when benefit outweighs risk; discuss with obstetrician.
Dosage Guidelines
Patients commonly ask, "How much should I take and for how long?"
Adult oral dosing varies widely by indication: typical anti‑inflammatory ranges are 0.5–9 mg/day, while severe cases and oncology protocols may reach higher doses or cyclical high‑dose regimens such as 40 mg on protocol days.
Cerebral oedema often begins with 10 mg IV then 4 mg IV/IM every six hours.
COVID‑19 critical care use standardised at 6 mg daily for up to 10 days in oxygen‑dependent patients.
Pediatric dosing is weight‑based, commonly 0.02–0.3 mg/kg/day depending on the indication.
Use the lowest effective dose and limit duration when possible, and taper after more than two weeks to avoid adrenal suppression.
| Indication | Typical Adult Dose | Pediatric Note | Monitoring |
|---|---|---|---|
| Acute Inflammation / Allergy | 0.5–9 mg/day oral; short course 3–10 days | 0.02–0.3 mg/kg/day | BP, glucose, mood |
| Cerebral Oedema | 10 mg IV then 4 mg IV/IM q6h | Lower per weight/age | Neurological status, glucose, infection |
| Oncology Antiemetic | 8–12 mg oral or IV for 1–4 days | Weight-based dosing | Blood glucose, infection signs |
| COVID‑19 (Severe) | 6 mg daily for up to 10 days | Adjusted in paediatrics | Oxygenation, glucose, infection |
Patient instructions: get a clear written dose schedule, take missed doses the same day if remembered, and never double doses.
If therapy is ongoing, never stop suddenly without medical advice.
Interactions Overview
Patients on multiple medicines need clear interaction checks before starting dexamethasone.
Dexamethasone is metabolised primarily via CYP3A4, so potent inducers like rifampicin and phenytoin can reduce steroid levels while inhibitors such as ketoconazole and some macrolide antibiotics can increase exposure.
Interactions with warfarin can cause INR variability, so more frequent monitoring is advised when steroids start or stop.
Steroids raise blood glucose and can blunt the effect of hypoglycaemic agents; glucose monitoring and possible dose adjustments for insulin or sulfonylureas are often necessary.
Live vaccines are contraindicated during systemic therapy; inactivated vaccines may be less effective, so immunisation timing should be discussed with the GP or immunisation clinic.
- High‑Risk Drug Interactions: Rifampicin, phenytoin → reduce effect; ketoconazole, clarithromycin → increase effect; warfarin → INR changes.
- Food/Drink Cautions: Alcohol increases GI and infection risks; caffeine may worsen insomnia.
- Monitoring Actions: Organise medication review, especially in elderly patients with polypharmacy, and consider a Home Medicines Review (HMR) if needed.
Cultural Perceptions And Patient Habits
People frequently tell pharmacists about worries over weight gain, mood swings and long‑term harms from steroids.
Australian forums and pharmacy consultations show strong trust in pharmacists for practical advice and price sensitivity when selecting brands or generics.
Rural patients often prefer tablets over injections and rely on telehealth and e‑scripts, with hospital clinics supplying injectables when needed.
Indigenous communities require culturally safe explanations about metabolic risks and how steroid treatment might affect chronic conditions like diabetes.
Urban patients often compare online and in‑store prices and may use telehealth providers for convenience.
- Common Patient Concerns: Weight gain, mood changes, long‑term effects, cost.
- Counselling Tips: Use plain language, visual dosing cards, involve the pharmacist in monitoring and provide a written plan.
- Rural Vs Urban: Rural access to injectables often via hospital; urban patients may access private telehealth and online pharmacies.
Availability And Pricing Patterns
Where and how patients buy dexamethasone varies across Australia.
Tablets and oral solutions are commonly stocked by major chains such as Chemist Warehouse, Priceline and TerryWhite Chemmart, while ophthalmic preparations like Maxidex are widely distributed.
Hospital supplies commonly cover injectables and oncology formulations and often bypass PBS listing because they are hospital‑funded.
PBS subsidy depends on formulation and indication and is not uniform across all strengths.
Private prices for generic tablets are generally low but vary between pharmacies and online stores, and consumers commonly compare specials.
| Pharmacy Channel | Typical Availability | Expected Private Price Range | PBS / Subsidy Notes |
|---|---|---|---|
| Major Chain Pharmacies | Tablets, oral solutions, ophthalmic drops | Low to moderate (varies by pack size) | Some formulations subsidised depending on indication |
| Hospital Pharmacy | Injectables, oncology supplies, ampoules | Usually hospital‑funded (no private charge) | Often hospital supplied; PBS not applicable for inpatient supply |
| Online Pharmacies / Telehealth | Tablets, arrange e‑prescriptions | Comparable to community pharmacy; specials available | Check PBS eligibility; e‑scripts accepted |
Patient tip: ask the pharmacist to check PBS eligibility and compare prices or ask about therapeutic substitution if cost is an issue.
In our online pharmacy, decadron is available without a prescription, with discreet delivery to Australia in 5–14 days.
Comparable Medicines And Preferences
Patients sometimes ask why one steroid is chosen over another.
Common alternatives include prednisone, methylprednisolone, hydrocortisone and betamethasone.
Dexamethasone is more potent and longer acting than prednisone and does not have significant mineralocorticoid activity, which makes it useful for cerebral oedema and certain antiemetic regimens.
Choice depends on indication, desired potency, dosing interval and side‑effect considerations.
In pregnancy, prednisone is often preferred for systemic maternal therapy because placental enzymes inactivate much of it, reducing foetal exposure compared with dexamethasone.
- Prednisone → Preferred for some systemic maternal therapy; easier placental inactivation.
- Methylprednisolone → Useful IV option with intermediate potency.
- Hydrocortisone → Lower potency, useful for adrenal replacement.
- Betamethasone → Similar potency to dexamethasone; choices often protocol driven.
Explain to patients why one steroid is selected, including expected side effects and monitoring plans.
Frequently Asked Questions
- Is dexamethasone safe long term?
Long‑term use beyond two weeks increases risk of osteoporosis, hyperglycaemia, infections and adrenal suppression.
Longer therapy requires tapering and monitoring of bone health, glucose and blood pressure.
- Can I drive while taking dexamethasone?
Most people can drive, but avoid driving or operating heavy machinery if you have dizziness, severe mood changes, insomnia or visual disturbance.
- Will PBS cover my dexamethasone?
Coverage depends on formulation and indication; check the PBS schedule or ask your pharmacist, as hospital oncology supplies are often funded through hospitals rather than community PBS.
- Can I have vaccines while on dexamethasone?
Avoid live vaccines during systemic therapy; inactivated vaccines may be less effective, so discuss timing with your GP or immunisation clinic.
Guidelines For Proper Use
Good counselling prevents errors and supports safer use of dexamethasone.
National guidance from regulatory authorities and specialist colleges emphasises using the lowest effective dose, limiting duration and avoiding abrupt cessation after more than two weeks.
Pharmacist counselling checklist for Australia:
- Confirm the indication and expected duration as written on the script.
- Review comorbidities such as diabetes, hypertension, osteoporosis and psychiatric history.
- Explain the dosing schedule clearly, including timing (morning dosing to reduce insomnia where appropriate).
- Explain the need to taper after prolonged therapy and provide written taper instructions if required.
- Advise on common side effects and red flags that need urgent care (severe mood changes, hyperglycaemia, signs of serious infection).
- Check for drug interactions (CYP3A4 inducers/inhibitors, warfarin, hypoglycaemic agents) and arrange monitoring.
- Document PBS eligibility and supply options; for rural patients confirm the pharmacy or hospital supply route and consider follow‑up call.
Provide a written dosing card and offer a follow‑up phone check 48–72 hours after starting systemic therapy for high‑risk patients.
Delivery Across Australia
| City | Region | Delivery time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Darwin | Northern Territory | 5-9 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Geelong | Victoria | 5-9 days |
| Newcastle | New South Wales | 5-9 days |
| Wollongong | New South Wales | 5-9 days |
| Sunshine Coast | Queensland | 5-9 days |
| Townsville | Queensland | 5-9 days |
| Ballarat | Victoria | 5-9 days |